
High chromogranin A alone does not mean you have a neuroendocrine tumor. Acid-suppressing medicines, reduced kidney function, and the laboratory method can change the result—and the safest next step depends on why the test was ordered.

ძირითადი დასკვნები
- One elevated result cannot diagnose a neuroendocrine tumor, identify its location, or determine its stage.
- PPI effects can be substantial: a small prospective study reassessed chromogranin A after 2 weeks of clinician-directed acid-suppression changes.
- თირკმლის ფუნქცია matters because reduced renal clearance can raise chromogranin A; an eGFR below 30 mL/min/1.73 m² makes interpretation especially difficult.
- საცნობი ლიმიტები are assay-specific: a hypothetical result of 300 ng/mL with an upper limit of 100 ng/mL equals 3 times that laboratory’s limit, not a cancer diagnosis.
- False-positive interpretation is common in selected referral populations: one study reported an 11% positive predictive value for elevated chromogranin A.
- Hormone secretion tests answer different questions: a 24-hour urine 5-HIAA collection assesses a serotonin metabolite, not chromogranin A.
- განმეორებითი ტესტირება should use the same laboratory method where possible, with medication changes approved by the prescribing clinician.
- სასწრაფო სიმპტომები override the marker: glucose below 54 mg/dL, or 3.0 mmol/L, with confusion or collapse needs immediate assessment.
Does high chromogranin A mean a neuroendocrine tumor?
High chromogranin A does not, by itself, diagnose a neuroendocrine tumor or cancer. Proton pump inhibitors, reduced kidney function, and stomach conditions can increase the concentration; conversely, some neuroendocrine tumors produce little measurable chromogranin A, so neither 1 high result nor 1 normal result settles the diagnosis.

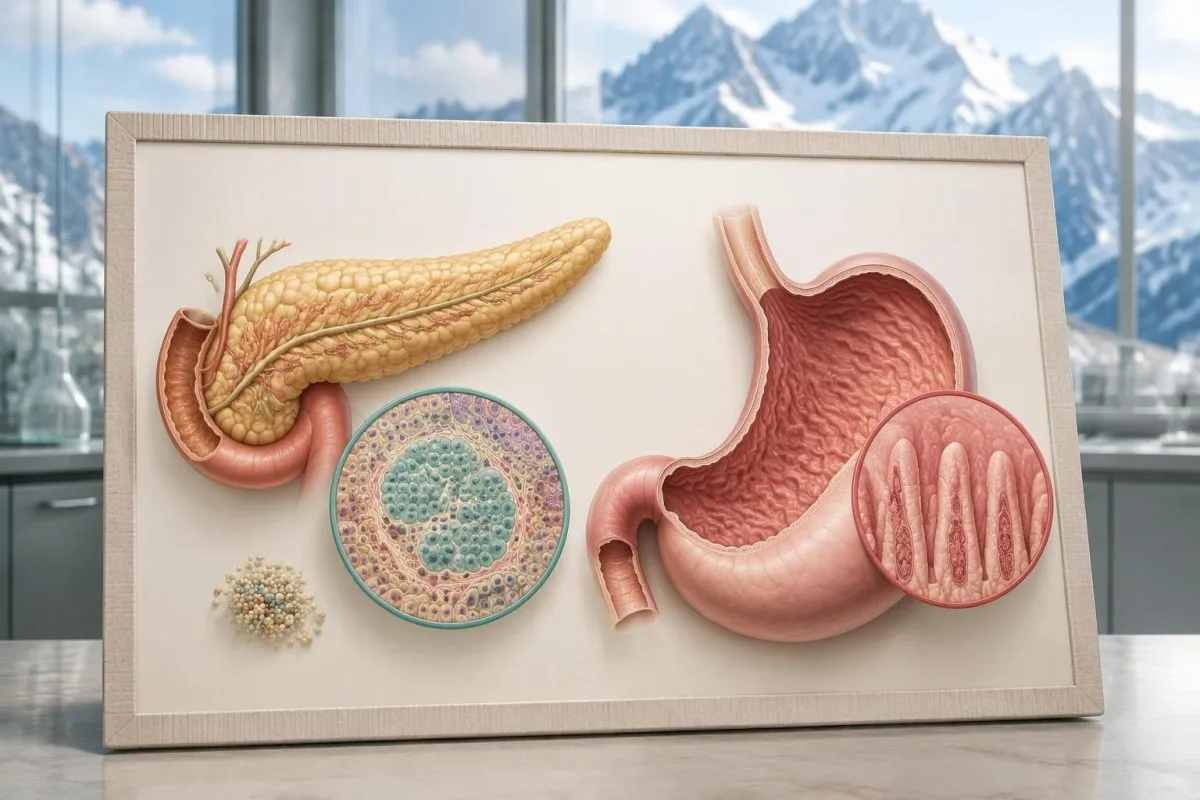
Chromogranin A, often abbreviated CgA, is a protein stored in the secretory granules of neuroendocrine cells, including cells in the digestive tract and pancreas. A circulating concentration measures protein released into the circulation—not a count of cancer cells—and a result of 500 ng/mL cannot reveal whether its source is a medicine effect, impaired clearance, or a growth.
კანტესტი არის AI სისხლის ტესტის ანალიზატორი that helps explain why 1 chromogranin A result needs its laboratory limit, medication history, and kidney measurements alongside it. We separate an abnormal marker from a confirmed diagnosis; the same distinction prevents misunderstandings with other nonspecific tumor markers.
A clearly hypothetical example shows the problem: 2 people each have CgA of 300 ng/mL, but one takes omeprazole and has no concerning symptoms, while the other has an unexplained pancreatic mass. The identical number leads to different investigations because imaging findings and clinical probability carry information that CgA alone cannot supply.
How high is high—and is there a cancer cutoff?
Chromogranin A has no universal reference range or cancer-diagnostic cutoff. Laboratories use different antibodies, calibration systems, and sometimes different units; a hypothetical result of 300 ng/mL with an upper reference limit of 100 ng/mL is 3 times the upper limit, but that ratio is not a validated cancer threshold.

The upper reference limit belongs to the assay on your report. One laboratory’s ng/mL result should not be compared numerically with another laboratory’s nmol/L result without a validated conversion, and even 2 laboratories reporting ng/mL may detect different protein fragments; using a universal online range can therefore manufacture an apparent change.
For example, an entirely hypothetical change from 180 ng/mL at a laboratory with a 90 ng/mL limit to 210 ng/mL at a laboratory with a 150 ng/mL limit looks like an increase in the raw concentration. Expressed relative to each limit, it changes from 2 times to 1.4 times; neither comparison proves a biological improvement because the methods differ.
A very large elevation deserves explanation, not automatic staging. There is no reliable rule that 5 times or 10 times the upper limit confirms metastases, especially with PPI exposure or advanced kidney impairment; our explanation of CA 19-9 interpretation limits addresses the related mistake of treating a marker’s height as a diagnosis.
| დონე | დიაპაზონი | მნიშვნელობა |
|---|---|---|
| Within the illustrative limit | ≤100 ng/mL | Hypothetical assay only; a result within range does not exclude a neuroendocrine tumor. |
| Above the illustrative limit | >100–300 ng/mL | Hypothetical 1–3× upper-limit band; review medicines, kidney function, and the reason for testing. |
| Several times the illustrative limit | >300–1,000 ng/mL | Hypothetical >3–10× band; these are explanatory categories, not validated diagnostic thresholds. |
| Marked illustrative elevation | >1,000 ng/mL | Hypothetical >10× band; substantial non-tumor elevations remain possible, and urgency depends on symptoms. |
Why do omeprazole and other PPIs raise chromogranin A?
Omeprazole and other proton pump inhibitors can raise chromogranin A by reducing stomach acid and increasing gastrin stimulation of gastric enterochromaffin-like cells. This is a biological increase rather than necessarily a laboratory error; even a commonly prescribed dose such as omeprazole 20 mg daily can be relevant to interpretation.
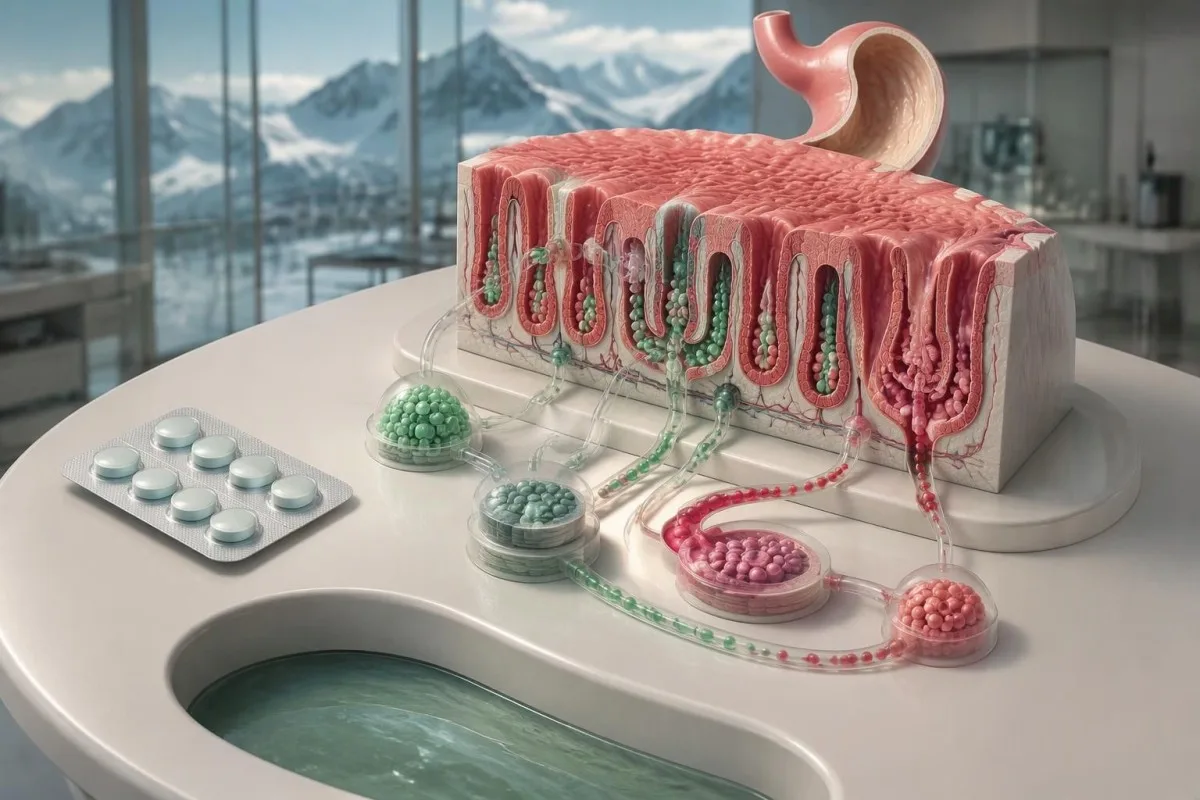
PPI-related CgA elevations may be several-fold, and their size does not reliably identify who has an underlying tumor. Omeprazole, esomeprazole, pantoprazole, lansoprazole, and related medicines belong on the medication list; a hypothetical rise from 100 to 600 ng/mL cannot be dismissed or diagnosed solely from its magnitude.
In a prospective study of 196 patients with neuroendocrine tumors, Korse et al. identified 19 with unexpectedly elevated CgA, all taking PPIs, and repeated measurements after 2 weeks of stopping or replacing the PPI under supervision. The group stopping all acid inhibition had an 82% reduction, illustrating a substantial drug effect—not an 82% reduction in cancer risk (Korse et al., 2011).
Gastrin and CgA can rise together during acid suppression, so ordering gastrin without documenting the PPI may create a second confusing result rather than resolve the first. Record the exact medicine, daily dose in mg, and last dose; our guide to PPI-related high gastrin explains why high gastrin also needs an acid-suppression history.
Should you stop omeprazole before a repeat test?
Do not stop omeprazole or another PPI solely because chromogranin A is elevated without speaking to the prescriber. A clinician may arrange a washout of approximately 2 weeks when safe, but the appropriate interval and any temporary alternative depend on the indication, symptoms, and laboratory instructions.

Stopping acid suppression can be unsafe in selected patients, particularly when severe acid hypersecretion is suspected or protection against gastrointestinal complications remains necessary. A 14-day pause is therefore a possible testing plan, not a universal self-care instruction; the clinician may instead interpret CgA on treatment or prioritize a different investigation.
An H2-receptor blocker may sometimes provide temporary symptom control, but it is not automatically free of effects on gastrin or CgA. Some laboratories request a further short interruption before sampling, while others use different protocols; ask for 1 written plan specifying the replacement medicine, timing, and what to do if symptoms return.
Rebound acid symptoms can follow PPI withdrawal, and they do not by themselves prove a gastrinoma or another neuroendocrine tumor. If a hypothetical 52-year-old develops heartburn during an approved 2-week pause, the practical response is to contact the prescriber rather than extend the pause indefinitely; reflux warning signs help distinguish routine symptoms from problems needing prompt care.
How does reduced kidney function affect chromogranin A?
Reduced kidney function can increase chromogranin A because renal handling and clearance of the protein and its fragments are impaired. The problem becomes especially pronounced in advanced kidney impairment, including an eGFR below 30 mL/min/1.73 m²; no universally accepted correction formula converts that result into a tumor-specific concentration.
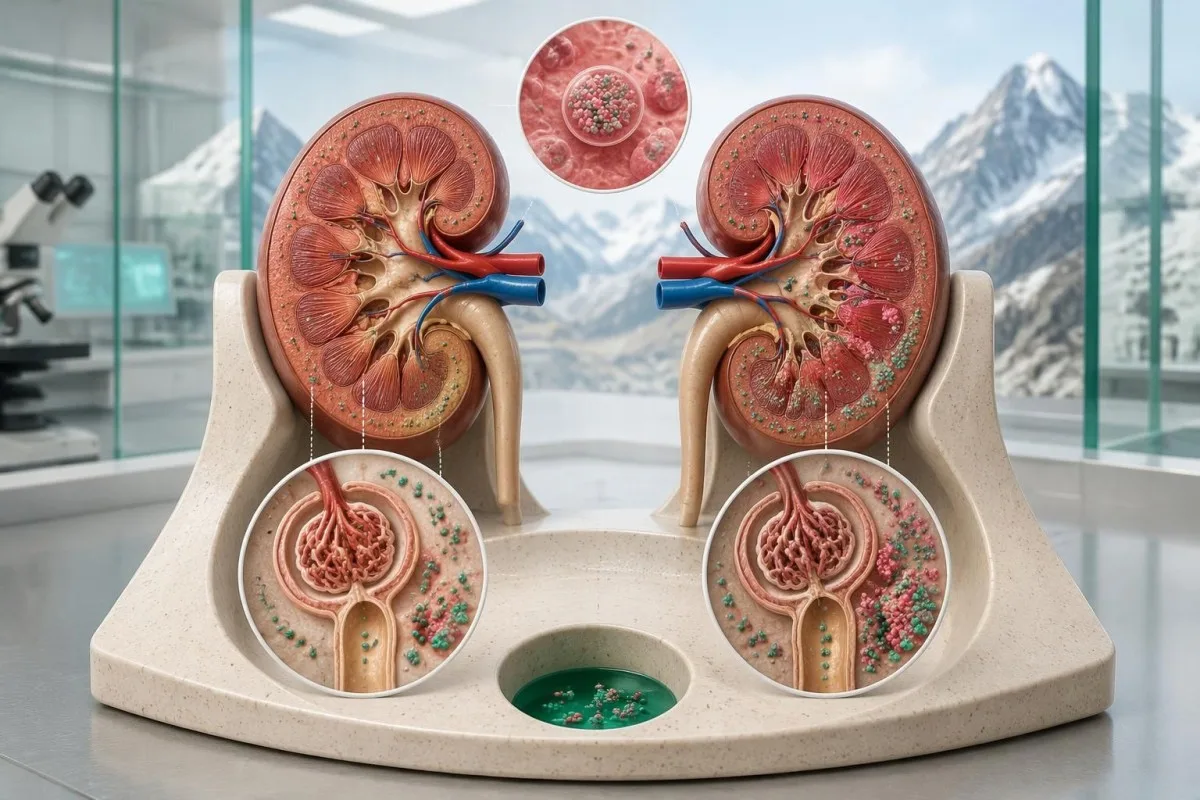
Creatinine and eGFR from near the sampling date are more useful than an old normal kidney result. An eGFR of 28 mL/min/1.73 m² and an eGFR of 85 mL/min/1.73 m² provide very different backgrounds for the same CgA concentration; Tramonti et al. documented the relationship between worsening renal function and higher circulating CgA (Tramonti et al., 2001).
A temporary kidney problem also matters: a creatinine rise of at least 0.3 mg/dL, approximately 26.5 µmol/L, within 48 hours meets one standard acute kidney injury criterion. CgA measured during acute illness may not represent a stable baseline, so reviewing hydration, recent illness, and low eGFR warning symptoms can change the timing and priority of follow-up.
Kantesti AI explains kidney context rather than mathematically subtracting a presumed renal contribution from CgA. If a hypothetical CgA of 700 ng/mL accompanies eGFR of 24 mL/min/1.73 m², both kidney-related elevation and a separate neuroendocrine condition remain possible; the BUN და კრეატინინის სახელმძღვანელო clarifies why no single renal measurement answers every clearance question.
What other conditions can elevate chromogranin A?
Atrophic gastritis, reduced stomach acid, and some other systemic illnesses can elevate chromogranin A without establishing a neuroendocrine tumor. A useful review starts with 3 contextual areas—acid suppression, kidney function, and gastric disease—rather than an indiscriminate search through every rare association reported for this nonspecific marker.
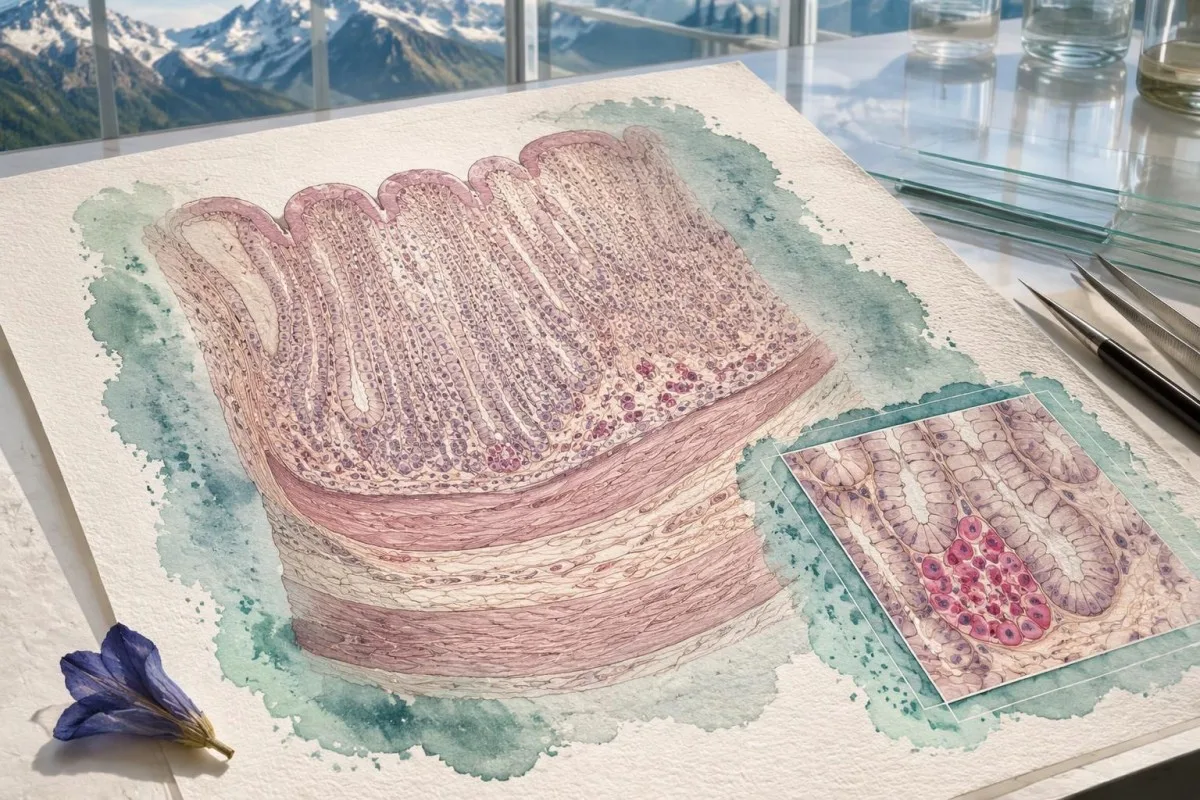
Autoimmune atrophic gastritis can raise both gastrin and CgA, because loss of acid-producing cells removes normal feedback on gastrin secretion. A concurrent vitamin B12 deficiency or iron deficiency provides a reason to investigate the stomach rather than order tumor imaging from 1 marker alone; პერნიციოზული ანემიის ტესტირება explains the autoimmune context.
Gastric endocrine-cell stimulation is not always a harmless endpoint: autoimmune atrophic gastritis can also predispose to type 1 gastric neuroendocrine tumors. That possibility means a convincing gastric explanation does not automatically close the case; endoscopy decisions should reflect the gastric diagnosis, symptoms, and previous findings, not a universal CgA cutoff.
Heart failure, liver dysfunction, and other illnesses have also been associated with elevated CgA, but these associations are less useful than a documented medication or renal explanation. If 2 accompanying findings—such as anemia and low B12—point toward impaired absorption, clinicians may prioritize that pathway; a ზღვრულ B12 შეფასებას can help identify what additional evidence is needed.
How should a clinician-directed repeat test be prepared?
A reliable repeat chromogranin A test uses comparable laboratory methods and documents medication exposure, kidney function, and sample preparation. When a safe PPI washout is chosen, approximately 2 weeks is a common starting interval, but the laboratory and clinician should specify the actual protocol rather than leaving preparation to guesswork.

Follow the laboratory’s fasting and collection instructions, because CgA protocols and accepted specimen types differ. If the laboratory requests an 8–12-hour fast, confirm whether water and essential medicines are permitted; neither that fasting interval nor a particular tube type should be assumed to apply to every assay.
A preparation note should contain at least 4 items: the exact CgA result and reference limit, the assay laboratory, acid-suppressing medicines with last-dose timing, and recent creatinine or eGFR. Add somatostatin-analogue treatment and other relevant therapies if there is an established neuroendocrine tumor, because treatment context changes what a repeat result means.
Repeat testing should have a question attached to it, such as whether an approved medication change removes an unexplained elevation. Repeating the same confounded test 3 times without changing the clinical context usually adds little; our პირველი ჩასხმის მომზადების ჩამონათვალი provides a practical way to record conditions before the appointment.
What does a falling or persistently high repeat result mean?
A fall after a clinician-approved PPI change supports a medication contribution, while persistent elevation requires reassessment of remaining explanations. Neither pattern proves or excludes a neuroendocrine tumor; even a hypothetical 80% fall must be interpreted alongside kidney function, symptoms, assay consistency, and the original reason for testing.

Consider a clearly hypothetical result that falls from 600 to 120 ng/mL after an approved 2-week PPI interruption, with an assay limit of 100 ng/mL and stable normal kidney function. The large decline strongly supports a PPI effect, but the remaining small elevation may reflect biological variation or another contributor; the next decision depends on clinical suspicion, not a demand for numerical perfection.
Persistent CgA elevation is not synonymous with persistent cancer. If another hypothetical result remains 450 ng/mL while eGFR is 22 mL/min/1.73 m², renal confounding remains unresolved; if the same concentration persists without an identifiable contributor and an unexplained mass is present, further investigation has a stronger rationale.
კანტესტი არის AI სისხლის ანალიზის განმარტების პლატფორმა that organizes CgA trends together with medication dates and kidney results, rather than treating 2 concentrations as a diagnosis. Our discussion of medication-aware result trends explains why a treatment change, assay change, or intercurrent illness can be more informative than the direction of the line.
How is chromogranin A different from hormone secretion tests?
Chromogranin A is a general neuroendocrine secretory-granule marker, not a test of one specific hormone syndrome. A 24-hour urine 5-HIAA test evaluates a serotonin metabolite, metanephrines assess catecholamine production, and appropriately timed insulin-related tests investigate hypoglycemia; these tests answer different questions and are not interchangeable.
A nonfunctioning neuroendocrine tumor may not cause a recognizable hormone-excess syndrome, even if it releases CgA. Conversely, hormone symptoms deserve targeted investigation even with 1 normal CgA result; deciding whether a growth exists and deciding whether it secretes a biologically active hormone are related but separate tasks.
For suspected serotonin-related carcinoid syndrome, clinicians may request urinary or plasma 5-HIAA, with availability and reference ranges depending on the laboratory. A 24-hour urine collection must be complete, and laboratories often specify food and medication precautions for roughly 2–3 days; the 5-HIAA collection and interpretation guide explains why preparation affects that different marker.
Plasma free or urinary fractionated metanephrines are the usual biochemical tests when pheochromocytoma is suspected, rather than CgA alone. For plasma sampling, many protocols use 20–30 minutes of supine rest to reduce false positives; a clinician can adapt collection safely, while our pheochromocytoma symptom guide explains which symptom patterns justify that pathway.
When are insulin, proinsulin, or gastrin tests appropriate?
Insulin-related testing is appropriate when documented hypoglycemia suggests inappropriate insulin secretion, while gastrin testing requires an acid-related clinical question. Glucose below 54 mg/dL, or 3.0 mmol/L, is clinically significant, but insulin, C-peptide, and proinsulin must be interpreted with the simultaneous glucose rather than with chromogranin A alone.
A high fasting insulin concentration at normal or high glucose does not establish an insulinoma. During a genuine hypoglycemic episode, clinicians may measure glucose, insulin, C-peptide, proinsulin, beta-hydroxybutyrate, and screen for relevant glucose-lowering medicines; a supervised fast can last up to 72 hours in selected investigations and should never be attempted at home.
A clearly hypothetical glucose of 45 mg/dL, approximately 2.5 mmol/L, with insulin that has not appropriately suppressed raises a different question from a CgA of 250 ng/mL. The insulin result concerns inappropriate hormone action during low glucose, whereas CgA remains nonspecific; the proinsulin and insulinoma workup explains why simultaneous samples are necessary.
Gastrin above 10 times an assay’s upper limit together with gastric pH of 2 or lower can support Zollinger–Ellison syndrome in the appropriate specialist evaluation. Gastrin elevation without acid-status assessment is less specific, especially during PPI treatment; arranging that evaluation may require monitored medication changes because uncontrolled acid hypersecretion can be dangerous.
When does elevated chromogranin A justify further investigation?
Further investigation is most appropriate when elevated chromogranin A accompanies a suspicious structural finding, a convincing hormone syndrome, or persistent unexplained elevation after confounders are reviewed. There is no single ng/mL threshold that mandates a scan; the clinical pattern determines whether repeat testing, specialist review, or imaging should come first.
Persistent watery diarrhea with recurrent flushing is more suggestive of a secretory syndrome than either symptom alone, but common gastrointestinal conditions remain possible. Symptoms lasting several weeks, unexplained weight loss, or an abdominal mass strengthen the case for assessment; visible blood in stool requires its own pathway, as explained in our stool-color urgency guide.
In a referral study of 197 patients investigated for possible neuroendocrine tumors, 167 had elevated CgA and only 19 of those had a confirmed tumor, giving a positive predictive value of approximately 11%. That finding reflects one selected population and its testing practices, not every patient’s personal probability, but it demonstrates the limits of CgA-led investigation (Baekdal et al., 2020).
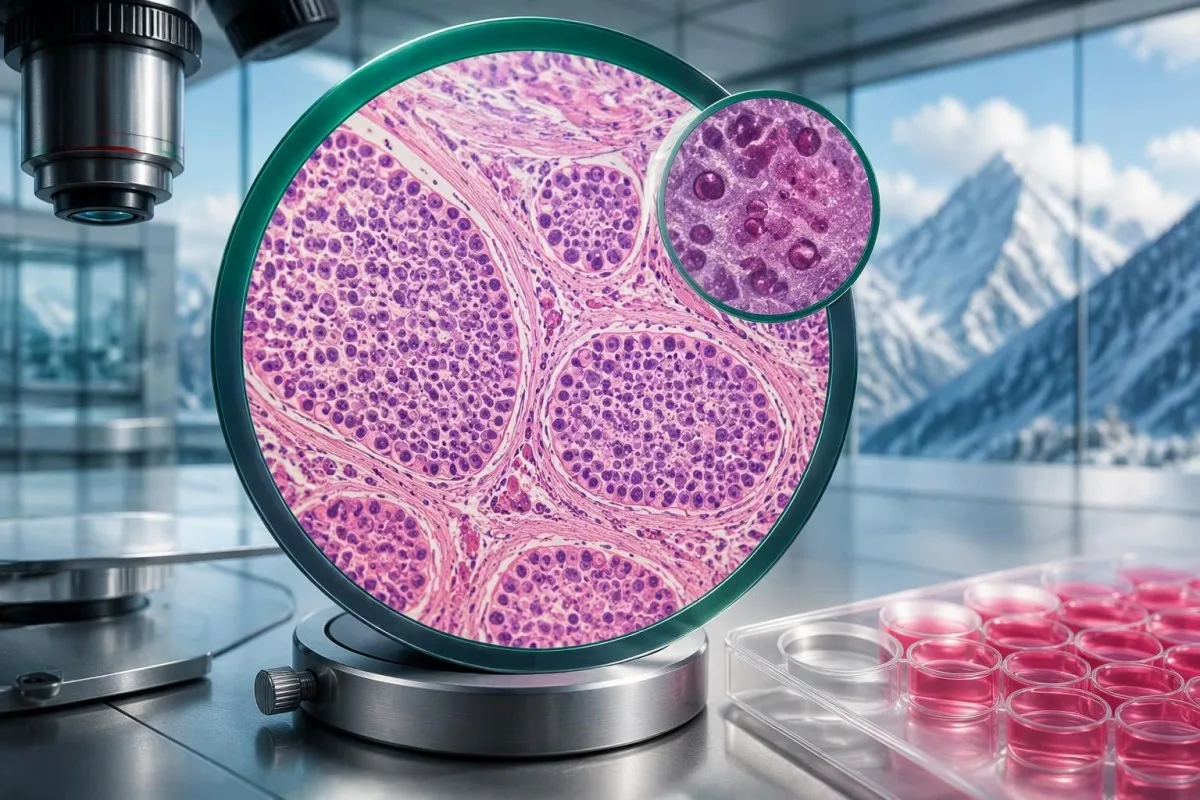
Kantesti AI presents an isolated high CgA result as a discussion point, not an instruction to obtain a whole-body scan. Depending on the suspected site, a specialist may select contrast CT, MRI, endoscopy, or somatostatin-receptor PET; receptor imaging is not a universal first test for 1 unexplained marker, and tissue examination commonly establishes the diagnosis and grade.
Is chromogranin A more useful after a tumor is diagnosed?
Chromogranin A may help monitor an established neuroendocrine tumor when it was elevated at baseline and remains interpretable, but it should not replace imaging or clinical assessment. A change between 2 measurements can reflect treatment, medication exposure, kidney function, or assay differences rather than a change in tumor burden.
A marker that was normal before treatment is usually a weak stand-alone monitoring tool for that individual. For example, a hypothetical person with biopsy-confirmed disease and baseline CgA of 70 ng/mL against a 100 ng/mL limit may need follow-up guided primarily by imaging, symptoms, and tumor-specific findings rather than repeated attempts to make CgA informative.
A hypothetical fall from 900 to 450 ng/mL is a 50% decrease, but it cannot be labeled a 50% reduction in tumor size. Tumor-directed therapy can alter secretion, and changing a PPI can alter CgA independently; the measurement describes concentration, while imaging evaluates structural response under its own criteria.
Small fluctuations should not automatically trigger treatment changes. A hypothetical rise from 110 to 125 ng/mL is approximately 14%, and its significance depends on analytical variation, biological variation, and the broader trend; our guide to მნიშვნელოვანი ცვლილებები ვიზიტებს შორის explains why a percentage alone does not establish progression.
What can AI interpretation add—and what can it not do?
AI interpretation can organize chromogranin A alongside its units, reference limit, kidney results, and medication context, but it cannot diagnose or exclude a neuroendocrine tumor. A report showing 300 ng/mL against a 100 ng/mL limit supports a 3-times-upper-limit calculation; deciding what caused that elevation requires clinical assessment.
კანტესტი არის AI ბიომარკერების ინტერპრეტაციის პლატფორმა that helps explain CgA results together with related laboratory findings and user-provided context. If a PDF is missing its reference limit or a medicine has not been entered, that missing information should remain explicit rather than being guessed; our AI ინტერპრეტაციის ტექნოლოგია describes the interpretation workflow.
Technical performance and diagnostic certainty are different claims. Correctly extracting 1 concentration from a report does not prove that the system can identify its biological cause, and a benchmark cannot substitute for examination or pathology; our ვალიდაციისა და კლინიკური ზედამხედველობის information explains how to evaluate methodology without treating it as a cancer-detection guarantee.
Kantesti recommends checking at least 3 source details before acting on an explanation: the marker name, the measurement units, and the laboratory’s own reference interval. Medication dates and symptoms should then be discussed with the clinician; our კონფიდენციალურობისა და მონაცემთა დამუშავების პრაქტიკა explain handling of the sensitive information used to provide that context.
What should you ask next—and which sources support this advice?
The practical next step is to ask why chromogranin A was ordered, whether a confounder is present, and what a repeat or additional test would change. Bring 4 essentials—the full laboratory report, medication list, recent kidney results, and symptom timeline—so follow-up is directed at a clinical question rather than the abnormal flag.
An isolated CgA elevation is usually a follow-up issue rather than an emergency, but severe symptoms should not wait for a repeat marker. Confusion or collapse with glucose below 54 mg/dL, or 3.0 mmol/L, severe breathing difficulty, major gastrointestinal bleeding, or sudden severe abdominal pain requires urgent care; ask the clinician what symptoms should change your own plan.
Kantesti Ltd is the UK organization behind this educational content, with Company No. 17090423; our ორგანიზაცია და მიზანი provide company context rather than clinical proof. Our სამედიცინო შინაარსის სტანდარტები describe the distinction between patient education, technical interpretation, and decisions that need an appropriately qualified treating professional.
The 3 external references listed below support the CgA-specific discussion of PPI effects, diagnostic limitations, and renal function. The 2 separate repository publications concern Nipah testing and hematology education, not chromogranin A or neuroendocrine diagnosis; their DOI registrations provide publication identifiers, not evidence for this article’s clinical conclusions or proof of peer review.
ხშირად დასმული კითხვები
შეიძლება თუ არა ქრომოგრანინ A-ს მაღალი დონე ომეპრაზოლით იყოს გამოწვეული?
ომეპრაზოლმა შეიძლება გაზარდოს ქრომოგრანინ A კუჭის მჟავას სეკრეციის დათრგუნვისა და გასტრინის მიერ კუჭის ენდოკრინული უჯრედების სტიმულაციის გაძლიერების გზით. შედეგის ინტერპრეტაციისას უნდა აღირიცხოს თუნდაც ხშირად დანიშნული დოზა, მაგალითად, 20 მგ დღეში; მომატების სიდიდე კი საიმედოდ ვერ განასხვავებს მედიკამენტის ეფექტს სიმსივნისგან. მცირე პერსპექტიულ კვლევაში ქრომოგრანინ A ხელახლა შეამოწმეს PPI-ის ცვლილებებიდან 2 კვირის შემდეგ, რომლებიც კლინიცისტის მითითებით განხორციელდა, და მაჩვენებლის მნიშვნელოვანი შემცირება დაფიქსირდა. ომეპრაზოლის მიღება არ შეწყვიტოთ გამომწერის რჩევის გარეშე.
ქრომოგრანინ A-ის რა დონე მიუთითებს კიბოზე?
ქრომოგრანინ A-ს არცერთი კონცენტრაცია საიმედოდ ვერ ადგენს კიბოს დიაგნოზს თავისთავად. ჰიპოთეტური შედეგი — 300 ნგ/მლ, როდესაც ლაბორატორიის ზედა ზღვარი 100 ნგ/მლ-ია — ამ ტესტის ზღვარს 3-ჯერ აღემატება, თუმცა მედიკამენტებმა და თირკმლის ფუნქციის დაქვეითებამაც შეიძლება კონცენტრაცია რამდენჯერმე გაზარდოს. სხვადასხვა ტესტს განსხვავებული საცნობარო ზღვრები აქვს და ისინი ყოველთვის ურთიერთჩანაცვლებადი არ არის. ნეიროენდოკრინული სიმსივნის დიაგნოზის დასასმელად საჭიროა შესაბამისი კლინიკური გამოკვლევა, რომელიც ხშირად მოიცავს ვიზუალიზაციასა და ქსოვილის გამოკვლევას.
Can kidney disease cause elevated chromogranin A?
Reduced kidney function can elevate chromogranin A because renal clearance and handling of the protein and its fragments are impaired. Interpretation becomes particularly difficult with advanced impairment, including eGFR below 30 mL/min/1.73 m². There is no universally accepted formula that removes the renal contribution and leaves a tumor-specific result. A clinician should review contemporaneous creatinine, eGFR, medication exposure, and the reason for testing.
How long should I be off PPIs before repeating chromogranin A?
Approximately 2 weeks is a commonly used starting interval for clinician-directed PPI withdrawal before repeat chromogranin A testing, but it is not a universal rule. The laboratory method, duration of acid suppression, original result, and reason for treatment can change the plan. Some people need a longer reassessment interval or should not interrupt acid suppression at all. Ask the prescribing clinician for written instructions, including any temporary alternative and when to seek help for returning symptoms.
Does a normal chromogranin A rule out a neuroendocrine tumor?
A normal chromogranin A result does not rule out a neuroendocrine tumor because some tumors release little measurable CgA. For example, a hypothetical result of 70 ng/mL within an assay limit of 100 ng/mL cannot cancel out a suspicious pancreatic mass or a convincing hormone syndrome. Hormone-specific testing, imaging, and sometimes tissue examination answer different diagnostic questions. The significance of a normal result depends on what prompted testing.
Is chromogranin A the same as the 5-HIAA test?
Chromogranin A and 5-HIAA measure different substances: CgA is a neuroendocrine secretory-granule protein, while 5-HIAA is a serotonin metabolite. A 24-hour urine 5-HIAA collection may help investigate serotonin-related carcinoid syndrome, with preparation and reference limits set by the laboratory. CgA does not establish that serotonin or another hormone is being secreted in excess. Neither test should be treated as a stand-alone cancer diagnosis.
მიიღეთ სისხლის ანალიზის შედეგების ახსნა
ატვირთეთ თქვენი ლაბორატორიული ანგარიში და Kantesti-ის AI რამდენიმე წამში თითოეულ ბიომარკერს მარტივი ენით აგიხსნით. მას მსოფლიოში 2 მილიონზე მეტი ადამიანი იყენებს.
ცნობები
- Klein, T., Mitchell, S., & Weber, H. (2026). ნიპას ვირუსის სისხლის ტესტი: ადრეული გამოვლენისა და დიაგნოსტიკის გზამკვლევი 2026. Kantesti AI-ის სამედიცინო კვლევა. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). სისხლის B უარყოფითი ჯგუფის, LDH-ის სისხლის ანალიზისა და რეტიკულოციტების რაოდენობის განსაზღვრის გზამკვლევი. Kantesti AI-ის სამედიცინო კვლევა. DOI
- Korse CM et al. (2011). Discontinuation of proton pump inhibitors during assessment of chromogranin A levels in patients with neuroendocrine tumours. British Journal of Cancer. DOI
- Baekdal MF et al. (2020). Limited Diagnostic Utility of Chromogranin A Measurements in Workup of Neuroendocrine Tumors. Diagnostics. DOI
- Tramonti G et al. (2001). Relationship between renal function and blood level of chromogranin A. Renal Failure. PubMed
- 2 მილიონი+გაანალიზებული ტესტები
- 127+ქვეყნები
- 100+ენები
სამედიცინო გუნდის შესახებ


E-E-A-T სანდოობის სიგნალები
გამოცდილება
ექიმის ხელმძღვანელობით კლინიკური მიმოხილვა ლაბორატორიული ინტერპრეტაციის სამუშაო პროცესებზე.
ექსპერტიზა
ლაბორატორიული მედიცინის აქცენტი იმაზე, როგორ იქცევიან ბიომარკერები კლინიკურ კონტექსტში.
ავტორიტეტულობა
სამედიცინო თვალსაზრისით რეცენზირებულია დოქტორ თომას კლაინის მიერ, დოქტორ სარა მიტჩელისა და პროფესორ ჰანს ვებერის მონაწილეობით.
სანდოობა
მტკიცებულებებზე დაფუძნებული ინტერპრეტაცია, მკაფიო შემდგომი ნაბიჯებით, რათა შემცირდეს განგაშის დონე.






სამედიცინო პასუხისმგებლობის შეზღუდვის განცხადება
ეს სტატია მხოლოდ საგანმანათლებლო მიზნებისთვისაა და არ წარმოადგენს სამედიცინო რჩევას. დიაგნოზისა და მკურნალობის გადაწყვეტილებებისთვის ყოველთვის მიმართეთ კვალიფიციურ ჯანდაცვის სპეციალისტს.
გამოქვეყნდა · დაუკავშირდით სარედაქციო გუნდს
გამოქვეყნებულია Kantesti Ltd-ის მიერ, რეგისტრირებულია ინგლისსა და უელსში, კომპანიის №. 17090423, ლონდონი, გაერთიანებული სამეფო.
