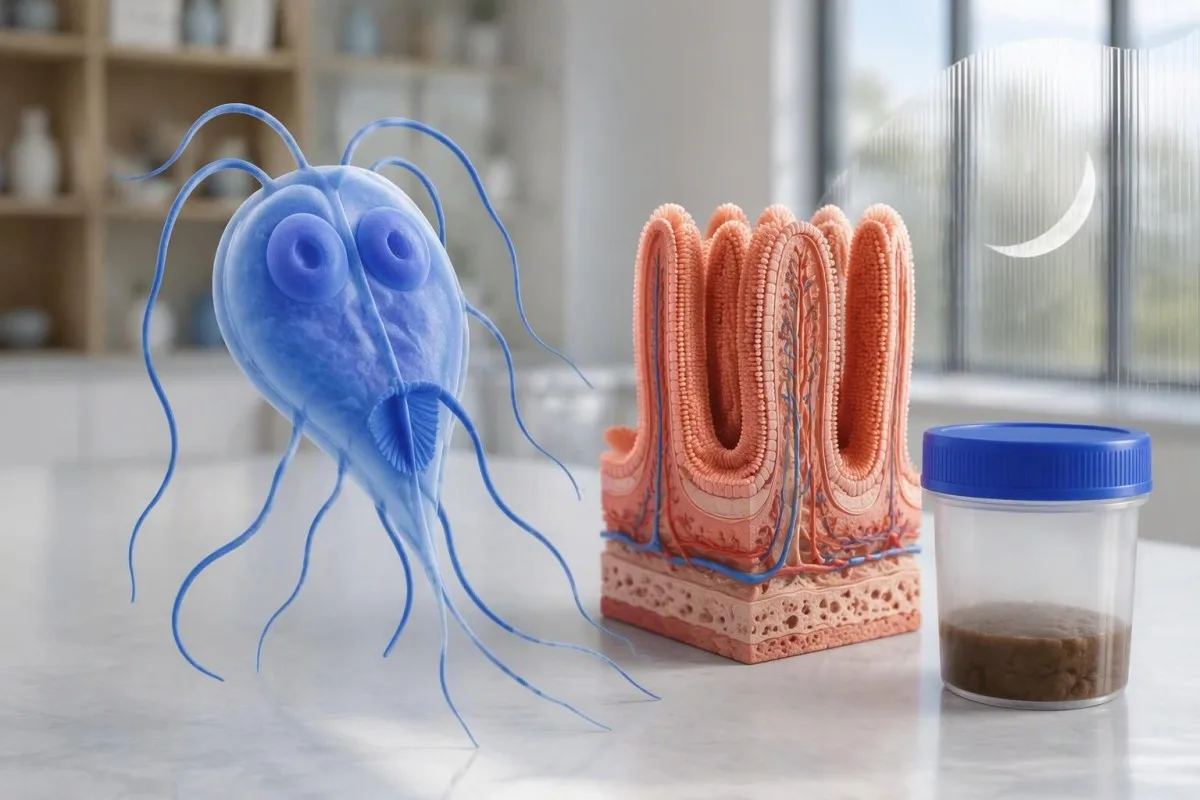
A positive stool antigen usually supports giardiasis, but treatment response and digestive recovery follow different timelines. Here is how clinicians separate ongoing infection from a gut that is still healing.



- Detected antigen means Giardia proteins were identified in stool; it usually supports infection but does not measure parasite burden or illness severity.
- Treatment selection depends on symptoms, age, pregnancy, previous medicines, and availability—not the strength of a positive antigen result.
- チニダゾール is commonly prescribed to adults as a single 2 g dose with food; it requires a prescription and an individual safety assessment.
- Illness duration is commonly 2–6 weeks without treatment, although untreated infection can last longer and symptoms may fluctuate.
- Digestive recovery can lag behind parasite clearance because temporary lactose malabsorption and post-infectious bowel dysfunction may continue.
- 再検査 is generally unnecessary when symptoms resolve; suspected treatment failure requires attention to timing and specimen collection.
- Persistent infection checks commonly involve 3 stool specimens collected over several days, with CDC guidance advising at least 2 weeks after the last medication dose before re-examination for treatment failure.
- Swimming precautions continue for 2 weeks after diarrhea stops because Giardia can still spread after someone feels better.
- 緊急の評価 is needed for inability to retain fluids, markedly reduced urination, fainting, bloody stool, or severe localized abdominal pain.
What does a detected Giardia stool antigen mean?
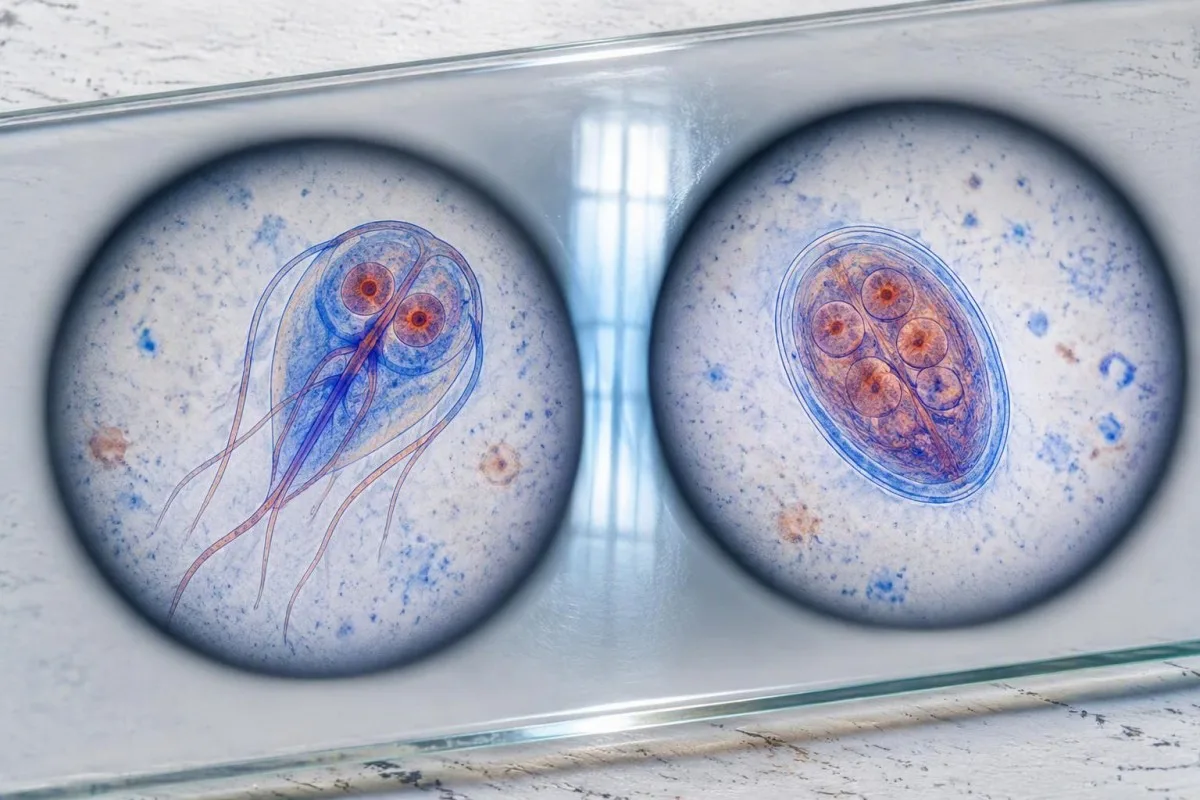
Giardia antigen detected means a stool assay found proteins from Giardia, a microscopic intestinal parasite. A positive result usually supports giardiasis and warrants clinical assessment; symptomatic patients commonly receive prescription treatment. Symptoms can persist after clearance, and repeat testing is usually reserved for persistent or recurrent illness rather than routinely performed after recovery.

A result reported as giardia stool antigen positive is usually qualitative: detected or not detected, rather than a concentration that predicts how sick you should feel. Laboratories may produce internal assay signals, but these are not interchangeable parasite counts; our explanation of 定性検査結果と定量検査結果 が、その違いを説明しています。.
The timing changes the interpretation. A first positive sample collected before treatment is different from a positive sample collected 2 days after finishing medication, when residual target material and testing limitations complicate the question of cure; neither result tells you precisely when the parasite was acquired.
My clinical approach, as Thomas Klein, MD, is to separate 3 questions: does the result fit the symptoms, is treatment appropriate, and is the person becoming dehydrated? Kantesti is an AI blood test analyzer that explains associated laboratory findings, not a substitute for a Giardia stool assay or a prescribing clinician; 組織についてさらに詳しく読むことができます。 describes that distinction.
How antigen testing differs from PCR and microscopy
Giardia antigen testing detects parasite proteins, PCR detects parasite genetic material, and microscopy looks for parasite structures. These 3 approaches can disagree because their targets, sensitivity, specimen requirements, and vulnerability to collection problems differ. A positive antigen is not an antibody result and does not mean immunity from a previous infection.

PCR, often included in a multiplex gastrointestinal panel, can detect Giardia alongside several other organisms in 1 specimen. That broader panel may reveal a second explanation for diarrhea, but detecting genetic material does not independently establish organism viability, and PCR signal values should not be interpreted as a standardized severity score.
Microscopy depends on what reaches the slide and who examines it. Routine ova-and-parasite examination may miss intermittent shedding; direct fluorescent antibody microscopy is a different, highly sensitive technique that CDC identifies as a diagnostic gold standard, so a report saying only 'microscopy negative' leaves at least 1 useful question unanswered: which method?
Discordance deserves context rather than a vote between tests. If 1 antigen assay is positive but microscopy is negative in a person with greasy diarrhea after untreated-water exposure, the positive remains clinically meaningful; a blood antibody result answers a different question, as explained in positive antibody interpretation.
How long does Giardia last, and which symptoms fit?
Giardia symptoms commonly begin 1–2 weeks after exposure and last 2–6 weeks, although untreated infection can persist longer. Typical symptoms include watery or greasy diarrhea, gas, abdominal cramps, nausea, fatigue, and weight loss. Some infected people have no symptoms, and others experience alternating better and worse days.
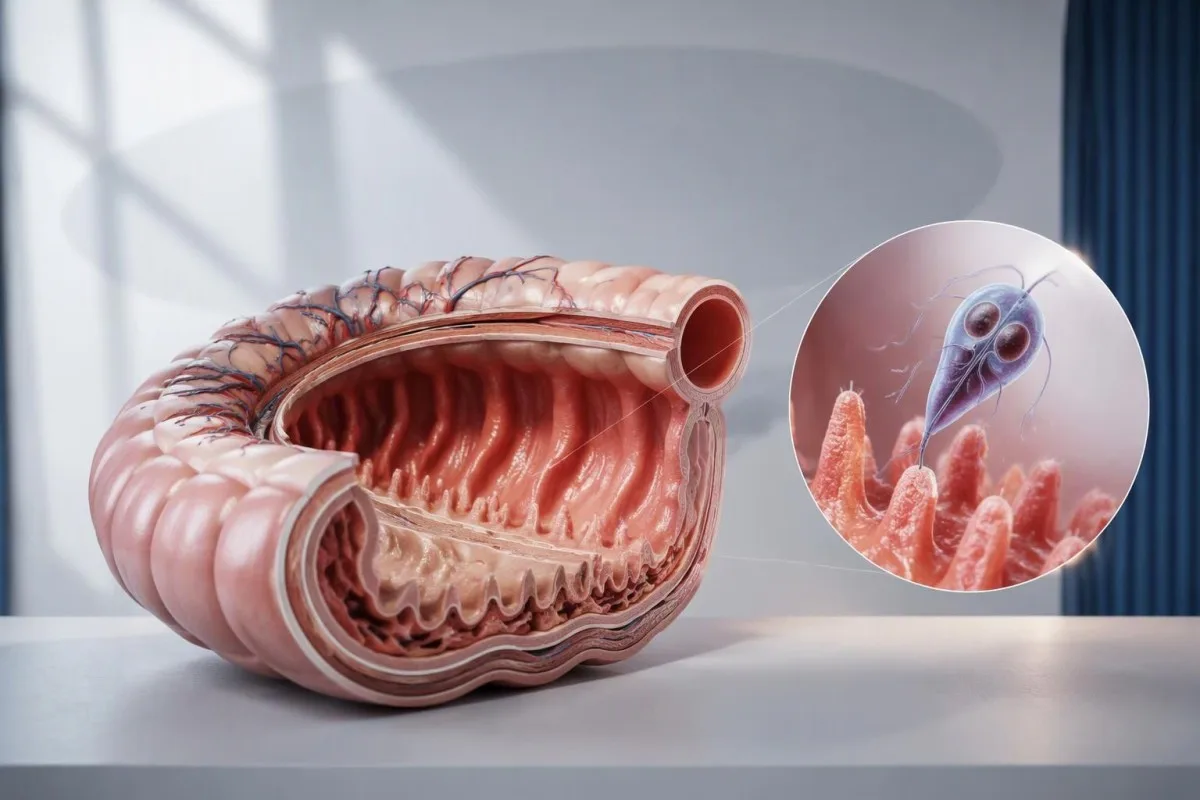
Greasy, foul-smelling stool reflects impaired absorption rather than a unique visual fingerprint of Giardia. Floating stool alone can result from gas, and yellow stool has several causes; yellow stool patterns are more useful when considered alongside weight change and the number of loose stools over 24 hours.
Consider an illustrative 34-year-old traveler whose diarrhea improves for 3 days and then returns before treatment. That interruption does not establish spontaneous clearance: intermittent symptoms and shedding can make the illness feel like separate episodes, while a household member with no diarrhea may still carry and transmit the parasite.
Successful treatment often brings noticeable improvement within several days, but there is no reliable deadline by which every bowel movement must normalize. A 7-day symptom diary recording stool frequency, food triggers, hydration, and weight direction provides better follow-up information than comparing today's stool appearance with yesterday's photograph.
How clinicians choose Giardia infection treatment
Giardia infection treatment commonly uses tinidazole, metronidazole, or nitazoxanide. The choice depends on age, pregnancy or breastfeeding, interactions, previous treatment, formulation, and local availability. A detected antigen does not identify drug susceptibility, so clinicians cannot choose the best medicine from the positive result alone.
Common adult regimens include tinidazole 2 g once with food, metronidazole 250 mg three times daily for 5–7 days, or nitazoxanide 500 mg twice daily with food for 3 days. These are examples, not instructions for self-treatment; local guidelines, product labeling, and individual circumstances can justify a different regimen.
Tinidazole combines a short schedule with strong efficacy evidence. Ordóñez-Mena, McCarthy, and Fanshawe's network meta-analysis found greater parasitological cure with tinidazole than metronidazole across the included trials, although study quality and follow-up varied (Ordóñez-Mena et al., 2018); completing 1 prescribed dose can also be easier than remembering multiple daily doses.
An asymptomatic positive result does not always require the same decision as symptomatic diarrhea. Clinicians may consider treatment when household transmission, vulnerable contacts, or occupational rules make carriage consequential; Kantesti cannot prescribe these medicines, and our discussion of medication safety monitoring distinguishes result interpretation from treatment authorization.
Which treatment precautions change the prescription?
Pregnancy, breastfeeding, childhood, anticoagulant use, and previous drug reactions can change the safest Giardia prescription. These circumstances should be disclosed before the first dose. Product-specific advice matters: 2 medicines used for the same parasite may have different age approvals, feeding precautions, and interaction risks.
Pediatric doses are generally weight-based, not a fraction of an adult tablet guessed at home. For example, tinidazole labeling permits a single 50 mg/kg dose, up to 2 g, for giardiasis in children older than 3 years; the child's clinician must check local approval, formulation, and whether another medicine is more appropriate.
Pregnancy needs an individual assessment of symptom severity, hydration, gestational timing, and drug evidence—not an automatic decision to delay all care. Tinidazole is generally avoided in pregnancy, particularly early pregnancy, and its labeling recommends interrupting breastfeeding during treatment and for 72 hours after the last dose; alternatives require clinician advice.
Metronidazole and tinidazole can increase warfarin's anticoagulant effect, making an INR monitoring plan relevant even for a short course. See 抗生物質投与後のINR変動 for the reasoning; alcohol restrictions also follow the prescribed product's instructions, commonly extending 72 hours after nitroimidazole treatment, rather than an assumption that 1 symptom-free evening proves safety.
What helps during the first days of recovery?
Oral rehydration and adequate food intake support Giardia recovery, but neither replaces antiparasitic treatment when it is indicated. Use a commercial oral rehydration solution mixed exactly as directed when diarrhea is substantial. Review the direction of change over 24–48 hours rather than expecting a normal stool immediately after medication.

Small, frequent sips can be easier to retain than a large glass taken quickly. For many otherwise healthy adults, roughly 200–250 mL of additional oral rehydration solution after each loose stool is a practical starting point, adjusted to thirst and losses; children and people with heart or kidney disease need individualized advice.
Plain water is useful, but substantial diarrhea also removes sodium and other electrolytes. Potassium below 3.5 mmol/L is generally low, although the laboratory range applies, and worsening weakness or palpitations can justify checking an 電解質パネル rather than simply drinking progressively larger amounts of water.
Dehydration can raise creatinine and temporarily lower calculated eGFR without proving chronic kidney disease. Kantesti is an AI blood test interpretation platform that can explain those accompanying results in context; a dehydration-related eGFR change is best reassessed after clinical recovery when appropriate, not labeled permanent from 1 dehydrated sample.
Why symptoms can persist after Giardia clears
Digestive symptoms can continue after Giardia clears because intestinal recovery is slower than parasite elimination. Temporary lactase deficiency, altered bowel sensitivity, and post-infectious irritable bowel syndrome are recognized explanations. A negative follow-up investigation and ongoing symptoms are not contradictory; they may describe 2 different stages of the same illness.
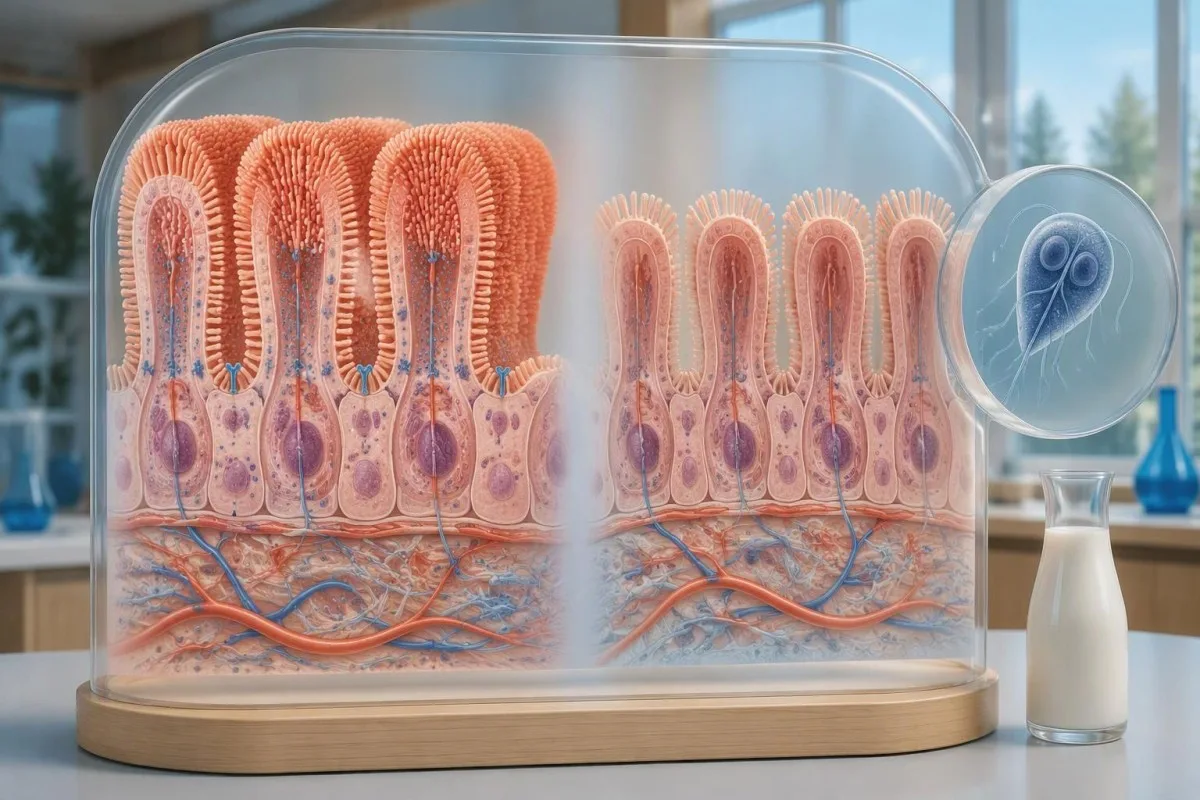
Lactase sits on the small-intestinal brush border, so Giardia-related surface disruption can make previously tolerated milk trigger gas and diarrhea. A 1–2 week trial of reduced lactose, followed by gradual reintroduction as symptoms settle, may be reasonable; lactose-free dairy retains protein and calcium, and complete dairy avoidance is not automatically necessary.
Post-infectious symptoms can also last much longer than temporary food intolerance. In a Norwegian outbreak cohort assessed 6 years later, IBS occurred in 39.4% of previously infected participants versus 11.6% of controls (Hanevik et al., 2014); those figures describe that particular cohort, not the expected outcome for every person with a positive antigen.
The pattern helps choose the next step: milk-triggered symptoms suggest malabsorption, whereas pain linked to defecation and fluctuating stool consistency may suggest post-infectious bowel dysfunction. In children, stool pH interpretation has limitations; 1 low result cannot identify Giardia or prove that a restrictive diet is needed.
What else should be checked if diarrhea continues?
Persistent diarrhea after Giardia treatment may reflect ongoing infection, reinfection, medication effects, or a separate digestive condition. Once appropriate stool investigations are negative, repeating antiparasitic prescriptions without reassessment can delay the correct diagnosis. Symptoms lasting 4 weeks or longer usually deserve a structured chronic-diarrhea review, sooner if warning signs appear.
Persistent bloating is not enough to diagnose small-intestinal bacterial overgrowth. A clinician may consider breath testing when risk factors and the symptom pattern support it, but test preparation and interpretation matter; our explanation of SIBO breath test limits shows why 1 positive-looking curve should not automatically trigger another antibiotic.
Celiac disease, inflammatory bowel disease, pancreatic problems, and another intestinal pathogen can enter the differential when weight loss, prolonged diarrhea, or nutritional abnormalities persist. If celiac testing is planned, removing gluten first can reduce test sensitivity; gluten exposure before testing should be discussed before starting a restrictive diet for 2 or more weeks.
The medication timeline often provides a simpler explanation than a new diagnosis. Nausea beginning with treatment, diarrhea associated with magnesium supplements, or symptoms after another antibiotic should be recorded with dates; in an illustrative patient whose stools improve by day 4 but bloating worsens after dairy, I would reassess the trigger before assuming resistance.
When should a positive Giardia test be repeated?
Repeat Giardia testing is usually appropriate when symptoms persist or recur, not routinely after symptoms resolve. In its treatment-failure pathway, CDC advises waiting at least 2 weeks after the last anti-Giardia medication dose before re-examination, using 3 stool specimens collected over several days. Worsening illness requires assessment without waiting for that interval.

The CDC Patient Care for Giardia Infection guidance uses antigen testing or microscopy on 3 specimens to assess whether infection remains (CDC, 2024). If those investigations are negative, ongoing infection becomes less likely even when symptoms continue; serial specimens address intermittent shedding rather than representing 3 identical confirmations from the same container.
An early positive result is harder to use as a clean treatment endpoint. Antigen proteins and genetic targets do not disappear according to 1 universal timetable, and laboratories differ in assay performance; ask which method was used, the collection date relative to the final dose, and whether the result would actually change management.
Public-health or workplace requirements can create exceptions, particularly during outbreaks or for specific childcare and food-handling roles. Kantesti separates test interpretation from clearance decisions; our 臨床方法論基準 explain why a positive or negative result must be interpreted with specimen timing and the relevant local rule, not 1 generic return-to-work promise.
What happens when Giardia remains positive after treatment?
A persistently positive Giardia result should prompt checks for reinfection and inadequate treatment before assuming drug resistance. Clinicians review the exact prescription, doses taken, vomiting, repeat exposures, and specimen timing. Confirmed infection despite an adequate regimen may require specialist-directed treatment using a different medicine or combination rather than blindly repeating the first course.
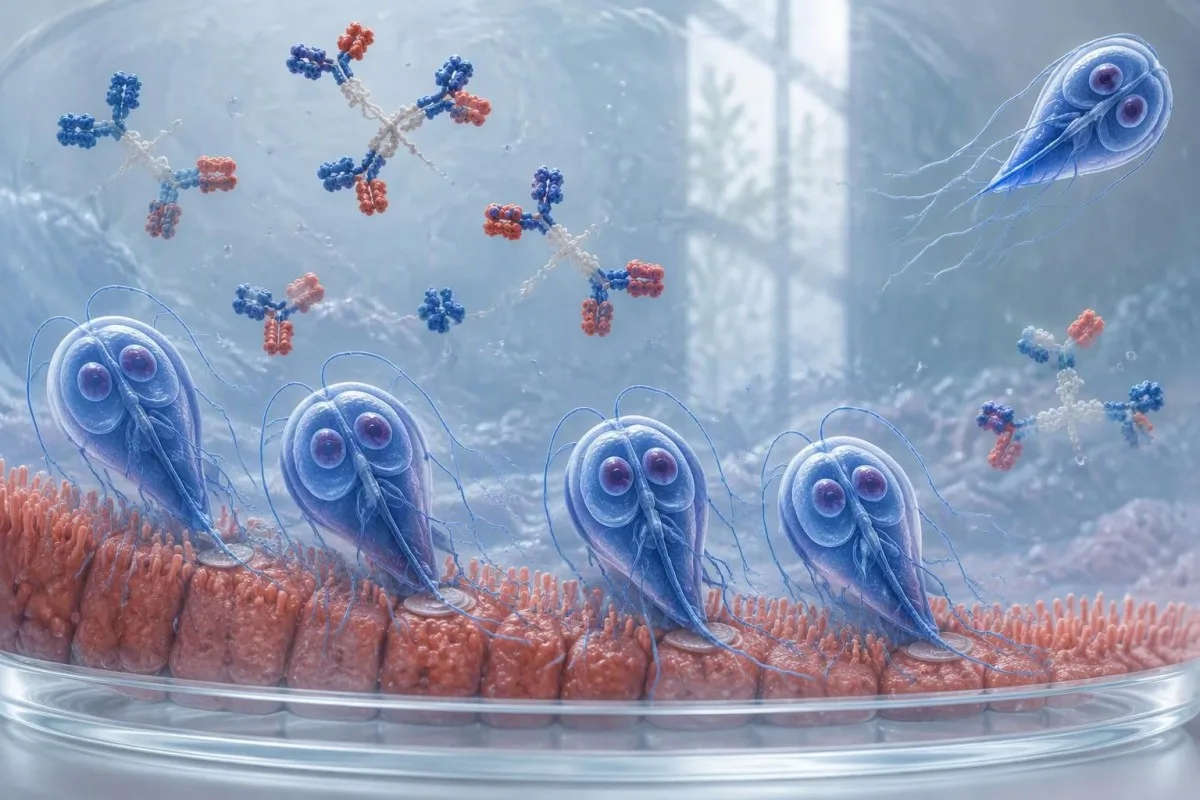
A returning positive result does not distinguish relapse from a fresh exposure. Ask whether untreated water is still being consumed, a symptomatic household member remains unassessed, or childcare exposure continues; a 2-week gap between improvement and renewed diarrhea can fit several explanations, so that interval alone cannot establish resistance.
Medication delivery is another practical checkpoint. Vomiting soon after a single dose, stopping a 7-day course early, or receiving an incorrect weight-based dose can reduce effective treatment; CDC places reinfection and inadequate treatment checks before combination therapy in its persistent-infection pathway (CDC, 2024).
Repeated confirmed giardiasis despite appropriate treatment can justify evaluating immune function, especially with other recurrent infections or unexplained nutritional decline. Clinicians may review IgG, IgA, and IgM together rather than ordering 1 isolated measurement; our 免疫グロブリン検査結果ガイド explains why low IgA and broader antibody deficiencies require different follow-up.
How to prevent spread and reinfection during recovery
Giardia spreads when microscopic cysts from fecal contamination are swallowed through water, food, hands, or contaminated objects. People may remain infectious after symptoms improve. Avoid swimming while diarrhea continues and for 2 weeks after it stops; routine pool chlorination does not immediately eliminate Giardia.

Soap-and-water handwashing after toilet use or diaper changes and before food preparation is a practical priority. Clean visible contamination before applying a suitable disinfectant according to its instructions; 1 quick wipe of a still-soiled surface is less reliable because organic material can interfere with disinfection.
For drinking water of uncertain safety, CDC recommends bringing water to a rolling boil for 1 minute, or 3 minutes above 6,500 feet, approximately 2,000 metres. A filter specifically rated to remove cysts, such as an appropriate absolute 1-micron filter, can help with Giardia but does not automatically remove every virus or chemical contaminant.
Household contacts with symptoms should seek assessment rather than share the patient's prescription. Food handling, childcare attendance, and intimate contact involving possible fecal exposure need additional precautions; contagiousness after gastroenteritis illustrates why feeling well and no longer transmitting are 2 separate questions, although each organism has its own rules.
Which symptoms need urgent medical assessment?
Seek urgent assessment for severe dehydration, inability to retain fluids, fainting, confusion, bloody or black stool, or severe localized abdominal pain. Giardia does not explain every abnormal symptom in someone with a positive test. Infants, older adults, pregnant patients, and immunocompromised people may need review earlier, even within the first 24 hours of worsening diarrhea.
Markedly reduced urination matters more than a reassuring stool result. An adult producing little or no urine for roughly 8–12 hours despite attempted drinking, particularly with dizziness or a rapid pulse, should obtain urgent advice; do not use that interval as a reason to wait if confusion, collapse, or rapid deterioration develops.
Visible blood, black tarry stool, or high fever should broaden the diagnosis beyond uncomplicated giardiasis. A temperature around 39°C with worsening abdominal symptoms warrants prompt review, and our guide to 便中の血液の緊急性 explains why color, volume, and associated symptoms change the response.
A normal inflammatory marker does not make severe abdominal pain safe to monitor at home. For example, a CRP of 3 mg/L may fall within a laboratory's normal range but cannot exclude an early abdominal emergency; WBCとCRPの不一致 is a reminder that clinical examination takes priority over 1 reassuring number.
Where blood tests and AI interpretation can help
Blood tests assess consequences of Giardia illness, such as dehydration or nutritional problems; they do not replace stool testing to establish infection or clearance. A CBC, electrolytes, kidney function, or selected nutritional markers may be useful when symptoms or examination justify them. An uncomplicated, improving case does not automatically require 1 large laboratory panel.

Persistent fatigue after diarrhea can reflect inadequate intake, sleep disruption, iron deficiency, or post-infectious illness. A hemoglobin below about 12 g/dL in a nonpregnant adult woman or 13 g/dL in an adult man generally suggests anemia, but local ranges and clinical context apply; fatigue alone cannot identify the cause or justify every supplement.
Kantesti is an AI biomarker interpretation platform that helps explain accompanying CBC, electrolyte, and kidney results rather than diagnosing Giardia from them. Our AIテクノロジーガイド describes the interpretation workflow; 1 uploaded report should be considered alongside symptoms, medicines, hydration, and the actual stool assay.
My editorial rule as Thomas Klein, MD, is simple: never let a normal blood panel overrule a worrying history, and never let an AI explanation authorize another antiparasitic course. Kantesti's 医療諮問委員会を provides information about our medical expertise; ongoing symptoms beyond 4 weeks deserve clinician-led reassessment rather than escalating diet restrictions or repeatedly checking the same biomarker.
研究ソースと関連する実験室出版物
The clinical recommendations here draw on CDC Giardia guidance and peer-reviewed research on treatment and post-infectious outcomes. As of October 24, 2026, the practical distinction remains infection clearance versus symptom recovery. The 2 Zenodo guides below address accompanying kidney or urine findings; neither is evidence that a Giardia stool antigen has cleared.
Treatment comparisons come from Ordóñez-Mena et al. (2018), while the 6-year post-infectious outcomes come from Hanevik et al. (2014); CDC's clinical-care pathway supplies the repeat-testing and treatment-failure framework. Kantesti's 医療コンテンツ基準 distinguish clinical research from educational repository publications, because a DOI identifies a document but does not establish peer review.
BUN/Creatinine Ratio Explained: Kidney Function Test Guide. (n.d.). Zenodo. https://doi.org/10.5281/zenodo.18207872. This publication provides background for kidney markers during dehydration, not a diagnostic rule for Giardia; the ResearchGateの出版物検索 そして Academia.edu 論文検索 are discovery links, not verified hosted copies.
Urobilinogen in Urine Test: Complete Urinalysis Guide 2026. (n.d.). Zenodo. https://doi.org/10.5281/zenodo.18226379. The 尿検査の解釈ガイド concerns urinary findings rather than parasite clearance; its ResearchGate発見検索 そして Academia.edu発見検索 likewise do not establish an independently reviewed publication record.
よくある質問
ジアルジア抗原が検出されたということは、現在感染しているということですか?
0 Giardia抗原が検出されたということは、便中に寄生虫のタンパク質が見つかったことを意味し、特に症状が一致する人で治療前に検査した場合、通常は現在の感染を裏付けます。この結果から寄生虫量を定量したり、感染した正確な日付を特定したりすることはできません。服薬の2日後に採取した検体は、適切な時期に採取した追跡検査用の検体と比べると、治療失敗の証拠として解釈するのが難しくなります。特に症状が続いている場合や、予想外の結果だった場合は、医療従事者に相談してください。.
ジアルジア便抗原陽性に対する通常の治療法は何ですか?
症候性ジアルジア感染症には、一般的にチニダゾール、メトロニダゾール、またはニタゾキサニドが処方されます。成人によく用いられるレジメンの一つは、食事とともにチニダゾール2 gを1回服用する方法です。代替薬として、メトロニダゾールを5~7日間、またはニタゾキサニドを3日間服用する方法があります。年齢、妊娠、授乳、薬物相互作用、過去の治療歴、地域での入手状況によって、処方内容が変わることがあります。残っている薬を使用したり、同居人の治療薬を共有したりしないでください。.
How long does Giardia last after treatment?
Giardia symptoms often begin improving within several days of effective treatment, but full digestive recovery can take longer. Untreated symptomatic illness commonly lasts 2–6 weeks and sometimes persists beyond that. Temporary lactose malabsorption or post-infectious bowel dysfunction can continue after the parasite has cleared. Worsening symptoms, dehydration, or persistent diarrhea should prompt reassessment rather than an automatic second prescription.
When should I repeat a Giardia stool test?
Routine repeat Giardia testing is usually unnecessary when symptoms resolve. For suspected treatment failure, CDC advises waiting at least 2 weeks after the last anti-Giardia medication dose before re-examination and using 3 stool specimens collected over several days. Local public-health rules may create exceptions. Severe or worsening illness needs assessment immediately rather than waiting for the testing interval.
Why do I still have bloating if my Giardia tests are negative?
Bloating after negative Giardia investigations can reflect temporary lactose malabsorption, post-infectious bowel sensitivity, or another digestive condition. A 1–2 week reduced-lactose trial may help identify a food trigger while intestinal function recovers. Persistent symptoms do not by themselves prove that Giardia remains present. Weight loss, nighttime diarrhea, bloody stool, or symptoms continuing beyond 4 weeks warrant a structured clinical review.
Can I spread Giardia after my diarrhea stops?
Giardia can still spread after diarrhea improves because microscopic cysts may continue to be passed in stool. CDC advises avoiding swimming for 2 weeks after diarrhea stops. Wash hands with soap and water after toilet use and before preparing food, and follow local food-handling or childcare rules. Symptomatic household contacts should seek their own assessment rather than share medication.
今日、AIによる血液検査分析を
いますぐ利用しませんか。即時で正確な検査分析を提供するKantestiを信頼する、世界中の200万人以上のユーザーに参加してください。血液検査結果をアップロードすると、15,000+のバイオマーカーについて数秒で包括的な解釈が得られます。.
📚 参考文献
Klein, T., Mitchell, S., & Weber, H. (2026). BUN/クレアチニン比の説明:腎機能検査ガイド.。 Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). 尿中ウロビリノーゲン検査:尿検査完全ガイド 2026.。 Kantesti AI Medical Research.
📖 外部の医学的参考文献
米国疾病予防管理センター(CDC) (2024)。. Patient Care for Giardia Infection. CDC Clinical Care Guidance.
Ordóñez-Mena JM, McCarthy ND, Fanshawe TR (2018). Comparative efficacy of drugs for treating giardiasis: a systematic update of the literature and network meta-analysis of randomized clinical trials. Journal of Antimicrobial Chemotherapy.
Hanevik K et al. (2014). Irritable bowel syndrome and chronic fatigue 6 years after Giardia infection: a controlled prospective cohort study.。 Clinical Infectious Diseases.




⚕️ 医療免責事項
この記事は教育目的のみを対象としており、医療助言を構成するものではありません。診断や治療の判断を行う際は、必ず有資格の医療提供者にご相談ください。.
E-E-A-T 信頼性シグナル
経験
医師主導による、検査結果解釈ワークフローの臨床レビュー。.
専門知識
臨床的な文脈においてバイオマーカーがどのように振る舞うかに焦点を当てた検査医学。.
権威
トーマス・クライン博士が執筆し、サラ・ミッチェル博士およびハンス・ヴェーバー教授によるレビュー。.
信頼性
アラームを減らすための明確なフォローアップ経路を備えた、エビデンスに基づく解釈。.
