
A detected mpox PCR result usually supports mpox when the specimen and symptoms fit; not detected means the assay found no target DNA in that sample. Inconclusive results need laboratory clarification. Lesion swabs are generally preferred over blood, and poor sampling or continuing suspicious symptoms can justify clinician-directed repeat testing—not routine testing to prove recovery.

Βασικά συμπεράσματα
- Detected means the assay found its target DNA; distinguish an MPXV-specific result from a broader orthopoxvirus result before interpreting it.
- Δεν εντοπίστηκε applies to the submitted specimen, not every body site; 1 poorly collected swab cannot reliably exclude a strongly suspected case.
- Inconclusive is neither positive nor negative; the laboratory may repeat extraction, check another target, or request 1 fresh specimen.
- Lesion swabs generally outperform blood for routine diagnosis because affected skin contains more reliably detectable viral material.
- Ποιότητα συλλογής matters: many services request 2 swabs from each of 2–3 lesions, but the receiving laboratory's instructions take priority.
- Επαναληπτικός έλεγχος has no universal 24-hour or 48-hour schedule; recollection should address the reason the first result was unhelpful.
- Exposure monitoring commonly extends to 21 days after the last exposure; a negative test before symptoms does not exclude later mpox.
- Ανάρρωση usually takes 2–4 weeks; routine negative PCR confirmation is generally not required to end precautions once clinical and local public-health criteria are met.
How do you read an mpox PCR test report?
Ενα mpox PCR test reports whether the assay detected viral DNA in the submitted specimen: detected, not detected, ή inconclusive. These 3 outcomes answer a specimen-specific question; they do not independently measure illness severity, establish when exposure occurred, or prove that somebody is no longer contagious.

The specimen description should be read before the result itself. A report saying skin-lesion swab answers a different clinical question from a blood or throat sample, even when both use PCR; record 3 details for your clinician: collection site, collection date, and the exact target name printed by the laboratory.
Most diagnostic mpox reports are ποιοτικό, rather than a standardized viral-load measurement in copies/mL. Our explanation of ποιοτικά έναντι ποσοτικών αποτελεσμάτων helps separate a yes-or-no finding from a numerical monitoring test; a value appearing beside the result may be a cycle threshold, not a concentration.
Το Καντέστι είναι ένα Αναλυτής εξέτασης αίματος AI that helps explain accompanying laboratory findings, but a routine blood panel cannot establish mpox. Information about ο οργανισμός μας should be considered separately from the laboratory's authority: 1 AI explanation cannot replace examination, appropriate specimen collection, or a clinician's interpretation of an infectious-disease result.
What does a detected or positive mpox PCR mean?
A detected MPXV-specific PCR means monkeypox virus DNA was found in the specimen and usually supports mpox when symptoms and sampling fit. A broader orthopoxvirus-positive result may require additional testing to identify the virus; these are 2 related but not identical report categories.
An unexpected weak positive deserves laboratory review rather than automatic dismissal or unquestioning acceptance. A CDC report described 3 false-positive orthopoxvirus results in people with low clinical likelihood, involving late amplification with cycle thresholds of at least 34; that observation is a caution, not a universal positive cutoff (CDC, 2022).
A hypothetical calculation illustrates why clinical likelihood matters: with 95% sensitivity and 99% specificity, testing 1,000 people at 1% prevalence would produce about 9.5 true positives and 9.9 false positives. Those assumptions are not measured mpox assay performance; they demonstrate why a surprising result may need confirmation even when a test is generally accurate.
PCR detection should not be confused with an antibody result showing previous exposure or an immune response. Our discussion of antibody confirmation limits explains that separate problem; for mpox, ask 2 questions instead: was this an MPXV-specific assay, and does the tested affected site match the current illness?
Can a not-detected result miss mpox?
A not-detected mpox PCR means the assay did not find its target above the detection limit in that specimen. A mpox test false negative can occur when insufficient material, an unsuitable site, or collection timing prevents detection; 1 negative result must be weighed against symptoms and exposure.
The strongest negative result comes from a suitable affected site, collected correctly and processed by a validated assay. A negative blood specimen cannot simply substitute for a negative lesion swab; if 2 specimens came from different sites, apparent disagreement may reflect where detectable DNA was present rather than laboratory error.
PCR's analytical sensitivity is not the same as its sensitivity in everyday clinical use. A laboratory may detect tiny quantities of purified target DNA under controlled conditions, yet 1 lightly collected swab can contain too little actual material; there is no single defensible false-negative percentage covering every mpox assay, specimen type, and collection setting.
Persistent symptoms change the meaning of a negative result, especially if a new accessible lesion appears after the original collection. The same timing principle appears in PCR collection windows, although mpox has its own specimen rules; contact the testing service with the original result and the date that the new affected area developed.
What do inconclusive, indeterminate, and invalid mean?
Inconclusive ή αδιευκρίνιστο means the laboratory cannot confidently classify the mpox result as detected or not detected. Invalid often indicates a failed control or processing problem; these 3 labels are laboratory-dependent, so the report comment matters more than the label alone.
Near the detection limit, different portions of the same specimen may contain different small quantities of target DNA. If 1 target amplifies weakly while another does not, the laboratory may repeat extraction or use an additional assay; this pattern does not automatically mean early disease, resolving disease, or contamination without supporting evidence.
A failed internal control can reflect substances that inhibit amplification, extraction failure, or another technical problem. Some controls also assess human material, but not every assay checks collection adequacy in that way; ask whether the control verified the PCR reaction, the specimen's cellular content, or both of these 2 distinct issues.
Reprocessing an existing specimen and collecting a new specimen solve different problems. Our guide to indeterminate laboratory results illustrates why uncertainty is not a halfway positive, although IGRA is a different test; for mpox, request the laboratory's reason and whether 1 fresh affected-site swab would be more informative.
Why are lesion swabs preferred over blood testing?
Lesion material is generally the preferred specimen for routine mpox PCR diagnosis because viral DNA is often more readily detectable at affected skin sites than in blood. WHO's 2022 laboratory guidance recommends skin-lesion material, including surface or exudate swabs and crusts, when available (WHO, 2022).

Blood can contain viral DNA, but its absence does not exclude mpox because circulating DNA may be low or transient. In a prospective Spanish cohort of 77 participants, investigators compared viral dynamics across multiple compartments, reinforcing that specimen sites behave differently over time (Suñer et al., 2023); blood testing is not an equivalent routine substitute for lesion collection.
A ΚΤΚ, CRP, kidney panel, or liver panel can answer questions about general illness and treatment safety, but none identifies MPXV. Our οδηγός ερμηνείας βιοδεικτών distinguishes those supporting tests; even 2 normal inflammatory measurements cannot rule out localized mpox, while abnormal measurements cannot confirm it.
Το Καντέστι είναι ένα πλατφόρμα ερμηνείας εξετάσεων αίματος AI, not a replacement for collecting an appropriate mpox specimen. The principle behind choosing the right specimen is broader than this virus: testing the convenient compartment rather than the informative compartment can leave 1 apparently reassuring result answering the wrong question.
What makes an mpox swab more reliable?
Reliable mpox swab collection requires adequate contact with an appropriate affected site, suitable collection materials, and correct transport. Many testing services request 2 swabs from each of 2–3 lesions, preferably representing different sites or appearances; the receiving laboratory's instructions always take priority.
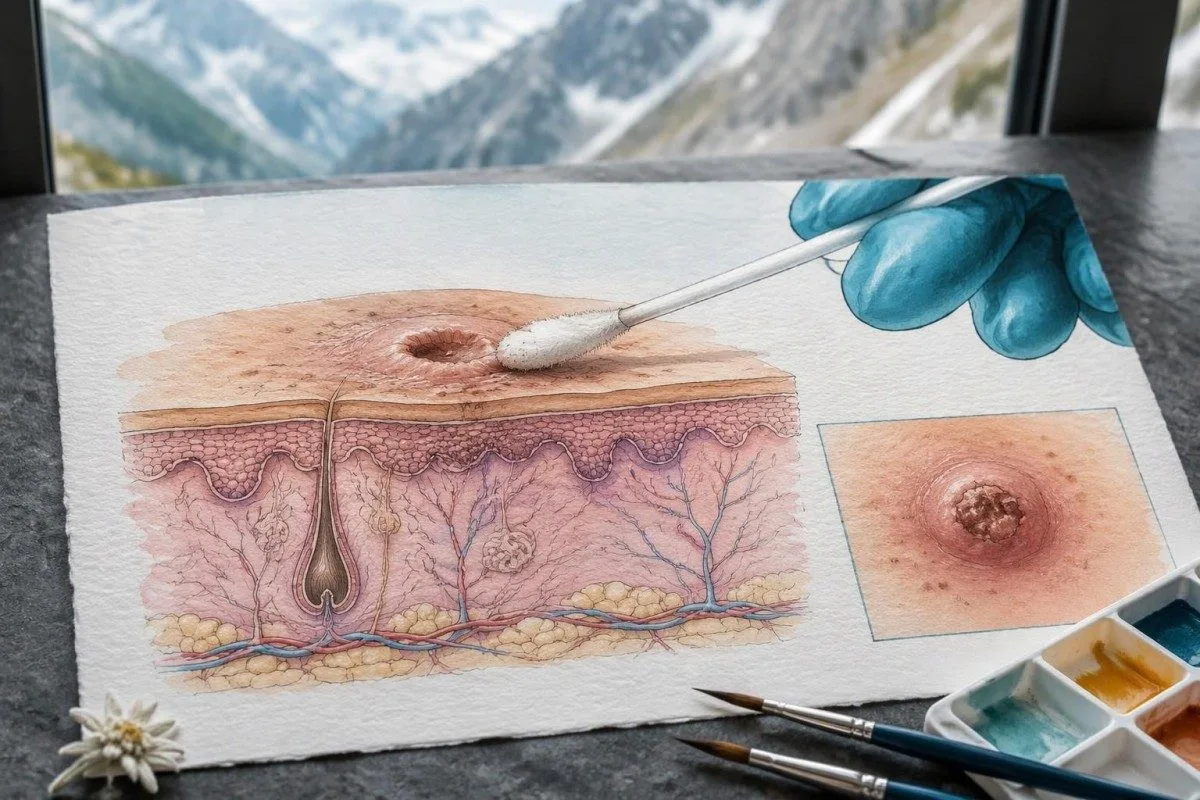
Firm surface swabbing by trained staff usually provides useful material without opening the lesion. Routine unroofing or use of sharp instruments is generally unnecessary and adds avoidable risk; do not puncture or scrape an affected area yourself to improve 1 test, and use home collection only when an authorized service supplies instructions.
Different laboratories accept different dry swabs, transport media, crust containers, and storage conditions. Putting a specimen into the wrong container can compromise processing even if the collection itself was good; keep 2 responsibilities separate: the clinician chooses an informative site, while the receiving laboratory specifies materials and handling.
Separate site labels help explain discordant results and preserve material for further testing when needed. Our guide to site-specific molecular testing covers another condition where location matters; for mpox, ask staff to document which of the 2–3 affected areas was sampled rather than treating every swab as interchangeable.
When should a clinician repeat an mpox PCR test?
Repeat mpox PCR testing is reasonable when the first specimen was unsuitable, the result was inconclusive, or compatible symptoms persist despite a negative result. δεν υπάρχει καθολικό 24-hour or 48-hour retesting interval; the next collection should correct a specific limitation of the first.

Recollection can be prompt—even on the same day—when the original specimen was rejected or clearly inadequate and a suitable affected site is available. Waiting 2 days without a biological or logistical reason does not repair poor sampling; ask whether the issue was the site, swabbing technique, transport, assay inhibition, or uncertainty near the detection limit.
Consider a clearly hypothetical example: a 34-year-old has a negative swab collected lightly from one old affected area, then develops 2 new firm lesions with continuing rectal symptoms. A clinician may collect fresh material and evaluate other causes simultaneously; another negative result is more useful if the second collection actually differs from the first.
Repeat testing should be driven by remaining diagnostic uncertainty, not by anxiety about a fixed calendar date. Our discussion of early false-negative testing illustrates that principle in another disease; Kantesti AI explanations cannot determine swab quality or decide whether 1 more specimen is clinically necessary.
Should you test after exposure if you have no lesions?
Routine mpox PCR screening after exposure is not a reliable way to exclude future illness when no suitable affected site is present. Public-health services commonly recommend symptom monitoring for 21 days after the last exposure; vaccination assessment and exposure advice should not wait for a negative screening result.
A negative throat or blood PCR before symptoms does not establish that exposure led to no infection. The incubation period can extend to 21 days, and detectable material may not yet be present in the sampled compartment; record the last exposure date, because repeated exposures can change the monitoring period.
Post-exposure vaccination is time-sensitive: public-health guidance generally aims for vaccination within 4 days to help prevent disease, with possible symptom reduction when given 4–14 days after exposure if symptoms have not developed. Eligibility and vaccine availability vary by jurisdiction; contact a clinician or public-health service rather than postponing that discussion while arranging screening.
Some symptomatic people have internal or mucosal affected sites without obvious external skin lesions. A clinician may consider validated site-specific sampling after examination, but 1 convenient throat swab is not a universal rule-out test; our guide to viral testing and timing explains why diagnostic windows must remain virus-specific.
What if symptoms persist but the mpox test is negative?
Persistent symptoms after a negative mpox PCR require reassessment of both specimen quality and alternative diagnoses. Mpox can coexist with another condition, so 1 positive test for a different infection does not necessarily explain every affected site or eliminate the need for appropriate mpox sampling.
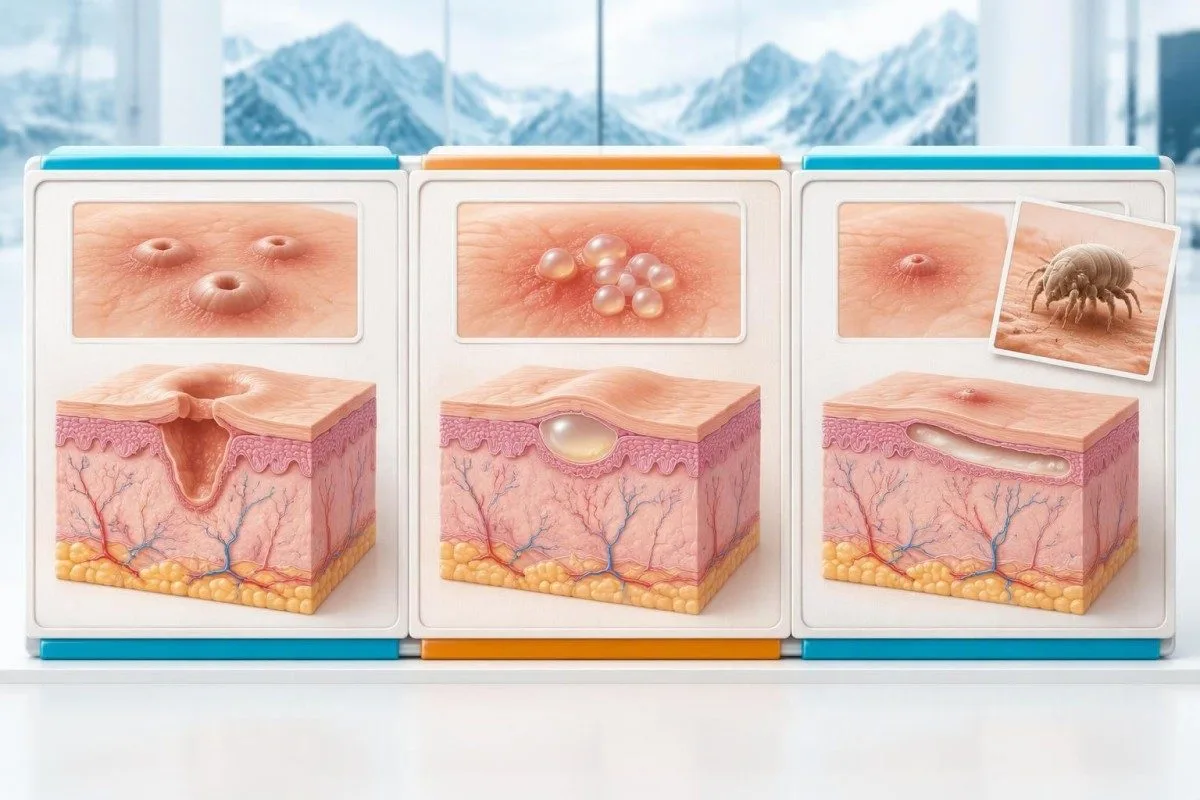
Herpes simplex, varicella-zoster, syphilis, bacterial skin infection, and noninfectious eruptions can overlap with parts of the mpox presentation. A rash concentrated on 1 side with grouped blisters may suggest a zoster pattern, but appearances are not definitive; our explanation of shingles rash patterns can help you describe the distribution accurately.
Night-time itch, household symptoms, and burrow-like markings may point toward scabies rather than mpox. Reviewing scabies symptom clues is useful for description, not self-diagnosis; 2 different rash processes can occur together, and photographs cannot assess every mucosal or deeper affected site.
Persistent rectal pain, painful swallowing, urinary difficulty, or worsening fever can justify examination even if the external rash looks minor. If symptoms continue through the usual 2–4-week recovery period or worsen sooner, a clinician should consider complications, another diagnosis, or further site-specific testing rather than ordering identical swabs indefinitely.
Does the PCR cycle threshold show contagiousness?
An mpox PCR cycle threshold, or Ct, cannot independently determine contagiousness or illness severity. Lower Ct values generally reflect more target DNA under comparable assay conditions, but there is no universal Ct 30, 34, or 35 threshold that proves somebody is safe to resume close contact.
Ct values depend on the assay, target, specimen, extraction method, and amount of material collected. Under ideal amplification, a 10-cycle difference represents roughly a 1,024-fold starting-target difference, but that mathematical example does not convert a lightly collected skin swab into a standardized viral-load measurement or support comparisons between unrelated laboratories.
PCR can remain positive after recoverable infectious virus has declined. Suñer et al.'s prospective cohort of 77 people used longitudinal PCR and viral culture to examine that distinction, but the findings do not establish a universal personal clearance cutoff (Suñer et al., 2023); our discussion of persistent viral DNA detection explains the general measurement problem.
Clinical recovery and molecular persistence are related but not interchangeable. The same distinction arises with testing after symptom recovery, although transmission rules differ between viruses; Kantesti does not translate 1 mpox Ct value into a contagiousness percentage, and patients should follow clinician and public-health instructions instead.
Do you need a negative PCR before ending precautions?
Routine repeat mpox PCR is generally not required to prove recovery or end isolation. Clinical criteria usually include healing of all affected areas, separation of scabs, and formation of new intact skin; typical illness lasts 2–4 εβδομάδες, but duration and local instructions can vary.

A healing site may still contain detectable DNA, so repeating PCR can create uncertainty without changing the care plan. One negative swab from a healed arm also cannot certify that a different mucosal site has recovered; ask the treating service which clinical criteria apply to your affected sites, household situation, and work setting.
A diagnostic repeat and a έλεγχος ίασης are 2 different uses of testing. Our explanation of when cure checks apply shows that some infections have explicit microbiological follow-up schedules; those schedules should not be imported into mpox simply because both diagnoses can involve molecular testing.
Specialist teams may order additional specimens for severe disease, prolonged illness, marked immunosuppression, or a specific public-health investigation. Those decisions are individualized rather than routine; do not treat day 14 or day 28 as automatic clearance dates if new affected areas are still developing or existing sites have not completely healed.
Which symptoms need care before a repeat result arrives?
Urgent symptoms override the PCR result: eye pain or visual change, breathing difficulty, confusion, severe dehydration, urinary retention, or uncontrolled rectal pain need prompt assessment. Do not wait 24–48 ωρών for another mpox PCR when symptoms suggest a complication or another serious illness.

New eye pain, marked redness, light sensitivity, or visual change warrants urgent medical assessment because ocular involvement can threaten vision. Avoid touching affected skin and then the eyes, and do not apply leftover steroid eye drops; 1 negative skin swab does not resolve an eye problem or determine which treatment is safe.
People who are pregnant, young children, and those with substantial immunosuppression should seek earlier clinician advice when mpox is suspected. Advanced HIV changes risk more than HIV status alone: a CD4 count below 200 cells/µL is a major immunosuppression marker, whereas an HIV viral load answers a different question; our HIV monitoring result guide εξηγεί αυτή τη διάκριση.
Call ahead when possible so the service can arrange suitable precautions, but never delay emergency care to do so. If you cannot drink, cannot pass urine, develop chest pain, or become confused, an examination and supporting investigations matter more than collecting a second swab; the need for acute treatment does not depend on having 2 positive results.
How can you prepare a useful follow-up plan?
A useful mpox follow-up plan records the exact result, specimen site, symptom timeline, and reason for any repeat test. Bring these 4 items to your clinician, together with relevant exposure and immune-status information; repeating a test is most helpful when the expected effect on care is explicit.
Το Καντέστι είναι ένα υπηρεσία ερμηνείας δοκιμών AI that can help organize accompanying blood-test findings, but it cannot verify how an mpox swab was collected. Our πληροφορίες κλινικής τεκμηρίωσης του Kantesti should not be read as validation of every pathogen-specific decision; 1 clear distinction is necessary between explaining a report and diagnosing a transmissible illness.
The 4 most useful questions are: was the assay MPXV-specific, was the sample suitable, does the clinical pattern still fit, and would another specimen change management? Our επεξήγηση τεχνολογίας AI describes interpretation tools, while the testing laboratory determines assay limitations; Kantesti AI explanations should support, not overrule, those limitations.
Keep different specimens separate in your notes rather than combining their outcomes into a single positive-or-negative label. For example, a hypothetical patient with 1 negative blood PCR and 1 positive lesion PCR needs interpretation of the informative lesion result, not an average of the two; include collection dates and any intervening treatment or new affected sites.
Which evidence supports mpox PCR interpretation?
WHO laboratory guidance and mpox-specific clinical studies support lesion-focused testing and cautious interpretation of uncertain results. Ο 3 εξωτερικές ιατρικές αναφορές listed below address specimen selection, false-positive testing, and viral dynamics; the 2 archived supporting publications have different topics and do not validate mpox diagnosis.

WHO's 2022 guidance provides the specimen-selection framework, while the CDC's 2022 report illustrates why a surprising late-amplification result merits review. Suñer et al.'s 2023 cohort adds longitudinal PCR and culture evidence, but its 77 participants cannot establish universal cutoffs for every clade, age group, immune state, or laboratory method.
Kantesti's 2 supporting DOI publications below concern digestive symptoms and women's health, not mpox PCR accuracy, repeat intervals, or antiviral treatment. A DOI identifies an archived publication; it does not itself establish peer review, diagnostic validation, or guideline status, and the mpox recommendations in this article rely on the separate condition-specific references.
Evidence must remain specific to the pathogen, specimen, and intended use. A separate virus-specific diagnostic guide cannot supply mpox assay thresholds; our πρότυπα ιατρικού περιεχομένου explain the editorial distinction between educational interpretation and clinical decisions, including why 1 uncertain result should not be turned into unwarranted reassurance.
Συχνές ερωτήσεις
What does an mpox PCR positive result mean?
A positive MPXV-specific PCR means monkeypox virus DNA was detected in the submitted specimen and usually supports mpox when symptoms and sampling fit. A broader orthopoxvirus-positive result may require further identification. The result does not measure severity or establish the exposure date. If 1 unexpected weak positive conflicts with the clinical picture, the clinician and laboratory may arrange confirmatory testing.
Can an mpox PCR test be falsely negative?
An mpox PCR test can be falsely negative if the wrong site is sampled, too little material is collected, or specimen handling or timing limits detection. One negative blood specimen is not equivalent to an adequately collected lesion swab. There is no single false-negative percentage that applies to all assays and specimen types. Persistent compatible symptoms justify clinician reassessment and sometimes a better-quality repeat specimen.
How soon should an inconclusive mpox test be repeated?
An inconclusive mpox result should be discussed with the laboratory or ordering clinician promptly, because the next step depends on why classification failed. The laboratory may reprocess the existing specimen or request a fresh affected-site sample. There is no universal 24-hour or 48-hour waiting rule. Recollection can occur promptly when the first specimen was unsuitable and an informative site is available.
Is a blood test or a lesion swab better for diagnosing mpox?
Lesion material is generally preferred for routine mpox PCR diagnosis because affected skin provides more reliably detectable viral DNA than blood. A negative blood PCR cannot reliably exclude mpox when compatible lesions are present. Many services request 2 swabs from each of 2–3 lesions, although laboratory instructions differ. Routine CBC or CRP measurements can support care but cannot identify monkeypox virus.
Do I need a negative mpox PCR to stop isolating?
Routine repeat mpox PCR is generally not required to establish recovery or end isolation. Decisions usually follow complete healing, scab separation, and new intact skin, together with clinician and local public-health guidance. Illness commonly lasts 2–4 weeks, but that range is not an automatic clearance deadline. PCR may detect residual DNA, so a positive repeat result does not independently measure contagiousness.
Can I test negative after exposure and still develop mpox?
A negative mpox PCR before symptoms does not exclude illness developing later, particularly when no suitable affected site was available for sampling. Exposure monitoring commonly continues for 21 days after the last exposure. Post-exposure vaccination is generally most useful within 4 days, with possible symptom reduction when given 4–14 days after exposure before symptoms develop. Contact a clinician or public-health service rather than using a screening result to end monitoring.
Δείτε πώς να διαβάσετε εξετάσεις αίματος
Ανεβάστε την εργαστηριακή σας αναφορά και η τεχνητή νοημοσύνη της Kantesti εξηγεί κάθε βιοδείκτη με απλή γλώσσα μέσα σε λίγα δευτερόλεπτα. Την έχουν χρησιμοποιήσει περισσότεροι από 2 εκατομμύρια άνθρωποι παγκοσμίως.
Αναφορές
- Klein, T., Mitchell, S., & Weber, H. (2026). Διάρροια μετά από νηστεία, μαύρα στίγματα στα κόπρανα και οδηγός γαστρεντερικού 2026. Ιατρική έρευνα της τεχνητής νοημοσύνης Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Οδηγός για την υγεία των γυναικών: ωορρηξία, εμμηνόπαυση και ορμονικά συμπτώματα. Ιατρική έρευνα της τεχνητής νοημοσύνης Kantesti. DOI
- Παγκόσμιος Οργανισμός Υγείας (2022). Laboratory testing for the monkeypox virus: interim guidance, 23 May 2022. Παγκόσμιος Οργανισμός Υγείας.
- Centers for Disease Control and Prevention (2022). Orthopoxvirus Testing Challenges for Persons in Populations at Low Risk or Without Known Epidemiologic Link to Monkeypox — United States, 2022. Εβδομαδιαία έκθεση νοσηρότητας και θνησιμότητας MMWR. DOI
- Suñer C et al. (2023). Viral dynamics in patients with monkeypox infection: a prospective cohort study in Spain. The Lancet Infectious Diseases. DOI
- 2+ εκατομμύριαΕξετάσεις που αναλύθηκαν
- 127+χωρών
- 100+Γλώσσες
Σχετικά με την ιατρική ομάδα


Σήματα εμπιστοσύνης E-E-A-T
Εμπειρία
Κλινική ανασκόπηση από ιατρό για τις ροές εργασίας ερμηνείας εργαστηριακών αποτελεσμάτων.
Πραγματογνωμοσύνη
Εστίαση στην εργαστηριακή ιατρική στο πώς συμπεριφέρονται οι βιοδείκτες στο κλινικό πλαίσιο.
Αυθεντικότητα
Ιατρική αξιολόγηση από τον Δρ. Thomas Klein, με συνεισφορές από τη Δρ. Sarah Mitchell και τον Καθ. Δρ. Hans Weber.
Αξιοπιστία
Ερμηνεία βασισμένη σε τεκμηριωμένα δεδομένα με σαφείς οδούς παρακολούθησης για τη μείωση του συναγερμού.




Ιατρική αποποίηση ευθύνης
Αυτό το άρθρο προορίζεται μόνο για εκπαιδευτικούς σκοπούς και δεν αποτελεί ιατρική συμβουλή. Συμβουλεύεστε πάντα έναν κατάλληλο επαγγελματία υγείας για αποφάσεις σχετικά με τη διάγνωση και τη θεραπεία.
Δημοσιεύθηκε · Επικοινωνήστε με τη συντακτική ομάδα
Εκδίδεται από την Kantesti Ltd, εγγεγραμμένη στην Αγγλία και την Ουαλία, αριθμός εταιρείας. 17090423, Λονδίνο, Ηνωμένο Βασίλειο.
