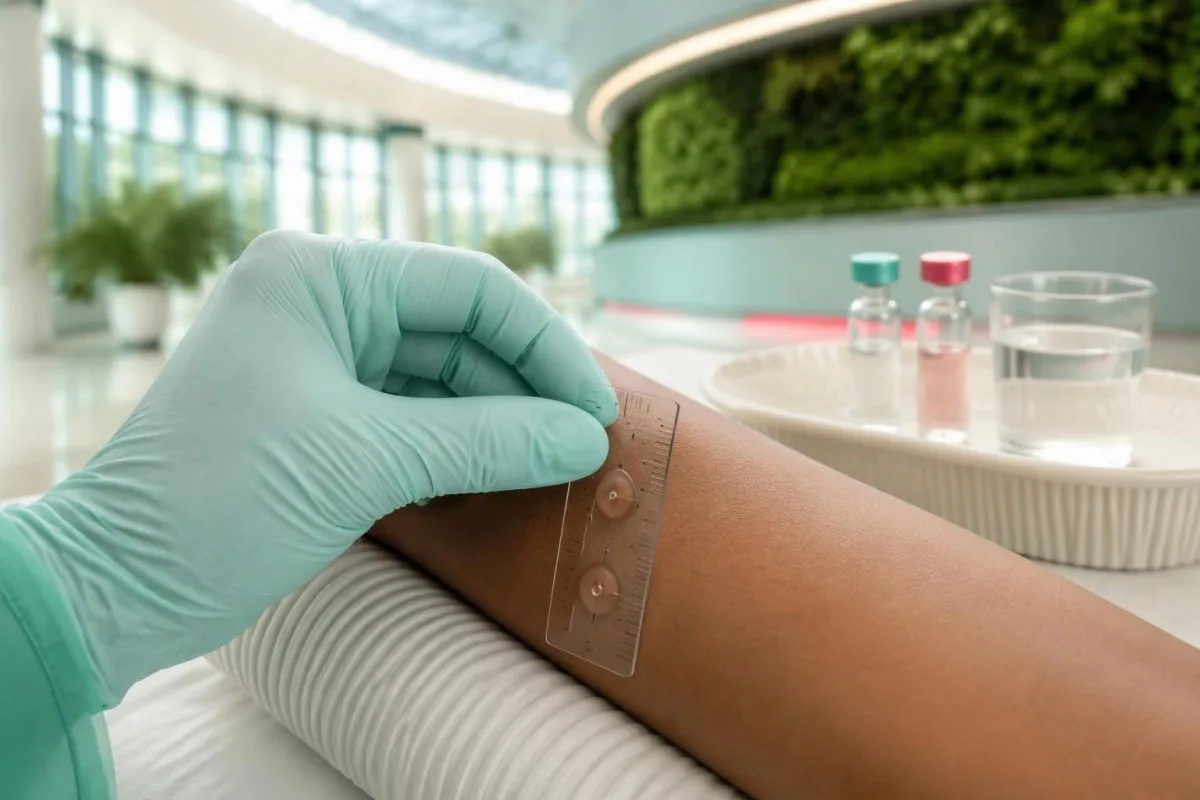
Many people can safely take penicillin again after clinician-led reassessment, but severe delayed reactions need a different pathway. Never test your tolerance at home.


- Penicillin allergy testing can often establish whether penicillin is safe again; a recorded allergy is not the same as a confirmed allergy.
- Low-risk histories may qualify for a supervised direct oral challenge without skin testing; family history alone does not establish drug allergy.
- PEN-FAST below 3 identified a low-risk adult group with a 96.3% negative predictive value in its derivation cohort, but severe delayed reactions override the score.
- Penicillin allergy skin tests assess immediate allergic sensitization; a negative result usually needs a supervised oral challenge to complete assessment.
- Amoxicillin oral challenge may use a clinic-selected adult dose such as 250 mg, followed by at least 60 minutes of observation under an appropriate protocol.
- Severe delayed reactions involving blistering, mucosal injury, fever with organ involvement, or immune-mediated organ damage are not routine challenge candidates.
- Allergy blood panels cannot reliably clear a penicillin label; normal total IgE, eosinophils, or negative drug-specific IgE do not prove tolerance.
- Penicillin allergy delabeling requires written documentation and updates to prescribing records; never attempt a challenge using leftover antibiotics at home.
Can penicillin allergy testing show you can take it again?
Yes—many people with a recorded penicillin allergy can take it again after clinician-led penicillin allergy testing. Clinicians first reconstruct the reaction, then choose a supervised oral challenge, skin testing followed by a challenge, or continued avoidance; severe delayed reactions follow a different pathway. Never attempt an antibiotic challenge at home.
A penicillin allergy label describes a past concern, not necessarily a current immune reaction. More than 9 in 10 labels are not confirmed when appropriately evaluated, although that figure must not be applied to someone with a documented severe reaction; eligibility matters more than the reassuring headline statistic.
Το Καντέστι είναι ένα Αναλυτής εξέτασης αίματος AI that can explain laboratory findings, but it cannot establish antibiotic tolerance from a report. Our οργανισμός και το κλινικό μας πεδίο εφαρμογής are separate from the hands-on allergy services needed for skin testing, medication administration, and emergency treatment.
An inaccurate label can push treatment toward a broader-spectrum antibiotic when a narrower penicillin would work better. That does not mean every alternative is inappropriate: the infection, local resistance, and individual risks still guide treatment, including the possibility of antibiotic-associated C. diff. Ask for reassessment before the next urgent prescription, not during an unsupervised experiment.
What details of your original reaction change the testing plan?
Ο timing, symptoms, treatment, and subsequent antibiotic exposures determine the first testing decision. Hives within 30 minutes suggest a different mechanism from a flat rash after 7 days, while blistering or organ injury changes the pathway entirely. The phrase “allergic as a child” does not contain enough information to make that decision.
I’m Thomas Klein, MD, and the first detail I would want is the interval between the last dose and the first symptom—not simply the day the antibiotic course began. Immediate reactions usually develop within 1 hour, although some appear over several hours; delayed reactions can start days later or after treatment has stopped.
An illustrative scenario helps: a 34-year-old recalls a childhood rash during glandular fever but no breathing problems, mouth sores, hospital admission, or treatment. That history may justify a low-risk assessment, not automatic clearance; μοτίβα αντισωμάτων EBV can explain the original illness without proving that amoxicillin caused or did not cause the rash.
Bring 4 kinds of evidence if available: the exact drug, photographs or discharge records, the treatment given, and names of antibiotics tolerated afterward. Tolerating penicillin years later may justify correcting the record without a new challenge if exposure is reliably documented; tolerating an unrelated antibiotic does not provide the same reassurance.
Which penicillin allergy histories are usually low risk?
Low-risk histories often include a remote uncomplicated rash, vague childhood symptoms without danger signs, or symptoms clearly consistent with intolerance. Some people need no allergy test at all—for example, when the label records only a family member’s allergy. Others still need a supervised challenge before the label can safely be removed.
Nausea or diarrhea alone is usually a side effect rather than an IgE-mediated allergy, especially without hives, swelling, or respiratory symptoms. That distinction can preserve an accurate intolerance entry while removing an inappropriate allergy warning; the aim is not to erase a real experience but to describe it correctly.
A flat, nonblistering rash more than 10 years ago is often less concerning than recent rapidly spreading hives, but age alone does not establish safety. Clinicians also ask whether the rash involved the mouth or eyes, whether fever occurred, and whether laboratory results or hospitalization suggested organ involvement—details that can overturn an initially reassuring history.
Repeated antibiotic treatment creates opportunities for both mistaken labels and genuinely new reactions. A review of τις διερευνήσεις συχνών λοιμώξεων may address why antibiotics keep being prescribed, but it cannot replace drug-allergy assessment; 2 separate questions need answering: whether treatment is necessary and which antibiotic can safely be used.
Which severe reactions should not undergo routine challenge?
Stevens–Johnson syndrome, toxic epidermal necrolysis, DRESS, and other serious delayed drug reactions are not routine oral-challenge candidates. A remote date or negative immediate skin test does not make re-exposure safe. Suspected drug-related liver injury, interstitial nephritis, hemolytic anemia, or a serious serum sickness pattern also requires specialist assessment rather than standard delabeling.
Danger signs include painful skin changes, blisters, peeling, mouth or eye involvement, facial swelling with fever, and symptoms suggesting organ injury. DRESS often appears 2–8 weeks after a drug is started, although antibiotic-associated cases can occur sooner; this timing can explain why the culprit was not recognized during the original prescription.
A raised eosinophil count may support investigation of DRESS, but neither eosinophilia alone nor a normal count settles the diagnosis. An absolute eosinophil count above 1.5 × 10^9/L deserves contextual review, particularly with new systemic symptoms; our guide to high eosinophil warning signs explains why counts and symptoms must be read together.
Organ involvement changes the safety question from “Will hives recur?” to “Could another exposure cause serious systemic harm?” Reviewing συντομογραφίες ηπατικών εξετάσεων can help identify what was measured, but even 1 documented episode of antibiotic-associated hepatitis or kidney injury can justify a specialist-only pathway; normal results today do not erase that history.
How do clinicians use PEN-FAST without missing dangerous histories?
PEN-FAST is an adult clinical decision rule that helps identify low-risk penicillin allergy histories; a score below 3 can support consideration of direct supervised challenge. It is not permission to take penicillin independently. Severe delayed reactions must be recognized separately because a numerical score cannot override a contraindication to re-exposure.
The rule assigns 2 points for a reaction within the previous 5 years, 2 for anaphylaxis, angioedema, or a severe cutaneous reaction, and 1 when treatment was required. A remote severe cutaneous reaction can therefore produce a deceptively low total; the clinician must apply the safety exclusions before using the score to select a challenge.
Trubiano et al. reported a 96.3% negative predictive value for PEN-FAST below 3 in the derivation cohort (Trubiano et al., 2020). That means the score was useful at identifying patients unlikely to have confirmed allergy in that setting—not that every person with a low score has a 96.3% chance of safely passing any unsupervised exposure.
The 2022 drug-allergy practice parameter emphasizes phenotype-based assessment and greater use of direct challenges in selected patients (Khan et al., 2022). Kantesti’s clinical validation boundaries should be understood just as carefully: blood-report interpretation is not validation of an allergy risk score, and 1 favorable laboratory result cannot certify challenge eligibility.
What does a penicillin allergy skin test actually measure?
A penicillin allergy skin test looks for evidence of immediate allergic sensitization using skin-prick testing and, when appropriate, intradermal testing. Clinicians use relevant penicillin reagents plus positive and negative controls. A negative result usually needs a supervised oral challenge to complete the evaluation; it does not exclude severe delayed immune reactions.
Testing commonly includes a major penicillin determinant and penicillin G, with additional reagents chosen according to availability and the original drug. Some clinics include amoxicillin when that was the culprit; reagent differences across countries matter because “negative penicillin testing” does not always describe an identical test panel.
Skin-prick responses are often read after 15–20 minutes, with a wheal at least 3 mm larger than the negative control commonly considered positive under the applicable protocol. The histamine control must respond appropriately; antihistamines, marked skin reactivity, or technical problems can make a result uninterpretable rather than reassuringly negative.
A negative skin test followed by a tolerated challenge substantially reduces the likelihood of current immediate allergy, but the history still determines what was excluded. Swelling without hives can sometimes have another mechanism, discussed in our C1 inhibitor interpretation guide; that distinction matters because not every episode of swelling after a prescription was caused by penicillin.
What happens during a supervised amoxicillin oral challenge?
Κατά τη διάρκεια μιας amoxicillin oral challenge, a clinician administers a protocol-selected dose and observes for a reaction in a setting equipped to treat anaphylaxis. Selected low-risk patients may receive a 1-step challenge; others receive a graded approach. The clinic decides the dose, monitoring interval, and whether skin testing is needed first.
An adult clinic might use 250 mg of amoxicillin followed by at least 60 minutes of observation, although protocols and doses vary. This is an example of professional practice, not a home-testing recipe: patient selection, baseline assessment, rescue medication, and trained staff are as important as the amount administered.
In the PALACE randomized trial, immediate immune-mediated reactions occurred in 0.5% of participants in both the direct-challenge and skin-testing-first groups among selected low-risk adults (Copaescu et al., 2023). The trial supports simplifying care for an appropriate population; it does not establish safety for people with severe delayed reactions or every type of previous anaphylaxis.
Observation focuses on new objective findings—hives, swelling, wheeze, changes in blood pressure—and on symptoms that need careful interpretation, such as isolated nausea or tingling. Reviewing οι τάσεις ασφάλειας φαρμάκων can help organize concurrent treatments, but no laboratory trend substitutes for real-time monitoring during the 1 challenge appointment.
How should you prepare for penicillin allergy testing?
Preparation means following the clinic’s medication instructions, bringing the original reaction history, and reporting current illness or uncontrolled asthma. Some antihistamines need to be withheld for several days before skin testing, but the interval depends on the drug. Do not stop prescribed medicines or alter asthma treatment without the testing team’s advice.
Many clinics request an antihistamine pause of roughly 3–7 days, but long-acting drugs and medicines with antihistamine effects can require different instructions. Beta-blockers and other cardiovascular medicines may affect emergency treatment decisions rather than skin-test readings; the clinic needs a complete list, including sleep aids, supplements, and nonprescription products.
Older adults often have more than 1 medication-related reason for cough, dizziness, or itching, which can complicate challenge interpretation. Our discussion of φαρμακευτικές επιδράσεις σε ηλικιωμένους is useful background, but the allergy team should decide whether a stable baseline has been reached before scheduling exposure.
If you take warfarin, distinguishing allergy from a separate drug interaction is especially useful: an antibiotic course can affect anticoagulation even when the allergy assessment is negative. Review Αλλαγές INR μετά από αντιβιοτικά, and ask whether monitoring is needed; passing 1 allergy challenge does not remove the interaction risks of a later treatment course.
Why can't routine allergy blood panels clear a penicillin label?
Routine allergy blood panels cannot reliably rule out penicillin allergy because they do not reproduce the relevant exposure and often do not measure the responsible immune mechanism. Normal total IgE and eosinophils are not clearance tests. Even negative penicillin- or amoxicillin-specific IgE cannot establish tolerance on its own.
Total IgE measures a broad antibody class, not a person’s clinical reaction to 1 antibiotic. Someone can have high total IgE from eczema or another allergic condition and still tolerate penicillin; our explanation of υψηλά αποτελέσματα IgE separates general sensitization signals from a drug-specific diagnosis.
Drug-specific IgE testing has limited sensitivity, depends on which determinants the assay includes, and may become negative as antibody levels decline over time. A reported value below a laboratory cutoff—sometimes 0.35 kUA/L—does not prove safety; conversely, a positive result needs interpretation because sensitization and clinically reproducible allergy are not interchangeable.
Το Καντέστι είναι ένα πλατφόρμα ερμηνείας εξετάσεων αίματος AI that can explain the difference between an assay threshold and a clinical conclusion, but it cannot issue allergy clearance. Molecular allergy component panels may refine selected food or respiratory allergy questions; that usefulness does not turn a negative broad panel into permission to take amoxicillin.
Can a delayed rash happen after a negative oral challenge?
Yes—a negative observed challenge can be followed by a delayed rash after the patient leaves or during a later full treatment course. A short challenge primarily addresses immediate tolerance and may not reproduce every delayed reaction. The discharge plan should explain what to report, whom to contact, and which symptoms require urgent care.
Some clinics arrange follow-up within 24–72 hours or ask patients to report symptoms over several days. A photograph, the time since the challenge, other new medicines, and whether fever or mucosal symptoms occurred can distinguish a mild exanthem from a more concerning pattern; “rash returned” is not enough detail to classify the reaction.
Routine multiday antibiotic exposure solely for testing is not necessary for many low-risk evaluations, according to the 2022 practice parameter (Khan et al., 2022). Clinicians sometimes use a longer protocol for a specific delayed history, but the potential information gain must justify exposing someone to additional antibiotic doses when there is no infection to treat.
Severe delayed reactions are not ruled out by a negative IgE test or 60 minutes of observation. Our explanation of abacavir hypersensitivity precautions illustrates another drug-specific immune safety pathway; the comparison is conceptual, because HLA-B*57:01 testing does not diagnose penicillin allergy or establish that penicillin re-exposure is safe.
How does testing differ for children, pregnancy, and chronic illness?
Children, pregnant patients, and people with significant comorbidity can be evaluated for penicillin allergy, but patient selection and the setting need adjustment. Pregnancy is not an automatic reason to retain an inaccurate label. Uncontrolled asthma or unstable illness may require postponement or specialist assessment rather than the standard outpatient pathway.
For children with a benign cutaneous reaction and no systemic danger signs, clinicians increasingly consider direct oral challenge rather than routine skin testing first (Khan et al., 2022). Pediatric dosing depends on the protocol and often weight; the 250 mg adult example should not be copied for a child, and viral rashes still need careful historical interpretation.
Pregnancy assessment can be particularly useful when penicillin may be needed for intrapartum group B streptococcal prophylaxis or syphilis treatment. If penicillin is essential and immediate allergy remains likely, specialists may consider desensitization in a monitored setting; this is temporary tolerance during treatment, not a permanent removal of the allergy label.
Kantesti does not use normal pediatric laboratory results as evidence that a child can safely receive penicillin. Our guide to ερμηνεία παιδιατρικών AI explains why age-specific laboratory context matters, but the allergy question remains exposure-specific; even 1 serious previous reaction needs evaluation outside an ordinary low-risk workflow.
Does an amoxicillin challenge clear every related antibiotic?
A tolerated amoxicillin challenge can support penicillin allergy delabeling when it matches the clinical question, but it does not automatically prove tolerance to every beta-lactam antibiotic. Selective side-chain allergy and reactions to another ingredient can require a narrower conclusion. The final report should name the drugs assessed and any restrictions that remain.
A reaction to amoxicillin–clavulanate may involve amoxicillin, clavulanate, or a nonallergic effect of the combination. Passing an amoxicillin-only challenge answers 1 part of that problem; it does not establish clavulanate tolerance, and a broad “all penicillins safe” statement can lose clinically useful detail.
Cephalosporin decisions depend substantially on side-chain similarity and the original reaction phenotype, not just a historical assumption of universal cross-reactivity. Some patients with penicillin allergy can receive an appropriately selected cephalosporin without penicillin delabeling; severe delayed reactions need a different level of caution, and the prescribing team should document its reasoning.
If immediate allergy is confirmed and an alternative is needed, the alternative may have its own monitoring requirements. For example, vancomycin exposure monitoring commonly targets an AUC24/MIC of 400–600 for serious MRSA infection under appropriate assumptions; that separate pharmacologic issue should not be confused with an allergy test or a reason to use vancomycin indiscriminately.
What should happen after successful penicillin allergy delabeling?
Penicillin allergy delabeling is complete only when the assessment result reaches the records used for future prescribing. A tolerated challenge should be documented with the drug, dose, date, observation, and any delayed follow-up. Removing a warning from 1 clinic’s chart may leave the same label active at a pharmacy or hospital.
Ask for a written statement that specifies which allergy was removed and whether any related-drug restriction remains. Send it to your primary-care clinician, pharmacy, relevant specialist, and hospital system where feasible; 4 updated destinations can prevent a future emergency prescription from reverting to the old allergy assumption.
Kantesti AI can help explain laboratory reports alongside a clinician’s written assessment, but it cannot change the prescribing record or verify an undocumented challenge. Our guide to η ασφαλής κοινοποίηση αποτελεσμάτων στον κλινικό ιατρό discusses communication workflows; keep the original allergy-service report rather than relying on a paraphrased summary.
Passing a challenge does not guarantee that every future rash, side effect, or new allergy is impossible. Our όρια υπεύθυνης χρήσης της ΤΝ reflect the same principle: 1 reassuring result should answer the question it actually tested, not become a blanket safety promise; a genuinely new reaction deserves fresh assessment and accurate documentation.
Where do laboratory interpretation and allergy reassessment separate?
Laboratory interpretation can support an allergy investigation, but only the appropriate clinical assessment can establish whether re-exposure is advisable. As of October 20, 2026, this article draws on the 2022 practice parameter and the 2023 PALACE trial—not an invented newer guideline. Our ιατρική συμβουλευτική ομάδα provides context for that clinical boundary.
Το Καντέστι είναι ένα Εργαλείο ανάλυσης αιματολογικών εξετάσεων με AI-powered that can explain eosinophil counts, liver enzymes, and other reported findings without turning them into a penicillin clearance test. As Kantesti’s Chief Medical Officer, Thomas Klein, MD, I draw a firm boundary here: suspected anaphylaxis or severe delayed injury requires clinical care, not another upload; our πρότυπα ιατρικού περιεχομένου describe the editorial approach.
The 2 repository publications listed below concern other laboratory topics and are not evidence for penicillin allergy testing. Our οδηγός ερμηνείας γενικής ούρων can explain urinary findings when a clinician is investigating a separate renal question, but normal urine results cannot rule out a past drug-induced kidney reaction or authorize re-exposure.
Similarly, our iron panel interpretation guide addresses iron metabolism, not antibiotic tolerance. ResearchGate and Academia.edu links below are title searches, not verified copies of these 2 publications; for the allergy question, the directly relevant guideline, decision-rule study, and randomized trial are listed separately in the medical references.
Συχνές Ερωτήσεις
Μπορεί μια αλλεργία στην πενικιλίνη να υποχωρήσει με την πάροδο του χρόνου;
Η άμεση αλλεργική ευαισθητοποίηση στην πενικιλίνη μπορεί να εξασθενήσει με την πάροδο του χρόνου, αλλά το μεγάλο χρονικό διάστημα από μόνο του δεν αποδεικνύει ασφαλή ανοχή. Ο κλινικός ιατρός μπορεί να θεωρήσει ότι μια αντίδραση που συνέβη πριν από περισσότερα από 5 χρόνια ενέχει χαμηλότερο κίνδυνο, αφού εξετάσει τα συμπτώματα και τη θεραπεία της. Οι σοβαρές καθυστερημένες αντιδράσεις εξακολουθούν να αποτελούν ξεχωριστό ζήτημα ασφάλειας ακόμη και δεκαετίες αργότερα. Ζητήστε επανεκτίμηση υπό την καθοδήγηση κλινικού ιατρού, αντί να πάρετε μια παλιά συνταγή για να δείτε τι θα συμβεί.
Μπορώ να πάρω αμοξικιλλίνη αν έχω αλλεργία στην πενικιλίνη;
Η αμοξικιλλίνη ανήκει στην οικογένεια των πενικιλλινών, επομένως μια καταγεγραμμένη αλλεργία στην πενικιλλίνη πρέπει να αξιολογηθεί πριν τη λάβετε, εκτός αν ο θεράπων ιατρός σας έχει ήδη καθορίσει ένα κατάλληλο σχέδιο. Επιλεγμένοι ασθενείς χαμηλού κινδύνου μπορεί να υποβληθούν σε επιτηρούμενη από του στόματος δοκιμασία πρόκλησης με αμοξικιλλίνη, μερικές φορές με δόση 250 mg για ενήλικες που επιλέγεται από την κλινική. Η δόση, το περιβάλλον και η παρακολούθηση εξαρτώνται από το ατομικό ιστορικό. Μην πάρετε δοκιμαστική δόση στο σπίτι.
Αρκεί μια εξέταση αίματος για να αποκλειστεί η αλλεργία στην πενικιλίνη;
Μια εξέταση αίματος από μόνη της δεν μπορεί να αποκλείσει με αξιοπιστία την αλλεργία στην πενικιλίνη. Οι φυσιολογικές τιμές ολικής IgE ή ηωσινοφίλων και η αρνητική ειδική για την πενικιλίνη IgE δεν αποδεικνύουν κλινική ανοχή, ακόμη κι αν το αναφερόμενο αποτέλεσμα είναι κάτω από το όριο μιας εξέτασης, όπως 0,35 kUA/L. Οι ειδικές για το φάρμακο εξετάσεις μπορεί να μην ανιχνεύσουν σχετική ευαισθητοποίηση και δεν αποκλείουν σοβαρούς μηχανισμούς όψιμης αντίδρασης. Αντίθετα, οι κλινικοί χρησιμοποιούν το ιστορικό της αντίδρασης, την αξιολόγηση κινδύνου και τις κατάλληλα επιτηρούμενες δοκιμασίες.
Do I need skin testing before an amoxicillin oral challenge?
Not every patient needs penicillin skin testing before an amoxicillin oral challenge. Selected low-risk adults and children with appropriate benign histories may qualify for direct supervised challenge, while more concerning immediate histories often require skin testing first. In the PALACE trial, immediate immune-mediated reactions occurred in 0.5% of both selected low-risk adult groups. That finding does not apply to routine re-exposure after severe delayed reactions.
How long does a penicillin allergy oral challenge take?
Many penicillin allergy oral challenge protocols include at least 60 minutes of observation after the final dose, with longer monitoring when clinically indicated. Registration, history review, baseline assessment, and any skin testing add time to the appointment. Delayed symptoms can occur after discharge, so clinics may arrange reporting or follow-up over 24–72 hours or longer. Ask the testing service for its specific schedule rather than assuming every protocol is identical.
What if I develop symptoms after a negative penicillin allergy test?
New symptoms after a negative penicillin allergy test should be assessed according to their severity, timing, and features. Breathing difficulty, throat swelling, collapse, or rapidly progressive symptoms require emergency care immediately; use prescribed emergency medication according to your existing plan. A rash arising over the next 1–3 days should be photographed and reported to the testing service, particularly if accompanied by fever, blisters, or mouth or eye involvement. Do not repeat the antibiotic challenge yourself to confirm the cause.
Λάβετε σήμερα ανάλυση εξετάσεων αίματος με AI
Εγγραφείτε σε πάνω από 2 εκατομμύρια χρήστες παγκοσμίως που εμπιστεύονται το Kantesti για άμεση, ακριβή ανάλυση εργαστηριακών εξετάσεων. Ανεβάστε τα αποτελέσματα εξετάσεων αίματος και λάβετε ολοκληρωμένη ερμηνεία βιοδεικτών του 15,000+ μέσα σε δευτερόλεπτα.
📚 Παραπομπές σε δημοσιεύσεις έρευνας
Klein, T., Mitchell, S., & Weber, H. (2026). Ουροβιλινογόνο σε εξέταση ούρων: Οδηγός πλήρους γενικής εξέτασης ούρων 2026. Ιατρική έρευνα του Kantesti με AI.
Klein, T., Mitchell, S., & Weber, H. (2026). Οδηγός Μελετών Σιδήρου: TIBC, Κορεσμός Σιδήρου & Ικανότητα Σύνδεσης. Ιατρική έρευνα του Kantesti με AI.
📖 Εξωτερικές ιατρικές αναφορές
Trubiano JA et al. (2020). Development and Validation of a Penicillin Allergy Clinical Decision Rule. JAMA Internal Medicine.
Copaescu AM et al. (2023). Efficacy of a Clinical Decision Rule to Enable Direct Oral Challenge in Patients With Low-Risk Penicillin Allergy: The PALACE Randomized Clinical Trial. JAMA Internal Medicine.
⚕️ Ιατρική αποποίηση ευθύνης
Αυτό το άρθρο προορίζεται μόνο για εκπαιδευτικούς σκοπούς και δεν αποτελεί ιατρική συμβουλή. Συμβουλεύεστε πάντα έναν κατάλληλο επαγγελματία υγείας για αποφάσεις σχετικά με τη διάγνωση και τη θεραπεία.
Σήματα εμπιστοσύνης E-E-A-T
Εμπειρία
Κλινική ανασκόπηση από ιατρό για τις ροές εργασίας ερμηνείας εργαστηριακών αποτελεσμάτων.
Πραγματογνωμοσύνη
Εστίαση στην εργαστηριακή ιατρική στο πώς συμπεριφέρονται οι βιοδείκτες στο κλινικό πλαίσιο.
Αυθεντικότητα
Γραμμένο από τον Δρ. Thomas Klein με ανασκόπηση από την Δρ. Sarah Mitchell και τον Καθ. Dr. Hans Weber.
Αξιοπιστία
Ερμηνεία βασισμένη σε τεκμηριωμένα δεδομένα με σαφείς οδούς παρακολούθησης για τη μείωση του συναγερμού.