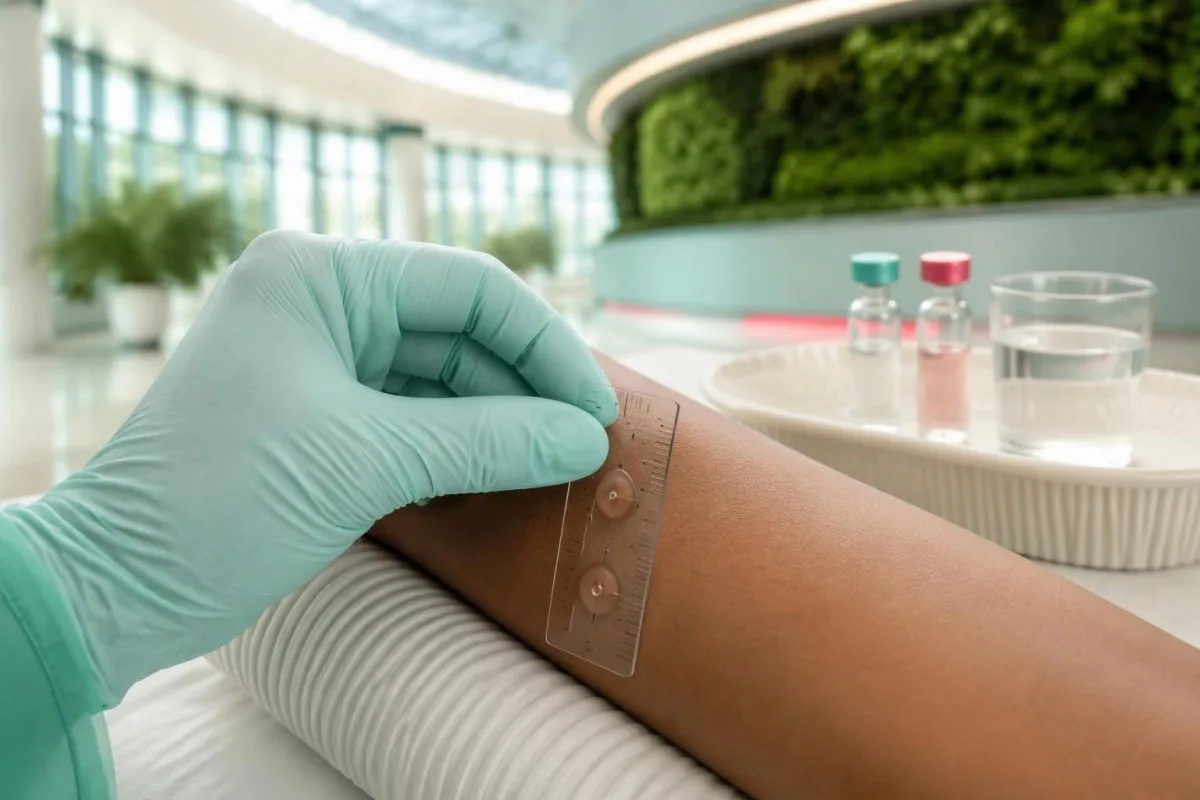
ብዙ ሰዎች በሐኪም መሪነት እንደገና ከተገመገሙ በኋላ ፔኒሲሊንን በደህና መውሰድ ይችላሉ፤ ነገር ግን ከባድ የዘገየ ምላሽ የተለየ አሰራር ይፈልጋል። በቤት ውስጥ የመቻቻል ችሎታዎን በፍጹም አይፈትሹ።.


- የፔኒሲሊን አለርጂ ምርመራ ብዙውን ጊዜ ፔኒሲሊንን እንደገና በደህና መውሰድ ይቻል እንደሆነ ሊያረጋግጥ ይችላል፤ የተመዘገበ አለርጂ ከተረጋገጠ አለርጂ ጋር አንድ አይደለም።.
- ዝቅተኛ አደጋ ያላቸው ታሪኮች የቆዳ ምርመራ ሳያስፈልግ በቀጥታ በአፍ የሚደረግ በክትትል ሥር ያለ የመቻል ምርመራ ሊፈቀድላቸው ይችላል፤ የቤተሰብ ታሪክ ብቻውን የመድኃኒት አለርጂን አያረጋግጥም።.
- PEN-FAST ከ3 በታች በመነሻ ጥናቱ የ96.3% አሉታዊ ትንበያ ዋጋ ያለው ዝቅተኛ አደጋ ያለበትን የአዋቂዎች ቡድን ለይቷል፤ ነገር ግን ከባድ የዘገየ ምላሽ ከውጤቱ ይበልጣል።.
- የፔኒሲሊን አለርጂ የቆዳ ምርመራዎች ፈጣን የአለርጂ ስሜትን ይገመግማሉ፤ አሉታዊ ውጤት ከሆነ ግምገማውን ለማጠናቀቅ ብዙውን ጊዜ በክትትል ሥር የአፍ የመቻል ምርመራ ያስፈልጋል።.
- በአፍ የአሞክሲሲሊን የመቻል ምርመራ ለምሳሌ በክሊኒኩ የተመረጠ 250 mg ያሉ የአዋቂዎች መጠን መጠቀም፣ ከዚያም ተገቢውን ፕሮቶኮል በመከተል ቢያንስ ለ60 ደቂቃዎች በክትትል ስር መቆየት ይቻላል።.
- ከባድ የዘገዩ ምላሾች እብጠትና ፊኛ የሚፈጥሩ የቆዳ ምላሾችን፣ የሙከሳ ጉዳትን፣ ከአካል ክፍሎች ተሳትፎ ጋር የሚመጣ ትኩሳትን ወይም በበሽታ የመከላከያ ሥርዓት የሚመራ የአካል ክፍል ጉዳትን የሚያካትቱ ሲሆን፣ በመደበኛነት ለምላሽ ምርመራ የሚመረጡ አይደሉም።.
- የአለርጂ የደም ምርመራ ፓነሎች የፔኒሲሊን አለርጂ መዝገብን በአስተማማኝ ሁኔታ ማስወገድ አይችሉም፤ መደበኛ የጠቅላላ IgE መጠን፣ የኢኦሲኖፊል ብዛት ወይም አሉታዊ የመድኃኒት-ተኮር IgE ውጤት መቻቻልን አያረጋግጡም።.
- የፔኒሲሊን አለርጂ ምልክትን ከመዝገብ ማስወገድ በጽሑፍ የተደገፈ ማስረጃና በመድኃኒት ማዘዣ መዝገቦች ላይ ማሻሻያ ይጠይቃል፤ በቤት የቀሩ አንቲባዮቲኮችን ተጠቅመው ምላሽ ምርመራ በፍጹም አይሞክሩ።.
የፔኒሲሊን አለርጂ ምርመራ እንደገና መውሰድ እንደሚችሉ ሊያሳይ ይችላል?
አዎ—የፔኒሲሊን አለርጂ ተብሎ በመዝገባቸው የተጻፈ ብዙ ሰዎች ከዚያ በኋላ እንደገና ሊወስዱት ይችላሉ በሐኪም የሚመራ የፔኒሲሊን አለርጂ ምርመራ. ። ሐኪሞች መጀመሪያ የተከሰተውን ምላሽ በዝርዝር ያጣራሉ፤ ከዚያም በክትትል ስር የሚደረግ የአፍ ምላሽ ምርመራ፣ ከዚያ በኋላ የሚደረግ ምላሽ ምርመራ የሚከተለው የቆዳ ምርመራ፣ ወይም መድኃኒቱን መቆጠብ መቀጠል ከሚሉት ይመርጣሉ፤ ከባድ የዘገዩ ምላሾች በተለየ መንገድ ይመራሉ። በቤት ውስጥ የአንቲባዮቲክ ምላሽ ምርመራ በፍጹም አይሞክሩ።.
የፔኒሲሊን አለርጂ ምልክት በቀድሞ የነበረ ጥርጣሬን ይገልጻል፤ አሁንም የበሽታ መከላከያ ምላሽ አለ ማለት አይደለም። ከ10 ምልክቶች ከ9 በላይ ተገቢው ምርመራ ሲደረግባቸው አይረጋገጡም፤ ይህ ቁጥር ግን የተመዘገበ ከባድ ምላሽ ላለው ሰው ተግባራዊ መደረግ የለበትም፤ ከሚያረጋጋው የስታቲስቲክስ መረጃ ይልቅ ብቁነት አስፈላጊ ነው።.
ካንቴስቲ እ.ኤ.አ. AI የደም ምርመራ ተንታኝ የላቦራቶሪ ውጤቶችን ሊያብራራ የሚችል፣ ነገር ግን ከሪፖርት ተነስቶ አንቲባዮቲክን መቻቻል ሊያረጋግጥ የማይችል፤ የእኛ ድርጅት እና ክሊኒካዊ ወሰን ለቆዳ ምርመራ፣ ለመድኃኒት አስተዳደር እና ለድንገተኛ ሕክምና ከሚያስፈልጉት በቀጥታ የሚሰጡ የአለርጂ አገልግሎቶች የተለዩ ናቸው።.
ትክክል ያልሆነ ምልክት ጠባብ የተግባር ወሰን ያለው ፔኒሲሊን የበለጠ ውጤታማ ሊሆን በሚችልበት ጊዜ ሕክምናውን ወደ ሰፊ የተግባር ወሰን ያለው አንቲባዮቲክ እንዲያዘነብል ሊያደርግ ይችላል። ይህ ማለት ሁሉም አማራጮች ተገቢ አይደሉም ማለት አይደለም፤ ኢንፌክሽኑ፣ በአካባቢው ያለው የመድኃኒት መቋቋም ሁኔታ እና የግለሰቡ አደጋዎች ሕክምናውን አሁንም ይመራሉ፤ ይህም የሚከተለውን የማጋጠም እድል ያካትታል ከአንቲባዮቲክ ጋር የተያያዘ C. diff. ። ያልተቆጣጠረ ሙከራ ከማድረግ ይልቅ፣ ቀጣዩ አስቸኳይ የመድኃኒት ማዘዣ ከመጻፉ በፊት እንደገና እንዲገመገም ይጠይቁ።.
የመጀመሪያው ምላሽዎ ምን ዝርዝሮች የምርመራ ዕቅዱን ይቀይራሉ?
የ የምላሹ ጊዜ፣ ምልክቶች፣ የተሰጠው ሕክምና እና በኋላ የተወሰዱ አንቲባዮቲኮች የመጀመሪያውን የምርመራ ውሳኔ ይወስናሉ። በ30 ደቂቃዎች ውስጥ የሚከሰት ቀፎ የሚመስል ሽፍታ ከ7 ቀናት በኋላ ከሚከሰት ጠፍጣፋ ሽፍታ የተለየ ስልት ያመለክታል፤ ፊኛ የሚፈጥር ሽፍታ ወይም የአካል ክፍል ጉዳት ግን መንገዱን ሙሉ በሙሉ ይቀይራል። “በልጅነት አለርጂ ነበረኝ” የሚለው ሐረግ ያንን ውሳኔ ለመስጠት በቂ መረጃ አይዟልም።.
እኔ ቶማስ ክላይን፣ MD ነኝ፤ መጀመሪያ ማወቅ የምፈልገው ዝርዝር ከመጨረሻው መጠን እና ከመጀመሪያው ምልክት መካከል ያለው የጊዜ ልዩነት ነው፤ የአንቲባዮቲኩ ኮርስ የጀመረበት ቀን ብቻ አይደለም። ፈጣን ምላሾች ብዙውን ጊዜ በ1 ሰዓት ውስጥ ይከሰታሉ፤ አንዳንዶቹ ግን በብዙ ሰዓታት ውስጥ ይታያሉ፤ የዘገዩ ምላሾች ደግሞ ከቀናት በኋላ ወይም ሕክምናው ከተቋረጠ በኋላ ሊጀምሩ ይችላሉ።.
ለምሳሌ የሚሆን ሁኔታ እንመልከት፦ የ34 ዓመት ሰው በጨቅላነቱ የጋንድ ትኩሳት በነበረበት ጊዜ ሽፍታ እንደነበረው ያስታውሳል፤ ነገር ግን የመተንፈስ ችግር፣ የአፍ ቁስል፣ ሆስፒታል መተኛት ወይም ሕክምና አልነበረም። ይህ የሕክምና ታሪክ ዝቅተኛ አደጋ እንዳለ ግምገማ ሊያስፈልግ ይችላል እንጂ በራስ-ሰር ንጹህ መሆኑን አያረጋግጥም፤; EBV የፀረ-ሰው ቅጦች የመጀመሪያውን ሕመም ሊያብራራ ይችላል፤ አሞክሲሲሊን ሽፍታውን አስከትሏል ወይም አላስከተለም ለማለት ግን ማስረጃ አይሆንም።.
ካሉ 4 ዓይነት ማስረጃዎችን ይዘው ይምጡ፦ ትክክለኛውን መድኃኒት፣ ፎቶግራፎች ወይም የሆስፒታል መውጫ ሰነዶች፣ የተሰጠውን ሕክምና እና ከዚያ በኋላ ተወስደው የታገሱ አንቲባዮቲኮችን ስም። ከዓመታት በኋላ ፔኒሲሊንን መቻል በአስተማማኝ ሰነድ ከተረጋገጠ፣ አዲስ ምላሽ ምርመራ ሳያስፈልግ መዝገቡን ማስተካከልን ሊያጸድቅ ይችላል፤ ከዚህ ያልተዛመደ አንቲባዮቲክን መቻል ግን ተመሳሳይ የማረጋገጫ ደረጃ አይሰጥም።.
የትኞቹ የፔኒሲሊን አለርጂ ታሪኮች ብዙውን ጊዜ ዝቅተኛ አደጋ አላቸው?
ዝቅተኛ አደጋ ያላቸው ታሪኮች ብዙ ጊዜ የሚያካትቱት ከሩቅ ጊዜ የተከሰተ ውስብስብ ያልሆነ ሽፍታ፣ የአደጋ ምልክቶች የሌሏቸው ግልጽ ያልሆኑ የልጅነት ምልክቶች፣ ወይም ከመድኃኒት አለመቻቻል ጋር በግልጽ የሚስማሙ ምልክቶች ናቸው። አንዳንድ ሰዎች የአለርጂ ምርመራ ጨርሶ አያስፈልጋቸውም፤ ለምሳሌ ምልክቱ የተመዘገበው የቤተሰብ አባል አለርጂ ብቻ ሲሆን። ሌሎች ግን ምልክቱን በደህና ከመዝገብ ማስወገድ በፊት በክትትል ስር የሚደረግ ምላሽ ምርመራ አሁንም ያስፈልጋቸዋል።.
Nausea or diarrhea alone is usually a side effect rather than an IgE-mediated allergy, especially without hives, swelling, or respiratory symptoms. That distinction can preserve an accurate intolerance entry while removing an inappropriate allergy warning; the aim is not to erase a real experience but to describe it correctly.
A flat, nonblistering rash more than 10 years ago is often less concerning than recent rapidly spreading hives, but age alone does not establish safety. Clinicians also ask whether the rash involved the mouth or eyes, whether fever occurred, and whether laboratory results or hospitalization suggested organ involvement—details that can overturn an initially reassuring history.
Repeated antibiotic treatment creates opportunities for both mistaken labels and genuinely new reactions. A review of ተደጋጋሚ ኢንፌክሽኖች ምርመራ may address why antibiotics keep being prescribed, but it cannot replace drug-allergy assessment; 2 separate questions need answering: whether treatment is necessary and which antibiotic can safely be used.
የትኞቹ ከባድ ምላሾች መደበኛ የመቻል ምርመራ ማድረግ የለባቸውም?
Stevens–Johnson syndrome, toxic epidermal necrolysis, DRESS, and other serious delayed drug reactions are not routine oral-challenge candidates. A remote date or negative immediate skin test does not make re-exposure safe. Suspected drug-related liver injury, interstitial nephritis, hemolytic anemia, or a serious serum sickness pattern also requires specialist assessment rather than standard delabeling.
Danger signs include painful skin changes, blisters, peeling, mouth or eye involvement, facial swelling with fever, and symptoms suggesting organ injury. DRESS often appears 2–8 weeks after a drug is started, although antibiotic-associated cases can occur sooner; this timing can explain why the culprit was not recognized during the original prescription.
A raised eosinophil count may support investigation of DRESS, but neither eosinophilia alone nor a normal count settles the diagnosis. An absolute eosinophil count above 1.5 × 10^9/L deserves contextual review, particularly with new systemic symptoms; our guide to high eosinophil warning signs explains why counts and symptoms must be read together.
Organ involvement changes the safety question from “Will hives recur?” to “Could another exposure cause serious systemic harm?” Reviewing የጉበት ምርመራ ምህጻረ ቃላት can help identify what was measured, but even 1 documented episode of antibiotic-associated hepatitis or kidney injury can justify a specialist-only pathway; normal results today do not erase that history.
ሐኪሞች አደገኛ የአለርጂ ታሪኮችን ሳያመልጡ PEN-FASTን እንዴት ይጠቀማሉ?
PEN-FAST is an adult clinical decision rule that helps identify low-risk penicillin allergy histories; a score below 3 can support consideration of direct supervised challenge. It is not permission to take penicillin independently. Severe delayed reactions must be recognized separately because a numerical score cannot override a contraindication to re-exposure.
The rule assigns 2 points for a reaction within the previous 5 years, 2 for anaphylaxis, angioedema, or a severe cutaneous reaction, and 1 when treatment was required. A remote severe cutaneous reaction can therefore produce a deceptively low total; the clinician must apply the safety exclusions before using the score to select a challenge.
Trubiano et al. reported a 96.3% negative predictive value for PEN-FAST below 3 in the derivation cohort (Trubiano et al., 2020). That means the score was useful at identifying patients unlikely to have confirmed allergy in that setting—not that every person with a low score has a 96.3% chance of safely passing any unsupervised exposure.
The 2022 drug-allergy practice parameter emphasizes phenotype-based assessment and greater use of direct challenges in selected patients (Khan et al., 2022). Kantesti’s clinical validation boundaries should be understood just as carefully: blood-report interpretation is not validation of an allergy risk score, and 1 favorable laboratory result cannot certify challenge eligibility.
የፔኒሲሊን አለርጂ የቆዳ ምርመራ በትክክል ምንን ይለካል?
A penicillin allergy skin test looks for evidence of immediate allergic sensitization using skin-prick testing and, when appropriate, intradermal testing. Clinicians use relevant penicillin reagents plus positive and negative controls. A negative result usually needs a supervised oral challenge to complete the evaluation; it does not exclude severe delayed immune reactions.
Testing commonly includes a major penicillin determinant and penicillin G, with additional reagents chosen according to availability and the original drug. Some clinics include amoxicillin when that was the culprit; reagent differences across countries matter because “negative penicillin testing” does not always describe an identical test panel.
Skin-prick responses are often read after 15–20 minutes, with a wheal at least 3 mm larger than the negative control commonly considered positive under the applicable protocol. The histamine control must respond appropriately; antihistamines, marked skin reactivity, or technical problems can make a result uninterpretable rather than reassuringly negative.
A negative skin test followed by a tolerated challenge substantially reduces the likelihood of current immediate allergy, but the history still determines what was excluded. Swelling without hives can sometimes have another mechanism, discussed in our C1 inhibitor interpretation guide; that distinction matters because not every episode of swelling after a prescription was caused by penicillin.
በክትትል ሥር በአፍ የአሞክሲሲሊን የመቻል ምርመራ ወቅት ምን ይከናወናል?
ውስጥ፣ ኢንሱሊን ተሰጥቶ የተቆጣጠረ ሃይፖግላይሴሚያ ለማስነሳት ይሰጣል፣ ብዙ ጊዜ የግሉኮስ መጣል እስከ amoxicillin oral challenge, a clinician administers a protocol-selected dose and observes for a reaction in a setting equipped to treat anaphylaxis. Selected low-risk patients may receive a 1-step challenge; others receive a graded approach. The clinic decides the dose, monitoring interval, and whether skin testing is needed first.
An adult clinic might use 250 mg of amoxicillin followed by at least 60 minutes of observation, although protocols and doses vary. This is an example of professional practice, not a home-testing recipe: patient selection, baseline assessment, rescue medication, and trained staff are as important as the amount administered.
In the PALACE randomized trial, immediate immune-mediated reactions occurred in 0.5% of participants in both the direct-challenge and skin-testing-first groups among selected low-risk adults (Copaescu et al., 2023). The trial supports simplifying care for an appropriate population; it does not establish safety for people with severe delayed reactions or every type of previous anaphylaxis.
Observation focuses on new objective findings—hives, swelling, wheeze, changes in blood pressure—and on symptoms that need careful interpretation, such as isolated nausea or tingling. Reviewing የመድኃኒት ደህንነት አዝማሚያዎች can help organize concurrent treatments, but no laboratory trend substitutes for real-time monitoring during the 1 challenge appointment.
ለፔኒሲሊን አለርጂ ምርመራ እንዴት መዘጋጀት አለብዎት?
Preparation means following the clinic’s medication instructions, bringing the original reaction history, and reporting current illness or uncontrolled asthma. Some antihistamines need to be withheld for several days before skin testing, but the interval depends on the drug. Do not stop prescribed medicines or alter asthma treatment without the testing team’s advice.
Many clinics request an antihistamine pause of roughly 3–7 days, but long-acting drugs and medicines with antihistamine effects can require different instructions. Beta-blockers and other cardiovascular medicines may affect emergency treatment decisions rather than skin-test readings; the clinic needs a complete list, including sleep aids, supplements, and nonprescription products.
Older adults often have more than 1 medication-related reason for cough, dizziness, or itching, which can complicate challenge interpretation. Our discussion of በአረጋውያን ላይ የመድኃኒት ውጤቶች is useful background, but the allergy team should decide whether a stable baseline has been reached before scheduling exposure.
If you take warfarin, distinguishing allergy from a separate drug interaction is especially useful: an antibiotic course can affect anticoagulation even when the allergy assessment is negative. Review አንቲባዮቲክስ ከተጠቀሙ በኋላ የ INR ለውጦች, and ask whether monitoring is needed; passing 1 allergy challenge does not remove the interaction risks of a later treatment course.
መደበኛ የአለርጂ የደም ምርመራ ፓነሎች የፔኒሲሊን አለርጂ መዝገብን ለምን ሊያጸዱ አይችሉም?
Routine allergy blood panels cannot reliably rule out penicillin allergy because they do not reproduce the relevant exposure and often do not measure the responsible immune mechanism. Normal total IgE and eosinophils are not clearance tests. Even negative penicillin- or amoxicillin-specific IgE cannot establish tolerance on its own.
Total IgE measures a broad antibody class, not a person’s clinical reaction to 1 antibiotic. Someone can have high total IgE from eczema or another allergic condition and still tolerate penicillin; our explanation of ከፍተኛ IgE ውጤቶች separates general sensitization signals from a drug-specific diagnosis.
Drug-specific IgE testing has limited sensitivity, depends on which determinants the assay includes, and may become negative as antibody levels decline over time. A reported value below a laboratory cutoff—sometimes 0.35 kUA/L—does not prove safety; conversely, a positive result needs interpretation because sensitization and clinically reproducible allergy are not interchangeable.
ካንቴስቲ እ.ኤ.አ. AI የደም ምርመራ ውጤት ትርጓሜ መድረክ that can explain the difference between an assay threshold and a clinical conclusion, but it cannot issue allergy clearance. Molecular allergy component panels may refine selected food or respiratory allergy questions; that usefulness does not turn a negative broad panel into permission to take amoxicillin.
የአፍ የመቻል ምርመራው አሉታዊ ከሆነ በኋላ የዘገየ ሽፍታ ሊከሰት ይችላል?
Yes—a negative observed challenge can be followed by a delayed rash after the patient leaves or during a later full treatment course. A short challenge primarily addresses immediate tolerance and may not reproduce every delayed reaction. The discharge plan should explain what to report, whom to contact, and which symptoms require urgent care.
Some clinics arrange follow-up within 24–72 hours or ask patients to report symptoms over several days. A photograph, the time since the challenge, other new medicines, and whether fever or mucosal symptoms occurred can distinguish a mild exanthem from a more concerning pattern; “rash returned” is not enough detail to classify the reaction.
Routine multiday antibiotic exposure solely for testing is not necessary for many low-risk evaluations, according to the 2022 practice parameter (Khan et al., 2022). Clinicians sometimes use a longer protocol for a specific delayed history, but the potential information gain must justify exposing someone to additional antibiotic doses when there is no infection to treat.
Severe delayed reactions are not ruled out by a negative IgE test or 60 minutes of observation. Our explanation of abacavir hypersensitivity precautions illustrates another drug-specific immune safety pathway; the comparison is conceptual, because HLA-B*57:01 testing does not diagnose penicillin allergy or establish that penicillin re-exposure is safe.
ለልጆች፣ ለእርግዝና እና ለሥር የሰደደ ሕመም ምርመራው እንዴት ይለያል?
Children, pregnant patients, and people with significant comorbidity can be evaluated for penicillin allergy, but patient selection and the setting need adjustment. Pregnancy is not an automatic reason to retain an inaccurate label. Uncontrolled asthma or unstable illness may require postponement or specialist assessment rather than the standard outpatient pathway.
For children with a benign cutaneous reaction and no systemic danger signs, clinicians increasingly consider direct oral challenge rather than routine skin testing first (Khan et al., 2022). Pediatric dosing depends on the protocol and often weight; the 250 mg adult example should not be copied for a child, and viral rashes still need careful historical interpretation.
Pregnancy assessment can be particularly useful when penicillin may be needed for intrapartum group B streptococcal prophylaxis or syphilis treatment. If penicillin is essential and immediate allergy remains likely, specialists may consider desensitization in a monitored setting; this is temporary tolerance during treatment, not a permanent removal of the allergy label.
Kantesti does not use normal pediatric laboratory results as evidence that a child can safely receive penicillin. Our guide to የሕፃናት AI ትርጓሜ ገደቦች explains why age-specific laboratory context matters, but the allergy question remains exposure-specific; even 1 serious previous reaction needs evaluation outside an ordinary low-risk workflow.
የአሞክሲሲሊን የመቻል ምርመራ ከእሱ ጋር የተያያዙ ሁሉንም አንቲባዮቲኮች ያጸዳል?
A tolerated amoxicillin challenge can support penicillin allergy delabeling when it matches the clinical question, but it does not automatically prove tolerance to every beta-lactam antibiotic. Selective side-chain allergy and reactions to another ingredient can require a narrower conclusion. The final report should name the drugs assessed and any restrictions that remain.
A reaction to amoxicillin–clavulanate may involve amoxicillin, clavulanate, or a nonallergic effect of the combination. Passing an amoxicillin-only challenge answers 1 part of that problem; it does not establish clavulanate tolerance, and a broad “all penicillins safe” statement can lose clinically useful detail.
Cephalosporin decisions depend substantially on side-chain similarity and the original reaction phenotype, not just a historical assumption of universal cross-reactivity. Some patients with penicillin allergy can receive an appropriately selected cephalosporin without penicillin delabeling; severe delayed reactions need a different level of caution, and the prescribing team should document its reasoning.
If immediate allergy is confirmed and an alternative is needed, the alternative may have its own monitoring requirements. For example, vancomycin exposure monitoring commonly targets an AUC24/MIC of 400–600 for serious MRSA infection under appropriate assumptions; that separate pharmacologic issue should not be confused with an allergy test or a reason to use vancomycin indiscriminately.
የፔኒሲሊን አለርጂ ምልክትን በተሳካ ሁኔታ ካስወገዱ በኋላ ምን መደረግ አለበት?
የፔኒሲሊን አለርጂ ምልክትን ከመዝገብ ማስወገድ is complete only when the assessment result reaches the records used for future prescribing. A tolerated challenge should be documented with the drug, dose, date, observation, and any delayed follow-up. Removing a warning from 1 clinic’s chart may leave the same label active at a pharmacy or hospital.
Ask for a written statement that specifies which allergy was removed and whether any related-drug restriction remains. Send it to your primary-care clinician, pharmacy, relevant specialist, and hospital system where feasible; 4 updated destinations can prevent a future emergency prescription from reverting to the old allergy assumption.
Kantesti AI can help explain laboratory reports alongside a clinician’s written assessment, but it cannot change the prescribing record or verify an undocumented challenge. Our guide to የውጤትን በደህንነት ለሐኪም ማጋራት discusses communication workflows; keep the original allergy-service report rather than relying on a paraphrased summary.
Passing a challenge does not guarantee that every future rash, side effect, or new allergy is impossible. Our የኃላፊነት ያለው AI ወሰኖች reflect the same principle: 1 reassuring result should answer the question it actually tested, not become a blanket safety promise; a genuinely new reaction deserves fresh assessment and accurate documentation.
የላቦራቶሪ ውጤት ትርጓሜ እና የአለርጂ ዳግም ግምገማ የሚለያዩት በየት ነው?
Laboratory interpretation can support an allergy investigation, but only the appropriate clinical assessment can establish whether re-exposure is advisable. As of October 20, 2026, this article draws on the 2022 practice parameter and the 2023 PALACE trial—not an invented newer guideline. Our የመድሃኒት ምክር ቡድን provides context for that clinical boundary.
ካንቴስቲ እ.ኤ.አ. በ AI የተጎላበተ የደም ምርመራ ትንተና መሳሪያ that can explain eosinophil counts, liver enzymes, and other reported findings without turning them into a penicillin clearance test. As Kantesti’s Chief Medical Officer, Thomas Klein, MD, I draw a firm boundary here: suspected anaphylaxis or severe delayed injury requires clinical care, not another upload; our የሕክምና ይዘት መስፈርቶች describe the editorial approach.
The 2 repository publications listed below concern other laboratory topics and are not evidence for penicillin allergy testing. Our የሽንት ምርመራ ትርጓሜ መመሪያ can explain urinary findings when a clinician is investigating a separate renal question, but normal urine results cannot rule out a past drug-induced kidney reaction or authorize re-exposure.
Similarly, our iron panel interpretation guide addresses iron metabolism, not antibiotic tolerance. ResearchGate and Academia.edu links below are title searches, not verified copies of these 2 publications; for the allergy question, the directly relevant guideline, decision-rule study, and randomized trial are listed separately in the medical references.
በተደጋጋሚ የሚጠየቁ ጥያቄዎች
የፔኒሲሊን አለርጂ ከጊዜ በኋላ ሊጠፋ ይችላል?
0 ወዲያውኑ የሚከሰት የፔኒሲሊን አለርጂ ስሜታዊነት ከጊዜ በኋላ ሊቀንስ ይችላል፤ ሆኖም ረጅም ጊዜ ማለፉ ብቻውን በደህና መታገስን አያረጋግጥም። አንድ ሐኪም ምልክቶቹንና የተደረገውን ሕክምና ከገመገመ በኋላ፣ ከ5 ዓመት በላይ ያለፈ ጊዜ የተከሰተ ምላሽ ዝቅተኛ አደጋ ያለው ሊሆን እንደሚችል ሊያስብ ይችላል። ከባድ ዘግይቶ የሚከሰቱ ምላሾች ከአሥርተ ዓመታት በኋላም የተለየ የደህንነት ስጋት ሆነው ይቀጥላሉ። የቆየ ትእዛዝ ያለ ሐኪም መመሪያ ወስደው ምን እንደሚፈጠር ከመመልከት ይልቅ፣ በሐኪም የሚመራ ዳግም ግምገማ ይጠቀሙ።.
ፔኒሲሊን አለርጂ ካለብኝ አሞክሲሲሊን መውሰድ እችላለሁ?
አሞክሲሲሊን የፔኒሲሊን ቤተሰብ አባል ስለሆነ፣ የሚያዝልዎ ሐኪም ተገቢ የሆነ ዕቅድ አስቀድሞ ካዘጋጀ በስተቀር፣ ከመውሰድዎ በፊት በመዝገብ የተመዘገበ የፔኒሲሊን አለርጂ መገምገም አለበት። አንዳንድ ዝቅተኛ አደጋ ያላቸው ታካሚዎች በሕክምና ባለሙያ ቁጥጥር ሥር የአሞክሲሲሊን በአፍ የሚወሰድ ሙከራ ሊያደርጉ ይችላሉ፤ አንዳንድ ጊዜም ክሊኒኩ የመረጠውን የአዋቂ ሰው መጠን 250 mg በመጠቀም። የመድኃኒቱ መጠን፣ የሚወሰድበት ቦታ እና የክትትል ጊዜ በግለሰቡ የቀድሞ ሁኔታ ላይ ይመረኮዛሉ። በቤት ውስጥ የሙከራ መጠን አይውሰዱ።.
0] የፔኒሲሊን አለርጂን ለማስቀረት የደም ምርመራ በቂ ነው?
የደም ምርመራ ብቻውን የፔኒሲሊን አለርጂን በአስተማማኝ ሁኔታ ለማስወገድ አይበቃም። መደበኛ የጠቅላላ IgE ወይም የኢኦዚኖፊል መጠን እና አሉታዊ የፔኒሲሊን-ተኮር IgE ውጤት፣ የተገለጸው ውጤት እንደ 0.35 kUA/L ያለ የምርመራ ወሰን በታች ቢሆንም እንኳ፣ በክሊኒካዊ ሁኔታ መቻሉን አያረጋግጡም። ለመድኃኒት ተኮር የሆኑ ምርመራዎች ተዛማጅ የበሽታ ተጋላጭነትን ላያገኙ ይችላሉ፣ እንዲሁም ከባድ የዘገየ ምላሽ ዘዴዎችን አያስወግዱም። በምትኩ፣ ሐኪሞች የምላሹን ታሪክ፣ የአደጋ ግምገማን እና በተገቢው ቁጥጥር ሥር የሚደረግ ምርመራን ይጠቀማሉ።.
ከአሞክሲሲሊን በአፍ ለመውሰድ የሚደረግ ሙከራ በፊት የቆዳ ምርመራ ማድረግ ያስፈልገኛል?
እያንዳንዱ ታካሚ የአሞክሲሊን በአፍ የሚወሰድ ሙከራ ከመደረጉ በፊት የፔኒሲሊን የቆዳ ምርመራ ማድረግ አያስፈልገውም። ተገቢ እና አሳሳቢ ያልሆነ የቀድሞ ታሪክ ያላቸው የተመረጡ አደጋቸው ዝቅተኛ አዋቂዎችና ሕፃናት በቀጥታ በክትትል ሥር ሙከራ ለማድረግ ብቁ ሊሆኑ ይችላሉ፤ ይበልጥ አሳሳቢ የሆኑ ፈጣን ምላሾች ያሉባቸው የቀድሞ ታሪኮች ግን ብዙውን ጊዜ በመጀመሪያ የቆዳ ምርመራ ያስፈልጋቸዋል። በPALACE ሙከራ፣ ወዲያውኑ የሚከሰቱ በሽታ የመከላከያ ስርዓት ምላሾች በሁለቱም የተመረጡ አደጋቸው ዝቅተኛ የአዋቂዎች ቡድኖች 0.5% ውስጥ ተከስተዋል። ይህ ግኝት ከከባድ ዘግይተው ከሚከሰቱ ምላሾች በኋላ በመደበኛነት ለመድኃኒቱ እንደገና መጋለጥ ላይ ተፈጻሚ አይደለም።.
የፔኒሲሊን አለርጂ በአፍ የሚደረግ ምርመራ ምን ያህል ጊዜ ይወስዳል?
ብዙ የፔኒሲሊን አለርጂ በአፍ የሚደረጉ የመቋቋም ሙከራ ፕሮቶኮሎች ከመጨረሻው መጠን በኋላ ቢያንስ 60 ደቂቃ ክትትልን ያካትታሉ፤ በክሊኒካዊ ሁኔታው ሲያስፈልግም ረዘም ያለ ክትትል ይደረጋል። ምዝገባ፣ የታሪክ ግምገማ፣ የመነሻ ሁኔታ ግምገማ እና ማንኛውም የቆዳ ምርመራ ለቀጠሮው ተጨማሪ ጊዜ ይጨምራሉ። ከሆስፒታል ከወጡ በኋላ የዘገዩ ምልክቶች ሊከሰቱ ስለሚችሉ፣ ክሊኒኮች ከ24–72 ሰዓታት ወይም ከዚያ በላይ ሪፖርት እንዲደረግ ወይም ክትትል ሊያዘጋጁ ይችላሉ። ሁሉም ፕሮቶኮሎች አንድ ዓይነት ናቸው ብለው ከመገመት ይልቅ፣ ለምርመራው አገልግሎት የተለየውን የጊዜ ሰሌዳ ይጠይቁ።.
የፔኒሲሊን አለርጂ ምርመራው አሉታዊ ከሆነ በኋላ ምልክቶች ቢታዩብኝስ?
ከፔኒሲሊን አለርጂ ምርመራ አሉታዊ ውጤት በኋላ የሚታዩ አዳዲስ ምልክቶች እንደ ክብደታቸው፣ መቼ እንደተከሰቱ እና ባህሪያቸው መገምገም አለባቸው። የመተንፈስ ችግር፣ የጉሮሮ እብጠት፣ መውደቅ ወይም በፍጥነት እየባሱ የሚሄዱ ምልክቶች ወዲያውኑ የድንገተኛ ሕክምና ይፈልጋሉ፤ በነባር ዕቅድዎ መሠረት የታዘዘልዎትን የድንገተኛ ሁኔታ መድኃኒት ይጠቀሙ። በሚቀጥሉት 1–3 ቀናት ውስጥ የሚከሰት ሽፍታ ፎቶ መነሳት እና ለምርመራው አገልግሎት ሪፖርት መደረግ አለበት፤ በተለይም ከትኩሳት፣ ከአረፋ ወይም ከአፍ ወይም ከዓይን መጎዳት ጋር ከተያያዘ። ምክንያቱን ለማረጋገጥ የአንቲባዮቲክ ሙከራውን በራስዎ እንደገና አያድርጉ።.
ዛሬ የAI-የኃይል የደም ምርመራ ትንተና ያግኙ
በፍጥነት እና ትክክለኛ የላቦራቶሪ ምርመራ ትንተና ለማግኘት Kantestiን የሚያምኑ ከ2 ሚሊዮን በላይ ተጠቃሚዎችን ይቀላቀሉ። የደም ምርመራ ውጤትዎን ይስቀሉ እና በ15,000+ ባዮማርከሮች ላይ የተሟላ ትርጓሜን በሰከንዶች ውስጥ ይቀበሉ።.
📚 የተጠቀሱ የምርምር ህትመቶች
📖 ውጫዊ የሕክምና ማጣቀሻዎች
Trubiano JA et al. (2020). Development and Validation of a Penicillin Allergy Clinical Decision Rule. JAMA Internal Medicine.
Copaescu AM et al. (2023). Efficacy of a Clinical Decision Rule to Enable Direct Oral Challenge in Patients With Low-Risk Penicillin Allergy: The PALACE Randomized Clinical Trial. JAMA Internal Medicine.
⚕️ የሕክምና ማስተባበያ
ይህ ጽሑፍ ለትምህርታዊ ዓላማ ብቻ ነው እና የሕክምና ምክር አይደለም። ለምርመራ እና ለሕክምና ውሳኔዎች ሁልጊዜ ብቁ የጤና ባለሙያን ያማክሩ።.
የE-E-A-T እምነት ምልክቶች
ልምድ
በሐኪም መሪነት የላቦራቶሪ ትርጓሜ የስራ ፍሰቶች ክሊኒካዊ ግምገማ።.
ባለሙያነት
በክሊኒካዊ አውድ ውስጥ ባዮማርከሮች እንዴት እንደሚሰሩ ላይ የላቦራቶሪ ሕክምና ትኩረት።.
ስልጣን ያለው
በዶክተር ቶማስ ክላይን የተፃፈ ከዶክተር ሳራ ሚቸል እና ፕሮፌሰር ዶክተር ሃንስ ዌበር ግምገማ ጋር።.
አስተማማኝነት
ለማስጠንቀቂያ ምላሽ መቀነስ ግልጽ የቀጣይ መንገዶች ያለው በማስረጃ የተደገፈ ትርጓሜ።.