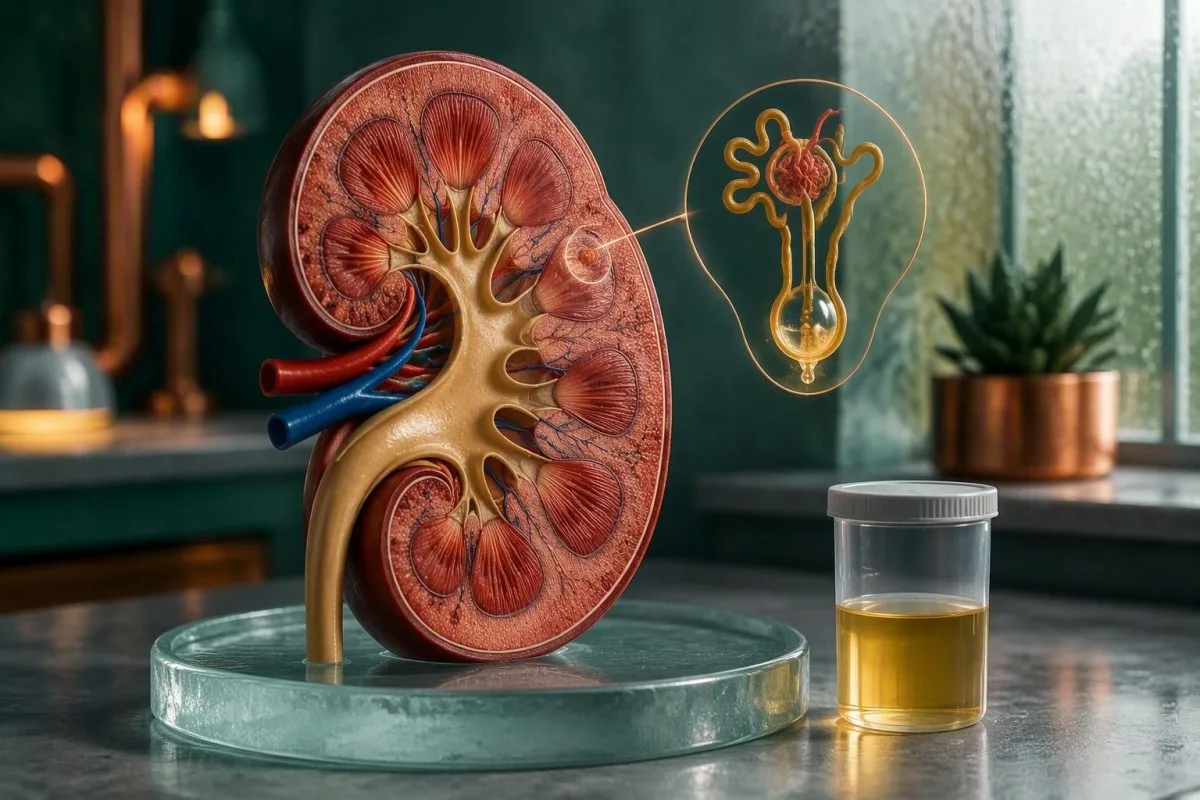
A low or high urine creatinine concentration usually reflects how diluted the sample was, not kidney damage by itself. The more useful question is whether the albumin-creatinine ratio or protein-creatinine ratio remains abnormal on a properly collected sample.


- Spot urine creatinine commonly varies from about 20 to 320 mg/dL because fluid intake changes concentration dramatically.
- Low urine creatinine below 20 mg/dL often indicates a very dilute random sample; it does not independently diagnose poor kidney function.
- Albumin-creatinine ratio below 30 mg/g is KDIGO category A1, 30-300 mg/g is A2, and above 300 mg/g is A3.
- Protein-creatinine ratio near 0.15 g/g or less is generally expected in adults; values above 0.5 g/g deserve clinical review.
- Ihi sa unang buntag is preferred for confirming a raised albumin-creatinine ratio because it reduces posture and hydration variation.
- Timed urine collection is useful when spot ratios conflict with symptoms, body size, pregnancy, or suspected heavy protein loss.
- Balik nga pagsulay after fever, vigorous exercise, urinary infection, menstruation, or dehydration prevents many false alarms.
- dali nga pagrepaso is appropriate for swelling, breathlessness, visible blood in urine, reduced urine output, or a protein-creatinine ratio near 3.5 g/g.
What a Random Urine Creatinine Result Actually Measures
Urine creatinine measures concentration in that one urine sample, not the amount of creatinine circulating in your blood. A result can shift from 35 mg/dL to 180 mg/dL in the same person within hours simply because one sample was collected after several glasses of water and the other after sleep.
A random laboratory result is usually reported in mg/dL or mmol/L. Many laboratories see roughly 20-320 mg/dL in adult spot specimens, but that broad interval is a specimen-quality clue rather than a personal target. In practice, I interpret the colour, specific gravity, timing, and requested ratio before reacting to the isolated number; our giya sa urine dipstick explains why those findings belong together.
Creatinine enters urine after filtration and a modest amount of tubular secretion. A concentrated morning specimen may read 220 mg/dL while total daily creatinine output remains entirely ordinary. By contrast, serum creatinine and eGFR address filtration in the bloodstream; they should never be substituted for a spot urine concentration.
As of September 17, 2026, Kantesti is an AI blood test analyzer that reads urine creatinine alongside serum creatinine, eGFR, albumin, and collection timing rather than treating one spot value as a diagnosis. That distinction has prevented a fair amount of needless anxiety in my clinical work.
Concentration is not excretion
A spot concentration answers “how much creatinine is in this cup right now?” A 24-hour value answers “how much creatinine left the body in a day?” Those are related measurements, but clinically they are not interchangeable.
Why Low Urine Creatinine Is Usually a Dilution Finding
Low urine creatinine most often results from a dilute specimen caused by high fluid intake, a short bladder-holding time, or collection later in the day. In many specimen-validity settings, less than 20 mg/dL is flagged as dilute, although medical laboratories must interpret it with the full clinical picture.
A patient who drinks 1-2 litres rapidly before an appointment can produce urine with creatinine below 20 mg/dL and a very low specific gravity. Diuretics, diabetes with high urine volume, pregnancy, and recovery from intravenous fluids can produce the same pattern. A dilute specimen may also make albumin concentration look low in mg/L, which is exactly why ratios were developed.
Low muscle mass can lower daily creatinine production, especially in frail older adults, people with neuromuscular disease, and those with substantial recent weight loss. A 45-kg adult may have a lower creatinine denominator than a 95-kg strength athlete, so an albumin ratio can look higher even when absolute albumin loss is modest. This is one limitation clinicians should say out loud.
Low urine creatinine with thirst, frequent urination, glucose in urine, or an elevated blood glucose needs a broader review, not just a repeat cup. Our guide to frequent urination tests covers the common metabolic and urinary causes.
Why High Urine Creatinine Often Means Concentrated Urine
High urine creatinine in a spot sample usually means concentrated urine after reduced intake, sweating, vomiting, diarrhoea, or an early-morning collection. A value above 300 mg/dL can occur in a concentrated specimen and does not, on its own, prove excess muscle breakdown or impaired kidney filtration.
I see this after endurance events more often than patients expect. A 52-year-old runner may submit a dark specimen at 7 am after a long run and show urine creatinine of 290 mg/dL; if serum creatinine, CK, blood pressure, and urine microscopy are reassuring, hydration and a later repeat often clarify the picture. Read more about creatinine human sa ehersisyo.
A concentrated sample can exaggerate albumin and protein concentrations expressed as mg/L, but a ratio should partly correct that effect. “Partly” matters: very concentrated or very dilute samples are mathematically less stable, particularly near decision cutoffs. Laboratories occasionally add a comment when urine creatinine is extremely low because ratio reliability becomes questionable.
Kantesti is an AI blood test interpretation platform that identifies discordance between a high spot urine creatinine concentration and signs of systemic dehydration, including raised sodium, urea, or haematocrit. Ang BUN and creatinine relationship can add useful context, although it does not diagnose dehydration by itself.
How the Urine Creatinine Ratio Corrects for Dilution
A urine creatinine ratio divides albumin or total protein by urine creatinine so that a watery or concentrated sample is less misleading. Albumin-creatinine ratio is commonly reported as mg/g in the United States and mg/mmol in the UK and many other countries.
The formula is straightforward: urine albumin divided by urine creatinine. For example, albumin 18 mg/L with creatinine 0.6 g/L produces an ACR of 30 mg/g, not simply “albumin 18.” This correction is why a ratio can uncover clinically relevant albumin loss in a pale sample that otherwise appears almost normal.
For international conversion, 1 mg/mmol is approximately 8.84 mg/g. An ACR of 3 mg/mmol is therefore about 27 mg/g, close to the usual A1-A2 boundary. Unit confusion is surprisingly common when patients compare reports from different countries, so I recommend recording both the number and unit in a results log.
The 2024 KDIGO chronic kidney disease guideline recommends confirming an elevated random ACR with a first-morning void when possible (KDIGO, 2024). Our giya sa pag-andam sa ACR explains how to collect that sample without artificially overhydrating.
Albumin-Creatinine Ratio Cutoffs That Change Follow-Up
An albumin-creatinine ratio below 30 mg/g is category A1, 30-300 mg/g is moderately increased albuminuria or A2, and above 300 mg/g is severely increased albuminuria or A3. Persistent A2 or A3 results deserve assessment with eGFR, blood pressure, diabetes status, and urine microscopy.
The 30 mg/g cutoff exists because albumin excretion above this level, when persistent, predicts higher kidney and cardiovascular risk more reliably than a single dipstick trace. ACR of 30-300 mg/g corresponds roughly to 3-30 mg/mmol; ACR above 300 mg/g corresponds to over 30 mg/mmol. The threshold is a risk category, not a sudden switch from safe to dangerous.
Diabetes, hypertension, sleep apnoea, obesity, smoking, heart failure, and inflammatory kidney conditions can raise ACR. Temporary increases also occur after fever, urinary infection, uncontrolled blood pressure, and strenuous exercise. In my experience, repeating before labelling someone with chronic disease is humane and medically sound when the initial elevation is modest.
KDIGO defines chronic kidney disease as an abnormality present for at least 3 months, not one result after a difficult week (KDIGO, 2024). For a wider framework, see our mga CKD stages at gabay sa ACR.
Protein-Creatinine Ratio Versus Albumin-Creatinine Ratio
Protein-creatinine ratio measures total urinary protein, whereas albumin-creatinine ratio measures albumin specifically. PCR is especially useful when a clinician suspects non-albumin protein loss, such as tubular disease or light-chain proteinuria.
A PCR below about 150 mg/g, or 0.15 g/g, is generally expected in adults, though reporting conventions vary. A PCR of 500 mg/g equals 0.5 g/g and warrants follow-up in most settings, particularly if it persists. A PCR around 3.5 g/g can approximate nephrotic-range protein loss and needs prompt evaluation rather than casual retesting.
When PCR is high but ACR is relatively low, clinicians consider tubular protein, monoclonal light chains, and occasionally sample interference. This is not a diagnosis of myeloma, but it is a pattern that changes the next test: urine and serum protein electrophoresis, free light chains, microscopy, and kidney assessment may be appropriate. See our explanation of the free light chain ratio.
Conversely, ACR is usually preferred for diabetes and hypertension monitoring because albumin is the earliest consistently validated marker of glomerular barrier stress. Kantesti AI interprets urine creatinine ratios by preserving the laboratory’s original units, rather than silently converting a mg/mmol result into a mg/g category.
Collection Details That Can Distort Urine Creatinine Ratios
First-morning midstream urine is the most reproducible sample for albumin-creatinine testing because it reduces hydration, exercise, and upright-posture effects. A random sample remains useful, but it should be repeated when it is borderline or clinically unexpected.
Avoid intense exercise for 24 hours before a planned repeat if your clinician agrees. Hard exercise can transiently raise albumin excretion and create a misleading ACR; long distance running can also cause temporary blood in urine. Our explanation of runner’s haematuria addresses when that is benign and when it is not.
Menstruation, visible blood, semen contamination, urinary infection, fever, and recent catheterisation can affect protein and albumin measurements. A clean-catch midstream specimen reduces contamination from skin cells and genital secretions. If epithelial cells are abundant, the epithelial cells in urine guide can help explain why a recollection is often sensible.
Do not force fluids before testing. Normal drinking is enough; an artificially clear sample may produce creatinine below 20 mg/dL and a ratio that your laboratory cannot interpret confidently.
When a Repeat Urine Creatinine Test Is the Right Next Step
Repeat a urine albumin or protein ratio when the first result is mildly abnormal, the sample is very dilute, or a temporary trigger was present. For a stable person without red flags, a first-morning repeat within 1-2 weeks is often reasonable, with persistence assessed over at least 3 months.
I generally repeat an ACR of 30-100 mg/g after infection resolves, after avoiding strenuous exercise, and when blood pressure is back to usual. A result over 300 mg/g, especially with reduced eGFR or swelling, should prompt earlier clinician contact rather than waiting months. The exact timetable depends on pregnancy, diabetes, medication use, and symptoms.
Transient albuminuria is more common than most online summaries admit. Orthostatic proteinuria, seen mainly in adolescents and young adults, can yield daytime protein but a normal first-morning ratio; comparing these samples can spare a young person invasive testing. Persistent proteinuria is different and should not be dismissed as “just hydration.”
Dr. Thomas Klein’s practical rule is simple: repeat the collection under controlled conditions, not the entire story. If a result remains abnormal, compare it with previous values using a checklist sa pagsubaybay sa laboratoryo rather than focusing on a single flagged line.
When a 24-Hour Timed Urine Collection Adds Value
A 24-hour urine collection is useful when a spot ratio conflicts with symptoms or clinical findings, when protein loss may be heavy, or when accurate daily excretion will guide treatment. It is not automatically more accurate; a missed or extra void can make it less reliable than a carefully collected spot ratio.
Expected daily creatinine excretion is roughly 15-20 mg/kg/day in many adult women and 20-25 mg/kg/day in many adult men, with large variation from age, diet, muscle mass, and mobility. Laboratories use this value as a rough completeness check. A surprisingly low daily creatinine may mean missed collections, while a very high value can mean an extra specimen was added.
Timed collections are particularly helpful for stone risk, selected endocrine testing, pregnancy complications, and quantifying substantial proteinuria. They can also clarify a ratio in someone with very low muscle mass, where the creatinine denominator is unusually small. The collection process itself has traps; our Giya sa pagkolekta og 24-oras nga ihi describes the common ones.
Keep the container as instructed, collect every void including the final one at the exact end time, and document spills. A collection that is “almost complete” is often not clinically interpretable; that small detail genuinely changes management.
Urine Creatinine Interpretation in Pregnancy, Athletes and Older Adults
Pregnancy, high-level sport, and low muscle mass alter urine creatinine interpretation because creatinine production and urine volume differ from the average adult. The ratio may remain useful, but thresholds, timing, and clinical urgency change.
In pregnancy, proteinuria can develop quickly with hypertensive disorders. A PCR of 0.3 g/g or more is widely used as a clinically significant threshold in the appropriate setting, but symptoms and blood pressure matter more than a home interpretation. Headache, visual changes, right upper abdominal pain, sudden swelling, or high blood pressure merit same-day maternity assessment; see our HELLP laboratory warning signs.
Athletes often have a high daily creatinine output from larger muscle mass and transient albuminuria after exertion. Testing after 24-48 hours of usual recovery can be more informative than a post-race sample. A high spot urine creatinine in an athlete is usually concentration, not a measure of “excellent kidneys.”
Older adults with sarcopenia can have low serum and urine creatinine despite reduced filtration, so cystatin C, eGFR trend, and ACR may be more informative together. Our Kinatibuk-ang pagtan-aw sa cystatin C explains why this alternative marker is sometimes requested.
Medicines and Illnesses That Change Urine Creatinine Results
Diuretics, SGLT2 inhibitors, NSAIDs, lithium, and acute illnesses can change urine volume, albumin excretion, or kidney filtration and therefore alter urine creatinine interpretation. Medication effects should be reviewed against serum creatinine, eGFR, potassium, blood pressure, and the reason the medicine was prescribed.
Diuretics can concentrate urine, while SGLT2 inhibitors increase urine glucose and volume early in treatment. Neither medication makes a spot urine creatinine result diagnostic on its own. An early eGFR dip after an SGLT2 inhibitor can be expected, but a sustained decline, dizziness, or dehydration calls for prescriber review; our giya sa SGLT2 eGFR provides context.
NSAIDs can reduce kidney blood flow in vulnerable people, especially during vomiting, diarrhoea, or diuretic treatment. Lithium requires particular care because chronic exposure can affect concentrating ability and kidney function; review our lithium monitoring tests if this applies to you.
Kantesti is an AI-powered blood test analysis tool that can organise medication dates with kidney-result trends, but it cannot decide whether a prescribed medicine should be stopped. That decision belongs with the clinician who knows the indication, dose, blood pressure, and current symptoms.
What to Do When Urine Creatinine and Other Kidney Results Disagree
A low urine creatinine with normal eGFR usually reflects specimen dilution, whereas albuminuria with declining eGFR suggests a more meaningful kidney pattern. Discordant findings should trigger a check of timing, hydration, blood pressure, diabetes control, microscopy, and repeat testing rather than a quick conclusion.
Consider a person with urine creatinine 12 mg/dL, ACR 55 mg/g, eGFR 98 mL/min/1.73 m², and a sample taken after excessive water intake. The ratio may still be valid enough to take seriously, but its denominator is weak; I would usually confirm a first-morning ACR before diagnosing persistent albuminuria. One number rarely earns a label.
The converse matters too: normal ACR does not rule out every kidney problem. Blood in urine, casts, rapidly rising serum creatinine, electrolyte disturbance, or systemic autoimmune symptoms need a different pathway. Granular casts, for example, change the urgency and differential diagnosis; our gabay sa granular casts nagpasabot kung nganong.
Kantesti’s medikal nga balidasyon nga framework requires contextual flags for contradictory laboratory patterns rather than a simplistic normal/abnormal verdict. In a patient with symptoms, a clinician should always overrule an algorithmic reassurance.
When Urine Protein or Creatinine Results Need Prompt Care
Seek prompt medical assessment for urine protein with new swelling, shortness of breath, visible blood in urine, markedly reduced urine output, severe headache with high blood pressure, or a rapid eGFR fall. Urine creatinine concentration alone is rarely an emergency, but the pattern around it sometimes is.
A PCR near or above 3.5 g/g, ACR above 2,000 mg/g, or proteinuria with low serum albumin can indicate substantial protein loss and should be assessed quickly. Foamy urine alone is not a reliable measure of protein, but persistent foam plus ankle swelling merits testing. Our article on padayon nga mabula nga ihi nagpasabot sa kalainan.
Visible blood, flank pain, fever, or clots require a different level of attention because infection, stones, obstruction, and glomerular disease are possibilities. A negative nitrite test does not exclude a urinary infection, especially with frequent urination or fever. Do not wait for a ratio repeat if you are unwell.
Dr. Thomas Klein advises treating severe symptoms as the priority, not as an add-on to laboratory interpretation. Emergency care is appropriate for confusion, severe breathlessness, chest pain, fainting, or inability to pass urine.
A Practical Plan for Your Next Urine Creatinine Test
For the most reliable urine creatinine ratio, collect a first-morning clean-catch midstream sample, maintain normal fluid intake, avoid unusually hard exercise for 24 hours, and tell the laboratory about menstruation or urinary symptoms. Bring previous eGFR, ACR, PCR, blood pressure, and medication information to the review.
Write down the collection time, whether you exercised the day before, recent fever or urinary symptoms, and major fluid changes. This modest record often explains a 2-fold ratio difference better than a dramatic biological change. For support reading a complete panel, our giya sa mga biomarker puts kidney markers into their wider laboratory context.
Ask three focused questions: Was the specimen dilute? Do I need a first-morning repeat? Does the ratio persist for 3 months or coexist with low eGFR, hypertension, diabetes, blood, or casts? Those questions help turn a confusing result into a sensible care plan without either panic or false reassurance.
Ang among mga doktor sa Lupon sa Medikal nga Magtatambag review the clinical principles behind Kantesti’s interpretations. Kantesti AI is an AI lab test interpretation service designed to make the next clinical question clearer, not to replace examination, diagnosis, or treatment from your own care team.
Kanunay nga Gipangutana nga mga Pangutana
Unsay buot ipasabot sa ubos nga urine creatinine?
Ang ubos nga urine creatinine sa random specimen kasagaran nagpasabot nga ang ihi kay gipamala tungod sa taas nga pag-inom ug pluwido, kasubsob nga pag-ihi, diuretics, o mubo nga panahon sukad sa kataposang pag-ihi. Ang bili nga ubos sa 20 mg/dL kasagaran gipahibalo nga gipamala sa trabaho sa specimen-validity, apan kini dili independente nga mag-diagnose sa gipamaba nga pag-andar sa kidney. Ang ubos nga kaunoran mahimo usab nga makapamaba sa adlaw-adlaw nga creatinine excretion. Kung ang albumin-creatinine ratio dili normal sa usa ka gipamala nga specimen, ang unang-buntag nga balik-balik sagad mao ang labing mapuslanon nga sunod nga lakang.
Delikado ba ang taas nga urine creatinine?
Ang taas nga konsentrasyon sa ihi nga creatinine dili kasagaran delikado sa iyang kaugalingon tungod kay kini sagad nagpakita sa dako nga ihi pagkahuman sa pagpuasa sa gabii, pagpasingot, pagsuka, kalibanga, o pagkunhod sa pag-inom og pluwido. Ang mga kantidad sa spot nga labaw sa 300 mg/dL mahimong mahitabo sa concentrated samples nga walay timailhan sa pagkapakyas sa kidney. Ang mga klinikal nga importanteng resulta mao ang padayon nga taas nga albumin-creatinine ratio, taas nga protein-creatinine ratio, pag-ubos sa eGFR, dugo sa ihi, paghubag, o taas nga presyon sa dugo. Kinahanglan nga hubad-on sa usa ka clinician ang taas nga ihi nga creatinine uban sa ihi nga specific gravity ug serum kidney results.
Unsa ang normal nga urine creatinine ratio?
Alang sa albumin-creatinine ratio, ubos sa 30 mg/g, o ubos sa 3 mg/mmol, mao ang KDIGO category A1 ug normal o medyo taas. Ang ACR nga 30-300 mg/g mao ang category A2, samtang ang ACR nga labaw sa 300 mg/g mao ang category A3. Alang sa total protein-creatinine ratio, mga 0.15 g/g o ubos pa kay kasagarang gipaabot sa mga hamtong, bisan og lainlain ang mga limitasyon sa reference sa laboratoryo. Ang mga ratio kinahanglang kumpirmahon gamit ang unang sample sa buntag kon ang mga resulta borderline o wala damha.
Makapaubos ba ang pag-inom ug tubig sa creatinine sa ihi?
Oo, ang pag-inom ug daghang tubig makapaubos sa konsentrasyon sa urine creatinine sulod sa pipila ka oras tungod kay ang parehong adlaw-adlaw nga output sa creatinine natunaw sa mas daghang ihi. Ang usa ka sample nga dili kaayo diluted mahimong magpakita og urine creatinine ubos sa 20 mg/dL ug mahimong dili kaayo lig-on ang interpretasyon sa ratio duol sa usa ka clinical cutoff. Mas maayo ang normal nga pag-inom ug pluwido sa dili pa mag-test; ang tinuyo nga pagpugong o pagpugos sa pluwido makadaut sa mga resulta. Ang unang ihi sa buntag kasagaran naghatag sa labing makanunayon nga konsentrasyon alang sa balik-balik nga ACR testing.
When is a 24-hour urine test better than a spot urine ratio?
A 24-hour urine test is useful when a spot ratio conflicts with symptoms or other kidney findings, when protein loss may be heavy, or when a clinician needs total daily excretion for a specific decision. Daily creatinine excretion is often roughly 15-20 mg/kg in adult women and 20-25 mg/kg in adult men, but age and muscle mass create wide variation. Missing even one void can invalidate the collection, so a careful spot first-morning ratio is often better for routine screening. Timed collection decisions should be individualized by a clinician.
Should I worry about a high protein-creatinine ratio?
A persistent protein-creatinine ratio above 0.5 g/g generally deserves clinical review, while a ratio near 3.5 g/g can indicate nephrotic-range protein loss and requires prompt assessment. The urgency rises when proteinuria occurs with swelling, low serum albumin, high blood pressure, blood in urine, or reduced eGFR. Exercise, fever, urinary infection, and pregnancy can temporarily raise urinary protein, so repeat testing may be appropriate when symptoms are absent. Do not rely on urine foam alone to estimate protein loss.
Karon na ang AI-Powered Blood Test Analysis
Apil sa kapin sa 2 milyon nga mga user sa tibuok kalibutan nga nagsalig sa Kantesti para sa dayon ug tukma nga pag-analisa sa lab test. I-upload ang imong resulta sa blood test ug makadawat og komprehensibong pagsabot sa 15,000+ nga mga biomarker sulod sa mga segundo.
📚 Mga Napangalan nga Research Publications
Klein, T., Mitchell, S., & Weber, H. (2026). Clinical Validation Framework v2.0 (Panid sa Balidasyon sa Medikal). Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2.5M nga mga Pagsulay ang Gisusi | Global Health Report 2026. Kantesti AI Medical Research.
📖 Mga Panlabas nga Sanggunian sa Medisina
⚕️ Pagpasabot sa Medikal
Kini nga artikulo para sa katuyoan sa edukasyon ra ug dili kini mosangpot sa medikal nga tambag. Kanunay mokonsulta sa usa ka kwalipikado nga healthcare provider alang sa mga desisyon sa diagnosis ug pagtambal.
Mga E-E-A-T Trust Signals
Kasinatian
Pagsusi sa klinika nga gipangulohan sa doktor sa mga workflow sa interpretasyon sa lab.
Kahanas
Pokus sa medisina sa laboratoryo kung giunsa paglihok ang mga biomarker sa konteksto sa klinika.
Pagka-awtorisado
Gisulat ni Dr. Thomas Klein ug gisusi ni Dr. Sarah Mitchell ug Prof. Dr. Hans Weber.
Kasaligan
Interpretasyon nga base sa ebidensya, nga adunay klaro nga mga agianan sa sunod nga buhat aron makunhuran ang kabalaka.