
Topiramate concentrations are not routinely checked because treatment response and side effects do not map reliably to one target number. Testing can clarify medication exposure or altered clearance; bicarbonate and kidney-function tests answer separate safety questions.

Conclusions principals
- Topiramate level testing is usually reserved for a specific question, such as unexpected seizures, suspected missed doses, interactions, or changed kidney function.
- Topiramate therapeutic range is commonly reported as 5–20 mg/L, but some laboratories use 2–10 mg/L; neither interval guarantees effectiveness or safety.
- Moment de la presa de la mostra vall means collecting the sample immediately before the next scheduled dose, with the last dose time documented.
- Estat estacionari usually develops in about 4 days when kidney function is normal and the dose is unchanged; reduced clearance can extend this interval.
- Conversió d’unitats és senzill: 1 mg/L equival a 1 µg/mL, de manera que 8 mg/L i 8 µg/mL descriuen la mateixa concentració.
- Toxicity assessment requires symptoms, examination, medication history, and relevant laboratory findings; no universal topiramate concentration establishes toxicity.
- Bicarbonate monitoring checks for metabolic acidosis, a recognized topiramate effect that can occur despite a concentration inside the laboratory interval.
- Kidney-function monitoring helps assess drug clearance; prescribing information recommends dose adjustment when adult creatinine clearance is below 70 mL/min/1.73 m².
Why is a topiramate level not routinely checked?
A topiramate level is not routinely checked because the relationship between concentration, benefit, and adverse effects varies substantially between people. A commonly quoted interval of 5–20 mg/L is a laboratory reference tool—not a number every patient must reach, and not a boundary that reliably separates safe treatment from toxicity.

Routine concentration-guided dosing has not been shown to improve outcomes for every person taking topiramate. The ILAE position paper supports therapeutic drug monitoring when a result can answer a defined clinical question, rather than ordering levels automatically for all antiseizure medicines (Patsalos et al., 2008); seizure frequency, migraine days, and tolerability remain central to treatment decisions.
For example, a hypothetical adult whose migraines improve on 50 mg twice daily does not necessarily need a dose increase because the laboratory flags a concentration below 5 mg/L. Migraine prevention does not have a well-established serum target; increasing treatment solely to correct the flag could worsen word-finding difficulty or appetite loss without adding meaningful benefit.
Kantesti is an AI blood test analyzer that helps explain why a 5–20 mg/L laboratory interval cannot replace assessment of symptoms and sample timing. Our organització i propòsit describe our role in interpreting reports; we do not prescribe medication, and an AI explanation should not become a reason to change a stable regimen independently.
What does a Topamax level test actually measure?
A Topamax level test measures the concentration of topiramate in a laboratory sample, usually serum or plasma. It reports medication exposure at the collection time—not the prescribed dose, seizure protection, or bicarbonate status; 1 mg/L equival a 1 µg/mL, which prevents a common unit-reading mistake.

Many laboratories measure topiramate using liquid chromatography with tandem mass spectrometry, although methods and acceptable sample containers vary. A result of 8 µg/mL is exactly the same concentration as 8 mg/L; by contrast, a prescription of 100 mg describes an administered amount and cannot be compared directly with either concentration unit.
Topiramate is relatively weakly protein-bound, with prescribing information describing approximately 15–41% binding. Routine testing generally measures total concentration, and there is no standard albumin-correction equation equivalent to approaches sometimes used for phenytoin; our explanation of free versus total phenytoin shows why interpretation rules should not be transferred indiscriminately between medicines.
A laboratory report listing topiramate at 6 mg/L and total CO2 at 19 mmol/L contains 2 fundamentally different measurements. The first reflects drug exposure; the second usually approximates serum bicarbonate and may indicate an acid–base problem, so a concentration inside the printed interval cannot dismiss an abnormal chemistry result.
What is the topiramate therapeutic range?
A commonly quoted topiramate therapeutic range is 5–20 mg/L, but some European laboratories use 2–10 mg/L. These intervals mainly support epilepsy-related interpretation; they are not universally validated treatment targets, and there is no widely accepted serum concentration target for migraine prevention.

Jacob and Nair's review lists a topiramate reference concentration of 5–20 mg/L while emphasizing selective use of monitoring and variable concentration–response relationships (Jacob and Nair, 2016). A reference interval summarizes concentrations considered useful in a population; it does not establish that every individual below its lower limit needs more medication.
Different laboratory intervals can produce different flags for the same number. A hypothetical trough of 12 mg/L sits within a 5–20 mg/L interval but above a 2–10 mg/L interval; that disagreement should trigger review of the laboratory's convention and the patient's clinical state, not an assumption that the medicine became toxic between reports.
An individual's previously effective, well-tolerated concentration can be more informative than the population interval. If someone remained seizure-free at a correctly timed trough of 4 mg/L, that documented baseline may help interpret a later change; the same individual-baseline principle appears in la interpretació dels resultats de levetiracetam, although the numerical ranges are different.
| Nivell | Interval | Què significa |
|---|---|---|
| Interval habitual de laboratori | 5–20 mg/L | A frequently quoted epilepsy-related reference interval, not a guaranteed effective or safe target. |
| Alternative laboratory interval | 2–10 mg/L | Used by some European laboratories; interpretation must follow the reporting laboratory and clinical context. |
| Above a 5–20 interval | >20 mg/L | Prompts review of symptoms, timing, dose, interactions, and clearance; does not establish toxicity by itself. |
| Individual reference concentration | Patient-specific; no universal cutoff | A prior correctly timed concentration obtained during effective, tolerated treatment can guide later comparisons. |
When can topiramate concentration monitoring help?
Topiramate concentration monitoring helps when clinicians need to distinguish changed medication exposure from other causes of worsening control or new adverse effects. Comparing 2 similarly timed samples can be useful after suspected missed doses, kidney-function changes, interacting medicines, pregnancy-related clearance changes, or an unexplained treatment failure.

Unexpected breakthrough seizures are one reason to investigate exposure, but the concentration cannot diagnose the cause of the event. The ILAE position paper identifies situations such as suspected nonadherence, toxicity, pharmacokinetic variability, and changing treatment conditions as appropriate reasons to consider monitoring (Patsalos et al., 2008); sleep deprivation, illness, and seizure classification still need separate assessment.
Establishing a personal reference concentration can help before an anticipated change. For a hypothetical person stable on 100 mg twice daily, a trough obtained during seizure control provides a comparison if kidney function later declines or another antiseizure drug is withdrawn; without that baseline, a later isolated result may be harder to interpret.
A test is less helpful if nobody can state what management decision it might change. Before requesting a concentration of 7 mg/L or any other result, ask whether the question concerns adherence, clearance, or possible adverse effects; our lacosamide monitoring explanation illustrates why selective monitoring is not the same as having no monitoring strategy.
When should the topiramate sample be collected?
For planned monitoring, a trough sample immediately before the next scheduled dose is usually the most comparable measurement. Topiramate's elimination half-life is approximately 21 hours in adults with normal kidney function, and steady state is generally reached in about 4 dies after an unchanged regimen begins.

Collection timing depends on the regimen, not on a universal morning rule. A twice-daily schedule may produce a trough around 12 hours after the preceding dose, whereas once-daily extended-release treatment involves a different interval; document the actual formulation, last dose time, collection time, and any recent missed doses rather than assuming the schedule was followed.
Steady state takes approximately 4–5 elimination half-lives, so reduced kidney clearance can make the usual 4-day estimate too short. A sample taken 1 day after a dose increase may not reflect the eventual concentration; Jacob and Nair discuss the pharmacokinetic basis for timing interpretation rather than treating every sample as equivalent (Jacob and Nair, 2016).
Kantesti AI helps distinguish a reported topiramate concentration of 10 mg/L from the circumstances needed to interpret it, including whether the sample was a trough. Our guide to trough timing principles explains the general concept, but tacrolimus targets and sampling protocols must not be applied to topiramate; urgent assessment should never wait for an ideal trough.
Does a low topiramate level prove missed doses?
A low topiramate level does not prove nonadherence. Un resultat per sota de 5 mg/L could reflect a modest dose, faster clearance, an interacting medicine, recent treatment changes, or collection timing; a fall from the person's own comparable baseline is often more informative than a low flag alone.

Consider a hypothetical trough that falls from 8 mg/L to 3 mg/L on an apparently unchanged prescription. That pattern warrants checking missed doses and refill access, but also whether an enzyme-inducing medicine was added, whether the earlier sample was actually post-dose, and whether the daily dose or formulation changed without being reflected in the laboratory request.
An undetectable result can strengthen suspicion of little recent exposure, but the assay's detection limit and elapsed time still matter. With an approximately 21-hour half-life, topiramate does not disappear immediately after 1 missed dose; a single concentration cannot reconstruct weeks of medication-taking behavior or distinguish intentional omission from vomiting, supply problems, or misunderstanding instructions.
The practical response is to review barriers before escalating treatment. If a dose is increased after a low result and regular dosing then resumes, exposure may rise unexpectedly; our lamotrigine concentration guide discusses a related monitoring problem, but each medicine requires its own missed-dose and restarting instructions rather than a shared numerical rule.
Can a high topiramate level establish toxicity?
A high topiramate level cannot establish toxicity by itself, and a result inside the laboratory interval cannot exclude it. A concentration above 20 mg/L may support concern about excessive exposure, but clinicians must assess symptoms, dosing history, kidney function, acid–base status, and other medicines.
Two hypothetical results show the limitation: 22 mg/L in an alert person after a post-dose sample is not equivalent to 10 mg/L in someone with new severe confusion and low bicarbonate. Neither situation should be interpreted from the number alone; cognitive slowing, dizziness, and impaired coordination may be medication-related even at concentrations the laboratory does not flag.
Sudden eye pain or blurred vision during topiramate treatment needs urgent assessment because acute myopia and secondary angle closure can occur, often within the first month of treatment. A level of 6 mg/L would not make that presentation safe to observe at home; glaucoma assessment methods address eye pressure and anatomy, which a drug concentration cannot measure.
Suspected overdose, markedly reduced alertness, breathing difficulty, or a prolonged seizure requires emergency evaluation without waiting for a send-out concentration result. A seizure lasting 5 minutes is an emergency threshold, and sudden one-sided weakness or new speech difficulty should also prompt emergency action rather than being attributed to topiramate; our signes d’alarma d’ictus expliquen aquesta distinció.
How does kidney function affect topiramate clearance?
Reduced kidney function can increase topiramate serum concentration perquè aproximadament 70% of an administered dose is eliminated unchanged in urine. Adult prescribing information recommends a reduced dose when creatinine clearance is below 70 mL/min/1.73 m², but a clinician must apply that advice to the indication and individual circumstances.
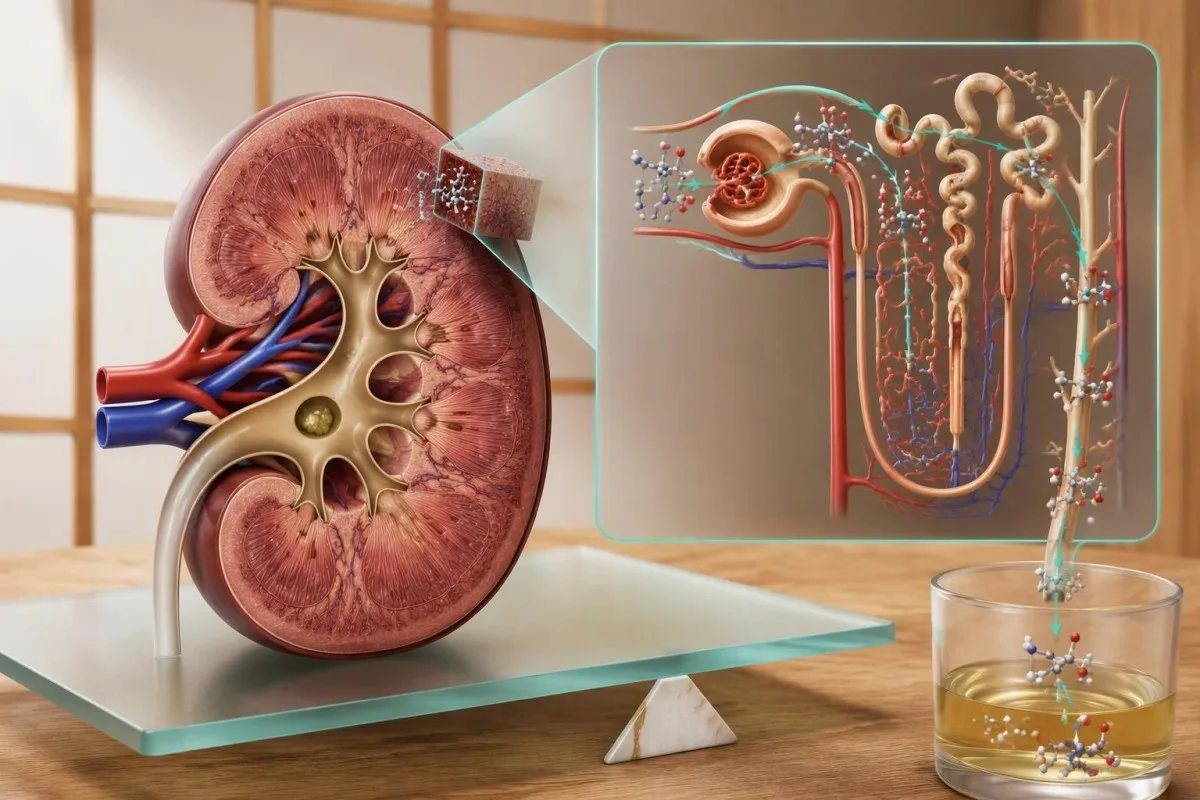
A hypothetical adult with an estimated creatinine clearance of 50 mL/min/1.73 m² may need a different regimen from someone with normal clearance, even if both have the same seizure type. Labeling commonly recommends one-half of the usual adult dose in renal impairment below the stated threshold; that is prescribing guidance, not permission to halve an existing prescription without review.
Creatinine-based eGFR and creatinine clearance are not automatically interchangeable, especially at unusual body sizes or during acute kidney injury. An eGFR of 45 mL/min/1.73 m² signals a need to review clearance, but the appropriate dosing calculation and the reliability of a rapidly changing creatinine require clinical judgment; our guia d’avaluació de l’eGFR baix explains when changes need prompt attention.
Kantesti is an AI blood test interpretation platform that helps separate a topiramate result of 14 mg/L from the kidney measurements that may explain it. Our guia de BUN i creatinina adds context, but a creatinine concentration alone cannot prove medication accumulation; sample timing, hydration, previous results, and the actual dosing history still matter.
Which medicines can change a topiramate result?
Enzyme-inducing antiseizure medicines can lower topiramate concentrations, while some other combinations increase exposure or adverse-effect risk without a predictable level change. Prescribing-information interaction studies report approximately 40% lower topiramate concentrations with carbamazepine i 48% lower concentrations with phenytoin, although individual effects vary.

Stopping an inducing medicine can raise topiramate exposure even when the topiramate prescription stays unchanged. For example, a hypothetical person taking 100 mg twice daily may develop more cognitive adverse effects after carbamazepine is withdrawn; our carbamazepine monitoring guide explains that medicine's own concentration monitoring, which remains separate from assessing its effect on topiramate clearance.
Hydrochlorothiazide increased topiramate exposure by approximately 29% in a pharmacokinetic study described in prescribing information, and the combination can also increase potassium loss. That percentage describes the studied group, not a guaranteed change for every patient; checking potassium and symptoms may be useful even if a repeat topiramate concentration remains inside a 5–20 mg/L interval.
Topiramate with valproate can be associated with hyperammonemia and encephalopathy, sometimes despite otherwise unremarkable routine laboratory results. New unexplained lethargy, vomiting, or altered mental status on these 2 medicines warrants prompt assessment and consideration of ammonia testing; a topiramate level is not a substitute, and our valproate result explanation describes why valproate concentrations also have interpretation limits.
Why is bicarbonate monitoring a different safety test?
Bicarbonate monitoring checks for metabolic acidosis, not topiramate exposure. Topiramate can cause renal bicarbonate loss through carbonic anhydrase inhibition; many laboratories use an adult bicarbonate interval around 22–29 mmol/L, and prescribing information recommends baseline and periodic measurement rather than relying on a drug level.

Topiramate typically causes a hyperchloremic, normal-anion-gap metabolic acidosis, although other conditions can create mixed patterns. Mirza and colleagues describe impaired renal acid–base handling and note that evidence for the optimal monitoring strategy is limited (Mirza et al., 2009); our patrons d'acidosi tubular renal explain why bicarbonate must be read with chloride, potassium, and the clinical history.
For a hypothetical chemistry panel with sodium 138 mmol/L, chloride 111 mmol/L, and bicarbonate 18 mmol/L, the anion gap excluding potassium is 138 − 111 − 18 = 9 mmol/L. That calculation is compatible with a normal-gap pattern in many laboratories, but it does not identify topiramate as the cause; diarrhea, other renal disorders, albumin changes, and mixed acid–base disturbances need consideration.
Kantesti AI explains why bicarbonate of 18 mmol/L deserves attention even when topiramate is 7 mg/L, while avoiding a diagnosis from those 2 numbers alone. Prescribing information uses bicarbonate below 17 mmol/L with a fall greater than 5 mmol/L as a trial definition of markedly low bicarbonate—not a universal emergency cutoff; our explicació del perfil d’electròlits helps interpret associated abnormalities.
What kidney safety checks does a drug level miss?
A topiramate concentration cannot detect kidney stones, measure urinary citrate, or establish renal tubular acidosis. Adult epilepsy development trials reported kidney stones in approximately 1.5% of topiramate-treated participants; risk depends on treatment context, and a concentration inside 5–20 mg/L does not eliminate the possibility.

Topiramate can increase urine pH and reduce urinary citrate, a combination that favors calcium phosphate stones. Mirza and colleagues link these urinary changes to carbonic anhydrase inhibition (Mirza et al., 2009); our guia de baix citrat en orina explains why a 24-hour urine assessment may become relevant after recurrent stones rather than being automatically required for every user.
Monitoring creatinine serves a different purpose from checking urinary stone risk. A hypothetical person with a topiramate level of 9 mg/L, normal creatinine, and recurrent flank pain still needs evaluation for stones; normal filtration does not guarantee normal urinary citrate, and persistent pain with fever, vomiting, or difficulty passing urine should not wait for a repeat drug concentration.
Adequate fluid intake is commonly advised, but there is no single safe target such as 3 liters daily for everyone. People with heart failure, advanced kidney disease, or a prescribed fluid restriction need individualized guidance; potassium citrate or bicarbonate treatment also requires clinician oversight because changing urine chemistry and potassium intake can create different risks from those measured by topiramate testing.
Who may need more individualized concentration monitoring?
Pregnancy, childhood, older age, and changing kidney function can make topiramate exposure less predictable. A personal pre-pregnancy concentration and 2 similarly timed follow-up samples may be more useful than chasing a population interval, but monitoring does not remove topiramate's pregnancy-related risks or replace specialist treatment planning.
Pregnancy can increase topiramate clearance, so a concentration may fall despite consistent dosing. Pregnancy also changes the interpretation of creatinine, and standard eGFR equations are not reliable for assessing filtration during pregnancy; our pregnancy kidney-function explanation explains why a apparently reassuring result should not be used to estimate drug clearance mechanically.
In the UK, topiramate is subject to a Pregnancy Prevention Programme for people who can become pregnant; it is contraindicated for migraine prevention during pregnancy and for epilepsy in pregnancy unless no suitable alternative exists. A level of 5 mg/L does not establish fetal safety, and someone who becomes pregnant should contact the prescriber promptly rather than abruptly stopping an antiseizure regimen.
Children may have higher weight-normalized clearance than adults, while older adults may clear the medicine more slowly because of reduced renal function. The adult 5–20 mg/L interval therefore needs context rather than a new age-based cutoff invented from a single report; pediatric dose decisions require specialist assessment, and post-pregnancy monitoring may matter if a dose was increased when clearance was higher.
How should you interpret a result with other findings?
Interpret a topiramate result by combining concentration, collection timing, symptoms, and safety chemistry. At minimum, compare 4 pieces of information: the current regimen, the last dose and sample times, the reason testing was ordered, and bicarbonate plus kidney-function results when available.

Hypothetical pattern 1: a trough falls from 8 to 3 mg/L, kidney function is stable, and seizures recur after several prescription refills were delayed. Reduced exposure is plausible, but the response should include a medication-access review and seizure assessment; raising the dose without addressing intermittent use could create excessive exposure when regular dosing resumes.
Hypothetical pattern 2: a trough rises from 9 to 16 mg/L while creatinine worsens and new coordination problems appear. Reduced clearance is a reasonable concern even though 16 mg/L remains inside a 5–20 mg/L interval; pattern 3, a level of 7 mg/L with bicarbonate of 18 mmol/L, instead highlights a possible acid–base effect that concentration monitoring alone would miss.
Kantesti is an AI-powered blood test analysis tool that helps organize these 3 patterns without treating any one as a confirmed diagnosis. Our guia de tendències de seguretat de medicaments explains how serial results support follow-up; keep the original laboratory interval and dates visible, because changing laboratories, formulations, or collection timing can make an apparent trend misleading.
What should you do next, and what evidence supports testing?
The next step is to ask what the topiramate result changes—not to adjust treatment from the number alone. Bring 2 informes datats, if available, and a medication timeline to the prescriber; monitoring recommendations rely on pharmacology, expert guidance, and clinical context rather than a universally validated toxicity threshold.
Ask the prescriber whether a repeat trough, bicarbonate check, kidney-function assessment, or medication review would answer the unresolved question. There is no evidence-based rule that every patient needs a topiramate concentration every 3 or 6 months; persistent low bicarbonate, new adverse effects, or changing clearance may justify a different follow-up plan from an isolated laboratory flag.
Kantesti helps explain reports, but our limitacions de la IA responsable distinguish educational interpretation from diagnosis and prescribing. Our enfocament de validació clínica provides methodology context; neither an AI confidence estimate nor a concentration of 10 mg/L can exclude toxicity, replace an examination, or authorize an independent dose change.
The 2 Zenodo publications listed below concern serum proteins and complement testing; they are not topiramate therapeutic-monitoring studies and should not be used to validate its concentration cutoffs. Our guia d'interpretació de proteïnes sèriques offers background for understanding albumin and other medicines, while the directly relevant external references support this article's discussion of selective monitoring, pharmacokinetics, and acid–base effects.
Preguntes freqüents
Quin és un nivell normal de topiramat?
Un interval de referència del topiramat citat habitualment és de 5–20 mg/L, tot i que alguns laboratoris fan servir 2–10 mg/L. Aquests intervals ajuden a interpretar els resultats, sobretot en l’epilèpsia, més que no pas a definir una concentració universalment normal o segura. Algunes persones poden respondre amb concentracions inferiors a l’interval indicat o experimentar efectes adversos dins d’aquest. Cal tenir en compte conjuntament l’interval del laboratori, el moment de la recollida de la mostra, els símptomes i una concentració prèvia eficaç.
Cal que em facin controls periòdics dels nivells de topiramat?
Most people do not need routine topiramate concentration testing on a fixed schedule. Testing may help with breakthrough seizures, suspected missed doses, interacting medicines, pregnancy-related changes, or reduced kidney clearance. There is no universally recommended concentration-testing interval such as every 3 or 6 months for all users. Baseline and periodic bicarbonate monitoring address a separate safety issue and may be appropriate even when drug levels are not measured.
When should a Topamax level test be taken?
A planned Topamax level test is usually most comparable when collected immediately before the next scheduled dose. With normal kidney function, topiramate generally reaches steady state in about 4 days after an unchanged regimen begins, but reduced clearance can extend that time. Record the last dose time, collection time, dose, and formulation. Suspected overdose or serious adverse effects require immediate assessment rather than waiting for a correctly timed trough.
Does a low topiramate serum concentration mean I missed doses?
A low topiramate serum concentration does not prove missed doses. A result below 5 mg/L can reflect a modest dose, increased clearance, an enzyme-inducing medicine, recent dose changes, or sample timing. A drop from a previous comparable trough, such as 8 to 3 mg/L, may provide stronger evidence of changed exposure. Clinicians should review medication access and dosing history before deciding whether the regimen needs adjustment.
What topiramate level is toxic?
There is no universally validated topiramate concentration that establishes toxicity. A result above 20 mg/L may prompt closer review, but some adverse effects occur inside commonly reported laboratory intervals. Symptoms, examination, kidney function, bicarbonate, other medicines, and the timing of the sample determine the clinical meaning. Suspected overdose, severe confusion, breathing difficulty, or sudden eye pain or visual change requires urgent assessment regardless of the measured level.
Can topiramate cause low bicarbonate with a normal drug level?
Topiramate can cause low bicarbonate even when its concentration is inside a laboratory interval such as 5–20 mg/L. Carbonic anhydrase inhibition can increase renal bicarbonate loss and produce hyperchloremic, normal-anion-gap metabolic acidosis. A bicarbonate result of 18 mmol/L warrants clinical interpretation but does not, by itself, prove topiramate is the cause or define emergency severity. Bicarbonate and kidney-function testing therefore cannot be replaced by a Topamax level test.
Fes que t’expliquin els resultats anàlisi de sang
Puja l’informe del laboratori i la IA de Kantesti t’explicarà cada biomarcador en llenguatge planer en qüestió de segons. Més de 2 milions de persones d’arreu del món ja l’han utilitzat.
Referències
- Klein, T., Mitchell, S., & Weber, H. (2026). Guia de les proteïnes sèriques: anàlisi de sang de globulines, albúmina i relació A/G. Recerca mèdica amb IA de Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Guia de les proves de sang C3 C4 del complement i del títol d'ANA. Recerca mèdica amb IA de Kantesti. DOI
- Patsalos PN et al. (2008). Antiepileptic drugs—best practice guidelines for therapeutic drug monitoring: a position paper by the subcommission on therapeutic drug monitoring, ILAE Commission on Therapeutic Strategies. Epilepsia. DOI
- Jacob S and Nair AB (2016). An Updated Overview on Therapeutic Drug Monitoring of Recent Antiepileptic Drugs. Drugs in R&D. DOI
- Mirza N et al. (2009). Effect of topiramate on acid–base balance: extent, mechanism and effects. British Journal of Clinical Pharmacology. DOI
- Més de 2 milionsProves analitzades
- 127+Països
- 100+Idiomes
Sobre l’equip mèdic


Senyals de confiança E-E-A-T
Experiència
Revisió clínica liderada per metges dels fluxos de treball d’interpretació de laboratori.
Experiència
Enfocament en medicina de laboratori sobre com es comporten els biomarcadors en context clínic.
Autoritat
Revisat mèdicament pel Dr. Thomas Klein, amb aportacions de la Dra. Sarah Mitchell i el Prof. Dr. Hans Weber.
Fiabilitat
Interpretació basada en l’evidència amb vies de seguiment clares per reduir l’alarma.






Exempció de responsabilitat mèdica
Aquest article és només per a finalitats educatives i no constitueix assessorament mèdic. Consulteu sempre un professional sanitari qualificat per a decisions de diagnòstic i tractament.
Publicat · Contacteu amb l’equip editorial
Publicat per Kantesti Ltd, registrat a Anglaterra i Gal·les, número de societat. 17090423, Londres, Regne Unit.
