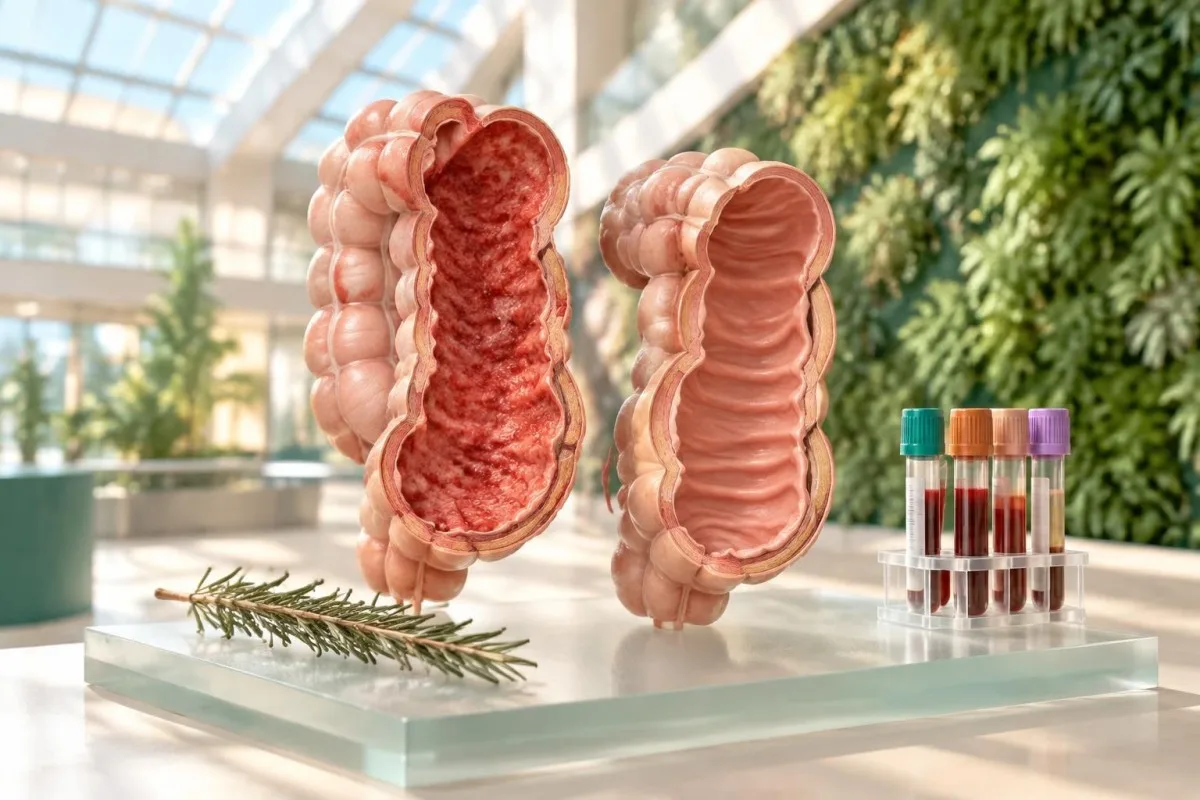
An ulcerative colitis blood test can reveal systemic inflammation, anaemia, nutritional effects and treatment safety issues, but no blood result confirms ulcerative colitis by itself. Diagnosis normally combines symptoms, stool testing, colonoscopy and tissue examination.

ዋና ዋና ነጥቦች
- ምርመራ: No ulcerative colitis blood test confirms the condition; colonoscopy with tissue samples is usually needed to establish the diagnosis and extent.
- CRP እና ESR: CRP ከ5 mg/L በታች መሆን እና ዝቅተኛ ESR መኖር ብዙውን ጊዜ ዝቅተኛ የስርዓታዊ እብጠት እንቅስቃሴን ያመለክታሉ፣ ነገር ግን መደበኛ ውጤቶች ንቁ colitis መኖሩን አያስወግዱም።
- ሲቢሲ: Haemoglobin below 120 g/L in many non-pregnant adult women or below 130 g/L in adult men suggests anaemia, which may reflect intestinal blood loss or chronic inflammation.
- ፕሌትሌትስ: A platelet count above 450 × 10⁹/L can accompany active inflammatory disease, although infection, iron deficiency and other causes can produce the same pattern.
- አልበም: Albumin below 30 g/L is a concerning marker in severe colitis because it may reflect inflammatory protein loss, reduced intake or intestinal protein leakage.
- የሰገራ ምርመራ: Faecal calprotectin is not a blood test, but values above about 150 µg/g commonly support active intestinal inflammation and help decide whether endoscopic assessment is needed.
- Flare assessment: Clinicians interpret trends in CRP, haemoglobin, albumin and platelets alongside stool frequency, urgency, weight and objective stool or endoscopic findings.
- Limits: መደበኛ CRP፣ አሉታዊ የፀረ እንግዳ አካላት ፓነል ወይም መደበኛ የነጭ የደም ሴል ብዛት የቁስለት ኮላይቲስን በደህና ሊያስወግዱ ወይም ስርየትን ሊያረጋግጡ አይችሉም።
What an ulcerative colitis blood test can and cannot show
የደም ምርመራዎች የአልሰራቲቭ ኮላይቲስ ግምገማን ይደግፋሉ፣ ግን ምርመራውን አያረጋግጡም። They can show systemic inflammation, anaemia, dehydration, low protein, liver involvement and medication risks; they cannot demonstrate the characteristic continuous mucosal pattern that endoscopy and tissue examination provide.

ከፍ ያለ ሲ-ሪአክቲቭ ፕሮቲን (C-reactive protein), elevated ESR, low haemoglobin or high platelet count can make active inflammatory bowel disease more plausible, but each finding has alternatives. For example, CRP above 10 mg/L may occur with respiratory infection, urinary infection, obesity or another inflammatory condition, so the result is not specific to colitis.
The 2019 ACG guideline describes ulcerative colitis as a diagnosis built from clinical, endoscopic and histological information rather than one laboratory threshold (Rubin et al., 2019). Our የሕክምና ማረጋገጫ መደበኛዎች reflect the same boundary: an interpreted result can organise evidence, but it cannot replace a gastroenterology assessment.
በየቀኑ ስድስት ጊዜ ልቅ ሰገራ፣ CRP 38 mg/L እና ሄሞግሎቢን 108 g/L ያለው የ28 ዓመት ሰው ምሳሌያዊ ሁኔታ አፋጣኝ ግምገማ የሚገባው ነው፣ በራስ-ሰር መለያ መስጠት ግን አይገባም። ይህ ጥምረት ንቁ እብጠትን ከደም ማነስ ጋር እንዳለ ይጠቁማል፣ ነገር ግን CRP 38 mg/L ብቻውን ብዙ ሁኔታዎችን ሊያመለክት ይችላል፤ የሰገራ በሽታ አምጪ ተህዋስያን ምርመራ እና colonoscopy አሁንም ምርመራውን ይወስናሉ።
CRP, ESR and white cells during a flare
CRP, ESR and white-cell counts measure inflammatory response, not ulcerative-colitis-specific injury. CRP በግምት በ24 እስከ 48 ሰዓታት ውስጥ በአንጻራዊነት በፍጥነት ይለወጣል፣ ESR ደግሞ በበለጠ ዝግታ ይለወጣል፣ እና የነጭ የደም ሴል ብዛት በተለይ በኢንፌክሽን፣ corticosteroids እና በጭንቀት በቀላሉ ይጎዳል።

Many laboratories report adult CRP as normal below 5 mg/L, although some use below 3 mg/L; a result of 20 mg/L therefore signals a meaningful inflammatory response but does not identify its source. ESR reference limits vary by age and sex, and an ESR of 35 mm/hour may remain elevated after CRP has already fallen.
ከ11 × 10⁹/L ገደማ በላይ የሆነ የነጭ የደም ሴሎች ብዛት ንቁ ኮላይቲስን ሊያጅብ ይችላል፤ ነገር ግን ፕሬድኒሶሎን የኒውትሮፊሎችን ከደም ሥር ግድግዳ መለያየትን በማሳደግ፣ የአንጀት ቲሹ ምላሽ እየባሰ እንደሆነ ሳያመለክት የእነሱን ብዛት ሊያሳድግ ይችላል። በተቃራኒው፣ የበሽታ መከላከያን የሚገቱ ሕክምናዎች ሉኮሳይቶሲስን ሊቀንሱ ይችላሉ፤ ስለዚህ 6 × 10⁹/L የሆነ መደበኛ የሴሎች ብዛት የበሽታ መባባስን ሊያስወግድ አይችልም።
CRP and ESR disagreement is common: a person may have CRP 4 mg/L with ESR 42 mm/hour because of anaemia, age or another chronic condition. Our guide to WBC and CRP differences አዝማሚያን፣ ምልክቶችን እና ናሙናው የተወሰደበትን ጊዜ መመልከት፣ ከሁለቱ ምልክት ሰጪዎች አንዱን እንደ አዎ-ወይም-አይደለም ምርመራ ከመቁጠር ይልቅ የበለጠ መረጃ የሚሰጥበትን ምክንያት ያብራራል።
Why stool calprotectin often adds more than blood
በሰገራ ውስጥ ያለው ካልፕሮቴክቲን በአንጀት ውስጥ የኒውትሮፊል እንቅስቃሴን ያንጸባርቃል፣ እናም ብዙውን ጊዜ ከCRP የበለጠ ለአንጀት የተለየ መለኪያ ነው። It is not a blood test, but a result below about 50 µg/g generally supports low intestinal inflammatory activity, while values above 150 µg/g commonly justify repeat assessment or further investigation.

Calprotectin between 50 and 150 µg/g is an uncertainty zone rather than a diagnosis; recent infection, non-steroidal anti-inflammatory drugs and strenuous exercise can raise it. A result above 250 µg/g is more concerning for active intestinal inflammation, but it still cannot distinguish ulcerative colitis from Crohn disease, infection or some other bowel disorders.
The STRIDE-II treat-to-target update places symptoms, biomarkers such as CRP and faecal calprotectin, and endoscopic healing on different levels of assessment (Turner et al., 2021). That hierarchy matters because CRP 3 mg/L and calprotectin 420 µg/g are not contradictory: the first may be quiet systemically while the second detects local bowel activity.
A hypothetical patient whose calprotectin falls from 1,100 to 180 µg/g after treatment may be improving without having reached a low-risk target. Our የካልፕሮቴክቲን ትርጓሜ መመሪያ calprotectinን ከlactoferrin ጋር ያነጻጽራል፣ እንዲሁም በተቅማጥ ጊዜ ወይም NSAID ከተጠቀሙ ብዙም ሳይቆይ የተሰበሰበ ናሙና ለምን አውድ ሊያስፈልገው እንደሚችል ያብራራል።
Blood tests do not distinguish a flare from infection
A flare-like blood pattern can result from infection, so stool microbiology is part of safe assessment. C. difficile፣ Campylobacter፣ Salmonella፣ Shigella፣ ጥገኛ ተህዋሲያን እና ከሳይቶሜጋሎቫይረስ ጋር የተያያዘ በሽታ ከቁስለት ኮላይቲስ ንቁነት ጋር የሚመሳሰል ተቅማጥ፣ ከፍ ያለ CRP እና ዝቅተኛ አልቡሚን ሊያስከትሉ ይችላሉ።

CRP above 50 mg/L and a white-cell count of 14 × 10⁹/L may indicate severe inflammation, but the same numbers can occur with C. difficile colitis. Starting corticosteroids before appropriate infection assessment can worsen some infections, so clinicians often request stool toxin or molecular testing before escalating immunosuppression.
A positive C. difficile molecular assay can indicate toxin-gene carriage rather than toxin-mediated disease, particularly when stool is formed or symptoms have another explanation. The practical interpretation of C. difficile test combinations በምልክቶች፣ በመርዛማ ንጥረ ውጤቶች እና በላቦራቶሪው የምርመራ ዘዴ ላይ ይመረኮዛል፤ በደም ሴሎች ብዛት ላይ ብቻ አይደለም።
A negative stool pathogen panel also has limits: timing, prior antibiotics and the panel's organism coverage affect sensitivity. If a patient has CRP 12 mg/L, calprotectin 700 µg/g and persistent bloody diarrhoea after negative bacterial tests, endoscopic assessment may still be needed rather than assuming the result proves a non-infectious flare.
CBC results: anaemia, platelets and hidden disease burden
The complete blood count often reveals complications of ulcerative colitis rather than proving colitis itself. Low haemoglobin may reflect iron deficiency, inflammation, vitamin deficiency or ongoing intestinal loss; thrombocytosis can mirror inflammation but also occurs with iron deficiency and infection.

WHO መስፈርቶች በአጠቃላይ የደም ማነስን በአዋቂ ወንዶች ከ130 g/L በታች እና እርጉዝ ባልሆኑ አዋቂ ሴቶች ከ120 g/L በታች የሆነ ሄሞግሎቢን በመሆኑ ይገልጻሉ፤ ሆኖም እርግዝና፣ ዕድሜ እና የአካባቢ መመሪያ ትርጓሜውን ይቀይራሉ። ከ80 fL በታች የሆነ ዝቅተኛ MCV ከዝቅተኛ ferritin ጋር ሲኖር የብረት እጥረትን ይደግፋል፤ መደበኛ ወይም ከፍተኛ MCV ግን የተቀላቀለ የብረትና B12 እጥረትን አያስወግድም።
Platelets above 450 × 10⁹/L are often called thrombocytosis and may track inflammatory activity, but a platelet count of 510 × 10⁹/L is not specific. Iron deficiency can drive a similar rise, which is why clinicians pair the CBC with ferritin, transferrin saturation, CRP and the clinical history.
የደም ሄሞግሎቢን 96 g/L፣ MCV 72 fL፣ ፌሪቲን 8 µg/L እና ፕሌትሌቶች 590 × 10⁹/L የሆኑትን 52 ዓመት የሆነ ምናባዊ ታካሚ እንውሰድ፤ ይህ ሁኔታ የብረት ክምችት መሟጠጡን ከአጸፋዊ ትሮምቦሳይቶሲስ ጋር በጠንካራ ሁኔታ ያሳያል፤ ከባድ የኮላይቲስ መባባስ መኖሩን ግን አያረጋግጥም። መገምገም low MCHC and red-cell patterns can help explain why the CBC needs iron studies rather than a single-marker conclusion.
Ferritin and iron studies when inflammation is present
ፌሪቲን በብረት እጥረት ዝቅተኛ ሊሆን ይችላል፤ በእብጠት ጊዜ ግን በሐሰት መደበኛ ወይም ከፍተኛ ሊታይ ይችላል። Ferritin below 30 µg/L commonly indicates depleted iron stores, but in active inflammatory bowel disease a value below 100 µg/L may still be compatible with iron deficiency when transferrin saturation is below 20%.

የትራንስፈሪን ሙሌት ከ20% በታች መሆኑ፣ ለቀይ የደም ሴሎች ምርት በደም ዝውውር ውስጥ በቂ ብረት እንደሌለ ያመለክታል፤ ከፍተኛ ጠቅላላ የብረት ማሰሪያ አቅም ደግሞ ፍጹም የብረት እጥረትን ይደግፋል። በእብጠት ወቅት ሄፕሲዲን የብረት መለቀቅን ይቀንሳል፣ ትራንስፈሪንም ሊቀንስ ይችላል፤ ይህም ፌሪቲን 65 µg/L መሆኑ በቂ የብረት ክምችት እንዳለ የማያረጋግጥበትን የተቀላቀለ ንድፍ ይፈጥራል።
የ CRP 46 mg/L፣ ፌሪቲን 74 µg/L፣ የሴረም ብረት 4 µmol/L እና የትራንስፈሪን ሙሌት 9% ያለው ግምታዊ ታካሚ ከእብጠት ጋር የተያያዘ የብረት አጠቃቀም ተግባራዊ መገደብ ከእውነተኛ እጥረት ጋር ተደምሮ ሊኖረው ይችላል። የ የብረት ምርመራዎች ማጣቀሻ መመሪያ explains why the result should be interpreted as a pattern and why oral or intravenous replacement depends on disease activity and clinical advice.
Iron deficiency can persist even when haemoglobin is 128 g/L, because storage depletion often precedes anaemia. Fatigue, reduced exercise tolerance and restless legs therefore deserve attention even when the CBC looks close to normal; repeat ferritin and saturation after treatment are more useful than assuming one normal haemoglobin ends the investigation.
በንቁ በሽታ ጊዜ አልቡሚን፣ ኤሌክትሮላይቶች እና የውኃ እጥረት
Low albumin and abnormal electrolytes indicate disease burden or physiological stress, not a unique ulcerative-colitis signature. Albumin below 35 g/L may reflect inflammation, reduced intake or protein loss, while values below 30 g/L are more concerning when accompanied by frequent diarrhoea, oedema, tachycardia or weight loss.

Albumin has a half-life of roughly 20 days, so it may remain low after CRP improves and should not be used as an instant flare meter. A sodium level of 132 mmol/L may reflect gastrointestinal losses or excess free-water intake, whereas potassium below 3.0 mmol/L can become clinically urgent because diarrhoea and some medicines increase arrhythmia risk.
አልቡሚን 27 g/L፣ ፖታሲየም 2.9 mmol/L እና ክሬያቲኒን 118 µmol/L ያለው ታካሚ፣ CRP 18 mg/L ብቻ ቢሆንም እንኳ አስቸኳይ የፈሳሽና የኤሌክትሮላይት ግምገማ ሊያስፈልገው ይችላል። ምክንያቱም የተዋሃደው የውጤት ንድፍ የሰውነት ፈሳሽ መጥፋትንና የፕሮቲን መጥፋትን ስለሚያመለክት ነው፤ እያንዳንዱን ውጤት ብቻውን ከመመልከት ይልቅ የሰውነት ፊዚዮሎጂያዊ ሁኔታዎቹን በአንድነት መመልከት የበለጠ መረጃ ይሰጣል።
Prealbumin changes faster than albumin but is also affected by inflammation, liver function and kidney disease, so it is not a pure nutrition score. Our የፕሪአልቡሚን ውስንነቶች መመሪያ explains why dietitian assessment, weight trend and intake history should accompany protein markers.
የጉበት የደም ምርመራዎች እና ከአልሰራቲቭ-ኮላይቲስ ጋር የተያያዙ ሁኔታዎች
የጉበት ምርመራዎች በቁስለት ኮላይቲስ ባለባቸው ሰዎች ላይ የመድኃኒት ተፅዕኖዎችን፣ የይዛወርና ቱቦ በሽታን ወይም የስብ ጉበትን ሊለዩ ይችላሉ፤ ነገር ግን ኮላይቲስን አይመረምሩም። የአልካላይን ፎስፋታዝ ወይም የጋማ-ግሉታሚል ትራንስፈሬዝ መጨመር ዋና ስክሌሮዚንግ ኮላንጊቲስን ጨምሮ ለኮሌስታሲስ ግምገማ ሊያነሳሳ ይችላል፤ ALT እና AST ግን ብዙውን ጊዜ የሄፓቶሴሉላር ጭንቀትን ያመለክታሉ።
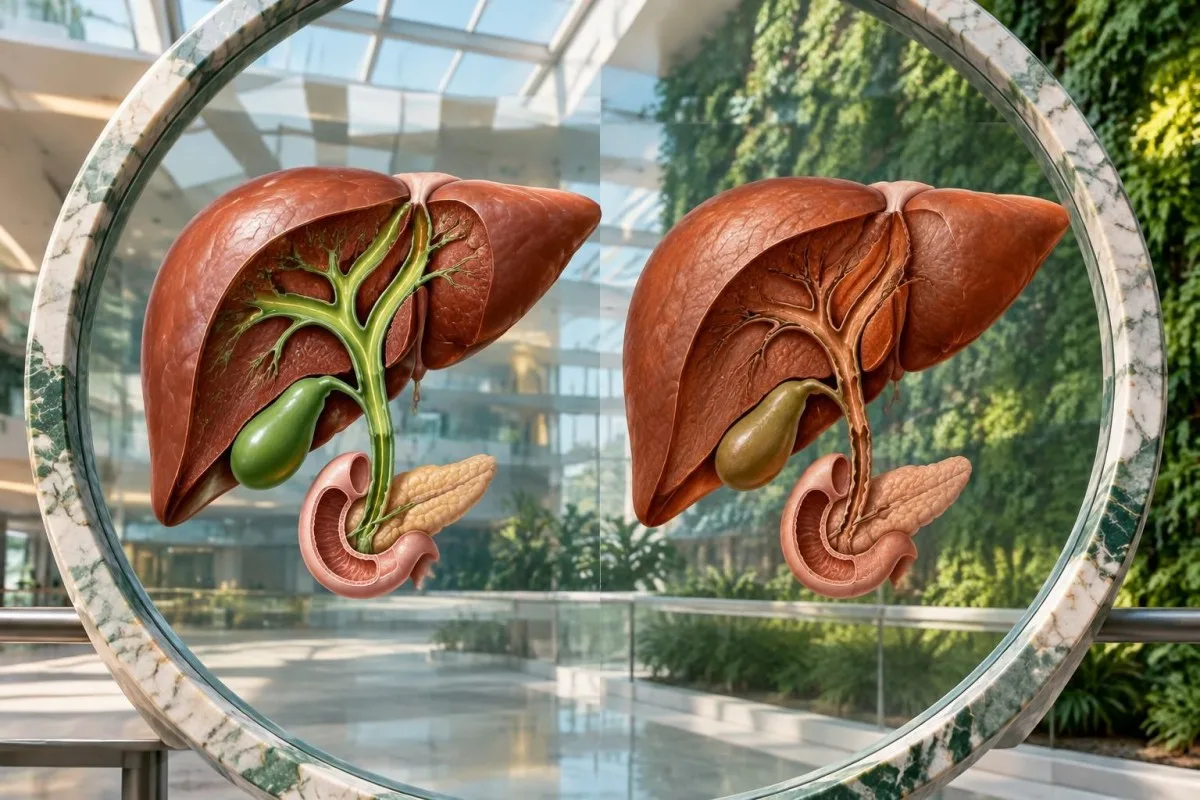
An ALT of 85 IU/L is approximately twice the upper limit in many laboratories, but reference limits differ and the result may reflect medication, metabolic liver disease or viral hepatitis. An alkaline phosphatase above 1.5 times the local upper limit, especially with raised GGT or bilirubin, deserves a different pathway from isolated mild ALT elevation.
ዋና ስክሌሮዚንግ ኮላንጊቲስ ከአንጀት እብጠት በሽታ ጋር ይያያዛል፣ ነገር ግን በአንድ የኢንዛይም ደረጃ ገደብ አይለይም፤ የማያቋርጡ የኮሌስታሲስ ውጤቶች ወደ አልትራሳውንድ ወይም የማግኔቲክ ሬዞናንስ ኮላንጂዮግራፊ ሊያመሩ ይችላሉ። የቢሊሩቢን መጠን 45 µmol/L እና የአልካላይን ፎስፋታዝ መጠን 360 IU/L መሆን ከተናጠል CRP መጨመር ይልቅ የቢሊያሪ ፍሰት መታወክን ይበልጥ ያመለክታል፣ ሆኖም መዘጋትና በመድኃኒት የሚመጣ ጉዳት አሁንም ሌሎች አማራጮች ናቸው።
የመድኃኒት ግምገማ አስፈላጊ ነው፣ ምክንያቱም thiopurines፣ biologics፣ corticosteroids እና ከIBD ውጪ የሆኑ መድኃኒቶች የጉበት ውጤቶችን ሊለውጡ ይችላሉ። ያተኮረ የጉበት ምርመራ ማብራሪያ can help organise ALT, AST, ALP, GGT and bilirubin, but persistent or worsening abnormalities require clinician-led investigation rather than self-directed drug changes.
Why IL-6 and other specialist markers are not routine tests
Specialist inflammatory markers such as interleukin-6 may rise in active disease, but they are not routine diagnostic substitutes for CRP, stool testing or endoscopy. IL-6 ባዮሎጂያዊ ፍላጎት ያለው ነው፣ ምክንያቱም የጉበትን የአጣዳፊ ደረጃ ምላሾች ስለሚያንቀሳቅስ፤ ሆኖም የምርመራው መገኘት፣ ጊዜ እና የሕክምና ተፅዕኖዎች የግለሰብ ክሊኒካዊ ጠቀሜታውን ይገድባሉ።

An IL-6 concentration of 12 pg/mL may be above one assay's reference interval and normal for another, because methods and calibration differ. Cytokines also fluctuate over hours, so a single measurement can be less reproducible than CRP, whose routine interpretation is better standardised.
The reason IL-6 and CRP can disagree is biological: IL-6 may rise early, while the liver-derived CRP response follows later and can be altered by targeted treatment. Our IL-6 result guide explains why a specialist marker should answer a defined clinical question rather than become an expensive general screen.
Research assays may help compare populations or investigate treatment response, but a patient should not infer remission from IL-6 2 pg/mL if stool calprotectin is 600 µg/g and symptoms persist. The opposite combination also needs review, because a low cytokine result does not visualise the mucosa or exclude a structural complication.
ለሕክምና ደህንነት እና ለbiologic ደረጃዎች የሚደረጉ የደም ምርመራዎች
Once ulcerative colitis is diagnosed, blood tests often monitor treatment safety and drug exposure rather than diagnose the disease. Liver enzymes, creatinine, full blood count and infection screening protect against avoidable harm; trough drug levels can help explain loss of response in selected situations.

ለኢንፍሊክሲማብ፣ ከ3 እስከ 5 µg/mL ገደማ በታች የሆነ የመጨረሻ የመድኃኒት መጠን በአንዳንድ የጥገና ሕክምና ሁኔታዎች በቂ ተጋላጭነት እንደሌለ ሊያመለክት ይችላል፤ ነገር ግን ዒላማዎች እንደ የምርመራ ዘዴው፣ የሕክምናው ደረጃ እና ዓላማው ምልክቶችን መቆጣጠር ወይም የማኮሳ መፈወስ መሆኑ ይለያያሉ። ከመድኃኒቱ ጋር የሚቃረኑ ፀረ-ሰውነት አካላት እና አልቡሚን ትርጓሜውን ይነካሉ፤ ስለዚህ ዝቅተኛ መጠን ብቻውን መድኃኒቱ አልሰራም ማለት አይደለም።
A hypothetical result showing infliximab 1.2 µg/mL, high anti-drug antibodies and CRP 28 mg/L suggests a pharmacokinetic problem more than a simple need for dose escalation. The infliximab level guide ጊዜው በትክክል መመዝገብ ለምን እንደሚያስፈልግ ያብራራል፦ ከኢንፍዩዥን በኋላ ወዲያውኑ የተወሰደ ናሙና ዝቅተኛ የመድኃኒት መጠን ጊዜ ላይ የተወሰደ አይደለም።
Before biologic or immunomodulator treatment, clinicians may check hepatitis B, tuberculosis risk, vaccination status and baseline CBC or liver tests. A normal CRP does not make a medicine safe, and a raised ALT does not automatically prove toxicity; the medication timeline and repeat testing are essential.
TPMT, blood counts and thiopurine safety
TPMT and NUDT15 testing can predict susceptibility to thiopurine toxicity, but they do not diagnose ulcerative colitis. A normal genotype or enzyme activity reduces one risk pathway; it does not remove the need for serial CBC and liver monitoring because toxicity can occur through other mechanisms.
TPMT activity below about 10 units per millilitre of red cells is often treated as low, while intermediate activity may require a reduced thiopurine dose; laboratories use different units and cutoffs. NUDT15 variants are especially relevant in some Asian and Hispanic populations, so a normal TPMT result alone may not capture inherited risk.
A falling neutrophil count below 1.5 × 10⁹/L or a rising ALT after starting azathioprine needs prompt clinical review, even if baseline testing was normal. The thiopurine metabolite guide የሜታቦላይት ውጤቶች የመድኃኒት መጠን ከሚያስፈልገው በታች መሆንን፣ መድኃኒቱን አለመውሰድን፣ በተመረጠ መንገድ መፍረስን እና የመርዛማነት ንድፎችን እንዴት ሊለዩ እንደሚችሉ ያሳያል።
A blood test taken 3 days after treatment starts cannot reliably establish long-term safety because marrow suppression may develop later. Monitoring intervals vary by local protocol, but repeat CBC and liver tests during the first weeks and months are more informative than relying on one reassuring baseline panel.
Why endoscopy remains central to diagnosis
ኮሎኖስኮፒ ከሕብረ ሕዋስ ምርመራ ጋር ዋና የምርመራ ዘዴ ሆኖ ይቀጥላል፣ ምክንያቱም የሙኮዛውን ስርጭት፣ ክብደት እና በጥቃቅን ምርመራ የሚታይ ለውጥ በቀጥታ ይገመግማል። Blood tests can indicate inflammatory burden, but they cannot show whether inflammation is continuous from the rectum, whether ulcers are present, or whether microscopic features support an alternative diagnosis.
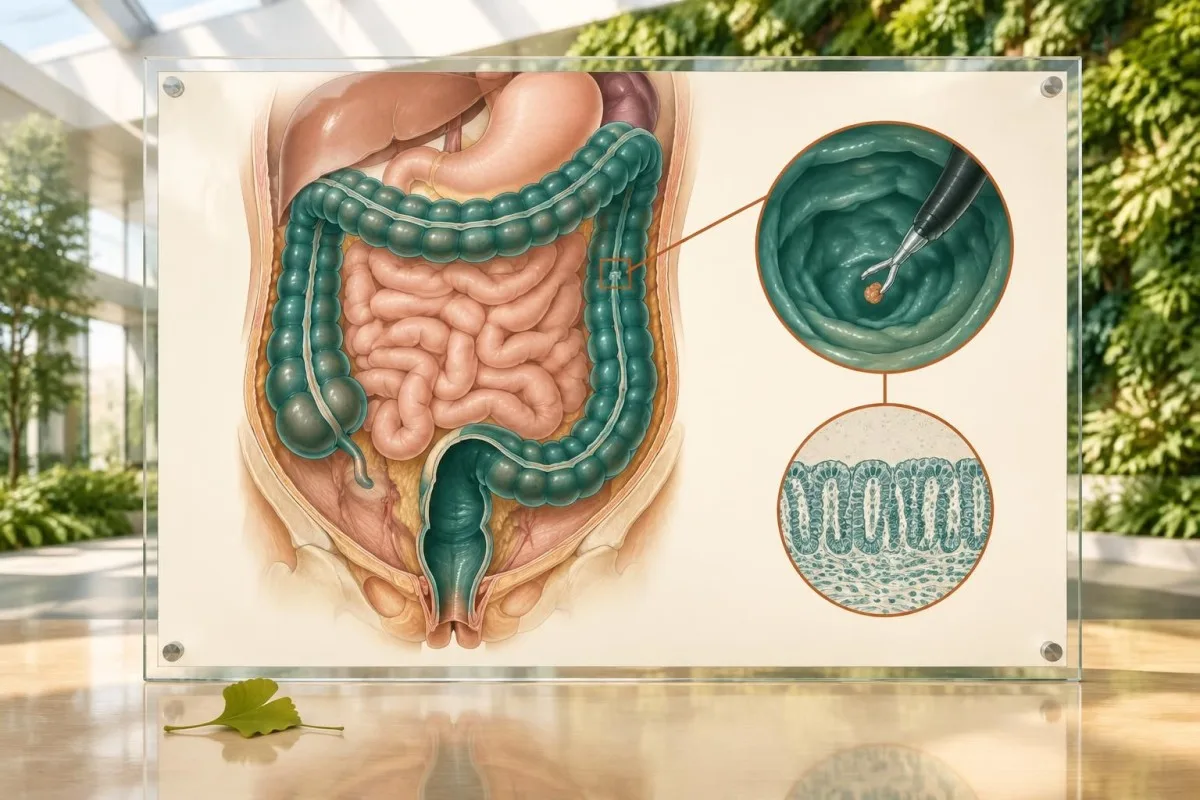
The ECCO-ESGAR diagnostic guideline recommends combining symptoms, laboratory results, stool testing, ileocolonoscopy and biopsies when evaluating suspected inflammatory bowel disease (Maaser et al., 2019). A CRP of 6 mg/L with rectal urgency may still warrant endoscopy, while CRP 80 mg/L may require urgent stabilisation before a full procedure.
Endoscopy also detects extent, which blood tests cannot grade reliably: proctitis, left-sided colitis and extensive colitis can produce overlapping CRP values. Histology may identify chronic architectural change, microscopic activity or cytomegalovirus-related findings that would alter treatment, even when the blood count is near normal.
A negative colonoscopy does not always end the workup if symptoms persist, because sampling location, preparation quality and treatment exposure affect what is seen. The diagnostic process should document medication use, stool results and the number and distribution of tissue samples rather than treating an isolated normal blood marker as decisive.
የደም ውጤቶች ከባድ በሽታን ወይም አስቸኳይ እንክብካቤን ሲያመለክቱ
የደም ውጤቶች ተደጋጋሚ ደም ያለበት ሰገራ፣ ትኩሳት፣ tachycardia፣ የውኃ እጥረት፣ ከባድ ሕመም ወይም ፈጣን መባባስ ጋር ሲደመሩ አስቸኳይ ይሆናሉ። In acute severe ulcerative colitis, classic Truelove and Witts criteria include at least 6 bloody stools daily plus systemic features such as pulse above 90 beats per minute, temperature above 37.8°C, haemoglobin below 105 g/L or ESR above 30 mm/hour.

A haemoglobin of 101 g/L with pulse 112, temperature 38.1°C and six or more bloody stools is not a result to manage through an online interpretation alone. The combination raises concern for acute severe disease, where hospital assessment may include intravenous fluids, infection exclusion, abdominal imaging and urgent gastroenterology review.
Creatinine above a person's baseline, urea elevation, potassium below 3.0 mmol/L or lactate elevation can indicate dehydration or systemic compromise, but each result needs the clinical setting. A normal lactate of 1.3 mmol/L does not make severe colitis safe if the patient is faint, unable to drink or passing frequent blood-stained stools.
Do not wait for repeat home testing if there is heavy rectal blood loss, fainting, confusion, severe abdominal distension, persistent vomiting or inability to keep fluids down. Our explanation of የደም መርጋት ምርመራ ውስንነቶች also clarifies that a normal PT or aPTT does not rule out gastrointestinal blood loss or determine its cause.
How to read ulcerative colitis blood-test trends
ተከታታይ ለውጦች ከተናጠል የአልሰራቲቭ ኮላይቲስ የደም ምርመራ እሴቶች የበለጠ ጠቃሚ ናቸው። A falling CRP, recovering albumin, stable haemoglobin and normalising platelets support improvement, but objective stool or endoscopic assessment is still needed because symptoms and mucosal activity can move at different speeds.

A CRP decline from 64 to 18 mg/L over 7 days is encouraging, but it does not prove mucosal healing; albumin may lag because its half-life is about 20 days. A haemoglobin fall from 124 to 111 g/L over the same period is a separate warning that ongoing loss or dilution may be occurring.
Kantesti የእብጠት፣ የደም ማነስ፣ የአመጋገብ ሁኔታ እና የሕክምና ደህንነት ልዩነትን እየጠበቀ ተከታታይ የbiomarker ቅጦችን የሚያነጻጽር የAI የደም ምርመራ ተንታኝ ነው። የእኛ የAI ቴክኖሎጂ መመሪያ explains why trend interpretation can flag combinations for clinician review without converting a pattern into a diagnosis.
The most useful personal record includes sample date, symptoms, stool frequency, medication dose, recent infection, menstrual or other blood loss and whether the sample was taken during steroids. Two CRP results 48 hours apart after a viral illness do not carry the same meaning as two results 6 weeks apart during stable treatment.
Can normal blood tests rule out ulcerative colitis?
Normal blood tests cannot rule out ulcerative colitis, especially when disease is limited to the rectum or left colon. CRP ንቁ የማኮሳ በሽታ ሲኖር ከ5 mg/L በታች ሊቆይ ይችላል፤ እንዲሁም መደበኛ የሂሞግሎቢን ወይም የነጭ የደም ሴሎች ብዛት ስለ ቀድሞ፣ በአካባቢ የተገደበ ወይም ከጊዜ ወደ ጊዜ ስለሚንቀሳቀስ እብጠት ብዙ መረጃ አይሰጥም።
የፊንጢጣ ደም መፍሰስ፣ አስቸኳይ የመፀዳዳት ፍላጎት እና CRP 2 mg/L ያለው ታካሚ ሥርዓታዊ እብጠት አነስተኛ ቢሆንም በሕክምና አስፈላጊ የሆነ ፕሮክቲቲስ ሊኖረው ይችላል። ተግባራዊው ምክንያት አናቶሚያዊ ነው፤ በአንድ ትንሽ የተቃጠለ አካባቢ የሚለቀቀው ምልክት የሰውነትን አጠቃላይ ምልክት ለማሳደግ በቂ ላይሆን ይችላል፣ ምልክቶቹ ግን በአካባቢው ከባድ ሆነው ይቀጥላሉ።
Conversely, CRP 35 mg/L can result from pneumonia, dental infection or a strenuous inflammatory illness without any colitis. This is why a normal or abnormal result must be matched to stool studies, examination, calprotectin and endoscopy rather than used as a standalone rule-in or rule-out test.
A normal blood panel is reassuring for anaemia, kidney function and some complications, but it does not replace surveillance or a planned review. If symptoms persist for more than a few weeks, recur after treatment reduction or include blood and nocturnal diarrhoea, clinical assessment should take priority over repeated self-ordered panels.
How to use blood-test interpretation without replacing care
AI interpretation can organise laboratory patterns, but it cannot confirm ulcerative colitis or decide urgent treatment. A safe workflow uses the original report, laboratory reference intervals, dates, medicines and symptoms, then sends concerning combinations to a qualified clinician.
Kantesti የምርመራ ውጤቶችን በአውዳቸው፣ ከነ መለኪያ ክፍሎቻቸው፣ የማጣቀሻ ክልሎቻቸው እና በጊዜ ሂደት ከተፈጠሩ ለውጦች ጋር የሚተረጉም በAI የሚሰራ የደም ምርመራ ውጤት ትርጓሜ መድረክ ነው። CRP 42 mg/L፣ አልቡሚን 29 g/L እና ሄሞግሎቢን 104 g/L በአንድነት ከማንኛውም አንድ ውጤት በላይ አሳሳቢ የሆነ ሁኔታ እንደሚያመለክቱ አንባቢዎች እንዲለዩ ሊረዳ ይችላል፤ ሆኖም አንጀቱን መመርመር ወይም የኢንዶስኮፒ ምስልን መተርጎም አይችልም።
Kantesti ትርጉሞች ሊኖሩት የሚችሉትን እና ተጨማሪ የክትትል ጥያቄዎችን ለማብራራት ሰፊ የባዮማርከር የእውቀት መሠረት ይጠቀማል፤ ትክክለኛ የአንጀት እብጠት በሽታ ምርመራ ለመስጠት አይደለም። ሪፖርት መጫን በከባድ ሕመም፣ በመሳት፣ በብዛት በፊንጢጣ በኩል የሚፈስ ደም፣ ከ38°C በላይ ትኩሳት ወይም መጠጣት አለመቻል ምክንያት አስቸኳይ እንክብካቤ መፈለግን ፈጽሞ ማዘግየት የለበትም።
ውጤቶችን ከማጋራትዎ በፊት፣ ተገቢ ሲሆን መለያ ሰጪ መረጃዎችን ያስወግዱ እና የመጀመሪያውን የላቦራቶሪ ሪፖርት ይያዙ፣ ምክንያቱም ክልሎች በአገሮችና በተንታኞች መካከል ይለያያሉ። ክሊኒካዊ ባለሙያ ትክክለኛውን ምርመራ፣ የናሙና መሰብሰቢያ ቀን እና የመድኃኒት የጊዜ ሂደት ያስፈልገዋል፤ እንደ CRP 18 ያለ ክፍል አልባ የተገለበጠ ቁጥር ያልተሟላ ነው፣ ምክንያቱም mg/L እና mg/dL በ10 እጥፍ ይለያያሉ።
የulcerative colitis የደም ውጤቶችን ከተቀበሉ በኋላ ምን መጠየቅ እንደሚገባ
ምርጥ የክትትል ጥያቄዎች ውጤቱን ከምርመራው፣ ከበሽታው ንቁነት፣ ከውስብስቦች እና ከሚቀጥለው እርምጃ ጋር ያያይዛሉ። የትኞቹ ግኝቶች ልዩ መሆናቸውን፣ ኢንፌክሽን መወገዱን፣ የጊዜ ሂደት አስፈላጊ መሆኑን እና የሰገራ ምርመራ ወይም ኤንዶስኮፒ እንደሚያስፈልግ ይጠይቁ።
Ask whether the laboratory used CRP below 5 mg/L as its reference limit, whether ferritin is reliable in the presence of inflammation, and whether the haemoglobin pattern suggests iron, B12 or folate deficiency. These questions prevent a result such as ferritin 70 µg/L from being misread as proof that iron stores are adequate.
የድጋሚ ምርመራን ምን እንደሚያስነሳ ይጠይቁ፦ ለምሳሌ፣ የ CRP ከ4 ወደ 25 mg/L መጨመር፣ የአልቡሚን ከ30 g/L በታች መውረድ ወይም የፖታሲየም ከ3.0 mmol/L በታች መሆን እያንዳንዱ የአስቸኳይነት ደረጃን ሊቀይር ይችላል፤ ነገር ግን መጠኖቹ በምልክቶች እና በመነሻ እሴቶች ላይ ይመረኮዛሉ። እንዲሁም ናሙናው የተወሰደው ከስቴሮይድ፣ ከአንቲባዮቲክ፣ ከባዮሎጂካል መድኃኒት መጠን ወይም ከደም ሥር ፈሳሽ በፊት ወይም በኋላ መሆኑን ይጠይቁ።
Kantesti is an AI-powered blood test analysis tool that can help prepare a concise list of result-specific questions for an appointment, while the የሕክምና አማካሪ ቦርድ በጤና ይዘታችን ጀርባ ያሉትን የክሊኒካዊ ቁጥጥር መርሆች ያብራራል። ሙሉውን ሪፖርት እና የምልክቶች የጊዜ ሂደት ይዘው ይምጡ፤ የተለዩ ከመደበኛ ውጭ የሆኑ እሴቶችን ብቻ አይዘው አይምጡ።
ተደጋግመው የሚጠየቁ ጥያቄዎች
የደም ምርመራ የቁስለት ኮላይቲስን ማረጋገጥ ይችላል?
ምንም የደም ምርመራ ብቻውን የቁስለት ኮላይቲስን አያረጋግጥም። CRP ከ5 mg/L በላይ፣ ESR ከአካባቢያዊው የማጣቀሻ ክልል በላይ፣ የደም ማነስ ወይም ከ450 × 10⁹/L በላይ የሆነ የፕሌትሌት ብዛት ንቁ እብጠትን ወይም ችግሮችን ሊደግፉ ይችላሉ፤ ሆኖም እነዚህ ውጤቶች ለዚህ በተለይ የሚያመለክቱ አይደሉም። የደም ምርመራዎች የአንጀት በሽታውን ስርጭት ወይም በአጉሊ መነጽር የሚታየውን ንድፍ ማሳየት ስለማይችሉ፣ ምርመራው ብዙውን ጊዜ ምልክቶችን፣ የሰገራ ምርመራን፣ ኮሎኖስኮፒን እና የቲሹ ምርመራን በማጣመር ይደረጋል።
የትኛው የCRP መጠን የአልሰራቲቭ ኮላይቲስ ምልክት መባባስን ያመለክታል?
ከ5 mg/L በላይ የሆነ CRP ለአዋቂዎች ከተለመደው የማጣቀሻ ወሰን በላይ ነው፤ ከ10 mg/L በላይ የሆኑ እሴቶችም ብዙ ጊዜ በክሊኒካዊ ጠቀሜታ ያለውን እብጠት ያመለክታሉ፤ ሆኖም ማንኛውም የCRP ገደብ የአልሰራቲቭ ኮላይቲስ ማባባስን በእርግጥ አያረጋግጥም። CRP በኢንፌክሽን፣ በጉዳት ወይም በሌሎች የእብጠት ሁኔታዎች ሊጨምር ይችላል፤ በተመሳሳይም ንቁ የአካባቢ ኮላይቲስ CRP ከ5 mg/L በታች ሲሆን ሊኖር ይችላል። ሐኪሞች CRPን ከሰገራ ድግግሞሽ፣ ከሰገራ ካልፕሮቴክቲን፣ ከኢንፌክሽን ምርመራዎች እና ከምርመራ ጋር በማያያዝ ይተረጉማሉ።
በአልሰራቲቭ ኮላይቲስ ምክንያት የሚመጣ የደም ማነስን የሚያሳይ የደም ምርመራ የትኛው ነው?
ሙሉ የደም ቆጠራ የደም ማነስን ያሳያል፤ ፌሪቲንና የትራንስፈሪን ሙሌት ደግሞ የብረት እጥረትን ለመለየት ይረዳሉ። በብዙ አዋቂ ወንዶች ከ130 g/L በታች ወይም እርጉዝ ባልሆኑ አዋቂ ሴቶች ከ120 g/L በታች የሆነ ሄሞግሎቢን በተለምዶ የደም ማነስ መለኪያን ያሟላል፤ የትራንስፈሪን ሙሌት ከ20% በታች መሆኑም በቂ የሆነ ብረት እንደሌለ ይደግፋል። ከ30 µg/L በታች የሆነ ፌሪቲን ብዙውን ጊዜ የተመናመኑ የብረት ክምችቶችን ያመለክታል፤ ነገር ግን እብጠት ፌሪቲንን ሊያሳድግ ስለሚችል፣ ንቁ የአንጀት እብጠት በሽታ ሲኖር ከ100 µg/L በታች የሆነ ውጤት አሁንም ከብረት እጥረት ጋር ሊስማማ ይችላል።
ulcerative colitis በመደበኛ CRP ንቁ ሊሆን ይችላል?
አዎ፣ በተለይ እብጠቱ በፊንጢጣው ወይም በግራ ኮሎን ሲወሰን የቁስለት ኮላይቲስ ንቁ ሆኖ ሳለ CRP መደበኛ ሊሆን ይችላል። CRP ከ5 mg/L በታች መሆኑ ዝቅተኛ የስርዓታዊ እብጠት ምልክትን ያመለክታል፣ ግን የሙኮዛ ፈውስን አያረጋግጥም። የማያቋርጥ አስቸኳይ የመጸዳዳት ስሜት፣ ተቅማጥ ወይም የፊንጢጣ ደም በCRP እና በነጭ የደም ሴል ብዛት መደበኛ ቢሆኑም የሰገራ ካልፕሮቴክቲን፣ የሰገራ ኢንፌክሽን ምርመራ ወይም ኢንዶስኮፒ ሊያስፈልጉ ይችላሉ።
በአልሰራቲቭ ኮላይቲስ ምልክቶች ሲባባሱ የትኞቹ የደም ምርመራዎች ይደረጋሉ?
የክስተት መባባስ ግምገማዎች ብዙውን ጊዜ ሙሉ የደም ቆጠራን፣ CRP፣ ESR፣ ኤሌክትሮላይቶችን፣ የኩላሊት ተግባርን፣ አልቡሚንን፣ የጉበት ምርመራዎችን እና የብረት ጥናቶችን ያካትታሉ። ሄሞግሎቢን ከ105 g/L በታች፣ አልቡሚን ከ30 g/L በታች፣ ፖታስየም ከ3.0 mmol/L በታች መሆን ወይም ክሬአቲኒን ከመነሻ ደረጃው በላይ መጨመር ፈጣን ግምገማ የሚያስፈልጋቸውን ውስብስቦች ሊያመለክቱ ይችላሉ፤ ሆኖም እያንዳንዱ ገደብ በክሊኒካዊ ሁኔታ መተርጎም ይፈልጋል። የሰገራ በሽታ አምጪ ተህዋሲያን ምርመራ እና የሰገራ ካልፕሮቴክቲንም አስፈላጊ ናቸው፤ ምክንያቱም የደም ምርመራዎች ኢንፌክሽንን ከአንጀት እብጠት በአስተማማኝ ሁኔታ መለየት አይችሉም።
ከፍተኛ የፕሌትሌት ብዛት የአልሰራቲቭ ኮላይቲስ ምልክት ነውን؟
ከ450 × 10⁹/L በላይ የሆነ የፕሌትሌት ብዛት ከንቁ ulcerative colitis ጋር አብሮ ሊታይ ይችላል፣ ነገር ግን ይህ የተለየ መለያ የሌለው ምላሽ ሰጪ ግኝት ነው። የብረት እጥረት፣ ኢንፌክሽን፣ ቀዶ ጥገና እና ሌሎች እብጠት የሚያስከትሉ ችግኝቶች ተመሳሳይ ውጤት ሊያመጡ ይችላሉ፤ ስለዚህ ፕሌትሌቶች ብቻቸውን colitisን አያረጋግጡም። ከሕክምና በኋላ ከCRP እና ከምልክቶች ጋር አብሮ ሲቀንስ፣ ወይም ዝቅተኛ ferritin እና microcytosis ጋር ተያይዞ የብረት እጥረትን ሲያመለክት ከፍተኛ ቁጥሩ የበለጠ መረጃ ሰጪ ይሆናል።
የደም ምርመራ ውጤት እንዴት ማንበብ
የላቦራቶሪ ሪፖርትዎን ይስቀሉ፤ የKantesti AI እያንዳንዱን ባዮማርከር በቀላል ቋንቋ በጥቂት ሰከንዶች ውስጥ ያብራራል። በዓለም ዙሪያ ከ2 ሚሊዮን በላይ ሰዎች ይጠቀሙበታል።.
ማጣቀሻዎች
- ክላይን፣ ቲ.፣ ሚቸል፣ ኤስ.፣ እና ዌበር፣ ኤች. (2026)።. የብረት ጥናቶች መመሪያ፦ TIBC፣ የብረት ሙሌት እና የማሰር አቅም።. የKantesti AI የሕክምና ምርምር።. የዶአይ
- ክላይን፣ ቲ.፣ ሚቸል፣ ኤስ.፣ እና ዌበር፣ ኤች. (2026)።. የaPTT መደበኛ ክልል፦ የD-Dimer፣ የፕሮቲን C እና የደም መርጋት መመሪያ።. የKantesti AI የሕክምና ምርምር።. የዶአይ
- Rubin DB et al. (2019). ACG የክሊኒካዊ መመሪያ፦ በአዋቂዎች ላይ የቁስለት ኮላይቲስ። የአሜሪካ ጆርናል ኦፍ ጋስትሮኢንተሮሎጂ።. የዶአይ PubMed
- Maaser C et al. (2019). ECCO-ESGAR Guideline for Diagnostic Assessment in IBD Part 1: Initial Diagnosis, Monitoring of Known IBD, Detection of Complications. Journal of Crohn's and Colitis. የዶአይ PubMed
- Turner D et al. (2021). STRIDE-II: An Update on the Selecting Therapeutic Targets in Inflammatory Bowel Disease Initiative of the International Organization for the Study of IBD. ጋስትሮኤንተሮሎጂ።. የዶአይ PubMed
- 2ሚ+የተተነተኑ ምርመራዎች
- 127+አገሮች
- 100+ቋንቋዎች
ስለ የሕክምና ቡድኑ


የE-E-A-T እምነት ምልክቶች
ልምድ
በሐኪም መሪነት የላቦራቶሪ ትርጓሜ የስራ ፍሰቶች ክሊኒካዊ ግምገማ።.
ባለሙያነት
በክሊኒካዊ አውድ ውስጥ ባዮማርከሮች እንዴት እንደሚሰሩ ላይ የላቦራቶሪ ሕክምና ትኩረት።.
ስልጣን ያለው
በዶ/ር ቶማስ ክላይን በሕክምና የተገመገመ፣ ከዶ/ር ሳራ ሚቼል እና ከፕሮፌሰር ዶ/ር ሃንስ ዌበር አስተዋጽኦ ጋር።.
አስተማማኝነት
ለማስጠንቀቂያ ምላሽ መቀነስ ግልጽ የቀጣይ መንገዶች ያለው በማስረጃ የተደገፈ ትርጓሜ።.




የሕክምና ማስተባበያ
ይህ ጽሑፍ ለትምህርታዊ ዓላማ ብቻ ነው እና የሕክምና ምክር አይደለም። ለምርመራ እና ለሕክምና ውሳኔዎች ሁልጊዜ ብቁ የጤና ባለሙያን ያማክሩ።.
ታትሟል · የአርትዖት ቡድኑን ያነጋግሩ
በKantesti Ltd የታተመ፣ በእንግሊዝና ዌልስ የተመዘገበ፣ የኩባንያ ቁጥር. 17090423, ፣ ለንደን፣ ዩናይትድ ኪንግደም።.
