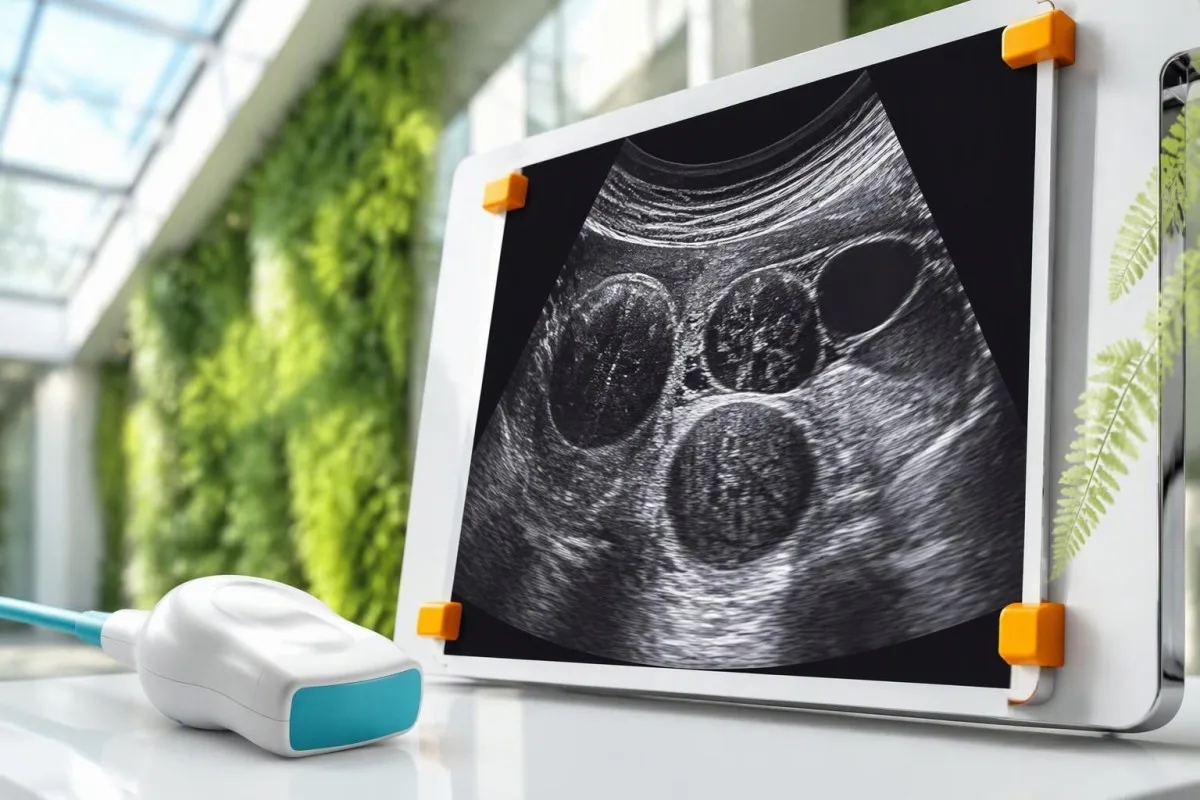
Get checked for periods that disrupt daily life, persistent pelvic pressure, increasing abdominal size, or fertility concerns. Seek urgent care for heavy bleeding with faintness, sudden severe pain, or pregnancy-related pain and bleeding.


- Get checked when bleeding, pelvic pressure, or increasing abdominal size affects everyday life; you do not need to wait several months.
- Urgent bleeding means soaking approximately 1 pad per hour for 2 consecutive hours warrants same-day assessment; faintness or breathlessness makes the situation more urgent.
- Location matters because a 2 cm fibroid affecting the uterine cavity can cause more bleeding than an 8 cm fibroid growing outward.
- Ultrason usually establishes the clinical diagnosis by showing fibroid number, size, and location; no blood test confirms or excludes fibroids.
- Demir eksikliği can precede anemia; ferritin below 15 ng/mL strongly supports depleted iron stores, although inflammation complicates interpretation.
- Kabızlık can result from a large posterior fibroid pressing on the rectum, but ordinary bowel disorders and oral iron are often alternative explanations.
- Fertility depends more on cavity distortion than diameter alone; many people with fibroids conceive without fibroid treatment.
- After menopause any vaginal bleeding after 12 months without periods needs prompt assessment, even when fibroids were diagnosed years earlier.
When do uterine fibroids symptoms need a medical appointment?
Get checked for heavy or prolonged periods, persistent pelvic pressure, increasing abdominal size, or difficulty conceiving. Seek urgent assessment for heavy bleeding with dizziness, sudden severe pelvic pain, or pain and bleeding when pregnancy is possible; ultrasound—not bloodwork—usually establishes whether fibroids are present.
Bleeding deserves attention when it changes what you can do, not only when it reaches a particular volume. Periods lasting more than 7 days, repeated nighttime changes, or avoiding work because of flooding are useful appointment triggers; our guide to heavy period warning signs explains how urgency changes with associated symptoms.
The NICE heavy menstrual bleeding guideline prioritizes quality of life rather than a rigid measured loss of 80 mL per cycle (NICE, 2018, updated 2021). You rarely need to measure menstrual loss at home; describing interrupted sleep, missed exercise, and the number of products used gives a clinician more actionable information.
I’m Thomas Klein, Chief Medical Officer at Kantesti. My starting question would be, “What changed, and over how many cycles?”—because a new 2-cycle pattern deserves a different assessment from lifelong heavy periods accompanied by nosebleeds or easy bruising.
Kantesti bir AI kan testi analizörü that can help explain laboratory consequences of menstrual loss, but it cannot see or diagnose a fibroid. Our kuruluşumuz ve klinik odağımız describe that distinction: interpreting hemoglobin or ferritin supports care, while imaging answers the structural question.
What are the early signs of fibroids?
The early signs of fibroids may include heavier periods, longer bleeding, pelvic fullness, or increasing urinary frequency; some fibroids cause no early symptoms at all. A gradual change across 2 or 3 cycles is more informative than one unusually heavy period, although severe symptoms should never wait.
Iron-related symptoms can appear before the pelvis feels different. Reduced exercise tolerance, restless legs, or unusual fatigue may accompany falling iron stores despite hemoglobin remaining at or above 12 g/dL; our explanation of iron deficiency before anemia covers why a normal CBC can miss that stage.
Clots approximately 2.5 cm across, needing two menstrual products together, or waking repeatedly to change protection suggest substantial flow, but none proves fibroids. Clot size reflects pooling and flow rate; it does not tell you the size, number, or position of a growth.
A fibroid pressing toward the bladder may first show up as 2 additional nighttime bathroom trips rather than obvious pain. However, thirst, burning urination, or suddenly passing unusually large volumes point toward other explanations, so a symptom diary should record volume and discomfort as well as frequency.
An illustrative scenario: a 38-year-old notices periods increasing from 5 to 8 days while her waistband still fits normally. That pattern could reflect a small cavity-affecting fibroid, but a polyp or ovulatory change is also plausible; the history directs testing rather than settling the diagnosis.
How does fibroid size affect symptoms?
Fibroid size influences pressure and abdominal enlargement, but diameter alone does not predict bleeding or fertility effects. A 2 cm fibroid protruding into the uterine cavity may cause substantial bleeding, whereas an 8 cm outward-growing fibroid may mainly cause fullness, urinary frequency, or no symptoms.
A diameter change can look modest while the volume change is considerable. For a roughly spherical growth, increasing from 4 to 5 cm nearly doubles its volume—about 1.95 times—although real fibroids are irregular and ultrasound measurement variation can exaggerate apparent growth between examinations.
NICE recommends specialist discussion for fibroids measuring 3 cm or more in patients with heavy menstrual bleeding, considering their number, location, and symptom severity (NICE, 2018, updated 2021). The 3 cm threshold is a referral and treatment-planning aid, not a boundary between safe and dangerous fibroids.
Several 3 cm fibroids may enlarge the uterus more than one isolated growth. An ultrasound report listing only the largest diameter can therefore underdescribe bulk symptoms; ask whether the report records overall uterine dimensions and the approximate number of fibroids, not merely the biggest one.
There is no reliable “pain starts at 5 cm” rule. Pressure from fibroids and discomfort from other pelvic structures overlap, and our discussion of ovarian cyst warning patterns explains why sudden one-sided pain should not automatically be attributed to a known fibroid.
Why does fibroid location matter more than the number?
Submucosal fibroids affect the uterine cavity and are particularly associated with bleeding and reproductive problems; intramural fibroids grow within the muscle wall, while subserosal fibroids grow outward and more often produce bulk symptoms. A location description can be more clinically useful than a diameter such as 4 cm.
The FIGO classification describes the relationship between a fibroid and the uterine lining or outer surface. Types 0, 1, and 2 are submucosal; type 3 touches the endometrium without projecting into the cavity, and type 4 is entirely intramural—distinctions that matter when planning treatment.
Subserosal types 5, 6, and 7 extend toward the outside, with type 7 attached by a stalk. A stalk changes mobility and occasionally complication risk, but it does not mean an emergency is likely; the ACOG management bulletin emphasizes matching treatment to symptoms and anatomic findings rather than size alone (ACOG, 2021).
A posterior 6 cm fibroid may push toward the rectum, while an anterior growth of similar size may affect the bladder. Pain during sex or bowel movements can also come from endometriosis; our guide to endometriosis diagnostic limits explains why normal bloodwork cannot resolve that alternative.
Ask one practical question after imaging: “Does any fibroid distort the cavity?” Two reports describing the same 3 cm growth as simply “intramural” versus “intramural with cavity distortion” may lead to different fertility counseling and different choices for bleeding treatment.
Which bleeding patterns suggest symptomatic fibroids?
Fibroid-related bleeding usually presents as heavier or longer menstrual periods, especially when a growth affects the cavity. Bleeding between periods also needs assessment, but it is not specific to fibroids; bleeding after sex or after 12 months without periods should prompt evaluation for other causes as well.
Cavity distortion can increase the bleeding surface and interfere with local contraction and hemostasis; altered vessels and signaling also contribute. This explains why an outward-growing 7 cm fibroid may produce less menstrual loss than a 2 cm submucosal growth, although individual patterns remain unpredictable.
Heavy periods beginning with the very first menstrual cycles deserve a bleeding-disorder history, even if ultrasound later finds a fibroid. Frequent nosebleeds, easy bruising, or prolonged dental bleeding add useful clues; our explanation of von Willebrand kanama paternleri incelememiz shows why a structural finding need not be the only diagnosis.
Soaking approximately 1 pad or tampon per hour for 2 consecutive hours warrants same-day medical advice, particularly if the flow is still increasing. Absorbency varies considerably, so dizziness, faintness, chest symptoms, or breathlessness override any product-count rule and should trigger emergency assessment.
Record 3 things rather than estimating milliliters: bleeding days, flooding episodes, and interference with daily activities. A menstrual cup can provide approximate volumes, but changing brands or absorbency can make comparisons misleading; the most useful record is a consistent one rather than a perfectly measured one.
What does fibroid pelvic pressure feel like?
Fibroid pelvic pressure often feels like persistent heaviness, fullness, or a downward pushing sensation rather than sharp pain. It may accompany urinary frequency, incomplete emptying, or lower-back discomfort; a 6 cm growth can cause different symptoms depending on whether it presses anteriorly, posteriorly, or upward.
Mechanical pressure may persist outside menstruation and become more noticeable with a full bladder or prolonged sitting. The pattern matters more than assigning a pain score of 4 versus 6; progressive symptoms, new nighttime urination, and difficulty emptying deserve examination even when discomfort remains tolerable.
Urinary frequency does not establish compression. Diabetes, a urinary tract disorder, pregnancy, and bladder sensitivity are other possibilities; our guide to testing frequent urination explains why 2 patients with similar bathroom frequency may need very different investigations.
An inability to pass urine despite a strong urge and a painful, full lower abdomen requires urgent assessment. Rarely, a large pelvic growth affects urine drainage higher up; a normal creatinine result on 1 occasion does not prove that the bladder or ureters are free from obstruction.
Kantesti can help explain kidney results when a clinician has ordered them for urinary symptoms, but laboratory interpretation cannot establish the cause of pressure. I would separate 2 questions: whether kidney function is affected, and whether imaging shows a growth mechanically affecting urinary drainage.
Can fibroids cause constipation or rectal pressure?
Yes, fibroids can cause constipation, particularly when a large posterior growth presses on the rectum, but constipation alone is weak evidence of fibroids. Fewer than 3 bowel movements per week, hard stools, straining, and incomplete emptying describe constipation; imaging and the broader history help determine its cause.
A pressure-related pattern may include rectal fullness even after passing a stool, combined with pelvic heaviness or urinary symptoms. Hard Bristol type 1 or 2 stools instead suggest slow transit or stool dehydration, although mechanisms can coexist; our stool consistency guide helps describe the distinction.
Oral iron can worsen constipation soon after treatment starts, making a fibroid seem more symptomatic even when its size has not changed. If bowel symptoms begin within 1 or 2 weeks of starting iron, discuss formulation, dose scheduling, and appropriate constipation treatment rather than assuming the growth has enlarged.
New constipation accompanied by repeated vomiting, marked abdominal swelling, or inability to pass gas needs urgent assessment. A large fibroid is only 1 possible explanation; stool impaction, bowel obstruction, and unrelated abdominal conditions must also be considered rather than managed indefinitely with more fiber.
Increasing fiber toward roughly 25–30 g daily may help uncomplicated constipation, but it will not remove mechanical compression and may worsen bloating if increased abruptly. For persistent rectal pressure, ask whether ultrasound documents a posterior fibroid and whether its position plausibly matches the bowel symptoms.
When does abdominal enlargement need investigation?
Fibroids can enlarge the lower abdomen when their combined bulk enlarges the uterus, but progressive abdominal swelling should not be assumed to be fibroids. A waistband becoming tighter over 2 or 3 months deserves assessment, especially with persistent bloating, early fullness after meals, or new urinary symptoms.
Daily fluctuation suggests a different mechanism from a steadily enlarging mass. An abdomen that feels larger after meals and smaller each morning may reflect bowel distension, whereas sustained lower-abdominal fullness over 6 weeks raises a structural question; neither pattern is diagnostic without an examination.
Clinicians sometimes describe an enlarged uterus in pregnancy-week equivalents, such as “12-week size,” even when the patient is not pregnant. This is a rough examination comparison, not an actual gestational measurement or a precise fibroid volume, so an ultrasound dimension is usually more useful for tracking change.
Rapid growth does not by itself prove sarcoma, and most presumed fibroids are benign. However, a new or enlarging pelvic mass after menopause needs specialist evaluation; no single ultrasound appearance, CA-125 result, or LDH result can guarantee benignity, as our CA-125 interpretation cautions also explain.
Comparing 2 scans requires comparable technique and measurements. A different operator, imaging plane, or menstrual timing can produce small apparent differences; ask whether the change exceeds expected measurement variation and whether the whole clinical picture—not simply one larger diameter—supports further investigation.
How do fibroids affect fertility and pregnancy planning?
Fibroids are most likely to affect fertility when they distort the uterine cavity, while many outward-growing fibroids have little direct reproductive effect. A 3 cm cavity-distorting fibroid may matter more than a larger subserosal growth; size alone cannot determine whether removal will improve the chance of pregnancy.
The ASRM guideline supports considering removal of cavity-distorting fibroids to improve pregnancy rates, but evidence is less certain for asymptomatic intramural fibroids without distortion (ASRM, 2017). There is no universal “remove every fibroid above 4 cm” fertility rule; proposed benefit must be weighed against adhesions, recovery time, and the individual reproductive plan.
Age changes the cost of waiting. A general infertility evaluation is appropriate after 12 months of trying below age 35, after 6 months at 35 or older, and sooner when a known problem exists; a fibroid should not distract from ovulation, tubal factors, or partner assessment.
AMH reflects aspects of ovarian reserve, not whether a fibroid changes implantation conditions. Our guide to düşük AMH yorumlaması explains why 1 hormone result cannot diagnose infertility or predict natural conception reliably, and why structural assessment must remain a separate part of planning.
Fibroids respond to estrogen and progesterone signaling, but routine circulating hormone levels do not quantify their fertility impact. Reviewing LH and FSH differences can clarify another part of the fertility assessment; the decisive fibroid question remains cavity involvement, often assessed with detailed ultrasound or saline sonography.
Why does ultrasound—not bloodwork—diagnose fibroids?
Pelvic ultrasound usually establishes the clinical diagnosis of fibroids by showing solid growths and their location, size, and relationship to the uterus. Blood tests cannot show these structural features. Transvaginal and transabdominal ultrasound provide complementary views; a 10 cm growth may need the broader abdominal view for full assessment.
Transvaginal ultrasound often provides more detailed views of the lining and smaller fibroids, while transabdominal ultrasound helps assess a larger uterus or growth extending beyond the pelvis. Consent, comfort, pregnancy context, and suitability guide the approach; declining 1 technique should lead to a discussion of alternatives, not abandonment of assessment.
NICE recommends selecting ultrasound or hysteroscopy according to the history and examination, with hysteroscopy favored when symptoms suggest a submucosal fibroid, polyp, or endometrial problem (NICE, 2018, updated 2021). Saline infusion sonography can clarify cavity distortion; MRI is generally reserved for uncertainty, complex mapping, or treatment planning.
Imaging a fibroid does not explain every source of vaginal bleeding. HPV and Pap screening assess cervical risk rather than diagnose fibroids, and our guide to HPV and Pap results explains why being up to date with screening does not replace evaluation of new bleeding.
Endometrial assessment may still be necessary, particularly with persistent irregular bleeding or relevant risk factors. Many US pathways consider sampling for abnormal uterine bleeding from age 45, while NICE favors risk-directed sampling during hysteroscopy; ultrasound identifies presumed fibroids but does not provide a tissue diagnosis or exclude every coexisting condition.
Which blood tests help when fibroids cause heavy periods?
A complete blood count checks for anemia, while ferritin and sometimes iron studies assess depleted iron stores; none diagnoses fibroids. Hemoglobin below approximately 12 g/dL commonly indicates anemia in nonpregnant adult women, but laboratory ranges and clinical context matter. Ferritin below 15 ng/mL strongly supports iron deficiency.
NICE recommends a full blood count for heavy menstrual bleeding but does not recommend routine ferritin testing for every patient (NICE, 2018, updated 2021). Clinicians may add ferritin when iron deficiency is suspected from symptoms, diet, recurrent loss, or CBC changes; a normal hemoglobin does not settle the iron-store question.
Ferritin below 30 ng/mL often supports depleted stores in an appropriate clinical context, although inflammation can raise ferritin and mask deficiency. Transferrin saturation below 20% can add evidence; our complete iron studies explanation shows why isolated serum iron is a less reliable starting point.
An MCV below 80 fL indicates microcytosis in many adult laboratories, but early iron deficiency may leave MCV normal and thalassemia can also lower it. Our guide to düşük MCV nedenleri explains why cell size should be interpreted alongside ferritin, hemoglobin, and the history.
Kantesti bir AI kan tahlili yorumlama platformu that helps explain reported hemoglobin, ferritin, and related results together, while keeping imaging separate from laboratory inference. A hemoglobin of 8 g/dL with worsening symptoms deserves prompt clinical review; treatment urgency depends on active loss and stability, not an automated interpretation alone.
Hangi belirtiler acil veya ivedi değerlendirme gerektirir?
Emergency symptoms include fainting, severe breathlessness, chest pain, sudden severe pelvic pain, or heavy bleeding with signs of circulatory instability. Soaking approximately 1 pad per hour for 2 hours warrants same-day assessment even without those symptoms. Pregnancy-related pain and bleeding must not be dismissed as a fibroid flare.
Pain with a missed period, shoulder-tip pain, or collapse raises concern for ectopic pregnancy, including when contraception has been used. An early negative home test does not always exclude pregnancy; our explanation of pregnancy test timing limits describes why severe symptoms need clinical assessment rather than another test at home.
Sudden pain on 1 side, especially with vomiting, can indicate an ovarian emergency rather than a fibroid. Fibroid degeneration can also cause substantial pain, but that is a diagnosis made after assessment; existing imaging is not permission to assume every future episode has the same cause.
A temperature of 38°C or higher with pelvic pain, new inability to pass urine, or severe abdominal distension with vomiting requires urgent assessment. These combinations suggest problems that cannot be resolved by checking ferritin, waiting for an ultrasound appointment, or increasing an over-the-counter pain medicine.
Any vaginal bleeding after 12 months without periods needs a prompt appointment, even if it is light and stops quickly. Emergency care is appropriate when that bleeding is heavy or accompanied by faintness; otherwise, timely evaluation should investigate endometrial and cervical causes rather than presume an old fibroid is responsible.
Does an incidental fibroid need treatment?
An incidental fibroid usually does not need treatment if it causes no meaningful symptoms, fertility concern, or concerning imaging finding. There is no universal rule requiring surgery for every 5 cm fibroid. Management should address the actual problem—bleeding, pressure, or reproductive anatomy—not simply remove an abnormality from a report.
Observation is reasonable when the history and imaging fit a benign, asymptomatic finding; there is no single mandatory scan interval for every patient. A planned review in 6–12 months may suit some situations, while others are symptom-led; postmenopausal growth, uncertainty, or changing symptoms require a different plan.
Treatments for heavy periods can reduce loss without eliminating the growth, while pressure symptoms may respond poorly to bleeding-focused medicines. For example, a hormone-releasing intrauterine system may suit some patients without significant cavity distortion; myomectomy, embolization, or other procedures require individualized discussion of anatomy and pregnancy goals.
After iron treatment starts, the CBC can look temporarily more variable because newly produced cells differ from older iron-deficient cells. Our explanation of demir tedavisinden sonra RDW describes that transition; a higher RDW after 2–4 weeks does not automatically mean menstrual loss has worsened.
Kantesti can support understanding of serial laboratory reports, but improving hemoglobin is not evidence that a fibroid has shrunk. Our klinik doğrulaması ve gözetimi explain why laboratory interpretation must stay within its intended scope; ongoing pressure needs its own reassessment even when anemia treatment is working.
What should follow-up and the research evidence actually tell you?
Useful fibroid follow-up tracks symptoms, imaging when indicated, and recovery from iron deficiency as separate outcomes. As of October 24, 2026, this article draws on NICE, ACOG, and ASRM guidance; the 2 Figshare resources listed below provide adjacent laboratory and digestive education, not evidence for fibroid treatment.
A useful follow-up record has 3 parts: menstrual impact, bladder or bowel symptoms, and relevant laboratory trends. If bleeding improves but rectal pressure persists, the outcome is mixed rather than a treatment failure across the board; a repeat scan should answer a defined structural question instead of being ordered automatically.
Kantesti bir Yapay zekâ destekli kan testi analiz aracı that can help explain laboratory trends, but a rising hemoglobin cannot determine whether cavity distortion has resolved. Our hematology marker resource provides context for reticulocytes and LDH; neither marker confirms fibroids or reliably excludes a malignant pelvic growth.
I’m Thomas Klein; the distinction I would emphasize is between 1 educational resource and evidence supporting a treatment decision. The 2 DOI-linked deposits below concern hematology and digestive symptoms, and a DOI identifies a deposited work rather than certifying peer review; our tıbbi içerik standartları explain how source relevance should be assessed.
For a practical appointment, bring 2–3 cycles of records if available, the actual imaging report, and any recent CBC or ferritin results—but do not delay care to assemble them. Our Tıbbi Danışma Kurulu page identifies clinical advisers; your treating clinician must still connect these records to an examination and an individualized plan.
Sıkça Sorulan Sorular
Rahim miyomlarının ilk belirtileri nelerdir?
0 İlk rahim miyomu belirtileri, adet kanamalarının daha yoğun veya daha uzun sürmesi, pelvik dolgunluk, sık idrara çıkma ya da demir eksikliği belirtileri olabilir; bazı miyomlar tamamen belirtisiz kalır. 7 günden uzun süren adet kanamaları veya tekrarlayan aşırı kanamalar değerlendirilmelidir, ancak bunlar miyom olduğunu kanıtlamaz. Rahim boşluğunu etkileyen küçük bir miyom, karında herhangi bir büyüme ortaya çıkmadan önce kanamaya neden olabilir. Ultrason genellikle miyom olup olmadığını ve yerleşiminin belirtileri makul ölçüde açıklayıp açıklamadığını ortaya koyar.
Hangi boyuttaki miyom belirtilere yol açmaya başlar?
Semptomların başladığı tek bir miyom boyutu yoktur. Rahim boşluğunu etkileyen 2 cm'lik bir miyom ciddi kanamaya yol açabilirken, dışa doğru büyüyen 8 cm'lik bir miyom çoğunlukla basınç hissine neden olabilir veya hiç belirti vermeyebilir. NICE, yoğun adet kanaması olan hastalarda 3 cm veya daha büyük miyomlar için uzman görüşmesi önermektedir; ancak bu bir tehlike eşiği değildir. Yalnızca çapı değil, konumu, sayısı, rahmin genel boyutu ve günlük yaşam üzerindeki etkisi daha belirleyicidir.
Miyomlar kabızlığa neden olabilir mi?
Yeterince büyük bir posterior miyom büyümesi rektuma baskı yaptığında kabızlığa neden olabilir; ancak yalnızca kabızlık tanıyı doğrulamaz. Haftada 3’ten az bağırsak hareketi, sert dışkı, ıkınma ve tam boşalamama kabızlığın yaygın özellikleridir. Ağızdan alınan demir, beslenme, ilaçlar ve bağırsak hastalıkları belirtileri açıklayabilir veya miyomla birlikte belirtilere katkıda bulunabilir. Kusmayla birlikte şiddetli karın şişliği ya da gaz çıkaramama, sıradan miyom basıncı olduğu varsayılmamalı; acil değerlendirme gerektirir.
Kan testi rahim miyomlarını teşhis edebilir mi?
Rutin kan testlerinden hiçbiri rahim miyomlarını teşhis etmez veya dışlamaz; klinik tanı genellikle pelvik ultrasonla konur. CBC anemiyi kontrol ederken, klinik olarak endike olduğunda ferritin demir depolarını değerlendirir. Ferritinin 15 ng/mL’nin altında olması demir eksikliğini güçlü biçimde destekler, ancak hemoglobin ve ferritin düzeylerinin normal olması miyomları dışlamaz. CA-125, LDH ve rutin hormon düzeyleri yapısal görüntülemenin yerini tutamaz.
Miyom kanaması ne zaman acil bir durumdur?
Bayılma, belirgin baş dönmesi, göğüs ağrısı, nefes darlığı veya dolaşım instabilitesi belirtilerinin eşlik ettiği yoğun vajinal kanama acil değerlendirme gerektirir. Arka arkaya 2 saat boyunca saatte yaklaşık 1 pedi tamamen dolduracak kadar kanama, özellikle kanama devam ediyor veya artıyorsa aynı gün tıbbi görüş alınmasını gerektirir. Ürünlerin emiciliği değişiklik gösterir; bu nedenle eşlik eden belirtiler, kesin bir sayıdan daha önemlidir. Gebelik olasılığı varsa ağrı ve kanama, miyom dışındaki nedenler açısından da acil değerlendirme gerektirir.
Miyomlarınız varsa hamile kalabilir misiniz?
Miyomu olan birçok kişi, özellikle miyomlar rahim boşluğunun şeklini bozmuyorsa, miyom tedavisi görmeden hamile kalabilir. Rahim boşluğunun şeklini bozan 3 cm’lik bir miyom, dışa doğru büyüyen daha büyük bir miyomdan doğurganlık açısından daha önemli olabilir; ancak miyomun alınması hamileliği garanti etmez. ASRM, gebelik oranlarını artırmak için rahim boşluğunun şeklini bozan miyomların alınmasının değerlendirilmesini desteklerken, şekil bozukluğuna yol açmayan ve belirti vermeyen intramural miyomlara ilişkin kanıtlar daha belirsizdir. Bilinen bir endişe varsa daha erken olmak üzere, 35 yaşın altında 12 ay veya 35 yaş ve üzerinde 6 ay boyunca gebelik için denedikten sonra genellikle doğurganlık değerlendirmesi yapılması uygundur.
Belirtilere yol açmıyorsa miyomların tedavi edilmesi gerekir mi?
Asemptomatik bir miyom, görüntüleme bulguları ve klinik bağlam güven vericiyse genellikle tedavi yerine gözlem gerektirir. Çapı 5 cm'nin üzerindeki her miyomun ameliyat gerektirdiğine veya tesadüfen saptanan her bulgunun 6 ay sonra yeniden taranması gerektiğine dair evrensel bir kural yoktur. Doğurganlık hedefleri, endişe verici görüntüleme özellikleri, menopoz sonrası büyüme ve ortaya çıkan bası veya kanama belirtileri öneriyi değiştirebilir. Adet görmeden geçen 12 ayın ardından ortaya çıkan her türlü vajinal kanama, daha önce miyom tanısı konmuş olmasına bağlanmak yerine hızla değerlendirilmelidir.
Bugün Yapay Zekâ Destekli Kan Tahlili Analizini Alın
Anlık ve doğru laboratuvar testi analizi için Kantesti’ye güvenen dünya genelindeki 2 milyondan fazla kullanıcıya katılın. Kan testi sonuçlarınızı yükleyin ve saniyeler içinde 15,000+ biyobelirteçlerinin kapsamlı yorumunu alın.
📚 Kaynak Gösterilen Araştırma Yayınları
Klein, T., Mitchell, S., & Weber, H. (2026). B Negatif Kan Grubu, LDH Kan Testi ve Retikülosit Sayımı Rehberi. Kantesti Yapay Zeka Tıbbi Araştırma.
Klein, T., Mitchell, S., & Weber, H. (2026). Oruç Sonrası İshal, Dışkıda Siyah Noktalar ve Sindirim Sistemi Rehberi 2026. Kantesti Yapay Zeka Tıbbi Araştırma.
📖 Harici Tıbbi Kaynaklar
Ulusal Sağlık ve Bakım Mükemmelliği Enstitüsü (2018). Heavy menstrual bleeding: assessment and management. NICE guideline NG88. NICE Guidelines.
Amerikan Kadın Doğum ve Jinekoloji Uzmanları Koleji (2021). Management of Symptomatic Uterine Leiomyomas: ACOG Practice Bulletin, Number 228. Obstetrics & Gynecology.
Practice Committee of the American Society for Reproductive Medicine (2017). Removal of myomas in asymptomatic patients to improve fertility and/or reduce miscarriage rate: a guideline. Fertilite ve Sterilite.
⚕️ Tıbbi Uyarı
Bu makale yalnızca eğitim amaçlıdır ve tıbbi tavsiye niteliği taşımaz. Tanı ve tedavi kararları için her zaman yetkin bir sağlık hizmeti sağlayıcısına danışın.
E-E-A-T Güven Sinyalleri
Deneyim
Hekim liderliğinde laboratuvar yorumlama iş akışlarının klinik incelemesi.
Uzmanlık
Klinik bağlamda biyobelirteçlerin nasıl davrandığına odaklanan laboratuvar tıbbı.
Otorite
Dr. Thomas Klein tarafından yazılmış; Dr. Sarah Mitchell ve Prof. Dr. Hans Weber tarafından gözden geçirilmiştir.
Güvenilirlik
Alarmı azaltmaya yönelik net takip yollarıyla kanıta dayalı yorumlama.