
Low serum urate is often harmless when isolated, but a persistent result below about 2.0 mg/dL (119 µmol/L) can signal medication effects or excessive kidney urate loss.

Mambo muhimu ya kukumbuka
- Ufafanuzi: Hypouricemia commonly means serum urate below 2.0 mg/dL (119 µmol/L), although some laboratories flag values below 3.0 mg/dL (178 µmol/L).
- Sababu za kawaida: Uric acid lowering medicines, low purine intake, undernutrition, pregnancy-related dilution and increased kidney urate excretion can lower the result.
- Dalili: Low uric acid usually causes no symptoms; exertional kidney injury, flank pain or dark urine is uncommon but needs prompt assessment.
- Dokezo la dawa: Allopurinol, febuxostat, probenecid, losartan, fenofibrate and some SGLT2 inhibitors can reduce serum urate to varying degrees.
- Kidokezo cha figo: A fractional excretion of uric acid above approximately 10% during hypouricemia supports renal urate wasting, but the cutoff is not absolute.
- Recheck plan: An isolated mild result can usually be repeated in 2-8 weeks after reviewing medicines, hydration, illness and the laboratory range.
- Further testing: Persistent urate below 2.0 mg/dL, recurrent stones, exercise-related kidney symptoms or a family pattern may justify urine urate and renal evaluation.
What does a low uric acid result mean?
Low uric acid usually means serum urate is below the laboratory reference interval, not that the body has no uric acid. Many clinicians use less than 2.0 mg/dL (119 µmol/L) to describe hypouricemia, while some laboratories flag less than 3.0 mg/dL (178 µmol/L), so the printed range and clinical context matter.

Serum urate is the circulating form of uric acid measured by a chemistry assay. Typical adult reference intervals are roughly 3.4-7.0 mg/dL (202-416 µmol/L) for men and 2.4-6.0 mg/dL (143-357 µmol/L) for women, but methods and populations differ; some European laboratories use lower or narrower limits.
A result of 2.6 mg/dL (155 µmol/L) may be flagged low by one laboratory and accepted by another, whereas 1.2 mg/dL (71 µmol/L) is clearly unusual in most adults. The number should be interpreted with creatinine, estimated GFR, liver tests, medication history and recent illness rather than treated as a diagnosis by itself.
Kantesti is an AI blood test analyzer that places serum urate beside kidney function, liver markers, glucose and medication-related clues instead of treating one flagged value as a disease. Our mwongozo wa kumbukumbu ya biomarker explains why laboratory intervals are not universal treatment thresholds.
| Kiwango | Wigo | Maana yake |
|---|---|---|
| Kipimo cha kawaida cha watu wazima | About 2.4-7.0 mg/dL (143-416 µmol/L) | Interpret against the specific laboratory, sex, age and clinical setting. |
| karibu na chini | About 2.0-3.0 mg/dL (119-178 µmol/L) | Often harmless when isolated; review trends, medicines, diet and hydration. |
| Hypouricemia | Below 2.0 mg/dL (119 µmol/L) | Persistent values warrant a cause-focused review, especially if symptoms or family history exist. |
| Matokeo ya chini sana | Below 1.0 mg/dL (59 µmol/L) | Not automatically an emergency, but repeat confirmation and renal or metabolic assessment are more reasonable. |
Why is low serum urate often overlooked?
Low serum urate is often overlooked because most clinical attention focuses on high urate, gout and kidney stones. A low flag frequently causes no symptoms and may be dismissed as nutritional variation, even though a persistent value below 2.0 mg/dL (119 µmol/L) can reveal a medication effect or renal transport problem.
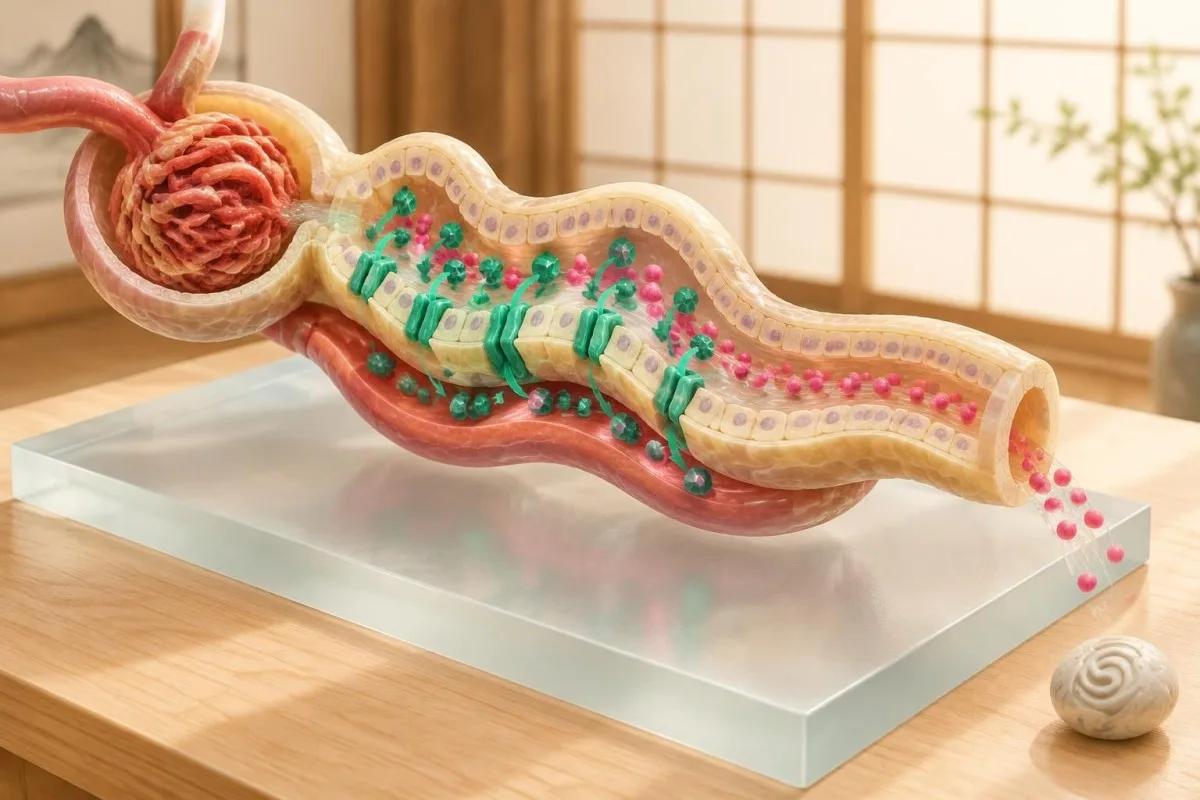
A single serum urate value has limited diagnostic power because it changes with fasting, fluid intake, recent exercise and assay timing. A fall from 4.1 to 2.1 mg/dL (244 to 125 µmol/L) after starting a medicine is more informative than one unexplained value of 2.7 mg/dL (161 µmol/L).
The direction of kidney function can also mislead interpretation: reduced filtration usually raises urate, while unusually efficient renal urate clearance can lower it. This is why a low result alongside an eGFR of 110 mL/min/1.73 m² deserves a different reading from a low result during acute illness with changing creatinine.
Results should be read as a timeline, not a collection of isolated flags; our mwongozo wa muda wa vipimo vya damu shows how diet, medicines and recent illness can make two apparently similar tests clinically different.
Which medicines can cause low uric acid?
Medicines are among the most common reversible causes of low uric acid, particularly urate-lowering therapy and drugs that increase urinary urate excretion. The result may be an intended treatment effect, not a new disease, but a sudden decline below 2.0 mg/dL (119 µmol/L) deserves medication reconciliation.
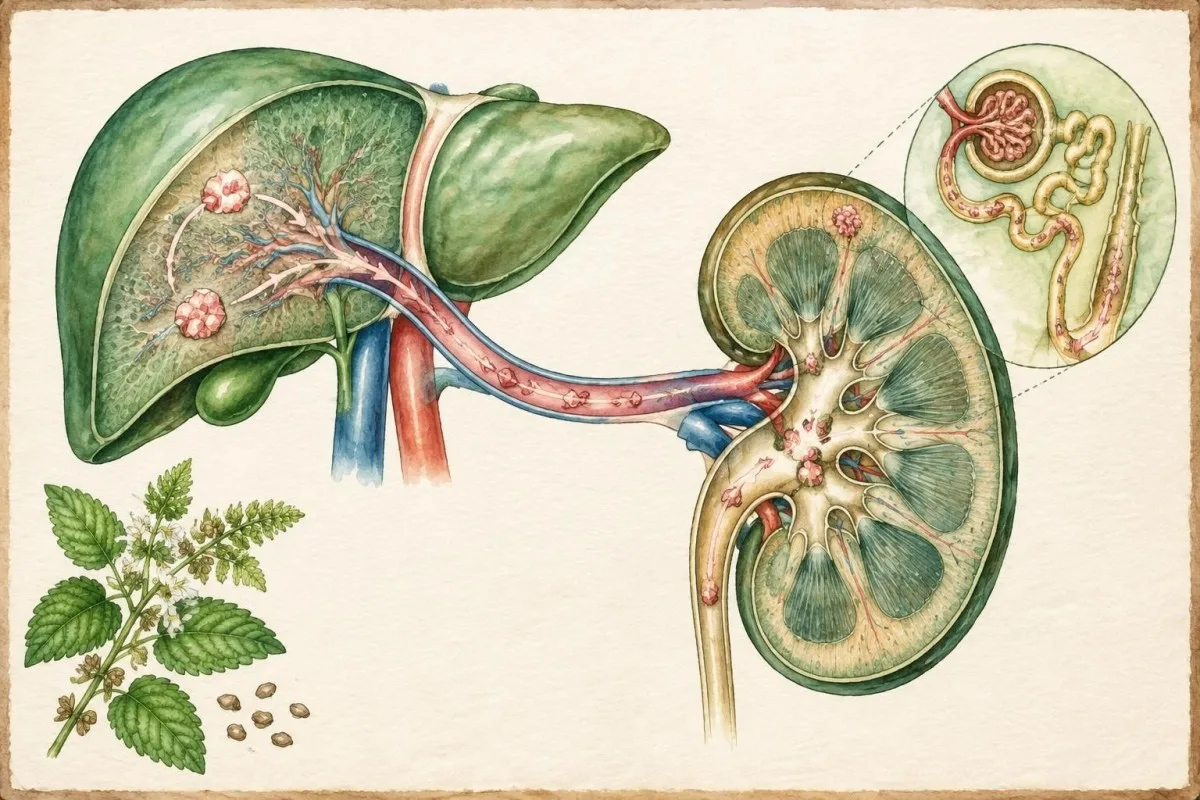
Allopurinol and febuxostat reduce urate production, while probenecid increases renal urate excretion; doses are adjusted for gout management rather than to maintain a particular minimum urate. Losartan and fenofibrate can have uricosuric effects, and SGLT2 inhibitors often lower serum urate by roughly 0.5-1.0 mg/dL (30-60 µmol/L), although individual responses vary.
For a hypothetical 68-year-old taking febuxostat whose urate falls from 7.8 to 1.8 mg/dL (464 to 107 µmol/L), the first question is whether the prescribed target has been overshot and whether the medicine is still appropriate. Do not stop or reduce treatment independently; the risk-benefit decision depends on gout history, kidney function and treatment goals.
Medication effects can be missed when a patient reports only prescription drugs and not supplements or recent dose changes; the medication-effects blood test guide offers a practical checklist for reviewing timing and trends.
Can diet, fasting or poor nutrition lower urate?
Low purine intake, prolonged fasting, low calorie intake and undernutrition can lower serum urate, but diet alone rarely explains a very low persistent value. A result below 2.0 mg/dL (119 µmol/L) should therefore be interpreted with weight change, albumin, liver markers, gastrointestinal symptoms and the overall dietary pattern.

Purines from cellular turnover and foods are converted into urate, so a sustained intake below approximately 400 mg of purines daily may contribute to lower production in some people. Severe calorie restriction, malabsorption, alcohol cessation after heavy use, or low protein intake can lower urate indirectly through reduced substrate and altered liver metabolism.
A hypothetical endurance athlete eating 1,200 kcal daily with an albumin of 30 g/L and urate of 1.7 mg/dL (101 µmol/L) needs nutritional assessment rather than a high-purine diet prescribed without supervision. Replacing energy and protein safely may help, but unexplained weight loss, chronic diarrhoea or persistent vomiting changes the priority.
Nutrition changes should account for kidney function and other results; our lishe ya figo explains why a diet designed for one renal problem can be unsuitable for another.
How do the kidneys create low uric acid?
The kidneys lower serum urate when filtered urate is reabsorbed less efficiently or secreted into urine more actively. Persistent hypouricemia with a high fractional excretion of uric acid, often above 10%, suggests renal urate wasting, although hydration and recent medicines can distort that calculation.

Most urate handling occurs in the proximal tubule, where transporters reabsorb and secrete urate in several steps rather than simply filtering it out. A fractional excretion of uric acid is calculated from serum and urine urate plus creatinine; values above approximately 10% during confirmed hypouricemia support renal wasting, while values below 5% suggest reduced production or another mechanism.
The evidence is mechanistically complex: transporters can change direction and activity, and a spot urine sample may not represent a full day. Bobulescu and Moe described this dynamic, bidirectional renal handling in their 2012 review in Advances in Chronic Kidney Disease, which is why a single urine ratio should not be treated as genetic proof.
A serum urate of 1.5 mg/dL (89 µmol/L) with normal creatinine and urine urate that remains high is a different pattern from low serum urate with very low urine urate; the Mwongozo wa BUN na creatinine helps place renal markers in sequence.
What inherited conditions cause hypouricemia?
Inherited renal hypouricemia usually results from altered urate transport, most often involving URAT1 or GLUT9 transporter pathways. It may remain unnoticed for years, but persistent urate below 2.0 mg/dL (119 µmol/L), a family pattern or exercise-related kidney injury makes inherited renal wasting more plausible.

SLC22A12 variants affect URAT1, while SLC2A9 variants affect GLUT9; both can impair tubular urate reabsorption. The 2004 JASN study by Ichida et al. identified URAT1-related renal hypouricemia in patients with markedly increased urinary urate excretion, demonstrating why a low serum result can reflect transport biology rather than inadequate production.
For a hypothetical 24-year-old with urate of 0.9 mg/dL (54 µmol/L), normal liver tests, normal nutrition and a sibling with a similar result, urine urate assessment and specialist advice are more useful than repeatedly changing diet. Genetic testing can confirm a variant, but a negative panel does not exclude every transport defect.
A previous episode of exercise-associated acute kidney injury strengthens the case for specialist review; a separate Wilson disease testing guide explains how clinicians distinguish rare metabolic clues from nonspecific liver or kidney abnormalities.
Why can low urate matter after intense exercise?
Some people with renal hypouricemia develop acute kidney injury after strenuous exercise, especially sprinting or intense interval training. The combination of urate below 2.0 mg/dL (119 µmol/L), severe flank or loin pain, nausea, reduced urine or dark urine after exercise needs prompt medical assessment.
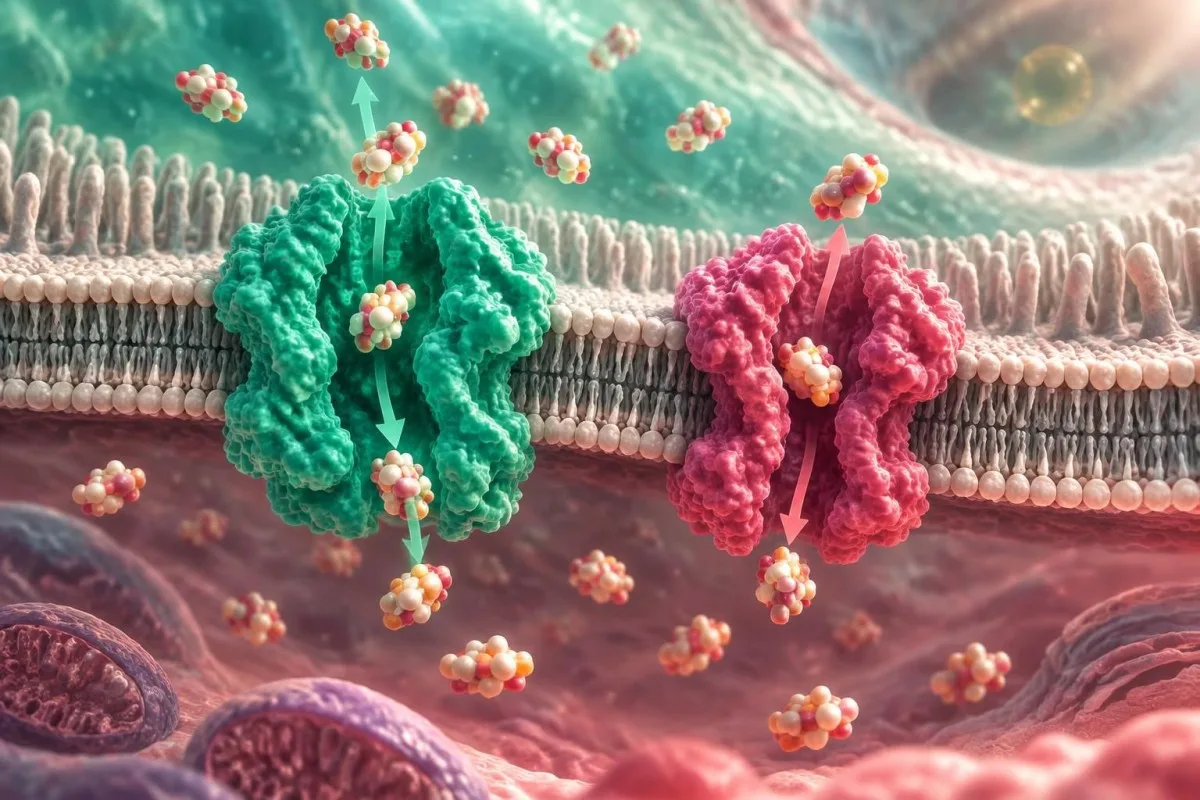
The mechanism is not fully settled; proposed contributors include intense muscle metabolism, renal vasoconstriction, oxidative stress and impaired urate antioxidant activity. Acute kidney injury is suggested by a creatinine rise of at least 0.3 mg/dL (26.5 µmol/L) within 48 hours or 1.5 times baseline within 7 days, regardless of the urate result.
Consider a hypothetical 31-year-old whose urate is 1.1 mg/dL (65 µmol/L) and creatinine rises from 0.9 to 1.5 mg/dL after repeated hill sprints. Continuing maximal exercise while waiting for a routine appointment would be unwise; same-day assessment can include repeat creatinine, electrolytes, urinalysis and hydration review.
People with recurrent symptoms should avoid assuming that sports supplements or aggressive rehydration are harmless; our urine citrate guide explains why urine chemistry needs to be interpreted as a pattern rather than a single target.
What symptoms can low uric acid cause?
Low uric acid itself usually causes no symptoms, so fatigue, weakness or dizziness should not automatically be blamed on a low serum urate. Symptoms become more concerning when they indicate the underlying cause, such as malnutrition, liver disease, medication adverse effects or exercise-related kidney injury.

There is no established symptom threshold at which low urate directly causes fatigue, headache or muscle weakness; a value of 1.8 mg/dL (107 µmol/L) can be completely asymptomatic. Urgent evaluation is more appropriate for reduced urine, severe flank pain, persistent vomiting, confusion, marked muscle weakness or cola-coloured urine after exercise.
A hypothetical person with urate of 2.2 mg/dL (131 µmol/L), normal creatinine and tiredness after poor sleep needs a broader fatigue assessment rather than urate treatment. By contrast, urate of 1.0 mg/dL (59 µmol/L) with new oliguria and a creatinine rise is a kidney problem until proven otherwise.
A low eGFR does not explain low urate in the usual way because impaired filtration tends to increase serum urate; our dalili za eGFR ya chini outlines which kidney findings deserve faster attention.
When should a low uric acid result be rechecked?
Repeat testing is sensible when low uric acid is unexpected, newly abnormal or below 2.0 mg/dL (119 µmol/L), with timing guided by symptoms and likely cause. An asymptomatic isolated result can often be repeated in 2-8 weeks, while medication changes, acute illness or kidney symptoms may require earlier clinician-directed testing.

Repeat the test under comparable conditions when possible: use the same laboratory, record fasting status, avoid unusual strenuous exercise for 24-48 hours and document all medicines and supplements. A change from 1.4 to 3.0 mg/dL (83 to 178 µmol/L) on repeat testing suggests a transient or pre-analytical factor, whereas two results below 2.0 mg/dL strengthen the case for evaluation.
If a urate-lowering drug was recently started, the prescriber may check the result at the medication's usual monitoring interval rather than stopping it immediately. The correct interval depends on treatment, kidney function and the reason for therapy; no universal recheck date applies to every low value.
Kantesti is an AI blood test interpretation platform that can compare dated urate, creatinine, eGFR, ALT and medication-related results so a clinician sees the direction of change. A repeat-test redraw guide also explains when a specimen problem justifies collecting a new sample.
Which tests investigate persistent hypouricemia?
Persistent hypouricemia is investigated with repeat serum urate, kidney function, urine urate handling and targeted tests for nutrition, liver disease or medication effects. The work-up should be proportional: a healthy person with one result of 2.8 mg/dL (167 µmol/L) needs less testing than someone with repeated values below 1.5 mg/dL (89 µmol/L).

A clinician may order serum creatinine, eGFR, electrolytes, bicarbonate, glucose, albumin, ALT, AST, complete blood count and urinalysis. A spot urine urate-to-creatinine ratio or fractional excretion calculation can assess renal wasting, while a 24-hour urine urate collection may help when stone risk or unusual excretion is suspected.
For example, urate of 1.3 mg/dL (77 µmol/L), eGFR 105, normal albumin and a high fractional excretion point toward renal urate loss; urate of 1.9 mg/dL with low albumin, anaemia and abnormal liver tests points toward systemic illness or undernutrition. Genetic testing is usually a second-stage decision, not the first response to a borderline result.
Urine sodium can add context when fluid balance or renal tubular handling is being considered; our mwongozo wa kutafsiri sodiamu kwenye mkojo explains why spot urine results change with diet, hydration and medicines.
How should low urate be read with other blood tests?
Low urate becomes more meaningful when it forms a pattern with kidney, liver, nutritional or electrolyte results. The reason clinicians compare markers is that low urate alone is usually benign, whereas low urate plus low albumin, abnormal liver tests or renal tubular findings can identify a broader process.

Low urate with normal albumin, normal liver enzymes, stable creatinine and no symptoms is commonly a low-risk isolated finding. Low urate with albumin below 35 g/L, ALT or AST above the laboratory upper limit, or new electrolyte abnormalities deserves review because those combinations suggest nutrition, liver or tubular disease more than urate itself.
A hypothetical 52-year-old with urate 1.7 mg/dL (101 µmol/L), albumin 29 g/L, ALT 92 IU/L and unintentional weight loss needs assessment for systemic illness, not a urate-raising supplement. In contrast, a runner with urate 1.7 mg/dL, albumin 46 g/L and stable renal markers may need only confirmation and exercise counselling.
Protein loss can complicate the picture when urine is persistently foamy or albumin is falling; the urine protein-to-creatinine guide explains how urine protein changes the interpretation of a chemistry panel.
Does low urate mean something different in pregnancy or childhood?
Pregnancy, childhood and adolescence require age- and stage-specific interpretation because plasma volume, growth, diet and kidney handling change serum urate. A value below 2.0 mg/dL (119 µmol/L) may be temporary in pregnancy, but persistent or symptomatic hypouricemia still deserves review.
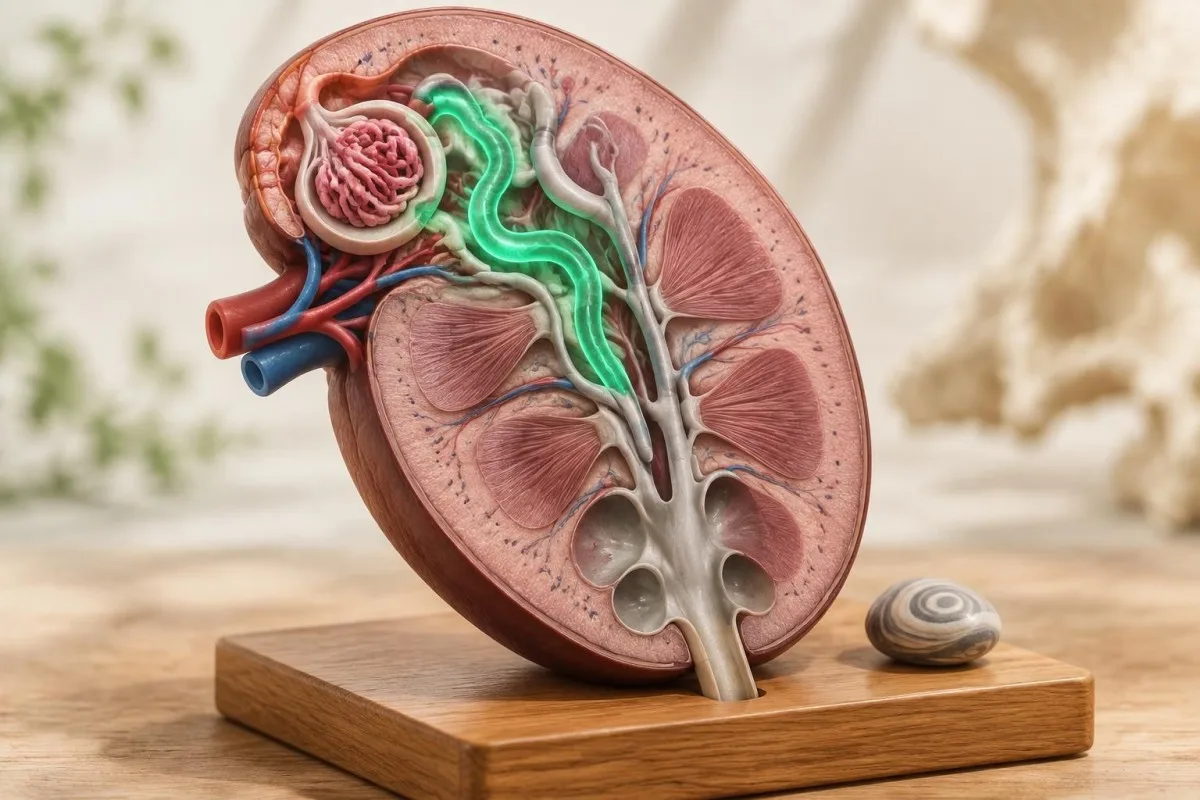
Serum urate often falls during early and mid-pregnancy because glomerular filtration and renal urate clearance increase, then rises later toward pre-pregnancy values. A low result must be interpreted with gestational age, blood pressure, proteinuria, vomiting, hydration and fetal or maternal concerns rather than a non-pregnant adult interval.
In children, laboratory ranges vary substantially by age and puberty; a 10-year-old with urate 2.0 mg/dL (119 µmol/L) cannot be assessed using an adult male cutoff alone. Persistent low values with poor growth, recurrent abdominal symptoms, excessive exercise or family history should be discussed with a paediatric clinician.
The same principle applies to test interpretation tools: Kantesti's AI can organize age, sex and pregnancy context, but a clinician must confirm decisions for children or pregnancy. Our mwongozo wa vipimo vya damu vya kila mwaka explains why screening panels should be risk-based rather than automatically expanded.
Could a laboratory issue make urate look low?
A specimen or reporting issue can produce an apparently low uric acid result, although persistent concordant results are less likely to be artefacts. Unexpected values should be checked against the assay method, sample quality, units and the laboratory's reference interval before launching an extensive work-up.
Urate may be reported in mg/dL or µmol/L, and 1 mg/dL equals approximately 59.48 µmol/L; unit confusion can make a normal result appear abnormal. A chemistry analyser may also use a different enzymatic method from a previous laboratory, so compare like with like when tracking a change.
For a hypothetical report showing 0.2 mmol/L, the value is about 3.36 mg/dL (200 µmol/L), not 0.2 mg/dL; checking units prevents an unnecessary alarm. If the number is discordant with previous results, ask whether the sample was delayed, diluted or affected by a reporting error, then repeat rather than self-treat.
Kantesti's platform can flag unit changes and trend discontinuities, but it cannot inspect specimen handling or override the reporting laboratory. A orodha yetu ya vipimo vya msingi husaidia kufanya vipimo vinavyorudiwa vilinganishike zaidi.
What should you do about a low uric acid result?
Most people should not try to raise uric acid deliberately after one low result. The safer response is to confirm the value, review medicines and nutrition, and investigate persistent or symptomatic hypouricemia rather than using high-purine foods, alcohol or supplements as treatment.

High-purine foods and alcohol can increase urate but may also increase gout, blood pressure, triglycerides and liver risk. There is no accepted supplement dose that safely corrects asymptomatic hypouricemia, and a value of 1.8 mg/dL (107 µmol/L) is not itself an indication for urate-raising treatment.
If allopurinol, febuxostat, probenecid, losartan, fenofibrate or an SGLT2 inhibitor is involved, the prescriber should decide whether the dose and indication remain appropriate. A person with a urate fall of 3.5 mg/dL (208 µmol/L) after a medication change should not stop therapy abruptly without discussing gout history, cardiovascular risk and kidney status.
Diet and supplements need the same caution when kidney disease is possible; our mwongozo wa usalama wa virutubisho vya figo explains why even non-prescription products can alter renal tests or interact with medicines.
How can a report trend improve low urate interpretation?
Trend analysis improves low uric acid interpretation by showing whether the result is stable, medication-related or part of a changing kidney or nutritional pattern. Three measurements over 3-6 months can be more informative than one isolated flag, provided the units, laboratory method and clinical circumstances are comparable.
Kantesti can organize dated urate, creatinine, eGFR, albumin, ALT, AST and glucose results into a readable trend, helping users identify a fall after a prescription change or a recovery after acute illness. A stable urate near 1.5 mg/dL (89 µmol/L) for 2 years has a different implication from a decline from 4.5 to 1.4 mg/dL (268 to 83 µmol/L) over 6 weeks.
The platform cannot diagnose inherited renal hypouricemia, interpret symptoms in isolation or replace urine testing; it is a preparation tool for a clinician conversation. Uploading the original report rather than manually retyping values also preserves units, reference intervals and neighbouring markers.
Kantesti is an AI-powered blood test analysis tool that summarizes patterns while keeping the original laboratory ranges visible. Its za uthibitisho wa kimatibabu describes the distinction between computational interpretation, clinical review and diagnosis.
A practical plan for your next low urate result
A practical plan is to classify the value, confirm the result, search for reversible causes and escalate only when the pattern warrants it. For most asymptomatic adults, a result between 2.0 and 3.0 mg/dL (119-178 µmol/L) can be reviewed at the next appointment, while values below 2.0 mg/dL or associated symptoms deserve closer follow-up.
First, record the exact value, units, reference interval, date, fasting status and recent exercise; second, review medicines, supplements, weight change and illness; third, repeat serum urate with creatinine and eGFR when the finding is unexpected. Two confirmed results below 2.0 mg/dL (119 µmol/L), especially with high urinary urate or a family pattern, justify discussing specialist assessment.
Seek prompt care for reduced urine, severe flank pain, persistent vomiting, confusion, substantial weakness or dark urine after intense exercise, because these features may indicate kidney injury rather than a harmless laboratory variation. Emergency assessment should be based on symptoms and accompanying results, not on the urate number alone.
Kantesti is an AI blood test analysis tool that helps convert a scattered report into questions for a qualified clinician, while our mwongozo wa teknolojia explains how context and trend data are handled. Keep the original report available for medical review.
Maswali ya mara kwa mara
Maana ya kiwango cha chini cha asidi ya uriki katika kipimo cha damu ni nini?
Asidi ya uriki iliyo chini kwa kawaida humaanisha kiwango cha urati katika seramu kiko chini ya kiwango rejea cha maabara, mara nyingi chini ya 2.0 mg/dL (119 µmol/L) madaktari wanapotumia neno hipourisemia. Baadhi ya maabara huashiria viwango vilivyo chini ya 3.0 mg/dL (178 µmol/L), kwa hiyo matokeo yanapaswa kulinganishwa na kiwango kilichochapishwa. Kiwango kimoja cha chini mara nyingi hakina madhara, lakini matokeo yanayoendelea kuwa chini yanaweza kuonyesha athari za dawa, ulaji mdogo, upotevu mkubwa wa urati kupitia figo au hali nadra ya kurithi inayohusu protini ya usafirishaji.
Je, kiwango cha chini cha asidi ya uriki ni hatari?
A low uric acid level is usually not dangerous when it is isolated, stable and symptom-free, even when it is around 2.0 mg/dL (119 µmol/L). Concern increases when urate remains below 1.5 mg/dL (89 µmol/L), falls rapidly after a medication change, or occurs with reduced urine, flank pain or dark urine after exercise. The danger usually comes from the underlying cause or associated kidney injury rather than from low urate itself.
Which medicines lower serum urate?
Allopurinol, febuxostat and probenecid can lower serum urate, while losartan, fenofibrate and some SGLT2 inhibitors may produce smaller reductions. SGLT2 inhibitors often lower urate by approximately 0.5-1.0 mg/dL (30-60 µmol/L), but individual responses vary. Do not stop or change any medicine because of a low result; the prescriber should consider the original indication, dose, kidney function and treatment goals.
When should low uric acid be rechecked?
An unexpected asymptomatic result can often be repeated in 2-8 weeks, while a medication change or acute illness may require a clinician-directed interval. Recheck sooner if urate is below 2.0 mg/dL (119 µmol/L) and there are kidney symptoms, major weight loss or abnormal creatinine. Use the same units and, when possible, the same laboratory so a change from 1.4 to 3.0 mg/dL (83 to 178 µmol/L) can be interpreted reliably.
Can dehydration cause low uric acid?
Dehydration more commonly concentrates serum urate and makes it higher, although complex illness, vomiting and changing kidney function can produce mixed results. A low urate result of 1.8 mg/dL (107 µmol/L) during severe illness should therefore be interpreted with creatinine, sodium, albumin and urine findings rather than attributed to dehydration alone. Repeat testing after recovery can distinguish a temporary pattern from persistent hypouricemia.
What tests are used for hypouricemia?
Evaluation can include repeat serum urate, creatinine, eGFR, electrolytes, albumin, liver tests, urinalysis and urine urate measurement. A fractional excretion of uric acid above approximately 10% during confirmed hypouricemia supports renal urate wasting, while a 24-hour urine urate collection may help when kidney stones or unusual excretion are present. Genetic testing for transporters such as URAT1 or GLUT9 is usually considered after persistent results and supportive clinical findings.
Pata maelezo ya jinsi ya kusoma matokeo ya vipimo vya damu
Pakia ripoti yako ya maabara na AI ya Kantesti itaeleza kila kiashiria cha kibayolojia kwa lugha rahisi ndani ya sekunde chache. Inatumiwa na zaidi ya watu milioni 2 duniani kote.
Marejeleo
- Klein, T., Mitchell, S., & Weber, H. (2026). Mwongozo wa Afya ya Wanawake: Ovulesheni, Kukoma Hedhi na Dalili za Homoni. Utafiti wa Kimatibabu wa AI ya Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Usaidizi wa Maamuzi ya Kliniki Unaosaidiwa na AI kwa Lugha Nyingi kwa Uchunguzi wa Awali wa Hantavirus: Muundo, Uthibitishaji wa Uhandisi na Utekelezaji wa Ulimwengu Halisi katika Ripoti 50,000 za Vipimo vya Damu Zilizotafsiriwa. Utafiti wa Kimatibabu wa AI ya Kantesti. DOI
- Ichida K et al. (2004). Clinical and molecular analysis of patients with renal hypouricemia in Japan—influence of URAT1 gene on urinary urate excretion. Jarida la Jumuiya ya Marekani ya Nephrology.
- Bobulescu IA, Moe OW (2012). Renal transport of uric acid: evolving concepts and uncertainties. Advances in Chronic Kidney Disease.
- 2M+Vipimo vilivyochanganuliwa
- 127+Nchi
- 100+Lugha
Kuhusu timu ya matibabu


E-E-A-T Trust Signals
Uzoefu
Mapitio ya kimatibabu inayoongozwa na daktari ya mifumo ya tafsiri ya maabara.
Utaalamu
Kuzingatia dawa za maabara kuhusu jinsi viashiria (biomarkers) vinavyobadilika katika muktadha wa kliniki.
Mamlaka
Imekaguliwa kimatibabu na Dkt. Thomas Klein, kwa michango kutoka kwa Dkt. Sarah Mitchell na Prof. Dkt. Hans Weber.
Uaminifu
Tafsiri inayotegemea ushahidi yenye njia zilizo wazi za ufuatiliaji ili kupunguza tahadhari za hofu.




Kanusho la kimatibabu
Makala haya ni kwa madhumuni ya elimu tu na si ushauri wa kimatibabu. Wasiliana na mtoa huduma aliyehitimu kila wakati kwa maamuzi ya utambuzi na matibabu.
Imechapishwa · Wasiliana na timu ya uhariri
Imechapishwa na Kantesti Ltd, imesajiliwa nchini Uingereza na Wales, nambari ya kampuni. 17090423, London, Uingereza.
