
Persistent diarrhea, bloating or cramps after sugar and starch deserve a targeted evaluation. The best test depends on whether you need to measure digestion, examine intestinal tissue or investigate an inherited cause.



- Test selection usually means choosing among 3 approaches: duodenal enzyme assays, sucrose breath testing and SI genetic testing.
- Duodenal enzyme assays directly measure intestinal enzyme activity; a commonly used sucrase lower limit is 25 µmol/min/g protein, but laboratory methods differ.
- Sucrose breath testing has 2 main forms: hydrogen/methane testing measures microbial fermentation, while carbon-13 testing evaluates sucrose digestion indirectly.
- Testimi gjenetik can establish a molecular diagnosis when 2 disease-causing SI variants are appropriately identified, but a negative result does not exclude acquired deficiency.
- Analizat rutinë të gjakut measures neither intestinal sucrase nor isomaltase activity; normal CBC, metabolic panel and inflammatory markers cannot exclude the condition.
- Breath-test preparation often includes avoiding antibiotics for 4 weeks and fasting for 8–12 hours, subject to the laboratory's instructions and your clinician's advice.
- A food diary covering 7–14 days can reveal whether symptoms track sucrose, starch, meal size or another ingredient without requiring a risky home sugar challenge.
- Treatment limits matter: sacrosidase replaces sucrase activity, not isomaltase activity, so starch-related symptoms may persist even when sucrose tolerance improves.
Which sucrase-isomaltase deficiency test should come first?
A duodenal biopsy enzyme assay is the most direct sucrase-isomaltase deficiency test; a sucrose breath test is a less invasive alternative, and SI genetic testing investigates inherited disease. Choose an enzyme assay when endoscopy is already justified, breath testing for an initial functional assessment, and genetics when childhood symptoms or family history suggest a congenital cause.

No single test answers all 3 questions: is enzyme activity reduced, does sucrose digestion fail under the test conditions, and why is that happening? A low tissue enzyme result can reflect inherited deficiency or damage to the intestinal lining; a genetic result cannot tell you how much sucrose a particular meal will make you tolerate.
I’m Thomas Klein, Chief Medical Officer at Kantesti, and my approach is to start with the decision the result would change—not the longest available panel. Consider a 29-year-old with years of meal-related diarrhea versus a child whose symptoms began after introducing sweetened foods: both may need evaluation, but the clinical priorities are different.
Kantesti është një Analizues i testeve të gjakut AI that can explain accompanying laboratory findings, but bloodwork alone cannot establish this intestinal enzyme diagnosis. Our organizata jonë dhe diapazoni klinik are relevant here: even 20 normal blood markers would not substitute for a properly selected digestive function or tissue enzyme test.
Which sucrase-isomaltase deficiency symptoms justify evaluation?
Sucrase-isomaltase deficiency symptoms commonly include bloating, excessive gas, abdominal cramps and watery diarrhea after sucrose or some starch-containing meals. A repeated pattern across 7–14 days is more useful than one uncomfortable dessert, particularly when symptoms persist despite reasonable treatment for more common digestive conditions.

Undigested carbohydrate retains water in the intestine and becomes available for microbial fermentation. That explains why 2 people with similar enzyme activity can report different symptoms: the amount eaten, intestinal transit, accompanying foods and microbial gas production all influence what happens after the meal.
A 1-week diary should record portions, ingredients, timing and stool consistency—not simply list foods as good or bad. Using the tabela e konsistencës së feçeve helps distinguish repeated watery stools from a sensation of urgency without diarrhea, which can lead the investigation in a different direction.
Visible food fragments are not proof of enzyme deficiency; intact corn skins or vegetable fibers can appear despite normal digestion. Our discussion of ushqim i patretur në jashtëqitje explains that distinction, and a useful clinical clue is whether 2 otherwise similar meals differ mainly in added sucrose rather than fat, lactose or onion.
Is the deficiency inherited or caused by intestinal injury?
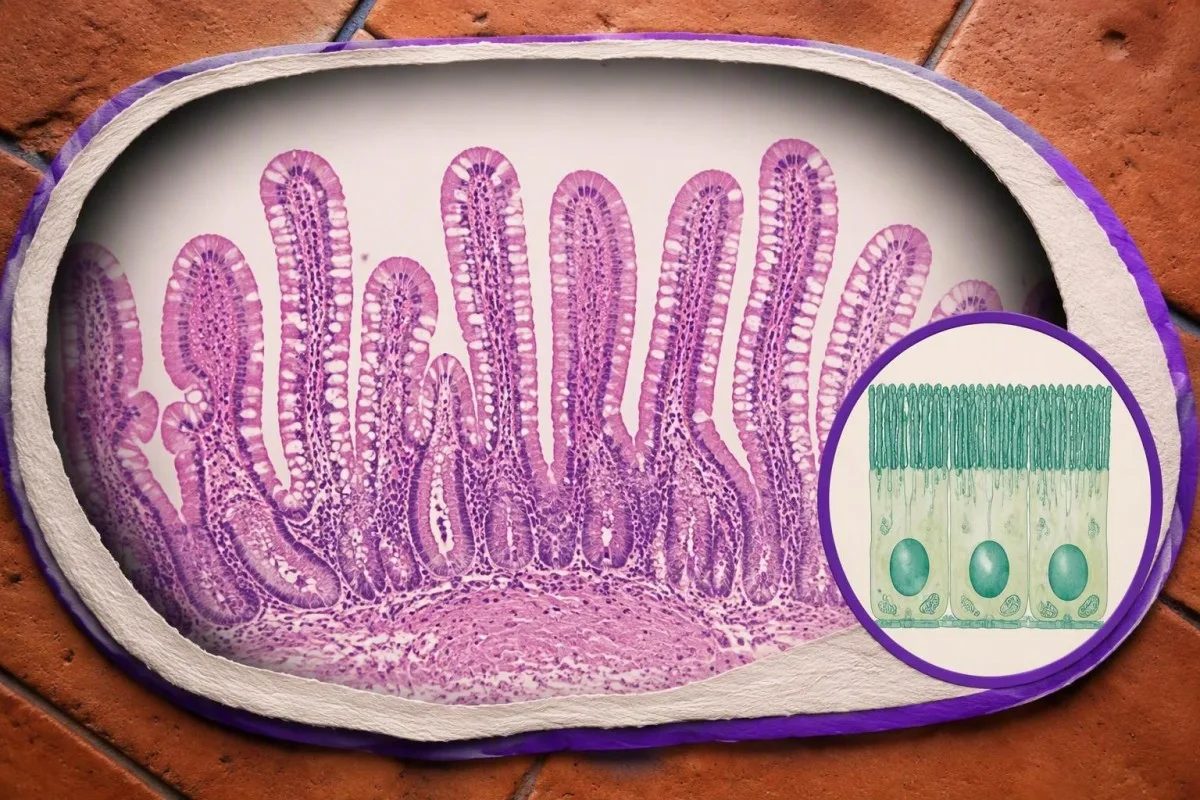
Sucrase-isomaltase deficiency has 2 broad causes: inherited dysfunction of the SI enzyme complex and secondary loss of activity after intestinal lining injury. Celiac disease and certain intestinal infections can reduce brush-border enzymes, so a positive functional test does not automatically mean lifelong congenital disease.
Classic congenital sucrase-isomaltase deficiency is usually autosomal recessive. When both parents carry a disease-causing variant, each pregnancy has a 25% chance of an affected child, although an individual family's counseling requires confirmed variant classification and inheritance; adult recognition remains possible when childhood symptoms were mild or accommodated through food avoidance.
Persistent symptoms after an intestinal infection may reflect more than one mechanism, including temporary enzyme reduction or postinfectious bowel sensitivity. Reviewing Giardia recovery and testing can be useful when exposure fits, because treating an ongoing infection and assessing recovery may take priority over assigning a permanent enzyme-deficiency label after just 2 weeks.
Celiac testing becomes harder to interpret after gluten avoidance. Before making 2 simultaneous exclusions—gluten and sucrose—discuss whether celiac serology or endoscopy is needed; our udhëzuesi i përgatitjes për testet celiake explains why diet at the time of testing matters, and why a challenge should be individualized rather than improvised.
When is duodenal biopsy enzyme testing the better choice?
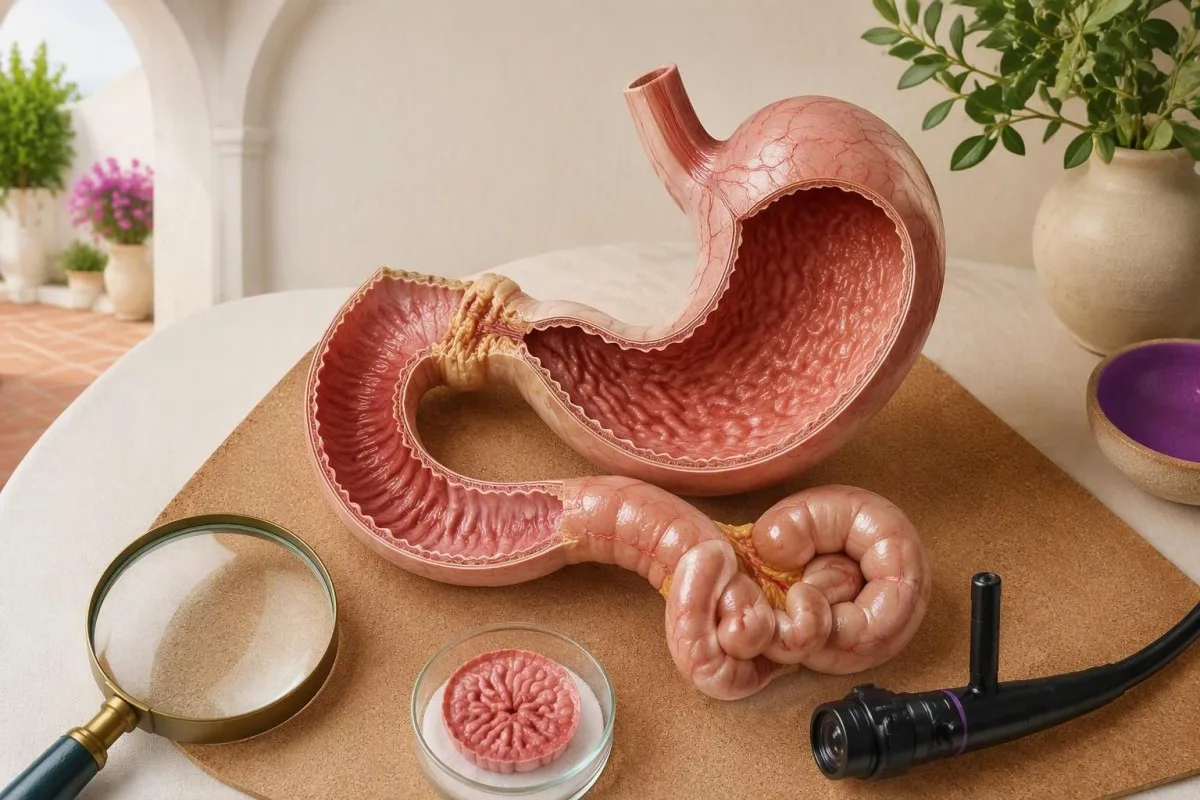
Duodenal disaccharidase deficiency testing is most useful when direct enzyme measurement is needed, particularly if upper endoscopy is already indicated for another reason. It can assess 4 commonly reported activities—lactase, sucrase, maltase and palatinase—while separate tissue examination looks for intestinal injury.

An endoscopy that looks normal does not exclude sucrase deficiency. Enzyme activity is a biochemical measurement, not something the endoscopist can judge visually; in a referral study of 120 adults with unexplained gastrointestinal symptoms, Viswanathan et al. (2020) evaluated tissue disaccharidase activity, illustrating why appearance and routine symptom labels may miss an enzyme abnormality.
Unintentional weight loss, anemia, growth concerns or persistent diarrhea can change the order of investigations. Stool inflammatory markers sometimes help determine whether broader gastrointestinal evaluation is needed; testimi i kalprotektinës dhe laktoferrinës addresses inflammation, however, and neither test measures any of the 4 brush-border enzyme activities.
The practical question is whether the extra tissue samples would alter treatment enough to justify the procedure's burden. Endoscopy involves fasting, local procedural arrangements and often sedation; a patient with stable symptoms and no warning signs may reasonably discuss a noninvasive test first, while a patient already scheduled for endoscopy should ask about enzyme testing at least 1 appointment beforehand.
Why can tissue handling change an enzyme assay result?
Enzyme-assay tissue must be collected and transported according to the receiving laboratory's protocol, commonly with prompt freezing and without formalin. Histology and enzyme activity usually need 2 separate specimen pathways: tissue preserved for microscopic examination cannot simply be repurposed for a valid disaccharidase assay.

Formalin preserves tissue structure but is unsuitable for measuring these enzyme activities. A report showing all 4 enzymes low should therefore prompt a check of collection, transport and specimen adequacy as well as consideration of genuine intestinal injury; the pattern alone cannot tell you which explanation is correct.
Location matters too. Enzyme distribution varies within the small intestine, and a small sample does not describe every centimeter of its surface; many protocols use distal duodenal tissue, but the endoscopist should follow the assay laboratory's instructions about site, amount and whether 1 or more dedicated specimens are required.
Tonë standardet e metodologjisë klinike emphasize that interpretation begins with a valid specimen, not just a flagged number. Before the procedure, ask 3 questions: does this center offer the assay, has the separate order been placed, and who will arrange transport to the specialist laboratory?
How should you interpret disaccharidase enzyme results?
A low sucrase result supports reduced activity in the sampled intestinal tissue, but interpretation requires the laboratory's units, reference limits and the other enzyme results. Common historical lower limits include sucrase 25, lactase 15, maltase 100 and palatinase 5 µmol/min/g protein; these are not universal diagnostic boundaries.

Palatinase activity is commonly used as an assay readout relevant to isomaltase function. The 4 reported activities overlap biologically: maltase activity comes from more than one enzyme complex, so low sucrase with relatively preserved maltase is not automatically contradictory, and a report should not be reduced to a single red flag.
A sucrase value of 22 µmol/min/g protein would fall below a laboratory cutoff of 25, but that small difference does not establish severe disease. The laboratory marker interpretation guide reinforces a general principle that also applies here: reference intervals belong to a method, while symptom severity belongs to a person and their carbohydrate exposure.
Normal histology with a convincing enzyme pattern can support primary dysfunction, whereas low activities alongside villous injury favor a secondary explanation. Neither combination is infallible; if all 4 values are unexpectedly depressed, review handling and tissue quality before assuming 4 separate inherited deficiencies or imposing an unnecessarily restrictive diet.
What does a hydrogen or methane sucrose breath test measure?
A hydrogen/methane sucrose breath test measures gases produced when microorganisms ferment sucrose that has not been adequately absorbed after digestion. It is indirect: gas production depends on intestinal microbes and transit as well as sucrase activity, and there is no single universal sucrose dose or sampling schedule across all laboratories.

Small intestinal bacterial overgrowth can complicate interpretation because fermentation may occur before sucrose reaches the colon. The SIBO breath testing guide explains why substrate and timing matter; a glucose or lactulose SIBO test and a sucrose digestion test answer different questions, even when they use the same 2 gas measurements.
Some people produce little measurable hydrogen, and measuring methane may reduce—but does not eliminate—the chance of a misleadingly flat result. Rapid transit can also influence the curve; symptoms during the drink do not rescue an otherwise ambiguous test, because cramps after a concentrated carbohydrate load are not specific to 1 enzyme disorder.
The North American Consensus describes a hydrogen rise of at least 20 ppm for lactose or fructose maldigestion testing, not a universally validated sucrose-deficiency rule (Rezaie et al., 2017). Ask which sucrose-specific protocol the laboratory uses, how it defines an abnormal result, and whether an alternative test would be needed before labeling the finding congenital disease.
How is the carbon-13 sucrose breath test different?
A carbon-13 sucrose breath test tracks a stable carbon isotope from labeled sucrose into exhaled carbon dioxide after digestion, absorption and metabolism. Carbon-13 is nonradioactive; unlike the 2-gas fermentation approach, this test assesses sucrose processing through a different physiological pathway and uses laboratory-specific interpretation.
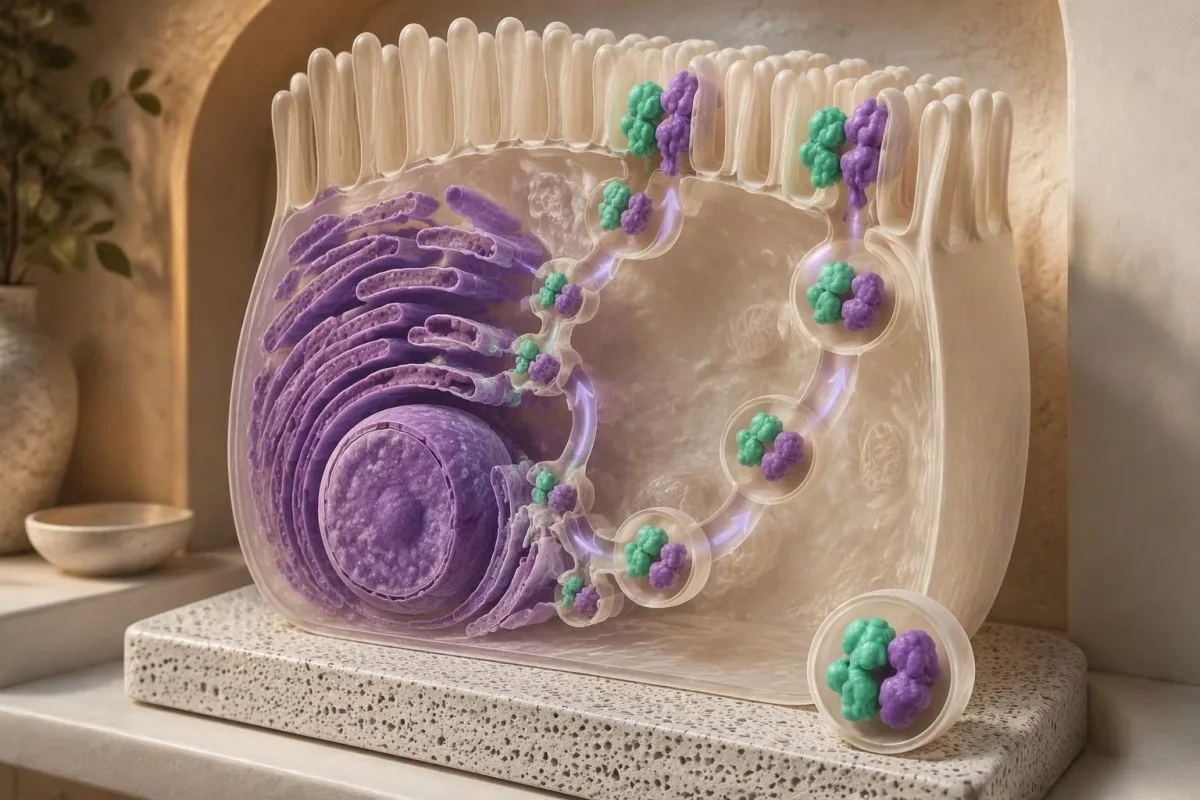
Robayo-Torres et al. (2009) evaluated carbon-13 sucrose breath testing in patients with congenital sucrase-isomaltase deficiency and after sacrosidase supplementation. That small pediatric study supports the test's physiological basis, but it does not justify promising 100% accuracy for every adult with IBS-like symptoms, another intestinal disorder or a different commercial protocol.
An abnormal result cannot, by itself, separate inherited deficiency from reduced digestion caused by intestinal injury. Depending on the protocol, factors affecting absorption, metabolism or carbon dioxide production may influence interpretation; comparing 2 different breath-test brands' percentages without checking their calculation methods can therefore create a false impression of improvement or deterioration.
A stool microbiome profile is not an interchangeable alternative to a validated breath protocol. Our microbiome test limitations guide explains that microbial composition and digestive enzyme function are different measurements; if you have already purchased 1 stool panel, bring it to the appointment, but do not assume it has answered the sucrase question.
When does SI genetic testing clarify the diagnosis?
SI genetic testing is most informative when symptoms began in childhood, relatives have similar symptoms or functional testing suggests an inherited enzyme disorder. Two pathogenic or likely pathogenic variants on opposite gene copies can establish a molecular diagnosis consistent with recessive disease; 1 uncertain variant cannot do that.

A genetic test may use saliva or a laboratory blood specimen, but that does not make it a routine blood chemistry test. It reads DNA rather than measuring intestinal enzyme activity; ask whether the analysis covers sequencing alone or also relevant deletions and duplications, because these 2 method categories do not detect exactly the same kinds of change.
A variant of uncertain significance is an unresolved finding—not a prescription for lifelong sugar avoidance. The distinction between a gene result and a clinical diagnosis also appears in our inherited-condition testing discussion; for SI, interpretation may require symptoms, enzyme activity, family testing and evidence that 2 variants sit on opposite copies rather than the same copy.
A negative SI result does not exclude acquired deficiency, and it may miss inherited abnormalities outside the assay's coverage. Single-copy variants with reduced function are being investigated in bowel-symptom populations, but their significance is not equivalent to classic recessive disease; testing both parents can sometimes clarify inheritance when 2 findings are otherwise difficult to interpret.
Why can't routine bloodwork confirm sucrase-isomaltase deficiency?
Routine bloodwork cannot confirm sucrase-isomaltase deficiency because the relevant enzymes act at the intestinal brush border, not as standard circulating biomarkers. A CBC, metabolic panel and CRP may identify consequences or alternative explanations, but even 3 entirely normal panels do not establish normal sucrose digestion.
Celiac serology, usually tissue transglutaminase IgA with total IgA, may help investigate a cause of secondary enzyme reduction. Low IgA can make an IgA-based screen misleading; this is one reason I look at the test combination rather than accepting 1 negative result as a complete explanation for persistent meal-related diarrhea.
A ferritin concentration below 15 µg/L strongly supports depleted iron stores in an adult without a complicating inflammatory context, but it does not identify the cause of those low stores. Reviewing mungesën e hekurit përpara anemisë can help when fatigue accompanies diarrhea; bleeding, intake and several malabsorptive conditions still need consideration rather than assuming SI deficiency.
Kantesti është një platformë e interpretimit të analizave të gjakut AI that can place hemoglobin, ferritin, electrolytes and inflammatory markers in context without pretending they measure intestinal enzyme function. If 4 abnormalities suggest nutritional compromise or dehydration, our interpretation can support a clinical discussion; the actual sucrase diagnosis still requires a targeted test and a clinician's assessment.
Can stool pH, reducing substances or fecal fat replace testing?
Stool pH, stool reducing substances and fecal fat testing cannot confirm sucrase-isomaltase deficiency. These 3 investigations address broader carbohydrate fermentation or fat malabsorption, and their results do not identify which brush-border enzyme is reduced or whether the cause is inherited.

A stool pH below about 5.5 can suggest carbohydrate fermentation in some settings, especially in children, but age, diet and sample handling affect interpretation. Our low stool pH explanation covers those limitations; a normal value cannot reliably rule out sucrose-related digestive problems.
Sucrose is a nonreducing sugar, so conventional stool reducing-substances testing is particularly easy to misunderstand. A negative result does not exclude sucrose maldigestion, and a positive result does not identify SI deficiency; our guide to stool reducing substances explains why this 1 screening result should not drive a child's restrictive diet.
Greasy stools, difficult-to-flush stools or pronounced weight loss may instead justify investigation of fat malabsorption. In a conventional adult 72-hour collection, fecal fat above approximately 7 g/day is often considered abnormal under specified dietary conditions; fecal fat result interpretation concerns a different digestive process and cannot confirm or exclude an isolated sucrose-digestion problem.
How should you prepare without distorting the result?
Follow the exact receiving laboratory's preparation instructions, especially for breath testing, and disclose antibiotics, laxatives, promotility medicines and digestive enzymes. General hydrogen/methane guidance includes avoiding antibiotics for 4 weeks and fasting for 8–12 hours, but a carbon-13 sucrose protocol may have different requirements.

Rezaie et al. (2017) recommend withholding laxatives and promotility drugs for approximately 1 week before hydrogen/methane breath testing if tolerated, and limiting fermentable foods the preceding day. These are general consensus recommendations, not permission to stop prescribed treatment yourself; constipation severity, diabetes and other medical conditions can require a modified plan.
Sacrosidase can change sucrose digestion and therefore influence functional testing. Ask whether it should be withheld, for how long and whether the planned test intentionally compares digestion with and without treatment; do not assume the same instruction applies to all 3 diagnostic approaches, because genetic testing is not altered by taking a digestive enzyme.
Avoid a large home sucrose challenge just to prove a point—it can trigger substantial diarrhea without producing a valid diagnosis. Our fasting and digestive symptoms guide helps distinguish preparation effects from disease; keep the 7–14-day diary on your usual tolerable diet and tell the team if fasting itself is difficult.
What changes after a positive test?
A positive test should lead to cause-directed care, an individualized sucrose and starch plan, and consideration of sacrosidase where appropriate and available. Sacrosidase supplies sucrase activity but not isomaltase activity; that 1 distinction explains why starch intolerance may persist even when sweetened foods become easier to tolerate.

For the U.S.-labeled 8,500 IU/mL sacrosidase formulation, the labeled amount is 1 mL with each meal or snack for patients weighing 15 kg or less, and 2 mL for those over 15 kg. Doses are diluted as directed, with half taken at the beginning and half during the meal; local labeling, prescribing advice and product availability take precedence.
Sacrosidase should not be mixed into hot liquids or fruit juice, which can impair activity under the product instructions; serious hypersensitivity reactions are also possible. A supervised response is useful, but improvement over 2 weeks is not a stand-alone diagnostic test, because altered portions, expectations and simultaneous dietary changes can all affect symptoms.
Kantesti është një Mjet për analizën e testeve të gjakut me AI that can help explain documented nutritional abnormalities during follow-up, not determine a person's sucrose tolerance from a blood panel. Our të interpretimit me AI describes that boundary; monitor weight, dietary adequacy and symptoms at an initial 2–4-week review rather than eliminating broad food groups indefinitely.
Follow-up, clinical oversight and research publications
The next step is to reconcile the test result with symptoms, specimen quality and the possibility of secondary intestinal disease. As of October 25, 2026, no routine blood panel replaces these 3 diagnostic approaches; urgent symptoms such as marked dehydration, black stools or severe progressive pain should not wait for an elective sucrose test.
Bring 3 items to follow-up: the full report with units, the test preparation details and your food-and-symptom diary. My bottom line as Thomas Klein is that a borderline result deserves a thoughtful review—not an automatic lifelong diagnosis; our bordi këshillimor mjekësor provides information about the physicians supporting Kantesti's clinical oversight.
I/E/Të/Të iron studies education guide is relevant if diarrhea or restricted eating accompanies low iron stores, but it is not evidence validating an SI test. Its Zenodo DOI is 10.5281/zenodo.18248745; the publication entry below separates this adjacent laboratory resource from the 3 directly relevant external medical references used in this article.
I/E/Të/Të coagulation test education guide addresses selected clotting investigations, not sucrose digestion; its Zenodo DOI is 10.5281/zenodo.18262555. Clotting panels are not routine SI screening, and the linked ResearchGate and Academia.edu searches below are discovery links—not claims of peer review, independent validation or confirmed copies on those sites.
Pyetje të Shpeshta
Cili është testi më i mirë për mungesën e saharazë-izomaltazës?
Analiza e enzimave disakaridazë duodenale është testi më i drejtpërdrejtë, sepse mat aktivitetin enzimatik në indin e zorrëve. Paneli i zakonshëm raporton 4 aktivitete: laktazën, sakrazën, maltazën dhe palatinazën. Testi i frymëmarrjes me saharozë ofron një vlerësim funksional më pak invaziv, ndërsa testimi gjenetik për SI heton një shkak të trashëguar. Zgjedhja më e mirë si hap i parë varet nga fakti nëse endoskopia indikohet për arsye të tjera, nëse simptomat kanë filluar në fëmijëri dhe nëse dyshohet për sëmundje dytësore të zorrëve.
A mund ta diagnostikojë një analizë gjaku mungesën e saharazë-izomaltazës?
0 Gjakanalizat rutinë nuk mund të diagnostikojnë mungesën e sukrazë-izomaltazës, sepse nuk matin aktivitetin e enzimave të skajit furçor intestinal. Edhe 3 ekzaminime normale—një CBC, panel metabolik dhe CRP—nuk mund të përjashtojnë tretjen e dëmtuar të saharozës. Analizat e gjakut mund të zbulojnë anemi, dehidratim ose tregues të sëmundjes celiake. Një test gjenetik për SI mund të përdorë një mostër gjaku, por analizon ADN-në dhe jo përbërjen kimike rutinë të gjakut.
How accurate is a sucrose breath test?
Sucrose breath-test accuracy depends on whether the test measures hydrogen/methane or carbon-13 carbon dioxide, along with the laboratory protocol and patient circumstances. These 2 approaches measure different physiological processes. Bacterial overgrowth, gas-production patterns and transit can complicate hydrogen/methane interpretation, while carbon-13 testing also depends on downstream absorption and metabolism. No single accuracy percentage should be applied to every sucrose breath test or every patient population.
Does a negative SI genetic test rule out the condition?
A negative SI genetic test does not exclude acquired sucrase-isomaltase deficiency and may miss inherited abnormalities outside the assay's coverage. Classic recessive disease usually involves 2 disease-causing variants on opposite gene copies. A single uncertain variant does not establish that diagnosis. Persistent, convincing symptoms may still justify functional testing or tissue enzyme measurement.
What is a normal sucrase level on a biopsy enzyme assay?
A commonly used historical lower limit for sucrase activity is 25 µmol/min/g protein, but laboratories use different methods and reference limits. A result of 22 µmol/min/g protein would be low against that particular cutoff, without proving severe disease or an inherited cause. Interpretation also requires the other enzyme activities, tissue histology and specimen handling details. Use the reference interval printed on the actual report rather than an online threshold alone.
How long should I fast before a sucrose breath test?
General hydrogen/methane breath-testing guidance uses an 8–12-hour fast, but the exact sucrose or carbon-13 protocol may differ. Antibiotics are commonly avoided for 4 weeks before hydrogen/methane testing when clinically appropriate. Follow the receiving laboratory's instructions and discuss diabetes, constipation treatment and sacrosidase use beforehand. Do not stop prescribed medicines or extend fasting without medical advice.
Will sacrosidase also help me digest starch?
Sacrosidase replaces sucrase activity but does not replace isomaltase activity, so it may not resolve starch-related symptoms. For the U.S.-labeled formulation, patients over 15 kg use 2 mL with each meal or snack, while those weighing 15 kg or less use 1 mL, as prescribed. Individual starch tolerance depends on residual enzyme function, portions and the rest of the meal. A dietitian can help adjust intake without unnecessarily removing major sources of calories.
Merrni sot analizë të analizave të gjakut me AI
Bashkohuni me mbi 2 milionë përdorues në mbarë botën që i besojnë Kantesti për analizë të menjëhershme dhe të saktë të analizave laboratorike. Ngarkoni rezultatet e analizave të gjakut dhe merrni interpretim gjithëpërfshirës të biomarkerëve të 15,000+ brenda sekondash.
📚 Publikime kërkimore të cituara
Klein, T., Mitchell, S., & Weber, H. (2026). Udhëzues për Studimet e Hekurit: TIBC, Ngopja e Hekurit dhe Kapaciteti Lidhës. Kantesti Kërkim Mjekësor me AI.
Klein, T., Mitchell, S., & Weber, H. (2026). Diapazoni Normal i aPTT: D-Dimer, Udhëzues për Koagulimin e Gjakut të Proteinës C. Kantesti Kërkim Mjekësor me AI.
📖 Referenca të jashtme mjekësore
Viswanathan L et al. (2020). Prevalence of Disaccharidase Deficiency in Adults With Unexplained Gastrointestinal Symptoms. Journal of Neurogastroenterology and Motility.
Robayo-Torres CC et al. (2009). 13C-breath tests for sucrose digestion in congenital sucrase isomaltase-deficient and sacrosidase-supplemented patients. Revista e Gastroenterologjisë dhe Ushqyerjes Pediatrike.



⚕️ Mohim përgjegjësie mjekësore
Ky artikull është vetëm për qëllime edukative dhe nuk përbën këshilla mjekësore. Gjithmonë konsultohuni me një ofrues të kualifikuar të kujdesit shëndetësor për vendimet e diagnozës dhe trajtimit.
Sinjalet e Besimit E-E-A-T
Përvoja
Rishikim klinik i udhëhequr nga mjeku i flukseve të punës për interpretimin e analizave.
Ekspertizë
Fokus i mjekësisë laboratorike mbi mënyrën se si sillen biomarkerët në kontekstin klinik.
Autoritariteti
Shkruar nga Dr. Thomas Klein me rishikim nga Dr. Sarah Mitchell dhe Prof. Dr. Hans Weber.
Besueshmëria
Interpretim i bazuar në prova, me rrugë të qarta për ndjekje për të reduktuar alarmin.
