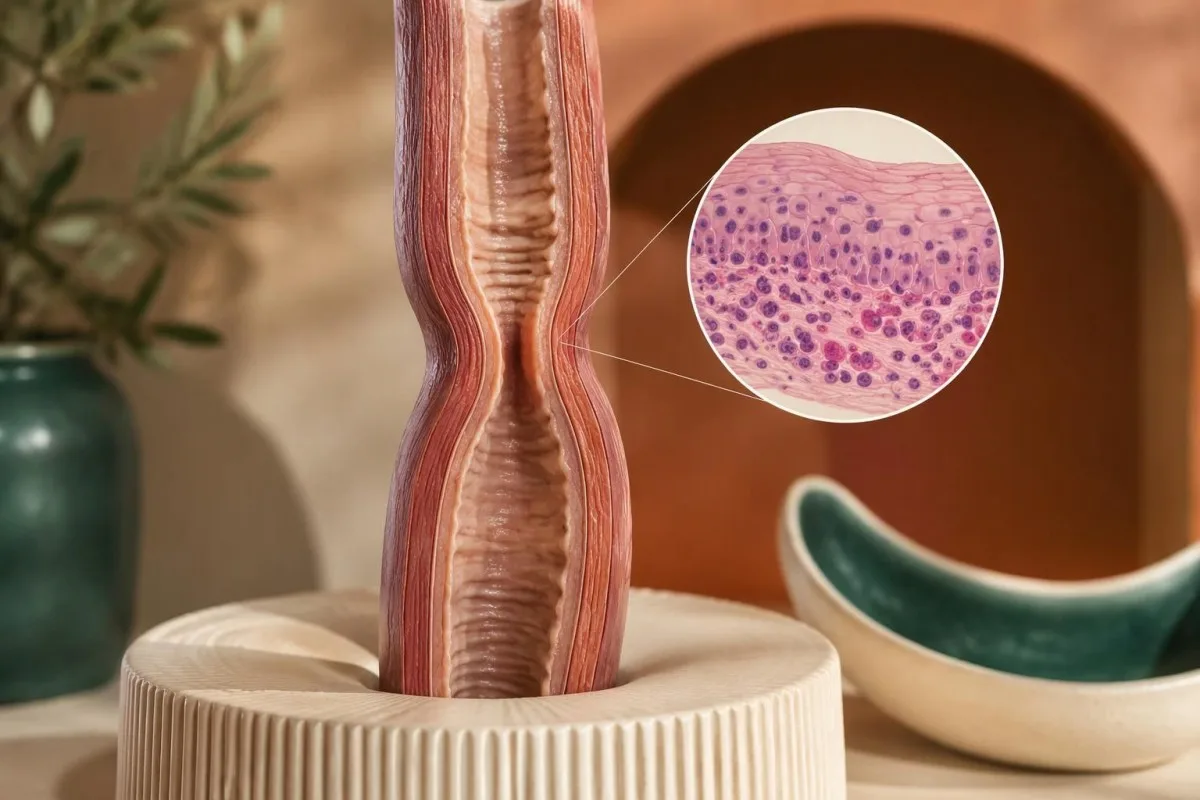
Eosinophilic esophagitis diagnosis requires swallowing-related symptoms and esophageal biopsies showing at least 15 eosinophils per high-power field, with alternative causes assessed. A normal blood eosinophil count cannot exclude EoE, and an elevated count cannot confirm it.

Principais conclusões
- Diagnóstico requires symptoms of esophageal dysfunction, at least 15 eosinophils per high-power field on biopsy, and assessment of other causes.
- Biopsy sampling should include at least 6 esophageal specimens from at least 2 levels because EoE can be patchy.
- Blood eosinophils commonly have an adult laboratory reference interval around 0.0–0.5 × 10⁹/L; neither a normal nor elevated result settles an EoE diagnosis.
- Food impaction with inability to swallow saliva requires emergency assessment now—not a repeat blood test or a routine appointment.
- Endoscopy appearance cannot exclude EoE: biopsies remain necessary when symptoms suggest it, even if the esophagus looks normal.
- PPI response does not exclude EoE, and a failed proton pump inhibitor trial is no longer a mandatory diagnostic requirement.
- Treatment exposure can lower tissue counts below 15 eos/hpf; tell the endoscopy team about acid suppression, dietary restriction, and steroid medicines.
- Acompanhamento often combines symptoms, endoscopic findings, and repeat biopsies around 8–12 weeks after starting or changing treatment; the schedule depends on the therapy.
What establishes an eosinophilic esophagitis diagnosis?
Eosinophilic esophagitis diagnosis rests on 3 linked findings: symptoms of esophageal dysfunction, a peak biopsy count of at least 15 eosinophils per high-power field, and assessment of other explanations for esophageal eosinophilia. No blood test can replace that tissue-based evaluation.

The American College of Gastroenterology's 2025 guideline uses this combined clinical and histological approach rather than diagnosing EoE from an isolated laboratory abnormality (ACG, 2025). The threshold identifies a characteristic degree of tissue eosinophilia; it does not establish why the cells accumulated or how severely swallowing is affected.
An incidental count of 20 eos/hpf in someone without recognized esophageal symptoms does not automatically establish EoE. Clinicians first check for overlooked food avoidance or prolonged meals, then consider whether the finding represents asymptomatic esophageal eosinophilia or another process; the pathology label and clinical diagnosis are not interchangeable.
Kantesti é um Analisador de teste de sangue de IA that can explain a circulating eosinophil count such as 0.3 × 10⁹/L, but cannot determine whether eosinophils have accumulated in esophageal tissue. That distinction matters because a normal complete blood count may otherwise create false reassurance about persistent swallowing difficulty.
Nosso organização e propósito describe Kantesti Ltd, UK Company No. 17090423, and our focus on explaining laboratory information. For suspected EoE, the useful question is not whether an algorithm detects an abnormal count—it is whether your symptoms warrant gastroenterology assessment and adequately sampled esophageal biopsies.
Which eosinophilic esophagitis symptoms prompt investigation?
Eosinophilic esophagitis symptoms commonly include solid-food swallowing difficulty and food impaction in adults, while children may have feeding refusal, vomiting, or poor growth. A person who needs 45 minutos to finish a meal because food repeatedly sticks may have substantial dysfunction despite describing symptoms as mild.

Adaptive eating can hide dysphagia for years. For example, a hypothetical homem de 29 anos who avoids bread, cuts every bite into tiny pieces, and drinks after each mouthful may report no swallowing problem until asked what happens without those adjustments; the adaptations are clinically useful clues, not proof of EoE.
Solid-food difficulty suggests a narrowed or inflamed esophagus, whereas difficulty with both solids and liquids raises additional concern about a motility disorder. Neither pattern is absolute: documenting 2 details—food consistency and when sticking occurs—helps clinicians choose between structural assessment, tissue examination, and later motility testing.
Children do not need to describe classic food sticking for EoE to be considered. A hypothetical 6 anos who rejects textured foods and has slowed weight gain needs pediatric assessment; our explanation of children's laboratory interpretation limits addresses why adult blood reference intervals cannot substitute for that evaluation.
Um registro útil de sintomas abrange 7 dias of meal duration, avoided textures, regurgitation, and episodes requiring food to be brought back up. Also record whether swallowing is painful, because painful swallowing can broaden the differential toward medication-related injury or infection rather than simply confirming an allergic explanation.
When does food impaction require emergency endoscopy?
Food impaction with inability to swallow saliva requires emergency assessment immediately. Não espere 24 horas, repeat a blood count, or try to force food down; persistent esophageal obstruction can require urgent endoscopic removal even when breathing remains normal.
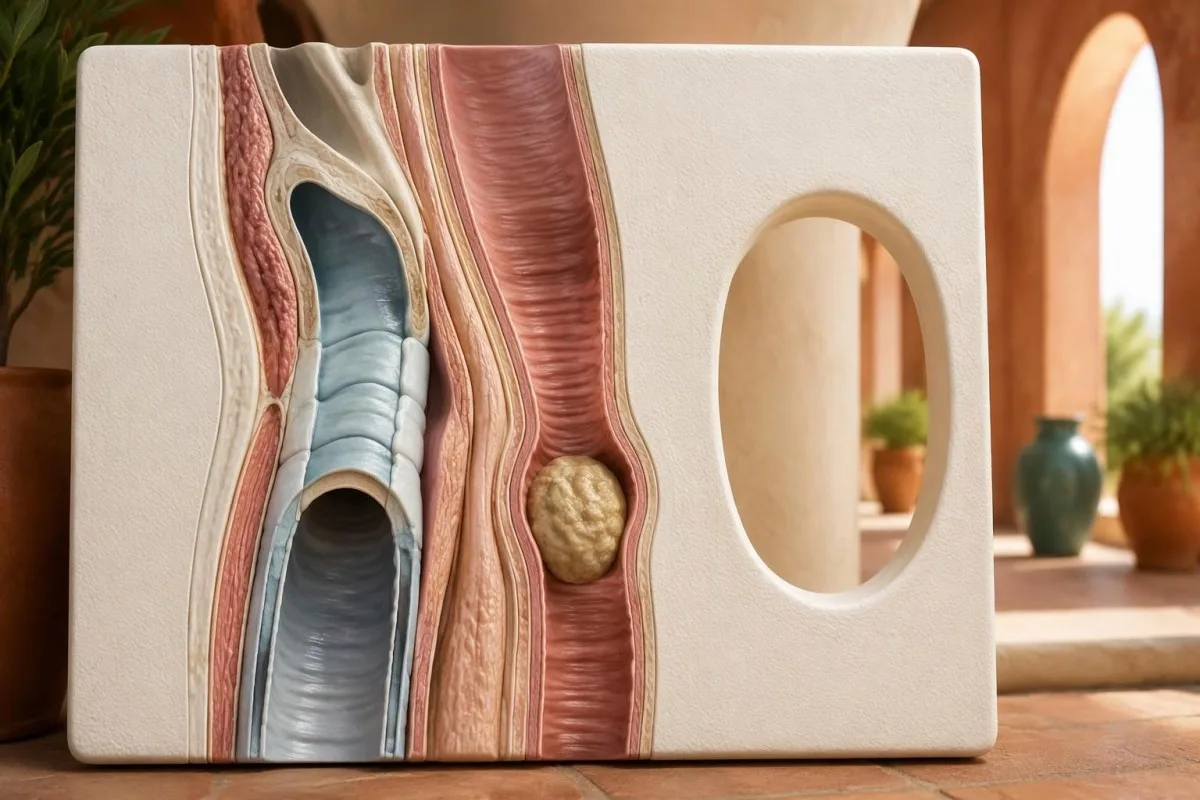
An esophageal blockage and an airway blockage are 2 different emergencies. If someone cannot breathe, speak, or cough effectively, activate emergency services and follow local choking guidance; if breathing is preserved but saliva cannot be swallowed, emergency assessment is still needed for possible esophageal obstruction.
A bolus that remains stuck despite the ability to swallow some saliva still needs urgent assessment, not a routine clinic booking. Even after just 30 minutos in a hypothetical episode, escalating pain, repeated regurgitation, or inability to manage secretions should prevent further eating and drinking while emergency advice is sought.
Clinicians can investigate the underlying cause during the same endoscopy used to remove food, taking esophageal samples when safe and avoiding traumatized contact areas. The usual diagnostic target remains at least 6 specimens; if sampling is unsafe or incomplete, the discharge plan should explicitly arrange follow-up endoscopy rather than treating removal as the end of care.
Severe chest pain after an impaction, fever, or sudden deterioration may indicate a complication or another emergency. Our guide to chest pain testing limits explica por que 1 normal blood result is not permission to wait; emergency assessment takes priority over any online interpretation.
Why can a normal-looking endoscopy still need biopsies?
A normal-looking esophagus does not exclude EoE, because microscopic inflammation may exist without obvious surface changes. When symptoms suggest EoE, clinicians should obtain at least 6 biopsies from 2 or more esophageal levels, rather than using visual appearance as a screening test that decides whether tissue is needed.
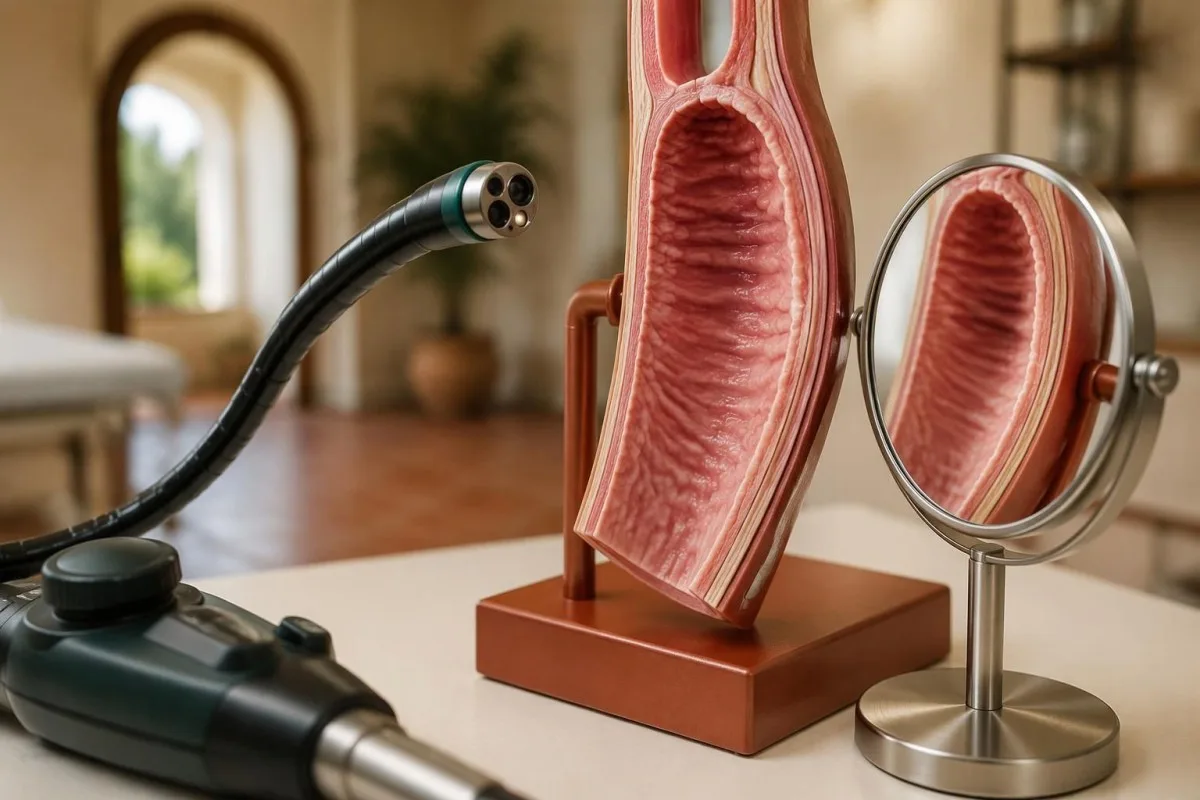
Recognized endoscopic features include edema, rings, white exudates, longitudinal furrows, and strictures. The 5-feature EREFS system records these findings consistently, but the score is not a substitute for histology; white surface material, for example, can have more than one explanation and requires contextual interpretation.
Visual and microscopic findings answer different questions. A hypothetical patient may have marked rings but only 8 eos/hpf while receiving treatment, because established remodeling can persist after active eosinophilic inflammation has decreased; interpreting this as either no disease or uncontrolled inflammation would oversimplify the evidence.
Reflux-like symptoms do not remove the need to investigate swallowing difficulty. Our reflux warning signs guide separates common heartburn patterns from alarm symptoms; 1 episode of food impaction can justify investigation even if antacids usually improve burning discomfort.
Endoscopy also identifies structural alternatives, including a focal ring or other narrowing, while allowing targeted tissue sampling. Ask for 2 documents—the endoscopy report and pathology report—because an apparently reassuring description of the surface cannot explain whether specimens were taken, where they came from, or what the tissue showed.
Why are at least six biopsies taken from two levels?
EoE is patchy, so a single esophageal biopsy can miss diagnostic inflammation. The ACG's 2025 guideline recommends at least 6 biopsies from at least 2 esophageal levels, targeting visible abnormalities when present while still sampling adequately if the surface appears normal.

The British joint guideline also recommends at least 6 biopsies from different esophageal sites, supporting broad agreement on sampling rather than reliance on one suspicious spot (BSG/BSPGHAN, 2022). The rationale is diagnostic sensitivity: a small specimen examines only a tiny part of an organ with unevenly distributed inflammation.
A common practical arrangement is 3 distal specimens and 3 proximal or middle specimens, although the precise allocation can vary. Separating samples by level helps the pathologist report distribution; inflammation confined distally may raise reflux-related questions, but distribution alone cannot reliably distinguish reflux from EoE.
An inadequate sampling result is not equivalent to a negative disease evaluation. For example, 2 distal samples with 7 eos/hpf in a hypothetical person with recurrent impaction leave more uncertainty than a properly sampled study, especially if the person was already taking acid suppression or restricting likely dietary triggers.
Review the specimen labels, not just the final impression. Our verificação de origem de relatórios médicos explain why the original report matters; ask whether 2 levels were sampled, whether the number of tissue fragments was adequate, and whether the findings fit the symptoms before requesting repeat testing.
What do the EoE biopsy criteria mean on a pathology report?
The central EoE biopsy criterion is a peak count of at least 15 eosinophils per high-power field, interpreted alongside symptoms and alternative causes. “Peak” means the most densely involved field, not an average across every sample; an isolated qualifying field can matter when the clinical picture fits.
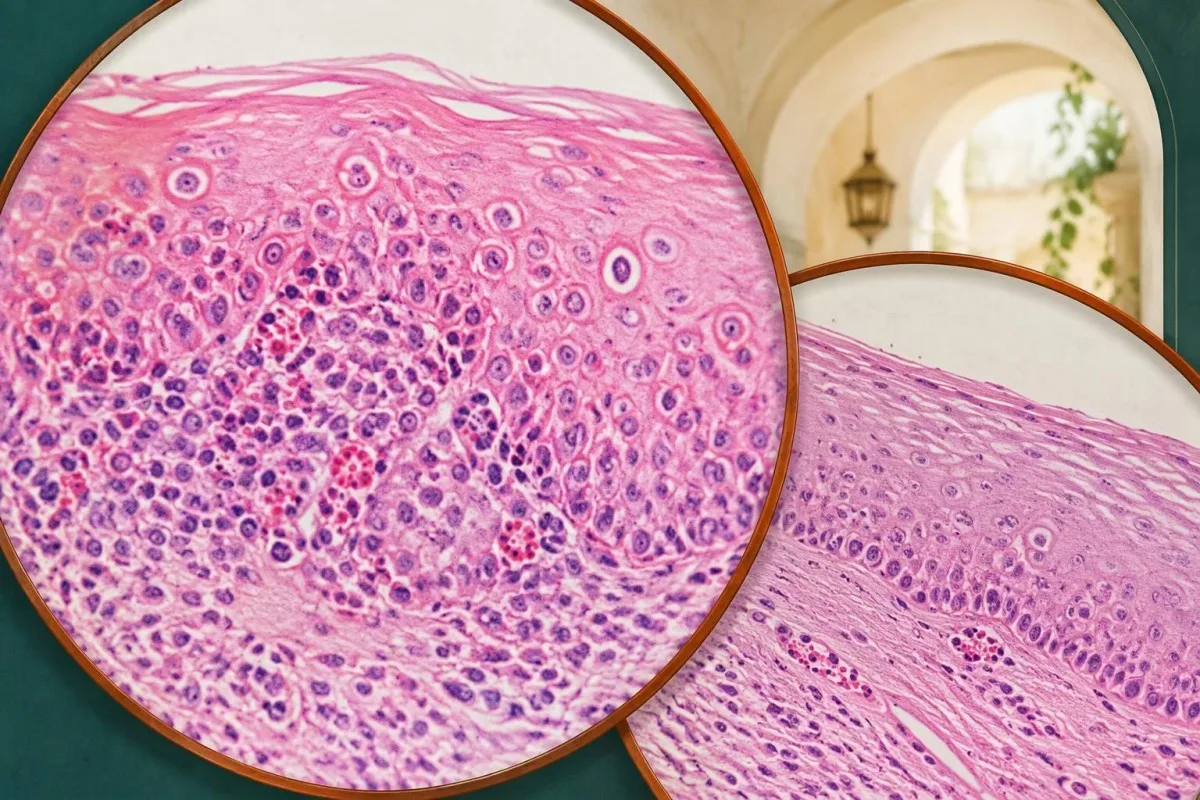
A high-power field is an area, not a universally identical unit. For example, 15 eosinophils in 0.24 mm² equals 62.5 eos/mm², whereas 15 in 0.30 mm² equals 50 eos/mm²; this explains why reports using cells per square millimeter need their field area checked before comparison.
Some guidelines describe approximately 60 eos/mm² as comparable to the traditional 15 eos/hpf threshold, but microscope field sizes differ. The threshold is a consensus-based clinical boundary supported by disease characterization, not a biological switch; a count of 14 and a count of 15 should not erase the importance of treatment exposure and sampling quality.
A report saying “increased eosinophils” without a number is less actionable than one stating “peak 32 eos/hpf” and naming the specimen level. Our guide to resultados qualitativos versus quantitativos explains that general reporting distinction; for EoE, a numerical tissue count is needed to assess the histological criterion.
Higher counts do not create a reliable severity ladder. A hypothetical count of 80 eos/hpf can indicate substantial active inflammation, but it does not by itself tell clinicians whether the esophagus has a dangerous narrowing; swallowing history, endoscopic caliber, and evidence of remodeling must be assessed separately.
What else do esophageal biopsies show besides eosinophils?
Esophageal biopsies can show epithelial injury and remodeling features in addition to eosinophil density. The peak 15 eos/hpf threshold is central to diagnosis, but basal-zone hyperplasia, intercellular swelling, eosinophil layering, and tissue fibrosis can add context when the specimen contains the relevant tissue.
Eosinophil microabscesses are small tissue clusters, not proof of bacterial infection. In a hypothetical report with 35 eos/hpf and surface layering, the arrangement supports an eosinophilic inflammatory pattern, but the clinician still needs symptoms and assessment of alternative causes rather than treating a descriptive pathology feature as an independent diagnosis.
Routine specimens often contain mainly epithelium and little underlying lamina propria. A report with 0 assessable fragments of lamina propria cannot reliably establish absence of fibrosis; “fibrosis not identified” may describe a sampling limitation rather than an esophagus free of remodeling.
Persistent swallowing difficulty after tissue counts fall can reflect a stricture or a motility problem rather than continuing eosinophilic activity. Our esophageal manometry explanation describes 3 achalasia subtypes; motility testing enters the pathway when endoscopy, histology, and symptoms do not adequately explain one another.
Histological remission and mechanical recovery are different treatment goals. For example, a hypothetical patient with 5 eos/hpf but persistent narrowing may need a structural assessment and possibly dilation; dilation can improve passage of food, but does not replace anti-inflammatory treatment for established EoE.
Why cannot blood eosinophil counts confirm or exclude EoE?
Blood eosinophils and esophageal eosinophils measure different compartments, so blood counts cannot confirm or exclude EoE. Many adult laboratories use an absolute eosinophil reference interval around 0,0–0,5 × 10⁹/L, but a result within that interval says nothing definitive about the peak tissue count.

EoE can recruit eosinophils into the esophageal lining without producing a diagnostically useful rise in circulation. A hypothetical patient with 0,2 × 10⁹/L in blood and 45 eos/hpf in tissue illustrates the mismatch; the normal circulating value should not override a properly established tissue-based diagnosis.
An elevated blood count also lacks specificity. A hypothetical result of 0,9 × 10⁹/L might reflect eczema, asthma, a medication reaction, parasite exposure, or another condition, with or without EoE; our elevated eosinophil interpretation guide explains why the differential extends beyond the esophagus.
O contagem absoluta is usually more informative than the percentage alone. If the total white count is 8.0 × 10⁹/L and eosinophils are 4%, the absolute count is 0.32 × 10⁹/L, or 320 cells/µL; percentages can look different simply because another white-cell population has changed.
Kantesti é um plataforma de interpretação de exame de sangue da AI that can explain a result such as 320 cells/µL without treating it as an EoE screening threshold. Our guia de biomarcadores no sangue supports reading units and laboratory intervals correctly; no validated routine blood cutoff currently replaces esophageal biopsies.
Which blood tests can still help during an EoE evaluation?
Blood tests can identify accompanying problems or alternative diagnoses, but they do not establish EoE. An absolute eosinophil count around 1.5 × 10⁹/L or higher, particularly if persistent or accompanied by systemic symptoms, merits broader assessment rather than being automatically attributed to esophageal disease.

Marked circulating eosinophilia changes the clinical question from “is there local EoE?” to “could another eosinophilic process also be present?” A hypothetical repeated count of 2.2 × 10⁹/L with rash, breathing symptoms, or cardiac symptoms needs clinician-led assessment; the count alone does not diagnose hypereosinophilic syndrome, which requires additional clinical evaluation.
Parasite testing should follow exposure history, not a blanket panel for every person with dysphagia. Our Strongyloides antibody interpretation guide explains one relevant pathway; exposure deserves attention before systemic steroid treatment, because an unrecognized infection can change medication safety decisions.
Restricted intake may justify checking nutritional status. A hypothetical ferritin of 9 ng/mL in someone avoiding many foods suggests depleted iron stores, not proof that EoE caused the deficiency; our guia dos primeiros sintomas de ferritina baixa and separate interpretação exame de sangue de ferro explain complementary parts of that assessment.
Kantesti AI can help explain a circulating count of 1,8 × 10⁹/L alongside laboratory ranges and trends, while the clinician investigates its cause. Total IgE, specific IgE, and inflammatory markers may answer other questions, but none provides an accepted numerical rule that confirms EoE or safely cancels indicated biopsies.
What alternative causes of esophageal eosinophils are assessed?
Esophageal eosinophilia can occur with reflux and other inflammatory, infectious, medication-related, or systemic conditions. A count of 15 eos/hpf or more therefore triggers clinical interpretation—not automatic labeling—and EoE and gastroesophageal reflux disease can coexist rather than being mutually exclusive diagnoses.
Reflux is assessed using symptoms, endoscopic findings, treatment history, and sometimes reflux testing, not a single tissue-location rule. A hypothetical distal count of 18 eos/hpf with erosive reflux needs more context; distal predominance may support reflux-related reasoning, but does not reliably rule out EoE.
Medication injury and infectious esophagitis become more relevant when painful swallowing, immune suppression, or a compatible exposure accompanies the biopsy finding. A clinician reviewing 3 items—the medication list, immune status, and pathology description—can decide whether targeted tests are needed; indiscriminate testing may introduce unrelated positive results.
Other considerations include Crohn's disease, eosinophilic gastrointestinal disease beyond the esophagus, connective-tissue disorders, and systemic eosinophilic conditions. If swallowing difficulty accompanies persistent abdominal symptoms, clinicians may sample additional gastrointestinal sites when indicated, rather than assuming every eosinophil-related symptom belongs to isolated EoE.
A positive parasite antibody result does not establish the cause of esophageal findings. Our Toxocara antibody interpretation guide explains why exposure, symptoms, and supporting evidence matter; 1 positive serology should not automatically displace an otherwise well-supported EoE diagnosis or trigger treatment without assessment.
Does improvement with a proton pump inhibitor rule out EoE?
Improvement with a proton pump inhibitor does not rule out EoE, and a failed PPI trial is no longer required before diagnosis. The 2018 AGREE international consensus removed that mandatory diagnostic step because PPI responsiveness does not reliably separate EoE from reflux-related disease.

The AGREE consensus treats PPIs as a treatment option rather than an exclusion test (AGREE Conference, 2018). Their effects can involve acid suppression and changes in inflammatory signaling, so improvement does not prove that acid exposure was the only mechanism behind tissue eosinophilia.
Treatment before diagnostic sampling can obscure the untreated tissue pattern. A hypothetical patient with recurrent food sticking and 6 eos/hpf while taking a PPI has a result that must be interpreted against medication exposure; that count alone cannot exclude EoE or establish what the untreated count would have been.
Heartburn relief is not the same as histological control. Over a hypothetical 8-week course, burning discomfort might disappear while swallowing adaptations continue; clinicians assess the different symptom domains and, when appropriate, repeat endoscopy rather than using overall improvement as proof of a particular diagnosis.
Acid suppression also affects some unrelated blood tests. Our PPI-related gastrin explanation describes why medication context matters; 1 altered biomarker may reflect treatment rather than a new disease, but it does not tell the clinician whether esophageal eosinophilia has resolved.
How can treatment and diet affect diagnostic biopsy results?
PPIs, swallowed steroids, dietary elimination, and some other steroid exposures can reduce esophageal eosinophils before diagnostic biopsies. The British joint guideline recommends withholding PPIs for at least 3 semanas before diagnostic endoscopy when clinically appropriate; medication changes must be agreed with the treating team, not undertaken independently.

The ACG's 2025 guidance also advises an initial diagnostic examination off therapies that could produce a false-negative result when feasible. The ideal washout is not equally established for every therapy, and urgent impaction care must not be delayed to complete a washout; this is one area where safety and diagnostic purity can conflict.
Do not stop essential asthma treatment or other prescribed steroids solely because of an online biopsy-preparation checklist. A hypothetical 2 semanas interruption could compromise another condition without guaranteeing an interpretable EoE result; tell gastroenterology about inhaled and intranasal steroids so the teams can weigh the actual risks.
Food-specific IgE tests do not reliably identify which foods drive EoE tissue inflammation. Our guia de teste de alergia a componentes explains what such tests can address; 1 positive food IgE result may indicate sensitization or immediate allergy risk, but is not an accepted substitute for biopsy-guided EoE evaluation.
Disease-specific preparation plans are not interchangeable. Our celiac gluten challenge explanation concerns a different diagnostic pathway; someone with 1 previous impaction should not deliberately reintroduce difficult foods or suspected allergens without clinical advice simply to make an EoE test more revealing.
How do clinicians interpret real-world biopsy patterns?
Clinicians interpret biopsy counts alongside sampling, treatment exposure, symptoms, and alternative causes—not in isolation. In a clearly hypothetical example, recurrent solid-food dysphagia plus adequately sampled counts of 32 proximal and 48 distal eos/hpf can support EoE even when the blood eosinophil count is normal.

Considere um hipotético homem de 34 anos with two food impactions, six biopsies from two levels, and no better alternative explanation for the tissue pattern. That combination supports a tissue-based EoE diagnosis; an absolute blood count of 0.25 × 10⁹/L does not weaken it simply because the laboratory labels the count normal.
A different hypothetical report shows 12 eos/hpf from two distal samples during PPI treatment, despite continuing dysphagia. This does not meet the usual numerical criterion on that examination, but the limited sampling and treatment exposure may justify a planned reassessment; it should not be converted into either a confirmed diagnosis or confident exclusion.
After treatment, a hypothetical reduction from 48 to 6 eos/hpf indicates substantial histological improvement, yet persistent food sticking still needs explanation. Dilation, anti-inflammatory therapy, and dietary treatment address different aspects of disease; symptom improvement after dilation does not demonstrate that mucosal inflammation is controlled.
Repeat endoscopy with biopsies is often considered around 8–12 semanas after starting or changing therapy, with timing adapted to the treatment and clinical situation. Our test timing and medication guide explains the broader principle that exposure changes results; blood trends still cannot replace tissue-based EoE follow-up.
What should you ask next, and where does AI interpretation fit?
The next step is to clarify whether symptoms, adequate biopsies, and the exclusion of better explanations support EoE. Bring the endoscopy and pathology reports, and ask about the 6-biopsy, 2-level sampling standard; AI interpretation can explain accompanying laboratory results but cannot perform the required tissue assessment.

Kantesti é um plataforma de interpretação de biomarcadores por IA that can help explain blood eosinophils reported in cells/µL or × 10⁹/L, without treating either unit as a diagnostic EoE test. Our explicação da tecnologia de IA describes the laboratory-focused workflow; a gastroenterologist and pathologist remain responsible for establishing the clinical diagnosis.
Our role is explanation, not confirmation of a tissue-defined disorder. Kantesti's informações sobre metodologia clínica should not be read as evidence that an AI output can verify a 15 eos/hpf finding, determine sampling adequacy from missing documents, or authorize medication withdrawal before endoscopy.
Pergunte 4 practical questions: Were enough levels sampled, what was the peak count and field unit, could treatment have suppressed the result, and what explains persistent swallowing difficulty? Our princípios de IA responsável reinforce that uncertainty and missing evidence should remain visible rather than being replaced by a confident label.
O 2 Kantesti educational publications listed below are companion reading, not EoE clinical trials, biopsy-validation studies, or evidence for the diagnostic threshold. The digestive symptom companion guide concerns other gastrointestinal questions; the directly relevant evidence here comes from the ACG, AGREE, and British joint guidelines.
Perguntas frequentes
Uma contagem normal de eosinófilos no sangue pode descartar esofagite eosinofílica?
Uma contagem normal de eosinófilos no sangue não pode descartar a esofagite eosinofílica, pois as células circulantes não refletem de forma confiável a inflamação do revestimento do esôfago. Muitos laboratórios para adultos usam um intervalo de referência em torno de 0,0–0,5 × 10⁹/L, mas a EoE pode ocorrer dentro desse intervalo. O diagnóstico requer sintomas compatíveis, biópsias esofágicas que mostrem pelo menos 15 eosinófilos por campo de grande aumento e avaliação de causas alternativas. A dificuldade persistente para engolir deve ser avaliada mesmo quando o hemograma completo está normal.
Quantas biópsias são necessárias para diagnosticar EoE?
The ACG's 2025 guideline recommends at least 6 esophageal biopsies from at least 2 levels when evaluating suspected EoE. Sampling multiple locations reduces the risk of missing patchy inflammation. Visible abnormalities can guide sampling, but a normal-looking esophagus still needs biopsies when symptoms suggest EoE. If an earlier examination took only a small number of samples, clinicians may reconsider whether it adequately assessed the condition.
O que significa 15 eosinófilos por campo de grande aumento?
Pelo menos 15 eosinófilos por campo de grande aumento é o limiar histológico central utilizado no diagnóstico de EoE. O patologista informa a densidade máxima, em vez de calcular a média de todas as amostras esofágicas em conjunto. A área do campo de grande aumento varia entre microscópios, portanto, os laudos que usam eosinófilos por milímetro quadrado exigem atenção à área real do campo. O limiar deve ser interpretado considerando os sintomas, a exposição ao tratamento, a qualidade da amostragem e outras possíveis causas de eosinofilia esofágica.
É possível ter EoE se sua endoscopia parecer normal?
A EoE pode estar presente mesmo quando a superfície esofágica parece normal à endoscopia. A inflamação eosinofílica microscópica pode não produzir anéis, sulcos ou exsudatos evidentes. Quando os sintomas sugerem EoE, os médicos devem obter pelo menos 6 biópsias de pelo menos 2 níveis do esôfago. Um laudo que descreva aparência normal sem coleta adequada de tecido não exclui a condição de forma confiável.
Responder ao omeprazol ou a outro IBP significa que não é EoE?
Uma resposta ao omeprazol ou a outro inibidor da bomba de prótons não exclui a EoE. O consenso internacional AGREE de 2018 removeu a exigência de falha em um teste com IBP antes do diagnóstico, reconhecendo que a resposta aos IBPs não distingue de forma confiável a EoE da doença relacionada ao refluxo. Os IBPs podem reduzir os sintomas e os eosinófilos nos tecidos, dificultando a interpretação de biópsias realizadas durante o tratamento como uma avaliação diagnóstica sem tratamento. Não interrompa um IBP prescrito sem um plano clínico acordado.
O que devo fazer se a comida ficar presa e eu não conseguir engolir a saliva?
0 Food preso no esôfago com incapacidade de engolir saliva requer avaliação de emergência imediata. Não espere 24 horas, não tente forçá-lo a descer com alimentos ou bebidas nem confie em um exame de sangue para decidir se é necessário procurar atendimento. Se a respiração, a fala ou a tosse eficaz estiverem comprometidas, acione os serviços de emergência e siga as orientações locais para engasgos. Após o tratamento da obstrução imediata, os profissionais de saúde devem providenciar uma avaliação da causa subjacente, incluindo biópsias esofágicas quando apropriado e seguro.
0. Uma biópsia com menos de 15 eosinófilos significa que a EoE foi curada?
A follow-up biopsy below 15 eosinophils per high-power field can indicate histological response, but does not establish that EoE has been permanently cured. Tissue counts may fall with treatment while narrowing or swallowing adaptations persist. Clinicians commonly reassess symptoms, endoscopic findings, and biopsies around 8–12 weeks after starting or changing therapy, with timing tailored to the treatment. Continuing treatment and monitoring decisions depend on the full clinical picture rather than the count alone.
Entenda os resultados do seu exame de sangue
Envie o laudo do seu exame, e a IA da Kantesti explica cada biomarcador em linguagem simples em segundos. Usada por mais de 2 milhões de pessoas em todo o mundo.
Referências
- Klein, T., Mitchell, S., & Weber, H. (2026). Guia sobre tipo sanguíneo B negativo, exame de sangue LDH e contagem de reticulócitos. Pesquisa médica com IA da Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Diarreia após jejum, pontos pretos nas fezes e guia gastrointestinal 2026. Pesquisa médica com IA da Kantesti. DOI
- Dellon ES et al. (2025). ACG Clinical Guideline: Diagnosis and Management of Eosinophilic Esophagitis. The American Journal of Gastroenterology. DOI
- Dellon ES et al. (2018). Updated International Consensus Diagnostic Criteria for Eosinophilic Esophagitis: Proceedings of the AGREE Conference. Gastroenterologia. DOI PubMed
- Dhar A et al. (2022). British Society of Gastroenterology (BSG) and British Society of Paediatric Gastroenterology, Hepatology and Nutrition (BSPGHAN) joint consensus guidelines on the diagnosis and management of eosinophilic oesophagitis in children and adults. Gut. DOI
- 2 milhões+Exames analisados
- 127+Países
- 100+Idiomas
Sobre a equipe médica


Sinais de confiança E-E-A-T
Experiência
Revisão clínica orientada por médicos dos fluxos de interpretação de exames laboratoriais.
Especialização
Foco em medicina laboratorial sobre como os biomarcadores se comportam no contexto clínico.
Autoridade
Revisado clinicamente pelo Dr. Thomas Klein, com contribuições da Dra. Sarah Mitchell e do Prof. Dr. Hans Weber.
Confiabilidade
Interpretação baseada em evidências, com caminhos de acompanhamento claros para reduzir alarmes.





Aviso médico
Este artigo é apenas para fins educacionais e não constitui aconselhamento médico. Consulte sempre um profissional de saúde qualificado para decisões de diagnóstico e tratamento.
Publicado · Entre em contato com a equipe editorial
Publicado por Kantesti Ltd, registrado na Inglaterra e no País de Gales, número da empresa. 17090423, Londres, Reino Unido.
