A yellow bowel movement is often a short-lived food or fast-transit change, but greasy persistence, dark urine, pain, fever, or weight loss changes the calculation. The pattern matters more than one glance in the toilet.


- Brief yellow stool after a high-fat meal, turmeric, carrots, or a diarrheal illness is commonly harmless when it resolves within 48-72 hours.
- Bile pigment normally turns stool brown; rapid transit can leave it yellow-green before intestinal bacteria fully alter it.
- Greasy, floating stool that is difficult to flush suggests excess fat and should prompt review for pancreatic, bile, or small-intestinal malabsorption.
- Pale clay stool plus dark urine can indicate reduced bile reaching the intestine and needs same-day clinical assessment.
- Yellow diarrhea with fever, dehydration, travel exposure, or symptoms lasting more than 7 days may need stool testing.
- د جگر ازموینې such as ALP, GGT, bilirubin, ALT, and AST help distinguish bile-flow patterns from many intestinal causes.
- ناڅاپي (بې ارادې) د وزن کمېدل of 5% or more over 6-12 months alongside persistent stool change warrants medical review.
- Children and older adults can become dehydrated quickly; reduced urination, lethargy, or inability to keep fluids down needs urgent care.
What yellow stool usually means in adults
Yellow stool most often means food moved through the gut too quickly for bile pigments to become fully brown, or that a recent food, supplement, or diarrheal illness changed its appearance. One isolated yellow bowel movement without pain, fever, jaundice, or weight loss is rarely an emergency.
Bile starts as a yellow-green fluid, and intestinal bacteria convert bilirubin-derived pigments into stercobilin, the main brown stool pigment. When transit is fast, particularly with Bristol type 6 or 7 stool, that conversion is incomplete and the result may look mustard yellow, yellow-green, or tan. The د Bristol غایطه چارټ is more useful than colour alone because consistency tells us whether speed is driving the change.
In my clinical experience, lighting causes needless alarm surprisingly often: cool LED bathroom lighting makes a normal light-brown stool appear yellow. Dr. Thomas Klein recommends checking the next one or two bowel movements in daylight before changing a diet or ordering tests, provided there are no warning symptoms. A colour change that lasts fewer than 72 hours and follows a clear dietary trigger is usually observed, not treated.
کانټیسټي یو دی د AI د وینې معاینې شنونکی that puts bilirubin, alkaline phosphatase, GGT, ALT, AST, albumin, and inflammatory markers into one follow-up context. Those tests do not diagnose stool colour by themselves, but a normal liver pattern makes clinically significant obstruction much less likely than it would be with yellow stool plus jaundice.
Colour is a clue, not a diagnosis
A toilet bowl can dilute and reflect colour, so clinicians ask about texture, frequency, oiliness, odour, pain, medication timing, recent antibiotics, and travel. A photograph can help a clinician compare a recurring pattern, but it should never delay urgent assessment for pale stool with dark urine or severe abdominal pain.
Food, supplements and medicines that can cause yellow stool
Turmeric, high-carotenoid foods, food dyes, and a sudden increase in dietary fat can produce yellow or orange-yellow stool without disease. The practical test is whether the colour settles after the exposure stops and stool consistency returns to baseline.
Turmeric or curcumin supplements may colour stool bright yellow at doses of 500-2,000 mg daily, while carrots, squash, sweet potato, and yellow food colourings can shift colour toward orange-yellow. These pigments are not the same as jaundice; they do not usually cause pale stool, itching, dark urine, or a rise in direct bilirubin. Review supplement labels, especially powders and gummies with several colour additives.
A fatty restaurant meal can produce a loose, lighter stool the following morning simply by triggering stronger gastrocolic motility. That is different from recurrent steatorrhoea, which tends to look bulky, greasy, pale-yellow, float repeatedly, and leave an oily film. Our guide to undigested food in stool explains why visible vegetable fragments alone are usually not evidence of malabsorption.
Some medicines also matter: orlistat commonly causes oily yellow-orange leakage because it blocks fat absorption, while magnesium-containing antacids and metformin may speed transit. Bismuth more often darkens stool, not yellows it. Do not stop a prescribed medicine abruptly; ask a pharmacist or prescriber whether the timing and dose fit the change.
Why fast transit causes yellow diarrhea
Yellow diarrhea occurs when stool crosses the intestine rapidly, leaving too little time to reabsorb water and metabolize bile pigments. Viral gastroenteritis, anxiety-related bowel acceleration, food intolerance, and some medicines are common triggers.
A person with abrupt watery diarrhea who is otherwise well often has a self-limited viral illness; yellow colour in that setting is usually a transit marker rather than excess bile production. Adults should aim for frequent oral rehydration, roughly 200-250 mL after each loose stool, adjusted for heart or kidney restrictions. Reduced urination for 8 hours, dizziness on standing, or confusion signals clinically meaningful dehydration.
Bile acids reaching the colon can stimulate water secretion and urgency, creating yellow-green loose stools. Bile acid diarrhea is especially worth considering after gallbladder removal, ileal disease, or ileal surgery, although symptoms overlap heavily with irritable bowel syndrome. The AGA guideline advises targeted testing for bile acid diarrhea in chronic watery diarrhea rather than assuming it is functional bowel disease (Smalley et al., 2019).
If loose yellow stool follows fasting, a large coffee, or a high-fructose drink, tracking the trigger for 2 weeks can be more revealing than a random single stool test. For a more detailed distinction between short-term and persistent symptoms, read our د هاضمي نښو لارښود. Blood in stool, nocturnal diarrhea, or symptoms persisting beyond 4 weeks move this out of the self-care category.
How bile in stool changes colour from yellow to brown
Bile in stool is normal; reduced delivery of bile or unusually rapid movement through the bowel changes its expected brown colour. Yellow-green stool usually reflects pigment that has not been fully processed, whereas putty-coloured or grey-white stool raises concern for too little bile entering the gut.
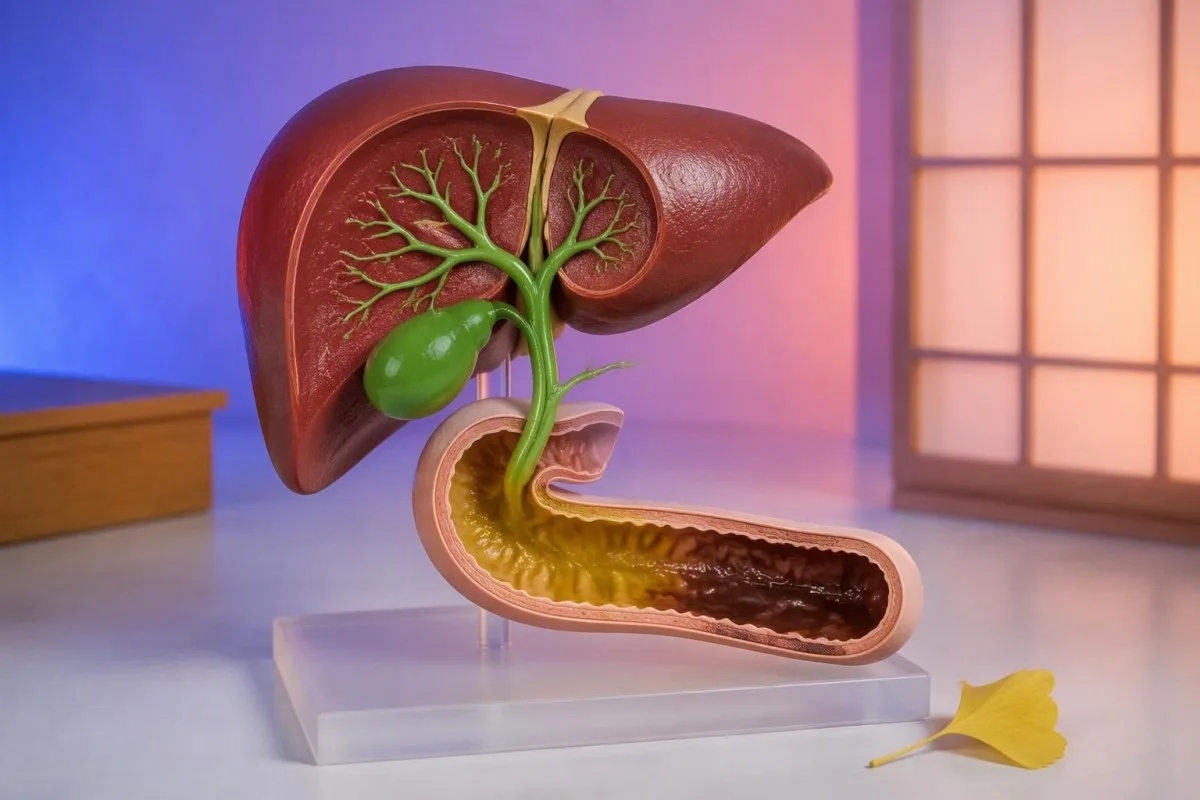
The liver makes about 500-1,000 mL of bile daily, and the gallbladder concentrates and releases it after meals. Bilirubin enters bile after red-cell pigment is processed by the liver, then intestinal microbes convert it through urobilinogen-related compounds into brown stercobilin. This is why a true blockage often produces both pale stool and dark tea-coloured urine: conjugated bilirubin is redirected into urine.
A yellow stool is not automatically “too much bile.” That phrase gets repeated online, but clinicians usually mean rapid transit, bile acid-related diarrhea, or impaired fat digestion when they investigate. The combination of a pale stool, generalized itching, yellow eyes, and dark urine is more informative than stool colour by itself; see our overview of لوړ مستقیم بilirوبین.
Kantesti AI interprets liver-panel results as a pattern, not as isolated red flags. A raised ALP and GGT with direct bilirubin elevation is more compatible with cholestasis than an isolated mild ALT rise, while completely normal bilirubin and ALP make a major bile-duct blockage less likely. Reference intervals still vary by laboratory, so the report’s own range remains the starting point.
When yellow stool suggests a gallbladder, liver or bile-duct problem
Yellow stool becomes more concerning when it is pale or clay-like and occurs with dark urine, jaundice, fever, itch, or right-upper abdominal pain. These features can indicate cholestasis, hepatitis, gallstone-related obstruction, or less commonly pancreatic obstruction.
Obstructive patterns are most urgent when pain is severe or fever develops. A stone obstructing the common bile duct may cause episodic upper abdominal pain, nausea, jaundice, and rising bilirubin; fever with jaundice and abdominal pain can indicate ascending cholangitis and needs emergency assessment. The cholecystitis blood test guide explains why normal early blood work cannot safely exclude a biliary problem when symptoms fit.
For adults, ALP above the laboratory upper limit plus elevated GGT supports a hepatobiliary source of ALP, although neither test locates a blockage. Total bilirubin above approximately 34 µmol/L (2 mg/dL) can make yellowing of the eye whites visible, but visible jaundice may appear earlier or later depending on skin tone and lighting. Ultrasound is often the first imaging test when obstruction is suspected.
کانټیسټي یو دی AI د وینې ازموینې تشریح پلیټفارم used to identify liver-test combinations that merit clinical follow-up rather than to replace an examination or scan. As of September 30, 2026, our clinical rule remains straightforward: pale stool with dark urine should be assessed the same day, even if pain has eased. Early obstruction can fluctuate, which is the annoying part.
Greasy yellow stool and malabsorption patterns
Repeated greasy, floating, foul-smelling yellow stool can indicate fat malabsorption, also called steatorrhoea. Pancreatic enzyme deficiency, coeliac disease, bile-flow disorders, and small-bowel disease are leading explanations when this pattern persists.
Steatorrhoea is not just a stool that floats once; it is usually recurrent, bulky, difficult to flush, and may leave an oily ring. People can lose weight despite eating normally because unabsorbed fat carries calories away, and long-standing malabsorption may lower fat-soluble vitamins A, D, E, and K. A qualitative stool-fat screen can help, but a timed 72-hour fecal-fat collection remains a reference method in selected cases.
Pancreatic exocrine insufficiency becomes more plausible with upper abdominal symptoms, diabetes, chronic pancreatitis risk factors, or low fecal elastase. A fecal elastase value below 200 µg/g supports pancreatic insufficiency, while values below 100 µg/g are more strongly suggestive; watery samples can falsely lower the measurement by dilution. Our stool elastase explanation covers this often-missed pre-analytic trap.
Coeliac disease may cause loose pale-yellow stools, iron deficiency, folate deficiency, abdominal bloating, fatigue, or no obvious gastrointestinal symptoms at all. The 2023 ACG guideline recommends tissue transglutaminase IgA testing with total IgA while the person is eating gluten, because starting a gluten-free diet before testing can produce a falsely reassuring result (Rubio-Tapia et al., 2023).
Infection, parasites and travel-related yellow stool
Acute yellow diarrhea with cramps is often infectious, while persistent greasy diarrhea after untreated water exposure raises suspicion for Giardia and other parasites. Most short illnesses resolve, but duration, fever, travel history, and immune status determine whether testing is sensible.
Giardia often produces bloating, sulfurous belching, fatigue, and pale or greasy loose stools 1-2 weeks after exposure, though timing varies. Risk rises after drinking untreated surface water, daycare exposure, or close household contact; a multiplex stool PCR or antigen test can detect infection without relying on a single microscopy sample. Persistent symptoms deserve a test rather than repeated empiric antibiotics.
Invasive bacterial illness is more likely when diarrhea contains blood, fever exceeds 38.5°C, or there is significant abdominal tenderness. The ACG guideline on acute diarrheal infections recommends stool testing when symptoms are severe, prolonged, dysenteric, or linked to outbreak and travel circumstances (Riddle et al., 2016). Antibiotics can occasionally worsen particular infections, so the diagnosis matters.
Children with yellow watery stools need a lower threshold for assessment because dehydration can develop over hours rather than days. Track wet nappies or urine output, tears, alertness, and drinking—not merely bowel-movement count. Our د غایطه کلتور لارښود explains why a positive organism is interpreted alongside symptoms, not treated automatically.
Tests clinicians use for persistent yellow stool
Persistent yellow stool is assessed with history first, then targeted liver tests, coeliac blood tests, stool studies, and imaging when the pattern points toward bile, infection, or malabsorption. There is no single “yellow stool blood test.”
A useful first blood panel often includes full blood count, electrolytes, CRP, ALT, AST, ALP, GGT, bilirubin, albumin, and coeliac serology. Low albumin below 35 g/L can occur with significant intestinal protein loss, liver synthetic dysfunction, or inflammation, but it is not specific to malabsorption. If diarrhea is prolonged, potassium and bicarbonate are clinically relevant because bowel losses can disturb both.
Stool testing should answer a question: PCR or culture for an infectious syndrome, fecal calprotectin or lactoferrin for suspected intestinal inflammation, fecal elastase for possible pancreatic insufficiency, and fecal fat when steatorrhoea is convincing. Calprotectin is best viewed as an inflammation signal rather than a diagnosis; our comparison of calprotectin and lactoferrin explains the trade-offs.
کانټیسټي یو دی د AI پر بنسټ د وینې ازموینې تحلیل وسیله that can organize relevant blood-test trends, including bilirubin and ALP changes over time, in about 60 seconds after a report upload. A normal blood panel cannot rule out Giardia, bile acid diarrhea, or mild coeliac disease, so our output should support a clinician-led next step rather than falsely close the investigation.
Reading liver tests alongside stool colour
A cholestatic liver-test pattern usually means ALP and GGT rise more prominently than ALT and AST, often with direct bilirubin elevation. Stool colour adds useful context, but blood results and symptoms determine urgency.
ALT and AST reflect hepatocyte injury more than bile flow, while ALP can arise from liver or bone. GGT helps clinicians decide whether a raised ALP is likely hepatobiliary, though alcohol, metabolic liver disease, and certain medicines can raise GGT without obstruction. A GGT of 90 IU/L with normal bilirubin means something very different from GGT 90 IU/L plus jaundice and pale stool.
The R-ratio can assist specialists: divide ALT as a multiple of its upper limit by ALP as a multiple of its upper limit. A ratio above 5 suggests a hepatocellular pattern, below 2 suggests cholestatic injury, and 2-5 is mixed; it is a triage tool, not a diagnosis. Patients can explore the component tests in our د کولیسټاسیس د وینې ازموینې لارښود.
Dr. Thomas Klein has seen people worry about a marginally high ALP that later proves to be bone-related, particularly during fracture healing or vitamin D deficiency. That is why clinicians may add ALP isoenzymes, vitamin D, calcium, phosphate, or imaging rather than assuming a liver diagnosis. The stool story can make that distinction more or less urgent.
Yellow diarrhea after gallbladder removal
Diarrhea after gallbladder removal can occur because bile flows continuously into the intestine rather than being released in concentrated pulses with meals. It often begins soon after surgery, is worse after fatty meals, and can be yellow-green because transit is accelerated.
Not everyone develops post-cholecystectomy diarrhea, and it is not automatically lifelong. Smaller lower-fat meals for 2-4 weeks can reduce urgency while the bowel adapts, but severe restriction is rarely necessary long term. Persistent watery stools more than 4 weeks after surgery should prompt discussion of bile acid diarrhea and other causes, especially if symptoms wake a person at night.
Where available, SeHCAT retention testing can support bile acid malabsorption; alternatives include serum 7α-hydroxy-4-cholesten-3-one or carefully monitored treatment trials. Bile-acid sequestrants may help but can interfere with absorption of thyroid medication, warfarin, and fat-soluble vitamins, so dose spacing is not a minor detail. A pharmacist can provide the exact schedule.
This pattern differs from a new episode of severe pain, fever, jaundice, or pale stool after surgery, which needs urgent assessment for a retained stone or another complication. Our overview of the د صفرا اسیدونو د وینې ازموینه also explains why generalized itching shifts attention back toward cholestasis rather than simple rapid transit.
Yellow stool in children, pregnancy and older adults
Yellow stools are common in breastfed infants and are usually normal, while persistent pale stools in any child require prompt paediatric evaluation. Pregnancy and older age also change the threshold for acting because dehydration and bile disorders carry different risks.
Breastfed infant stool is frequently mustard-yellow, loose, and seedy; that is expected when an infant is feeding and growing normally. Acholic stool, meaning distinctly white, grey, or putty coloured, is different and should be assessed urgently because biliary atresia and other neonatal cholestatic conditions are time-sensitive. Parents are right to trust a repeated colour pattern rather than one diaper under odd lighting.
During pregnancy, new pale stool, dark urine, itching of the palms or soles, or jaundice should lead to same-day maternity assessment. Serum bile acids can rise in intrahepatic cholestasis of pregnancy, but the test should be interpreted with liver results, gestational age, symptoms, and local obstetric guidance. The itching blood-test guide gives a practical testing framework.
In older adults, a new persistent stool change deserves attention sooner because medication effects, pancreatic disease, malignancy, and infection are more common, while thirst may be blunted. A loss of 5% body weight in 6-12 months is clinically significant at any age. Frailty, kidney disease, or diuretic use lowers the margin for dehydration.
What to do during the first 72 hours
For a single yellow stool or mild yellow diarrhea without red flags, hydration, a brief food-and-symptom record, and observation for 48-72 hours are reasonable. Avoid aggressive “cleanses,” fasting, or self-started antibiotics, which often muddy the clinical picture.
Write down the timing, Bristol stool type, meals, supplements, medicine changes, travel, fever, pain, urine colour, and number of bowel movements. This is more clinically useful than describing stool as “weird.” If you had a high-dose turmeric product, a fatty meal, or a stomach bug and symptoms settle within 3 days, no testing may be required.
Use oral rehydration solution rather than only plain water if diarrhea is frequent; standard solutions contain glucose and sodium in proportions that improve intestinal water absorption. Adults without fluid restrictions can use small repeated sips, especially after each loose stool. Avoid sports drinks as the sole replacement when diarrhea is substantial because their sodium content is often lower and sugar content higher.
If symptoms persist, our blood test for diarrhea guide can help you prepare questions for a clinician. Kantesti AI can also place liver and electrolyte results in chronological context, but an app cannot assess abdominal tenderness, hydration status, or jaundice through a screen. Those limitations matter.
When yellow stool needs medical review or urgent care
Seek urgent care for pale stool with dark urine or jaundice, severe or worsening abdominal pain, fever with jaundice, fainting, confusion, or signs of major dehydration. Arrange routine medical review for yellow stool lasting more than 1-2 weeks, recurring greasy stool, weight loss, or persistent diarrhea.
Emergency assessment is appropriate for inability to keep fluids down, black tarry stool, visible blood, severe weakness, a rigid abdomen, or jaundice with fever. These combinations carry more diagnostic weight than yellow colour alone because they may indicate bleeding, significant infection, obstruction, or systemic illness. If in doubt, err on the side of being seen—particularly for children, pregnancy, and immunosuppression.
A non-urgent appointment is still warranted if stool changes persist beyond 7 days with diarrhea or beyond 2 weeks without diarrhea, even when pain is absent. Bring medication and supplement containers, a 7-day symptom log, and prior laboratory reports. The article on blood in stool urgency helps distinguish red and black warning colours from benign food effects.
Kantesti's medical review standards are described by our د طبي مشورتي بورډ, ، او زموږ د کلینیکي تایید (validation) تګلاره explains where automated interpretation stops. Kantesti is an د AI لاب ټېسټ د تفسیر خدمت designed to surface follow-up patterns; it does not provide emergency triage or replace a clinician examining you.
Questions that make a yellow stool appointment more useful
The most useful appointment questions ask whether the stool pattern fits rapid transit, malabsorption, infection, or impaired bile flow and which test would change management. A focused history can prevent both under-testing and broad low-yield testing.
Ask: “Does my symptom pattern justify liver tests, coeliac testing, stool PCR, fecal calprotectin, fecal elastase, or ultrasound?” The answer should be tied to your duration, weight change, pain location, travel, surgery, and stool texture. A blanket panel is not always better; for example, stool PCR does not diagnose pancreatic enzyme deficiency, and liver tests do not rule out Giardia.
Ask for the actual results and the laboratory reference ranges, not simply “normal” or “abnormal.” A bilirubin trend from 9 to 28 µmol/L may be meaningful if it is paired with new dark urine, while an isolated stable bilirubin of 24 µmol/L can have a different explanation. Our د ځیګر پینل عمومي کتنه (liver panel overview) outlines what each component can and cannot tell you.
Kantesti AI was built by Kantesti Ltd to help people organize laboratory reports across visits, with privacy-focused handling and multilingual interpretation in 75+ languages. For the method behind that work, see our د AI ټکنالوژۍ لارښود. A good next step is specific: test, monitor, image, treat, or safely observe—not merely “repeat everything.”
Bottom line: match the colour to the whole pattern
Most yellow stool causes are temporary dietary or fast-transit effects, but pale stool, greasy recurrence, dark urine, jaundice, fever, pain, or weight loss need medical evaluation. The combination of colour, texture, duration, and associated symptoms is far more reliable than colour alone.
A brief yellow stool after turmeric, a rich meal, or a 24-hour diarrheal illness can usually be watched for 48-72 hours. Repeated oily floating stool points toward fat malabsorption, while clay-coloured stool with dark urine points toward reduced bile flow. That distinction is clinically useful because the investigations—and the urgency—are different.
Keep the evidence in proportion. Most patients I see with a short-lived colour change do not have serious liver or pancreatic disease, yet a small number have warning combinations that should not be dismissed as “just diet.” The fecal fat test guide is a sensible next read when oiliness and floating are the recurring features.
کانټیسټي یو دی د AI بایومارکر تفسیر پلیټفارم that helps connect laboratory patterns to informed questions for your clinician. It is not a substitute for care when red flags are present; severe pain, jaundice, fever, dehydration, or pale stool with dark urine should always be assessed in person.
پوښتل شوې پوښتنې
په لویانو کې د ژیړ ملا معنی څه ده؟
په لویانو کې ژیړ پاخه معمولا د کولمو چټک لیږد، د رژیم یو وروستي رنګ، لوړ غوړ خواړه، یا لنډمهاله اسهال ناروغي منعکس کوي. که نرم یا اوبه وي او د درد، تبه، تیاره پیشاب، ژیړی، یا وزن له لاسه ورکولو پرته په 48-72 ساعتونو کې سم شي، دا معمولا اضطراري نه ده. تکراري غوړ، تیرېدونکي، پاکولو کې سخت ژیړ پاخه د غوړ جذب نه کیدل ښیې او باید وکتل شي. تیاره خړ یا خټکي پاخه د تیاره پیشاب سره په ورځني کلینیکي ارزونې ته اړتیا لري ځکه چې د صفرا جریان کم کیدی شي.
ایا صفرا کولی شي د ژیړ نس ناستی لامل شي؟
Bile can contribute to yellow-green stool when intestinal transit is fast because its pigments have not been fully transformed into brown stercobilin. Normal bile production is about 500-1,000 mL daily, and bile itself is not a sign of disease when it reaches the bowel normally. The concern is not simply “too much bile”; it is persistent watery diarrhea from bile acids or too little bile reaching the intestine, which can produce pale stool. Dark urine, itch, jaundice, or a raised direct bilirubin level make a bile-flow problem more likely.
کله باید د ژیړ نس ناستې په اړه اندېښنه وکړم؟
ژیړ اسهال کله چې له ۷ ورځو څخه زیات دوام وکړي، وچوالی رامنځته کړي، وروسته له لوړ خطر سفر یا ناپاکو اوبو سره له تماس څخه راشي، یا له ۳۸.۵ درجې سانتي ګراد څخه لوړې تبه، وینې، شدید درد، یا وزن له لاسه ورکولو سره یوځای شي، نو سمدستي طبي مشورې ته اړتیا لري. لویان چې له ۸ ساعتونو راهیسې کم ادرار کوي، شدید سردرد، ګډوډي، یا د مایعاتو ساتلو ناتواني لري باید عاجل ارزونه ترلاسه کړي. په ماشومانو کې، ستړیا، ضعیف څښل، اوښکې نه شتون، یا کم لوند نیپي د جدي خبرتیا نښې دي. د ستونې PCR، کلتور، یا پاراسایټ ازموینه کیدای شي د تماس او نښو د نمونې سره سم مناسبه وي.
Does yellow stool mean pancreatic cancer?
Yellow stool by itself does not mean pancreatic cancer and is far more often caused by diet, rapid transit, or a short gastrointestinal illness. Clinicians investigate pancreatic disease when pale or greasy stools recur with unexplained weight loss, persistent upper abdominal or back pain, new diabetes, jaundice, or low fecal elastase below 200 µg/g. These symptoms have many non-cancer explanations, including pancreatic enzyme insufficiency and bile obstruction. Persistent warning patterns should be assessed rather than self-diagnosed from stool colour.
Can anxiety cause yellow stool?
Anxiety can contribute to yellow stool indirectly by accelerating bowel transit through gut-brain signaling, particularly in people with irritable bowel syndrome. Faster transit can leave stool loose, yellow-green, and urgent because bile pigment has less time to become brown. Anxiety should not be assumed to be the cause if symptoms are new after age 50, wake someone from sleep, involve blood, fever, weight loss, pale stool, or abnormal liver tests. A symptom diary over 2 weeks often clarifies whether stress timing truly correlates with bowel changes.
What tests are useful for persistent yellow stool?
Persistent yellow stool is usually evaluated with liver tests including bilirubin, ALP, GGT, ALT, AST, and albumin, plus targeted stool or coeliac testing based on the symptom pattern. Fecal elastase below 200 µg/g supports possible pancreatic enzyme insufficiency, while fecal calprotectin can help identify intestinal inflammation. Stool PCR or antigen testing is useful for diarrhea after travel, water exposure, or prolonged symptoms. Ultrasound is commonly used when pale stool, dark urine, jaundice, or upper abdominal pain raises concern about gallstones or bile obstruction.
همدا نن د AI په مرسته د وینې ازموینې تحلیل ترلاسه کړئ
له 2M+ څخه زیات کاروونکي په ټوله نړۍ کې زموږ په Kantesti باور لري چې د لابراتوار ازموینو تحلیل په فوري او دقیق ډول کوي. خپل د وینې ازموینې پایلې اپلوډ کړئ او په ثانیو کې د 15,000+ بایومارکرونو بشپړه تشریح ترلاسه کړئ.
📚 د څېړنې خپرونې چې حواله شوې دي
کلین، ټي، مېچېل، ایس، او وېبر، ایچ. (2026). Kantesti LTD. (2026). Women's Health Guide: Ovulation, Menopause & Hormonal Symptoms. Figshare. DOI: 10.6084/m9.figshare.31830721. Kantesti د AI طبي څېړنه.
کلین، ټي، مېچېل، ایس، او وېبر، ایچ. (2026). Kantesti LTD. (2026). Multilingual AI Assisted Clinical Decision Support for Early Hantavirus Triage: Design, Engineering Validation, and Real-World Deployment Across 50,000 Interpreted Blood Test Reports. Figshare. DOI: 10.6084/m9.figshare.32230290. Kantesti د AI طبي څېړنه.
📖 بهرني طبي مراجع
سماللي ډبلیو او نور (2019). د AGA کلینیکي عمل لارښوونې د فعالې نس ناستې او د نس ناستې - غالب خارښ لرونکي کولمو سنډروم په لور د لوربواریټري ارزونې په اړه په لویانو کې. Gastroenterology.
Rubio-Tapia A et al. (2023). . د کلینیکي معافیت (Immunology) ژورنال.. د امریکایي ګیسټروانټرولوژي ژورنال.
Riddle MS et al. (2016). ACG کلینیکي لارښود: د حاد اسهالي انتاناتو تشخیص، درملنه، او مخنیوی په لویانو کې. د امریکایي ګیسټروانټرولوژي ژورنال.
⚕️ طبي ردونه
دا مقاله یوازې د زده کړې لپاره ده او طبي مشوره نه جوړوي. د تشخیص او درملنې د پرېکړو لپاره تل د وړ روغتیايي خدمت وړاندې کوونکي سره سلا وکړئ.
د E-E-A-T باور نښې
تجربه
د ډاکټر تر مشرۍ لاندې کلینیکي بیاکتنه د لابراتواري تفسیر د کاري بهیرونو لپاره.
تخصص
د لابراتواري طب تمرکز پر دې چې بایومارکرونه په کلینیکي شرایطو کې څنګه چلند کوي.
واک ورکول
د ډاکټر توماس کلاین له خوا لیکل شوی، د ډاکټر سارا میچل او پروف. ډاکټر هانس ویبر له خوا بیاکتنه.
اعتبار
د شواهدو پر بنسټ تفسیر د روښانه تعقیبي لارو چارو سره، تر څو اندیښنه کمه شي.