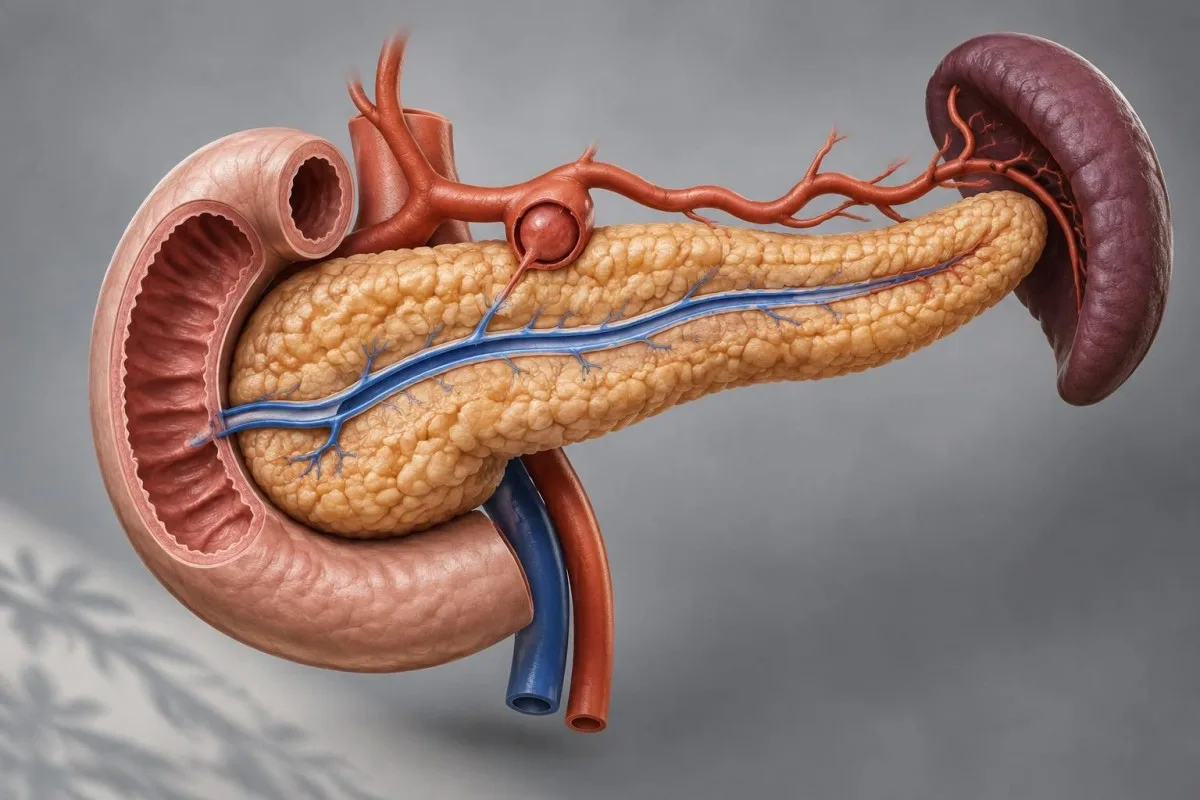
Bleeding through the pancreatic duct can be difficult to locate, especially when it stops and starts. Learn which symptoms need emergency care and how specialists investigate the source.

ძირითადი დასკვნები
- განმარტება: Hemosuccus pancreaticus is gastrointestinal bleeding that enters the pancreatic duct and flows into the small intestine.
- Emergency signs: Vomiting blood, black tarry stool, fainting, or severe weakness can signal a dangerous bleed; seek emergency care immediately.
- Intermittent bleeding: A first endoscopy can miss the source if bleeding has stopped or the duct opening is not clearly seen.
- Common setting: Pancreatitis and a nearby arterial pseudoaneurysm are recognized causes, but not everyone has a known pancreatic condition.
- გამოსახულება: CT angiography can identify an abnormal artery or active bleeding; a negative scan does not always exclude an intermittent bleed.
- Specialist treatment: Catheter angiography can both locate an arterial source and allow embolization to stop it.
- Blood tests: Hemoglobin helps assess anemia, but an early result can be normal and cannot identify the bleeding site.
- Stool tests: A positive or negative stool blood test cannot establish whether blood came from the pancreatic duct.
What happens in hemosuccus pancreaticus?
Hemosuccus pancreaticus occurs when blood enters the pancreatic duct and passes through its opening into the duodenum, the first part of the small intestine. It is a rare cause of gastrointestinal bleeding.
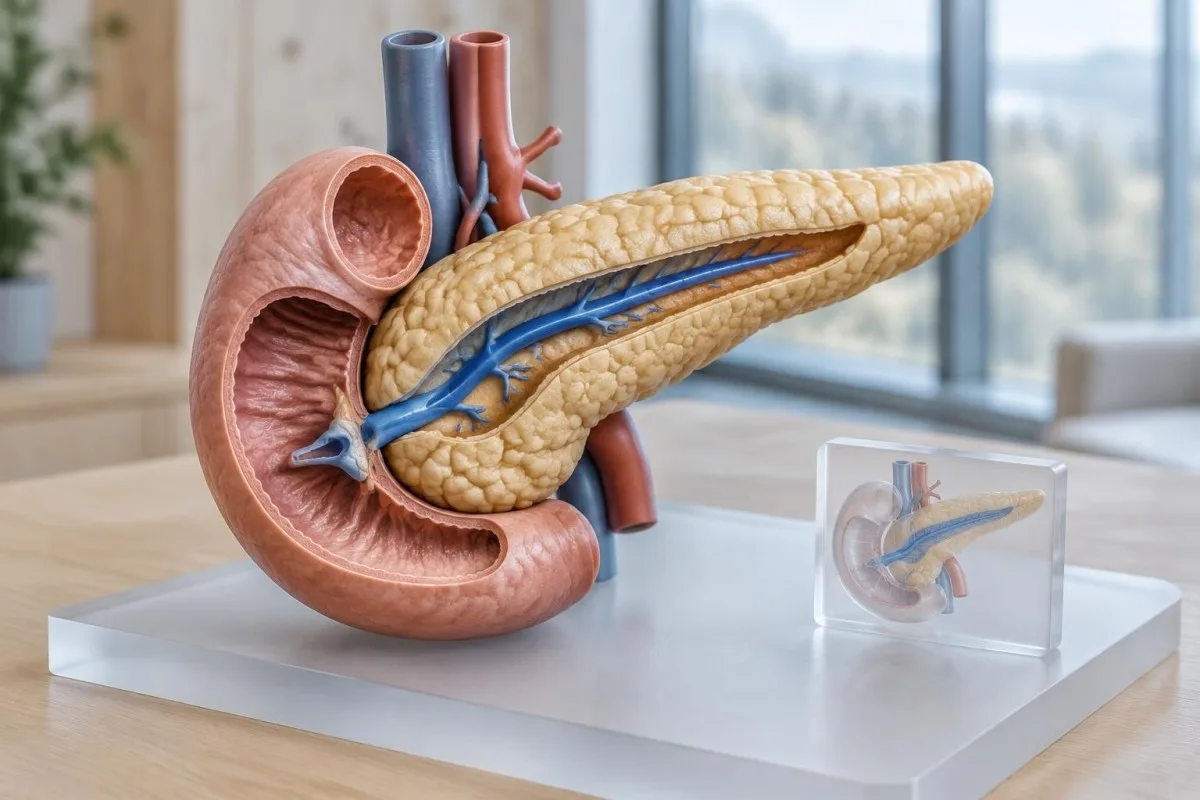
The pancreas sits behind the stomach and makes digestive enzymes. Its main duct normally carries these enzymes to the duodenum through an opening called the major papilla.
A damaged artery near the pancreas can connect with the duct, sometimes through a pancreatic fluid collection. Blood then follows the duct into the digestive tract rather than appearing at an obvious ulcer on the stomach lining.
სხვა მიზეზები განავალში სისხლი are much more common. Symptoms alone cannot establish that the pancreas is the source.
What are the symptoms of hemosuccus pancreaticus?
Hemosuccus pancreaticus symptoms can include black tarry stools, upper abdominal pain, weakness, dizziness, or vomiting blood. Some people have recurrent episodes separated by symptom-free intervals.
Black, sticky stool with a strong odor is called მელენა and can occur when blood is digested as it travels through the gut. Iron tablets and some medicines can also darken stool, but a new tarry stool needs urgent assessment.
Abdominal pain may accompany bleeding, although not every patient has pain. A clot within the pancreatic duct may obstruct drainage and contribute to discomfort, but pain alone does not establish the diagnosis.
Heavy gastrointestinal bleeding can occasionally cause bright red or maroon stool rather than black stool. For comparison, other digestive symptoms have different possible causes and do not identify a pancreatic source.
Which symptoms require emergency care?
Vomiting blood or material resembling coffee grounds, passing black tarry stool, fainting, or experiencing severe weakness with suspected bleeding requires immediate emergency evaluation. Call emergency services if the person is collapsing, confused, short of breath, or unable to travel safely.
Do not drive yourself if you feel faint, and do not wait for a stool test or an AI interpretation. A bleed that seems to stop can restart and become life-threatening.
Tell the emergency team about previous pancreatitis, pancreatic fluid collections, procedures, and any blood-thinning medicines. Bring a medication list if it is immediately available, but do not delay getting help to find it.
Fresh rectal bleeding also needs prompt medical assessment; a large amount, dizziness, fainting, or severe abdominal pain makes it an emergency. Our guide to განავალში სისხლი explains why a positive screening result still needs a clinician-led investigation.
What causes bleeding from the pancreatic duct?
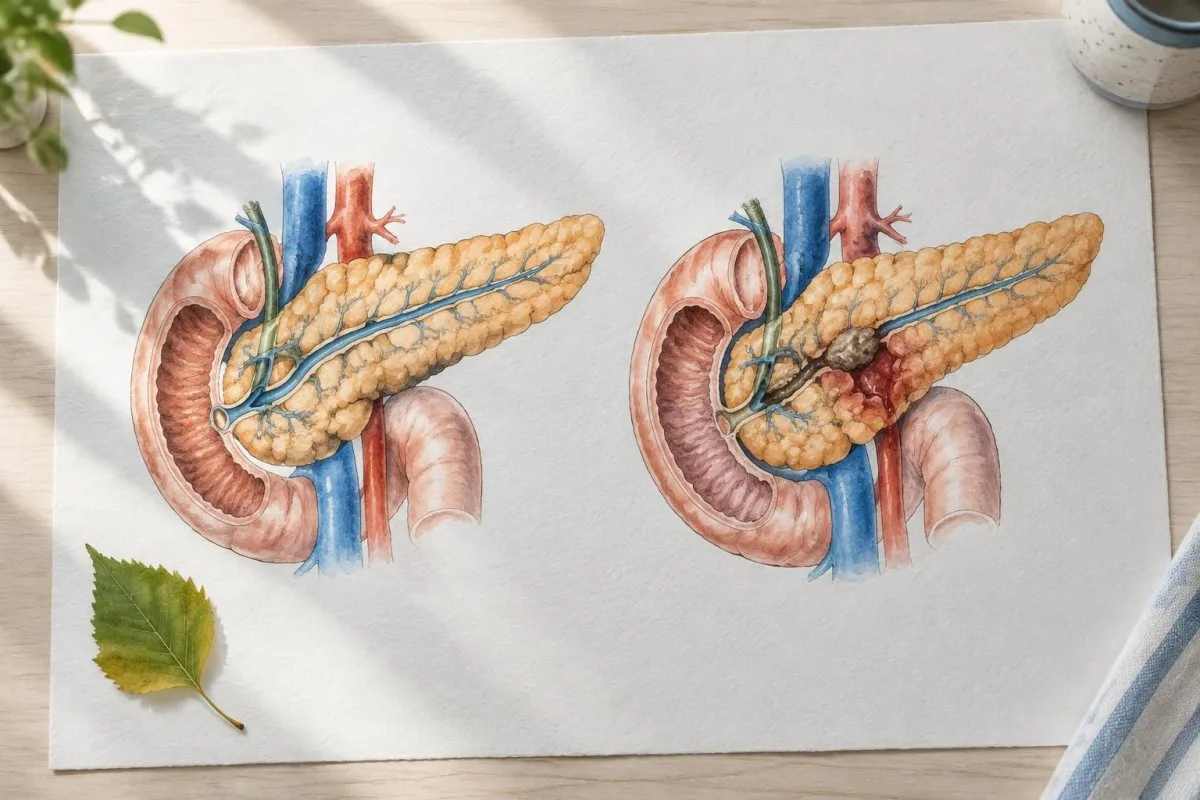
Bleeding from the pancreatic duct often results from an arterial pseudoaneurysm associated with pancreatitis or a pancreatic fluid collection. Less common causes include trauma, pancreatic tumors, and complications of procedures.
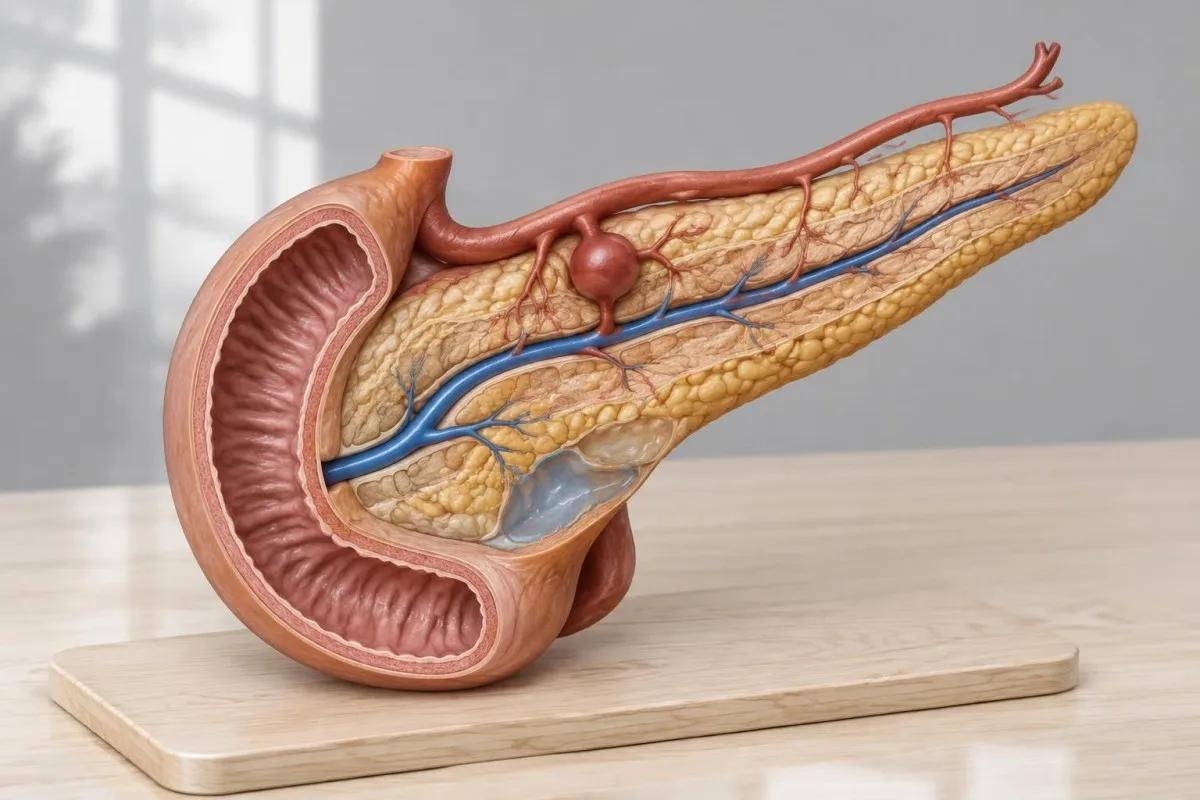
A pseudoaneurysm is a contained leak from an artery, not simply a widened artery with all its usual wall layers intact. Pancreatic inflammation and enzymes can weaken a nearby vessel, allowing a fragile blood-filled cavity to form.
The splenic artery is a recognized source because it runs close to the pancreas, although other nearby arteries can be involved. The precise vessel matters because an interventional radiologist plans treatment around its anatomy.
A review by Tarar and colleagues describes pancreatitis, pseudoaneurysms, and pseudocysts among the clinical settings associated with this condition (Tarar et al., 2022). In a separate diagnostic context, an IgG4 result cannot by itself establish pancreatic disease or a bleeding source.
Why can bleeding stop and restart?
Hemosuccus pancreaticus can be intermittent because clots or temporary changes in flow may interrupt the passage of blood into the pancreatic duct. Symptoms can settle even though the underlying vessel remains at risk.
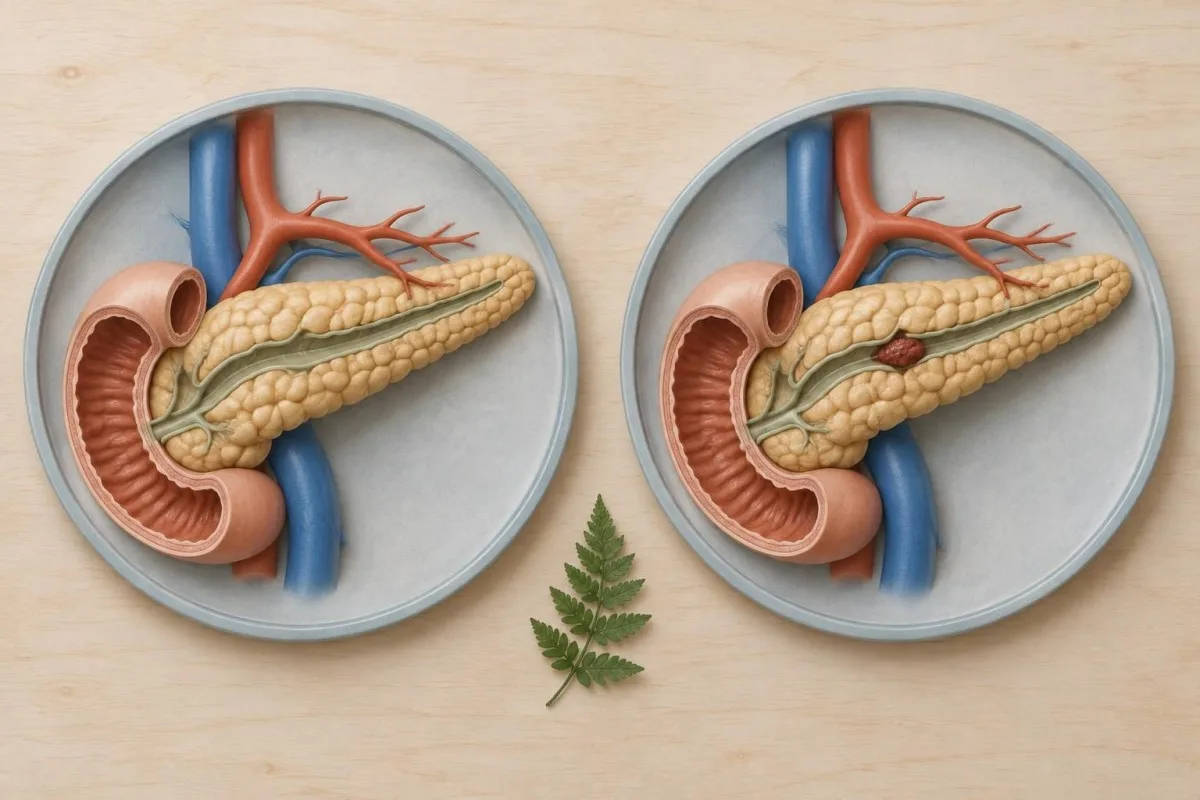
An examination performed between episodes may show no active blood at the papilla. That makes the timing of symptoms useful clinical information, not a reason to wait for another episode before seeking care.
For a hypothetical example, a person with prior pancreatitis has black stools on Monday and a normal-looking initial endoscopy on Tuesday. If symptoms recur, the team may reassess the pancreatic vessels rather than assume the first examination excluded every source.
A record of when stool changed, whether pain accompanied it, and any prior imaging can help clinicians compare events with investigations. Avoid self-testing during a suspected emergency; stool blood testing has a different purpose.
Why can an initial endoscopy miss the source?
An initial upper endoscopy can miss hemosuccus pancreaticus if bleeding is not active or the major papilla is difficult to inspect. A normal-looking stomach and duodenum therefore do not rule out a pancreatic duct source.

A standard upper endoscope examines the esophagus, stomach, and duodenum. It is valuable because ulcers and other more common upper gastrointestinal sources may be visible and treatable during the same procedure.
The papilla sits on the wall of the duodenum and may not be well seen with a forward-viewing scope. A side-viewing endoscope can provide a better view when specialists consider it appropriate, but it still may miss bleeding that has stopped.
Seeing blood emerge from the papilla can provide a strong clue, although clinicians must also consider blood coming from the bile duct. Other gastrointestinal diagnoses can likewise require a specific technique, as explained in our article on endoscopy and biopsy.
How does CT angiography help diagnosis?
CT angiography, or CTA, uses contrast and timed CT images to examine blood vessels and may show a pseudoaneurysm or active contrast leakage. It can also reveal pancreatitis, a fluid collection, or blood within the pancreatic duct.
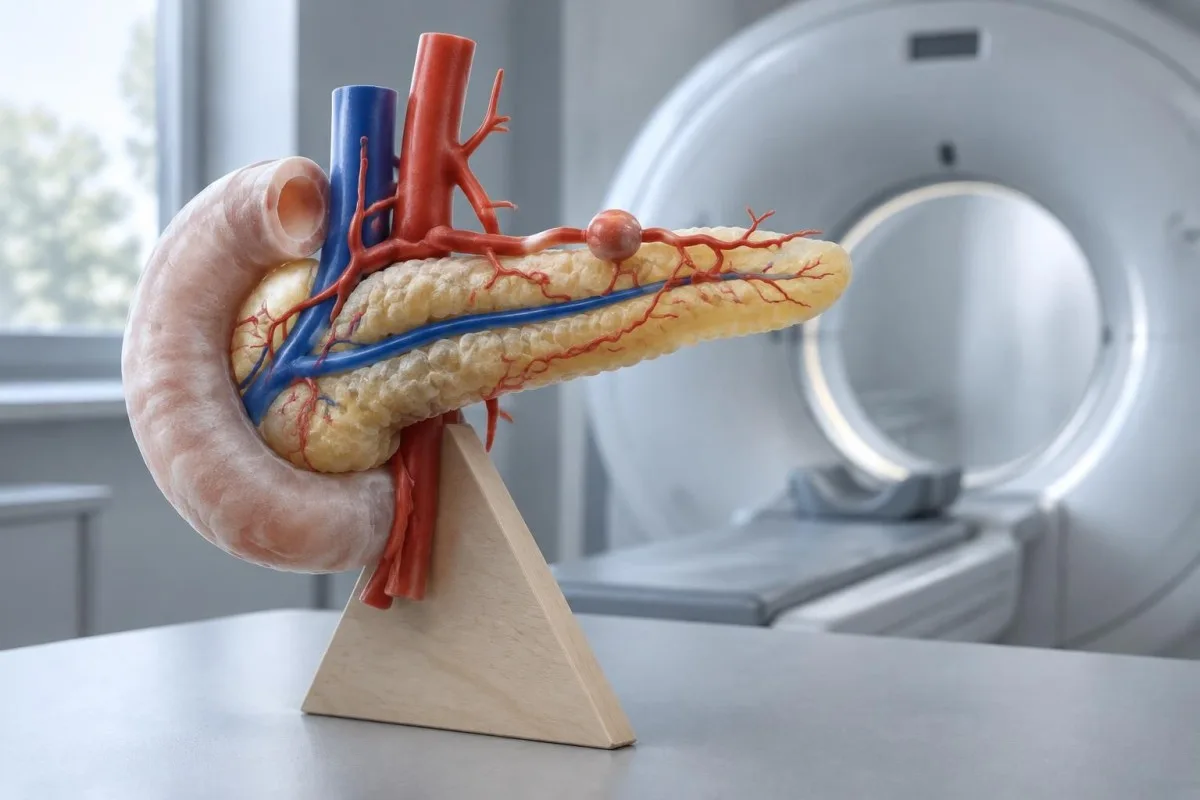
A multiphase study captures images at different times after contrast injection. The phases help a radiologist distinguish vessel anatomy from contrast that has escaped into nearby tissue or a duct.
A negative CTA does not exclude intermittent hemorrhage, particularly when there is no active flow at the time of imaging. A visible pseudoaneurysm may still be clinically significant even when active leakage is not seen.
The team considers contrast allergy and kidney function when choosing imaging, but potentially life-saving investigation should not be delayed without a clinical reason. BUN და კრეატინინი provide context about kidney function; neither test locates gastrointestinal bleeding.
What does catheter angiography add?
Catheter angiography maps arteries using contrast delivered through a small catheter and can identify a pancreatic arterial source. When an appropriate vessel is found, the same procedure can often treat it.
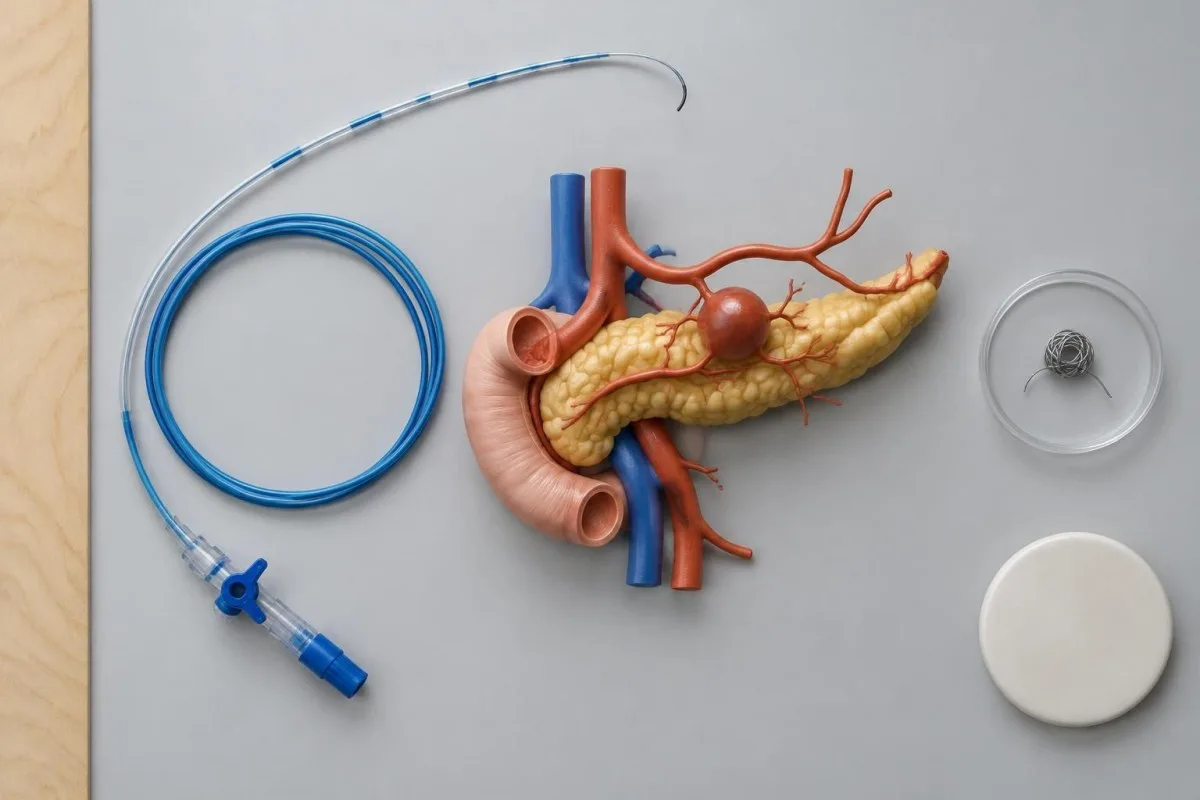
An interventional radiologist guides the catheter into selected arteries and takes images of the vessel network. The examination may reveal a pseudoaneurysm or active leakage, but intermittent bleeding can also make angiography negative.
A coil or another embolic material may be placed to block the responsible vessel. The choice depends on the artery, its branches, and the need to preserve circulation to nearby organs.
The team weighs procedure-related risks, including reduced blood supply to surrounding tissue, against the danger of continued bleeding. A crossmatch before transfusion may be needed as part of the broader emergency plan.
When are endoscopic ultrasound and ERCP used?
Endoscopic ultrasound and ERCP can provide additional information when the diagnosis remains uncertain, but neither replaces urgent stabilization or vascular imaging when a serious arterial bleed is suspected.
Endoscopic ultrasound places an ultrasound probe close to the pancreas from inside the digestive tract. Doppler imaging may help assess a nearby vessel or a pancreatic fluid collection, depending on the clinical question and local expertise.
ERCP, or endoscopic retrograde cholangiopancreatography, uses an endoscope and contrast to examine or treat selected pancreatic and bile duct problems. It is invasive and can cause pancreatitis or other complications, so specialists select it for a specific reason.
Finding a duct abnormality does not automatically prove it caused a bleed. Imaging findings and symptoms must be considered together, much as a pancreatic marker result requires clinical context.
Which blood tests help assess a suspected bleed?
A complete blood count, blood group and compatibility testing, kidney function tests, and clotting tests help clinicians assess and prepare for gastrointestinal bleeding. None can independently diagnose hemosuccus pancreaticus.
Hemoglobin measures the oxygen-carrying protein in red cells. After sudden blood loss, the first value may not yet show the eventual fall, so the team interprets repeat results alongside pulse, blood pressure, symptoms, and treatment.
In the American College of Gastroenterology guideline for hospitalized upper gastrointestinal bleeding, a hemoglobin threshold of 7 გ/დლ is suggested for transfusion in many patients (Laine et al., 2021). That is not a home-care cutoff: active bleeding, shock, heart disease, and other circumstances require individualized decisions.
კანტესტი არის AI სისხლის ტესტის ანალიზატორი that can help explain reported hemoglobin and other CBC values after urgent care has been arranged. It cannot assess circulation, replace repeat testing, or find a pancreatic vessel; see our explanation of hemoglobin and hematocrit.
Can a stool test identify pancreatic duct bleeding?
No routine stool test can identify the pancreatic duct as the source of bleeding. A fecal occult blood test or FIT may detect blood in some circumstances, but it cannot show where that blood originated.
FIT detects human hemoglobin and is mainly used in specific screening or assessment pathways for lower gastrointestinal bleeding. Blood from an upper source may be digested before it reaches the stool, so a negative FIT cannot safely rule out an upper gastrointestinal bleed.
A positive screening test needs follow-up for its own reasons; it does not prove pancreatic bleeding or cancer. Visible black tarry stool or vomiting blood warrants urgent clinical assessment rather than a home screening kit.
Stool inflammation tests answer a different question again. Our comparison of კალპროტექტინის და ლაქტოფერინის explains why markers of intestinal inflammation do not localize an arterial bleed.
How is hemosuccus pancreaticus treated?
Treatment combines resuscitation with a plan to control the bleeding source, often using catheter embolization when the anatomy allows. Surgery may be necessary if embolization fails, is unsuitable, or another pancreatic problem also needs an operation.
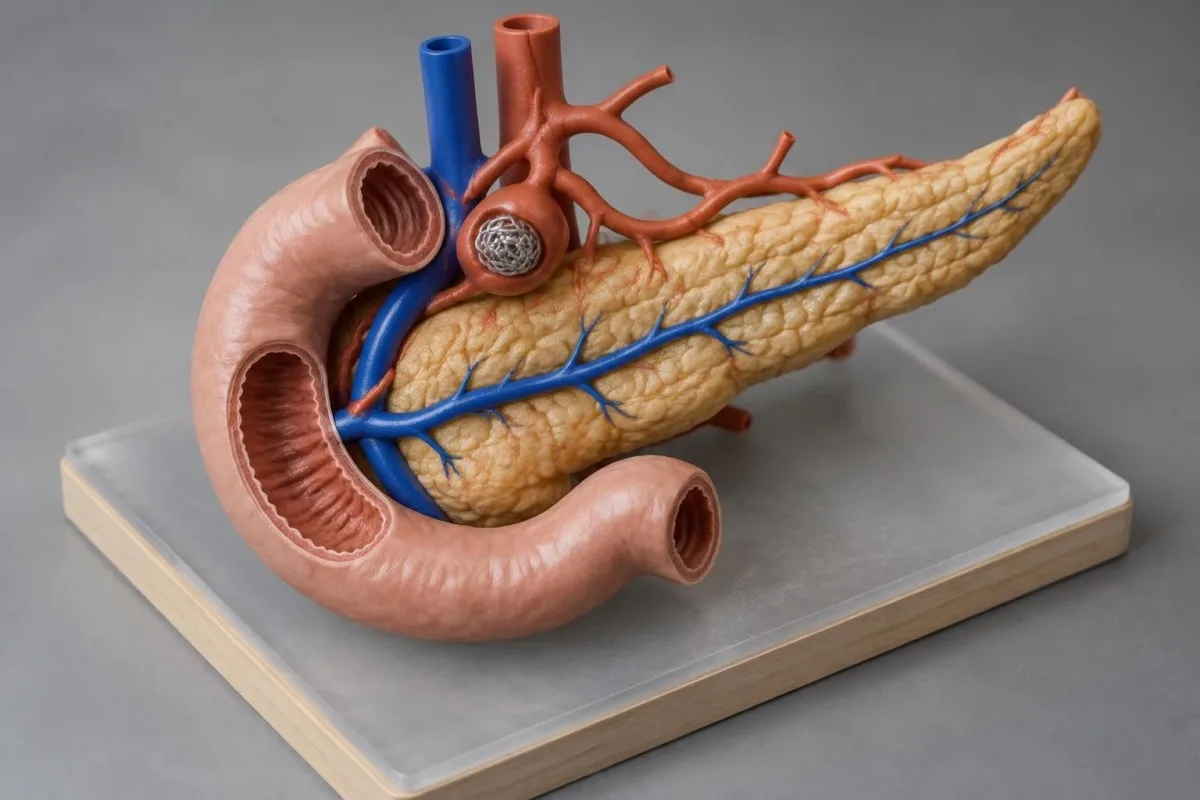
In hospital, clinicians monitor vital signs, establish intravenous access, and give fluids or blood products when needed. They also review anticoagulants and other medicines that can affect bleeding, balancing reversal against each person's clotting risk.
Embolization can stop flow through the affected artery without open surgery. Repeat imaging or another intervention may be needed if bleeding returns, because the initial procedure does not guarantee permanent control.
ნორმალური clotting panel does not rule out a damaged artery. Do not stop a prescribed anticoagulant independently unless the treating emergency team directs you to do so.
What follow-up is needed after treatment?
Follow-up after hemosuccus pancreaticus focuses on recurrent bleeding, recovery from anemia, and the pancreatic or vascular problem that caused the event. The schedule depends on the intervention and the person's condition.
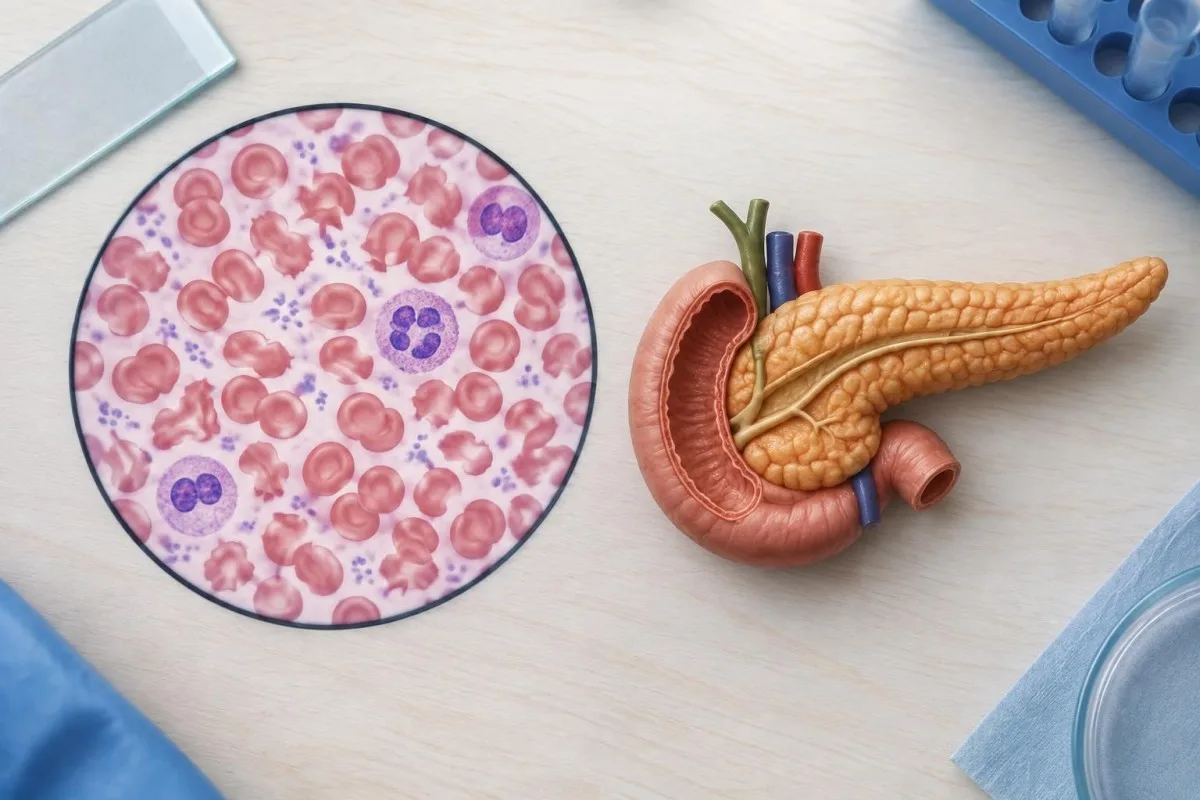
Before leaving hospital, ask which symptoms should trigger emergency care and whom to contact about non-emergency questions. New vomiting of blood, black tarry stool, fainting, or marked weakness should not wait for a scheduled appointment.
Repeat hemoglobin and, when appropriate, iron studies can help track recovery. Low ferritin may suggest depleted iron stores, but inflammation can complicate its interpretation; our რკინის შესწავლის სახელმძღვანელო explains the related markers.
კანტესტი არის AI სისხლის ანალიზის განმარტების პლატფორმა that can help organize follow-up laboratory results for discussion with a clinician. Its პასუხისმგებლიანი AI-ის შესახებ ინფორმაცია explains why an automated interpretation is not a substitute for clinical decisions.
What should you ask your care team?
Ask your care team whether a source has been confirmed, whether a pancreatic vessel or fluid collection was seen, and what to do if bleeding returns. These questions clarify both the current diagnosis and the plan if uncertainty remains.
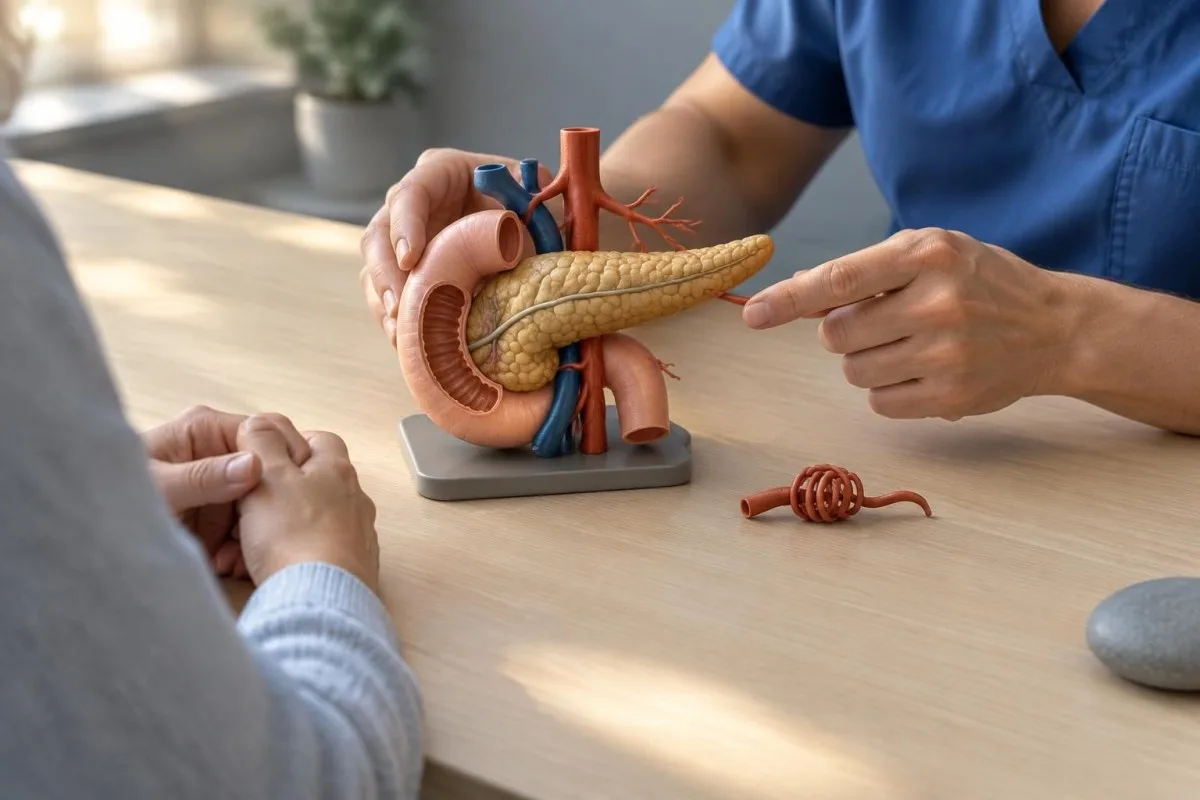
Useful questions include: “Was the papilla seen during endoscopy?”, “Did the scan show a pseudoaneurysm?”, and “Would repeat imaging or specialist review be appropriate if symptoms recur?” The answers depend on the actual examination and your clinical stability.
If treatment was performed, ask which vessel was treated, whether further imaging is planned, and when medicines can safely be resumed. Keep copies of the discharge summary and imaging reports available for future emergency visits.
Kantesti can support discussion of laboratory trends, but it cannot confirm a bleeding source or advise you to delay care. Our სამედიცინო შინაარსის სტანდარტები describe the approach used for health information on the site.
ხშირად დასმული კითხვები
ჰემოსუკუს პანკრეატიკუსი გადაუდებელი მდგომარეობაა?
ჰემოსუკუს პანკრეატიკუსი შესაძლოა სიცოცხლისთვის საშიში გადაუდებელი მდგომარეობა იყოს, რადგან დაზიანებული არტერიიდან შეიძლება ძლიერი სისხლდენა დაიწყოს ან სისხლდენა განმეორდეს. სისხლიანი ღებინების, შავი, კუპრისებრი განავლის, გონების დაკარგვის ან სავარაუდო სისხლდენასთან დაკავშირებული ძლიერი სისუსტის შემთხვევაში დაუყოვნებლივ მიმართეთ გადაუდებელ სამედიცინო დახმარებას. დახმარების მისაღებად ნუ დაელოდებით მეორე ეპიზოდს ან განავლის ანალიზის პასუხს.
შეიძლება ენდოსკოპიამ ჰემოსუკუს პანკრეატიკუსი ვერ გამოავლინოს?
დიახ. ზედა ენდოსკოპიამ შეიძლება ვერ გამოავლინოს hemosuccus pancreaticus, თუ სისხლდენა შეჩერებულია ან პანკრეასის სადინრის შესართავი მკაფიოდ არ ჩანს. ექიმმა, ვითარებიდან გამომდინარე, შეიძლება განიხილოს გვერდითი ხედვის ენდოსკოპიური გამოკვლევა, CT-ანგიოგრაფია ან სხვა სპეციალისტის მიერ ჩატარებული კვლევა. ერთი უარყოფითი ტესტი აუცილებლად არ გამორიცხავს პერიოდულ სისხლდენას.
რომელია ყველაზე ინფორმაციული კვლევა ჰემოსუკუს პანკრეატიკუსზე ეჭვის შემთხვევაში?
კომპიუტერული ტომოგრაფიული ანგიოგრაფია ხშირად სასარგებლოა, რადგან მას შეუძლია გამოავლინოს პანკრეასის ფსევდოანევრიზმა, კონტრასტული ნივთიერების აქტიური გაჟონვა და პანკრეასის სხვა თანმხლები ცვლილებები. კათეტერული ანგიოგრაფია არტერიების უფრო დეტალურ გამოსახულებებს იძლევა და, ამასთან, მკურნალობის საშუალებასაც შეიძლება იძლეოდეს. წყვეტილი სისხლდენის შემთხვევაში ორივე კვლევის შედეგი შეიძლება უარყოფითი იყოს, ამიტომ ექიმები მას სიმპტომებისა და სხვა მონაცემების გათვალისწინებით აფასებენ.
შეუძლია თუ არა ჰემოგლობინის ნორმალურმა დონემ პანკრეასის სადინრიდან სისხლდენის გამორიცხვა?
არა. უეცარი სისხლის დაკარგვის შემდეგ ჰემოგლობინი თავდაპირველად შეიძლება რეფერენსულ დიაპაზონში დარჩეს და ვერ განსაზღვრავს, საიდან დაიწყო სისხლდენა. კლინიცისტებმა შეიძლება გაიმეორონ სრული სისხლის ანალიზი და შეაფასონ არტერიული წნევა, პულსი, სიმპტომები და გამოსახულებითი კვლევების შედეგები. გადაუდებელი გადასხმის შესახებ გადაწყვეტილება კლინიკური სურათის მთლიან შეფასებას ეფუძნება და არა მხოლოდ ერთ ლაბორატორიულ მაჩვენებელს.
Does a positive FIT diagnose hemosuccus pancreaticus?
No. A positive FIT detects human hemoglobin in stool but does not locate the source or diagnose hemosuccus pancreaticus. A negative FIT also cannot reliably exclude an upper gastrointestinal bleed, because blood may be digested before it reaches the stool. Visible bleeding or black tarry stool requires clinical assessment rather than waiting for a screening test.
Can hemosuccus pancreaticus be treated without surgery?
Hemosuccus pancreaticus can sometimes be treated without open surgery through catheter-directed embolization of the responsible artery. The approach depends on the vessel anatomy, the person's stability, and available expertise. Surgery remains an option when embolization is not feasible, fails, or another pancreatic problem requires an operation.
მიიღეთ სისხლის ანალიზის შედეგების ახსნა
ატვირთეთ თქვენი ლაბორატორიული ანგარიში და Kantesti-ის AI რამდენიმე წამში თითოეულ ბიომარკერს მარტივი ენით აგიხსნით. მას მსოფლიოში 2 მილიონზე მეტი ადამიანი იყენებს.
ცნობები
- Klein, T., Mitchell, S., & Weber, H. (2026). BUN/კრეატინინის თანაფარდობის ახსნა: თირკმლის ფუნქციის ანალიზის სახელმძღვანელო. Kantesti AI-ის სამედიცინო კვლევა. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). ურობილინოგენი შარდში: სრული შარდის ანალიზის სახელმძღვანელო 2026. Kantesti AI-ის სამედიცინო კვლევა. DOI
- Tarar ZI et al. (2022). Hemosuccus Pancreaticus: A Comprehensive Review of Presentation, Diagnosis, and Management. Gastroenterology Research.
- Laine L et al. (2021). ACG Clinical Guideline: Upper Gastrointestinal and Ulcer Bleeding. American Journal of Gastroenterology. DOI
- 2 მილიონი+გაანალიზებული ტესტები
- 127+ქვეყნები
- 100+ენები
სამედიცინო გუნდის შესახებ


E-E-A-T სანდოობის სიგნალები
გამოცდილება
ექიმის ხელმძღვანელობით კლინიკური მიმოხილვა ლაბორატორიული ინტერპრეტაციის სამუშაო პროცესებზე.
ექსპერტიზა
ლაბორატორიული მედიცინის აქცენტი იმაზე, როგორ იქცევიან ბიომარკერები კლინიკურ კონტექსტში.
ავტორიტეტულობა
სამედიცინო თვალსაზრისით რეცენზირებულია დოქტორ თომას კლაინის მიერ, დოქტორ სარა მიტჩელისა და პროფესორ ჰანს ვებერის მონაწილეობით.
სანდოობა
მტკიცებულებებზე დაფუძნებული ინტერპრეტაცია, მკაფიო შემდგომი ნაბიჯებით, რათა შემცირდეს განგაშის დონე.




სამედიცინო პასუხისმგებლობის შეზღუდვის განცხადება
ეს სტატია მხოლოდ საგანმანათლებლო მიზნებისთვისაა და არ წარმოადგენს სამედიცინო რჩევას. დიაგნოზისა და მკურნალობის გადაწყვეტილებებისთვის ყოველთვის მიმართეთ კვალიფიციურ ჯანდაცვის სპეციალისტს.
გამოქვეყნდა · დაუკავშირდით სარედაქციო გუნდს
გამოქვეყნებულია Kantesti Ltd-ის მიერ, რეგისტრირებულია ინგლისსა და უელსში, კომპანიის №. 17090423, ლონდონი, გაერთიანებული სამეფო.
