
וריאנט JAK2 שזוהה יכול להיות רמז חשוב, אך ספירת הדם, שיטת הבדיקה והתמונה הקלינית קובעות מה יקרה בהמשך.

נקודות עיקריות
- תוצאה חיובית: וריאנט JAK2 שזוהה תומך בתהליך קלונלי של תאי דם, אך כשלעצמו אינו מבסס אבחנה מסוימת.
- V617F: JAK2 V617F מופיע בכ-95% ממקרי הפוליציתמיה ורה ובכמחצית ממקרי התרומבוציתמיה החיונית והמיאלופיברוזיס הראשונית.
- אקסון 12: מוטציה באקסון 12 של JAK2 רלוונטית במיוחד כאשר יש חשד לפוליציתמיה ורה ולא מתגלה V617F.
- תוצאה שלילית: תוצאה שלילית למוטציית JAK2 אינה שוללת כל מחלה מיאלופרוליפרטיבית; היא מתייחסת רק לווריאנטים שהבדיקה כוללת.
- עומס אללי: תדירות אללית של וריאנט בשיעור 1% מתארת בקירוב עותק מוטנטי אחד לכל 100 עותקי DNA שנבדקו, ולא בהכרח 1% מהתאים.
- ספירת דם: עלייה מתמשכת בהמוגלובין, בהמטוקריט או בטסיות יכולה להנחות את השלב הבא בבירור, אך לכל אחד מהם יש גם גורמים שאינם סרטניים.
- מעקב: Ask for the exact variant, specimen, detection limit and whether exon 12, CALR or MPL testing is appropriate.
- תסמינים דחופים: Sudden stroke symptoms, chest pain or breathlessness require emergency assessment regardless of the JAK2 result.
מה המשמעות של תוצאה חיובית למוטציית JAK2?
A positive JAK2 mutation test result means the laboratory detected a specified genetic change in the tested sample. It supports the possibility of a myeloproliferative neoplasm, or MPN, but it does not identify the MPN subtype or prove that diagnostic criteria are met.

JAK2 helps transmit signals that regulate production of blood-cell lineages. An acquired activating variant can give a group of marrow cells a growth advantage; that group is called a clone.
The JAK2 V617F positive meaning depends on why testing was ordered. A persistent elevation in red cells suggests a different workup from isolated high platelets, even if the same variant is found.
Kantesti is an AI blood test analyzer that can help organize a JAK2 report alongside a complete blood count for discussion with a clinician. The מדריך הביומרקרים שלנו provides context for other measurements, but AI cannot diagnose an MPN or replace hematology review.
אילו מצבים קשורים ל-JAK2 V617F?
JAK2 V617F is strongly associated with polycythemia vera, essential thrombocythemia and primary myelofibrosis. Its presence supports a clonal process, but all three conditions—and occasionally other myeloid disorders—can carry the same variant.
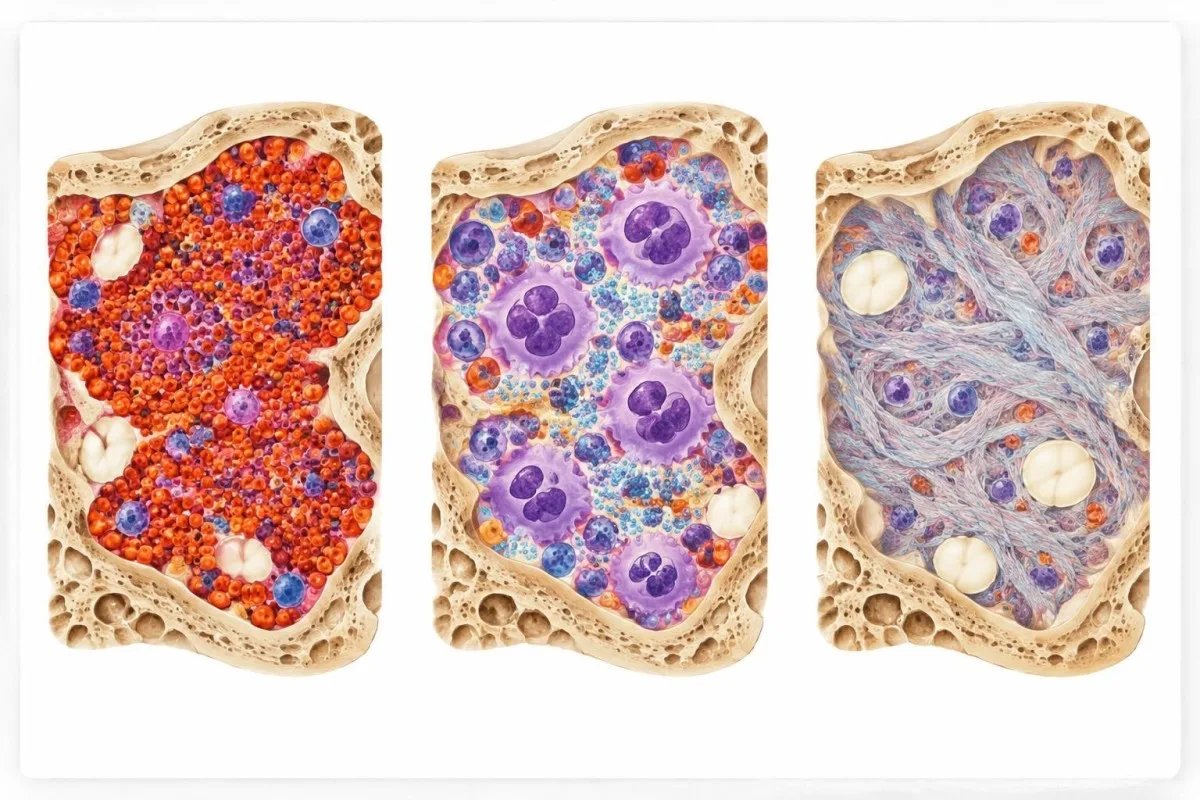
JAK2 V617F is present in approximately 95% of polycythemia vera cases and around 50–60% of essential thrombocythemia or primary myelofibrosis cases. These are approximate frequencies in diagnosed groups, not the chance that a person with a positive result has a particular disease.
פוליציטמיה ורה מתבטאת בעיקר בייצור מוגבר של תאי דם אדומים; תרומבוציטמיה ראשונית מאופיינת בעלייה מתמשכת במספר הטסיות; ולמיאלופיברוזיס ראשונית יש שינויים אופייניים במח העצם שעלולים להתקדם לפיברוזיס. מסגרות האבחון גם מבחינות בין מיאלופיברוזיס מוקדמת, או קדם־פיברוטית, לבין תרומבוציטמיה ראשונית (Arber et al., 2022).
רופא עשוי לשקול בדיקת BCR-ABL1 כאשר דפוס ספירת הדם מעלה אפשרות של לוקמיה מיאלואידית כרונית. זוהי בדיקה מולקולרית שונה, ולא שם חלופי לבדיקת JAK2.
מה המשמעות של מוטציה באקסון 12 של JAK2?
A מוטציה באקסון 12 של JAK2 היא שינוי נרכש בחלק אחר של הגן JAK2, הקשור באופן הדוק ביותר לפוליציטמיה ורה כאשר V617F אינה מזוהה. בדיקת אקסון 12 שימושית במיוחד בבירור אריתרוציטוזיס התואם לכך.
In the landmark report by Scott and colleagues, JAK2 exon 12 variants were identified in V617F-negative patients with polycythemia vera or related erythrocytosis (Scott et al., 2007). Exon 12 is a region containing several possible variants, rather than one single mutation.
A V617F-only report does not automatically cover exon 12. Ask whether exon 12 was included, performed as a reflex test after a negative V617F result, or requires a separate order.
Clinicians often pair molecular findings with an erythropoietin result. A low erythropoietin level can support polycythemia vera in the right setting, but it is not sufficient to diagnose it by itself.
מדוע תוצאה חיובית אינה מבססת אבחנה של MPN?
A positive JAK2 result does not establish an MPN diagnosis because the variant must be interpreted with blood counts, marrow findings when indicated, clinical history and applicable diagnostic criteria. A small JAK2-mutated clone can also be detected without an overt MPN.

The International Consensus Classification uses combinations of major and minor criteria rather than a JAK2 result alone (Arber et al., 2022). The specific criteria differ between polycythemia vera, essential thrombocythemia and primary myelofibrosis.
For example, a person may have a positive V617F result and a platelet count of 500 × 10⁹/L, but iron deficiency or inflammation may also contribute to the count. A hematologist assesses the whole pattern before assigning a diagnosis.
A myelodysplastic syndrome evaluation illustrates a related principle: molecular clues and the marrow examination answer different questions. Neither should be interpreted as an isolated verdict.
אילו דפוסים בספירת הדם מנחים את הבירור?
Persistent elevations in hemoglobin, hematocrit or platelets help clinicians decide which MPN criteria and alternative causes to investigate. A single abnormal complete blood count is a starting point, not a diagnosis.
For polycythemia vera, one commonly used adult criterion is hemoglobin above 16.5 גרם/ד״ל בגברים אוֹ 16.0 גרם/ד״ל בנשים, או המטוקריט מעל 49% or 48%, respectively. These thresholds are diagnostic criteria used with other findings, not stand-alone treatment triggers.
For essential thrombocythemia, a sustained platelet count of at least 450 × 10⁹/ליטר is one criterion. Infection, inflammation, iron deficiency and other conditions can also raise platelets, so the duration and associated findings matter.
Compare the values and units on your report with previous results. Our guide to hematocrit versus hemoglobin explains why the two measures can sometimes tell different stories.
מה המשמעות של עומס אללי נמוך של JAK2?
נמוך variant allele fraction, or VAF, means that a small proportion of JAK2 DNA copies in the tested sample carry the reported variant. A low VAF can occur in an early or small clone, but its clinical meaning depends on the assay and the rest of the evaluation.

A VAF of 1% means roughly 1 in 100 tested JAK2 copies carried the variant in that specimen. It does not automatically mean 1% of all cells are affected: cell mixture, gene-copy number and whether cells carry one or more variant copies can change the relationship.
For a simplified hypothetical example, if every relevant cell has two JAK2 copies and each affected cell has one variant copy, a 1% VAF could correspond to roughly 2% affected cells. Real clinical samples may not satisfy those assumptions.
Very small clones may represent המטופואזיס קלונלי, a finding that can occur without an established blood cancer. A hematologist may review count trends and the original assay rather than label a low result benign or malignant from its percentage alone; see our guide to תוצאות איכותיות וכמותיות.
כיצד גבולות הגילוי משפיעים על תוצאות JAK2?
A JAK2 assay detects variants only within its validated coverage and sensitivity. A result close to the laboratory’s detection or quantification limit may be less precise than a higher-level result, even when the finding is real.

ה limit of detection is the lowest level at which an assay can reliably detect a variant under its validation conditions. The limit of quantification concerns reliable measurement of its amount; the two limits can differ.
Hypothetically, a laboratory with a 0.1% detection limit could detect a clone missed by an assay with a 1% limit. This comparison only applies if both assays cover the same variant and use suitable specimens.
Reports may say “detected below the quantifiable range,” give a percentage, or provide only a positive/negative answer. Kantesti can help organize those terms, but the laboratory’s own method notes remain the reference; our מדריך טכנולוגיית בינה מלאכותית explains the platform’s general approach.
מה המשמעות של תוצאה שלילית למוטציית JAK2?
A JAK2 mutation negative result means no covered variant was detected above that test’s reporting limit. It does not exclude every MPN, every JAK2 variant or a clone below the assay’s sensitivity.

A negative V617F result is less supportive of polycythemia vera because about 95% of diagnosed cases carry V617F, but exon 12 variants account for many of the remaining cases. The next test depends on the clinical pattern and what the first assay actually covered.
Essential thrombocythemia and primary myelofibrosis can be associated with CALR אוֹ MPL variants instead of JAK2 V617F. Some patients have none of these three common driver variants detected, sometimes described as משולש-שלילי.
A report can be negative, indeterminate or technically unsuccessful; those are different outcomes. Ask the ordering team whether the specimen was adequate and whether genetic panel limitations affect the interpretation.
אילו בדיקות עשויות להתבצע בעקבות תוצאת JAK2?
Follow-up testing can include repeat blood counts, a blood-film review, erythropoietin, iron studies, additional molecular tests and sometimes a bone marrow examination. The choice depends on whether the main finding involves red cells, platelets, white cells or unexplained symptoms.

When platelets remain at or above 450 × 10⁹/ליטר, clinicians may assess iron status and inflammation as well as consider CALR and MPL testing. A raised platelet count is not specific for an MPN.
A marrow examination can distinguish patterns that a molecular result cannot, including essential thrombocythemia from prefibrotic primary myelofibrosis. The decision to perform one is individualized and depends on the diagnostic question.
A blood film may reveal immature cells or unusual shapes. Our guide to teardrop cells on a smear explains why such findings need context rather than automatic attribution to myelofibrosis.
האם מחסור בברזל או התייבשות יכולים לשנות את התמונה?
Iron deficiency can make red cells smaller and may obscure the degree of red-cell overproduction, while dehydration can make a blood count appear concentrated. Both can complicate the evaluation of suspected polycythemia vera.
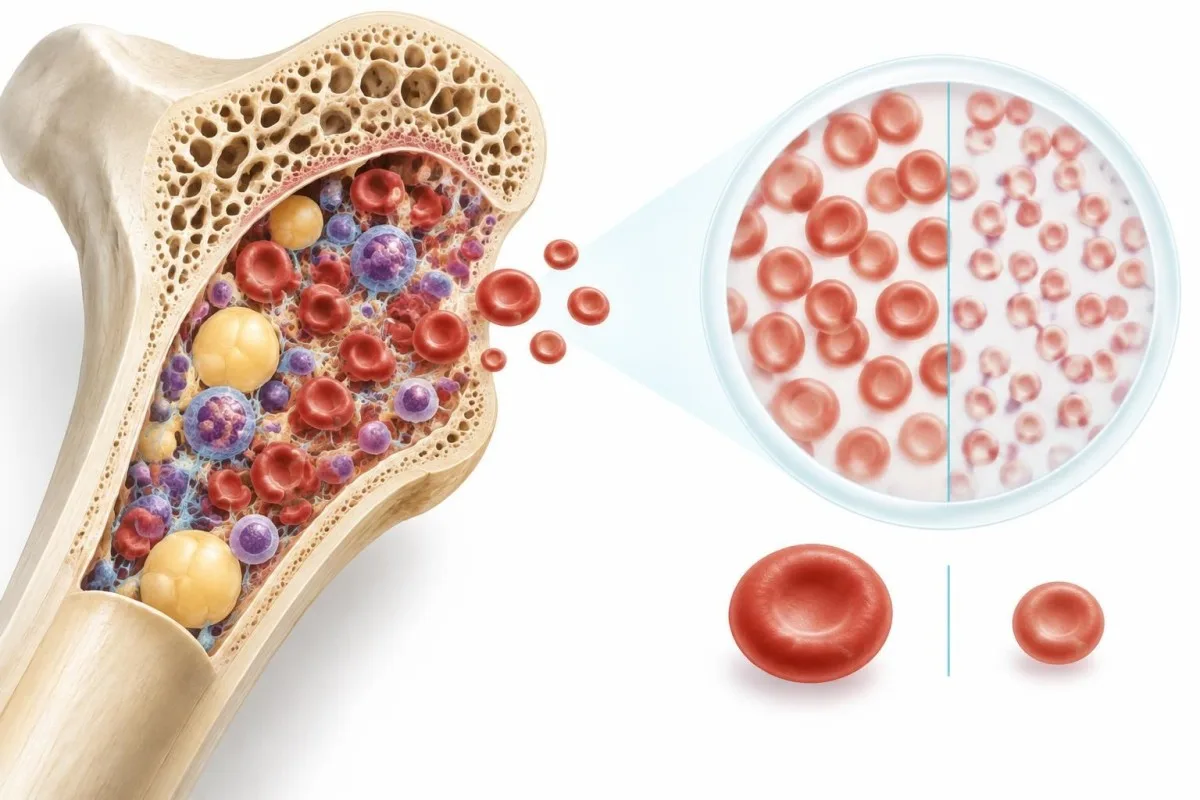
Low mean corpuscular volume, or MCV, can accompany iron deficiency. In a compatible clinical setting, a high red-cell count with small cells may deserve closer review even when hemoglobin is not strikingly elevated.
A hypothetically dehydrated patient may have a raised hematocrit because plasma volume is reduced, not because the body has produced excess red cells. A clinician can assess the history and decide when a repeat count is appropriate.
ה מדריך ללימודי ברזל explains how ferritin, transferrin saturation and related measurements fit together. Do not start or stop iron solely because of a JAK2 result; ask the clinician managing the workup.
האם מוטציית JAK2 עוברת בתורשה לבני משפחה?
JAK2 V617F and the exon 12 variants discussed in MPN testing are usually acquired, or somatic, changes in blood-forming cells rather than inherited variants present throughout the body. A positive result does not automatically mean children or siblings carry the same variant.
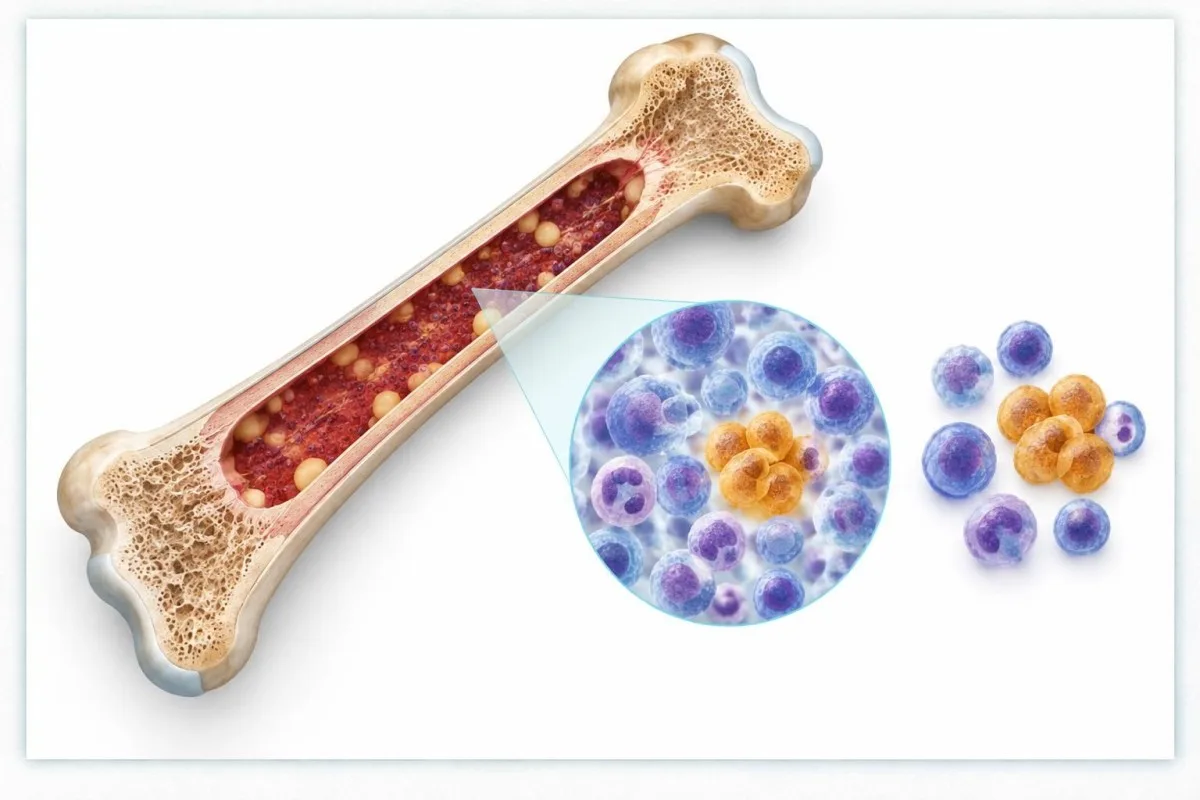
A family history of MPNs can still matter because inherited factors may affect susceptibility in some families. That is distinct from directly passing on the acquired V617F variant found in a blood-cell clone.
Blood-based testing alone can be difficult to use for determining whether some variants are inherited when a person has a myeloid disorder. If an inherited predisposition is suspected, a specialist can select appropriate testing and a suitable non-blood tissue source.
For contrast, our article on BRCA genetic results discusses inherited cancer-predisposition testing. It should not be treated as an interpretation guide for an acquired JAK2 result.
האם תוצאה חיובית ל-JAK2 פירושה שייווצר קריש דם?
A positive JAK2 result does not mean a blood clot will occur, although JAK2-associated MPNs can increase clotting risk. Risk assessment depends on the established diagnosis, prior clotting, age and other clinical factors—not the molecular result alone.
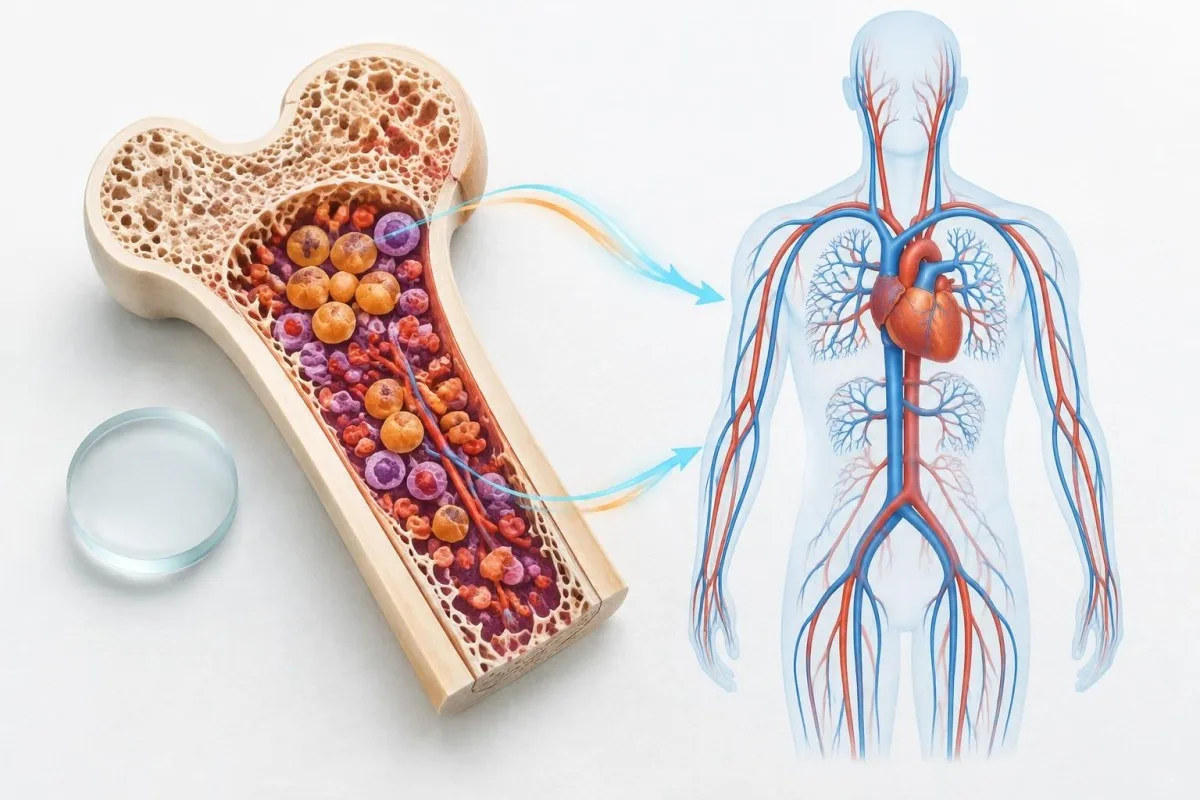
In polycythemia vera, clinicians commonly consider age over 60 שנים and a history of thrombosis when assessing risk. Other factors, including the blood count and cardiovascular risks, can influence individual management.
Do not begin aspirin, anticoagulants or phlebotomy solely because a JAK2 report is positive. These interventions have benefits and risks that require a diagnosis-specific plan.
New one-sided leg swelling can be a sign of deep vein thrombosis and needs prompt medical assessment. Sudden chest pain, severe breathlessness, facial droop, arm weakness or speech difficulty warrants emergency services.
מתי עשויה להיות תועלת בבדיקה חוזרת של JAK2?
Repeat JAK2 testing may be useful when a result is near an assay’s limit, the sample was inadequate, the clinical picture changes or a specialist needs to clarify discordant findings. There is no universal retest interval for every positive or negative result.

Two VAF values from different laboratories may not be directly comparable if their methods, specimen types or reporting limits differ. A change from 0.2% to 0.3%, for example, may be hard to interpret without knowing measurement uncertainty.
For someone receiving MPN treatment, the clinician may request molecular monitoring for a specific reason; VAF should not be used alone to change medication or predict an individual outcome. Blood counts, symptoms and the treatment plan still matter.
Kantesti is an AI biomarker interpretation platform that can help readers organize dated results for review, but it cannot validate whether two JAK2 assays are interchangeable. Our מדריך ללוח זמנים של בדיקות דם covers practical comparison questions.
על מה כדאי לשוחח עם הרופא המטפל בהמשך?
Bring the complete JAK2 report and recent blood counts to the ordering clinician, and ask whether a hematology referral is appropriate. The immediate next step depends on the variant, blood-count pattern, symptoms and reason for testing.

Ask four practical questions: Which variant was tested? Was the result qualitative or quantitative? What were the assay’s detection and quantification limits? Were exon 12, CALR or MPL variants included or tested separately?
Take prior complete blood counts, iron results, a medication list and any history of clotting or unusual bleeding. For example, a platelet count that has stayed above 450 × 10⁹/ליטר across repeated tests tells a different story from a single raised count during an acute illness.
Kantesti can help organize a PDF or photo of laboratory results, but an AI explanation is not a diagnosis or a reason to delay specialist care. Read our מידע על אימות רפואי for the platform’s stated approach and limitations.
שאלות נפוצות
האם תוצאה חיובית ל-JAK2 V617F פירושה שיש לי סרטן?
תוצאה חיובית ל-JAK2 V617F אינה מוכיחה כשלעצמה שיש לך סרטן. הווריאנט נפוץ בנאופלזמות מיאלופרוליפרטיביות, לרבות בכ-95% ממקרי הפוליציטמיה ורה, אך ניתן למצוא אותו גם בשבט קטן של תאי דם ללא MPN מאובחנת. רופא מפרש את התוצאה לצד ספירות הדם, התסמינים ולעיתים גם בדיקת מח עצם.
האם ייתכן שיש לי MPN אם תוצאת בדיקת JAK2 שלי שלילית?
כן. תוצאה שלילית ל-JAK2 אינה שוללת את כל המחלות המיאלופרוליפרטיביות, ובדיקה ל-V617F בלבד אינה שוללת מוטציה באקסון 12 של JAK2. בכמחצית מהמקרים של תרומבוציטמיה חיונית ושל מיאלופיברוזיס ראשונית יש JAK2 V617F; באחרים עשויות להיות וריאציות ב-CALR או ב-MPL, או שלא תתגלה אף אחת משלוש הווריאציות האלה. שאלו אילו וריאציות נבדקו בבדיקה שלכם והאם בדיקות נוספות מתאימות לדפוס ספירת הדם שלכם.
האם עומס האלל של JAK2 בשיעור של 1% הוא חמור?
שיעור האלל של הווריאנט JAK2 בשיעור של 1% פירושו שככל הנראה בערך 1 מכל 100 עותקי DNA של JAK2 שנבדקו נשא את הווריאנט בדגימה זו. כשלעצמו, הדבר אינו קובע את חומרת המחלה, אינו מנבא את התוצאה אצל אדם מסוים ואינו שווה ערך ל־1% תאים נגועים. שיטת הגילוי, ספירות הדם, התסמינים והשאלה אם נקבעה אבחנה של MPN — כל אלה חשובים. יש לדון בתוצאה ברמה נמוכה עם הרופא שהפנה לבדיקה, במקום להניח שהיא בלתי מזיקה או מסוכנת.
מה ההבדל בין JAK2 V617F לאקסון 12?
JAK2 V617F הוא וריאנט ספציפי, בעוד ש-JAK2 exon 12 מתייחס לאזור שבו יכולים להתרחש כמה וריאנטים שונים. V617F נמצא בכ-95% ממקרי הפוליציתמיה ורה ומופיע גם בתרומבוציטמיה חיונית ובמיאלופיברוזיס ראשוני. וריאנטים באקסון 12 רלוונטיים במיוחד לפוליציתמיה ורה שלילית ל-V617F. בדיקה המאתרת V617F בלבד עשויה שלא לבדוק את exon 12.
האם ניתן להעביר לילדיי מוטציית JAK2?
השינויים JAK2 V617F ו־exon 12 שמתגלים במהלך בירור של MPN נרכשים בדרך כלל בתאים יוצרי הדם ולא עוברים בתורשה. לכן, תוצאה חיובית אינה מעידה שילד ירש את אותה מוטציה. במשפחות מסוימות קיימת נטייה מוגברת ל־MPN, לכן שתפו את הרופא המטפל בהיסטוריה המשפחתית של מחלות דם. מומחה לגנטיקה יוכל לייעץ אם בדיקה להערכת סיכון תורשתי מתאימה.
האם עליי להתחיל ליטול אספירין לאחר בדיקת JAK2 חיובית?
אין להתחיל ליטול אספירין רק בגלל תוצאה חיובית של בדיקת JAK2. החלטות הטיפול תלויות בשאלה אם אובחן MPN, בתת־הסוג, בסיכון לדימום ובגורמים כגון גיל ופקקת קודמת. לדוגמה, גיל מעל 60 הוא אחד הגורמים המשמשים להערכת הסיכון בפוליציטמיה ורה, אך אין בכך הנחיה לטיפול עצמי. בקשו מהרופא המטפל תוכנית אישית.
קבלו הסבר על תוצאות בדיקות הדם שלכם
העלו את דוח המעבדה שלכם, וה-AI של Kantesti יסביר כל סמן ביולוגי בשפה פשוטה בתוך שניות. יותר מ-2 מיליון אנשים ברחבי העולם משתמשים בו.
הפניות
- Klein, T., Mitchell, S., & Weber, H. (2026). מנתח בדיקות דם בינה מלאכותית: 2.5M בדיקות נותחו | דוח בריאות עולמי 2026. מחקר רפואי של Kantesti AI. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). בדיקת דם ל-RDW: מדריך מלא ל-RDW-CV, MCV ו-MCHC. מחקר רפואי של Kantesti AI. DOI
- Arber DA et al. (2022). International Consensus Classification of Myeloid Neoplasms and Acute Leukemias: integrating morphologic, clinical, and genomic data. Blood. DOI
- Scott LM et al. (2007). JAK2 Exon 12 Mutations in Polycythemia Vera and Idiopathic Erythrocytosis. New England Journal of Medicine. DOI
- 2 מיליון+בדיקות שנותחו
- 127+מדינות
- 100+שפות
על הצוות הרפואי


אותות אמון E-E-A-T
הִתנַסוּת
סקירה קלינית בהובלת רופא של תהליכי עבודה לפענוח בדיקות מעבדה.
מוּמחִיוּת
רפואה מעבדתית מתמקדת באופן שבו סמנים ביולוגיים מתנהגים בהקשר קליני.
סמכותיות
נבדק רפואית על ידי ד״ר Thomas Klein, בתרומתם של ד״ר Sarah Mitchell ופרופ׳ ד״ר Hans Weber.
אֲמִינוּת
פרשנות מבוססת-ראיות עם מסלולי המשך ברורים כדי להפחית בהלה.



הצהרה רפואית
מאמר זה מיועד למטרות חינוכיות בלבד ואינו מהווה ייעוץ רפואי. תמיד יש להתייעץ עם גורם מוסמך בתחום הבריאות לצורך החלטות אבחון וטיפול.
פורסם · צרו קשר עם צוות העריכה
פורסם על ידי Kantesti Ltd, הרשומה באנגליה ובוויילס, מספר חברה. 17090423, לונדון, בריטניה.
