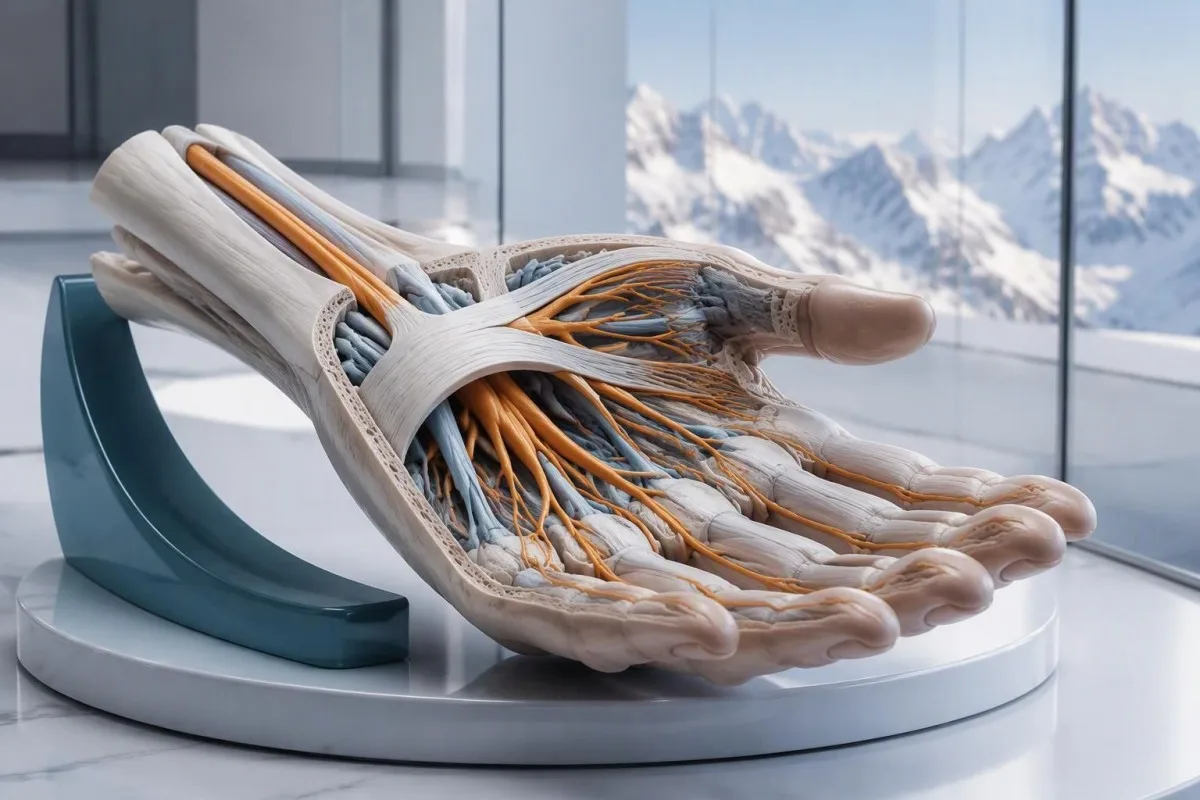
De troffen fingers helpe om it senuwprobleem te lokalisearjen. Symptomen nachts, de krêft fan 'e tomme en it patroan bûten de hân helpe te bepalen oft allinnich ûndersyk genôch is.


- Fingerpatroan: It karpale-tunnelsyndroom treft meastal de tomme, de wiisfinger, de middelfinger en de helte fan 'e ringfinger oan 'e tommekant — it gebiet fan likernôch 3½ fingers dat troch de mediane senuw betsjinne wurdt.
- Lytse finger: Dommens benammen yn 'e lytse finger en de neistlizzende ringfinger wiist op de ulnaire senuw, ynstee fan op in isolearre karpale tunnel.
- Tinteljen nachts: In polsspalk dy't de pols yn in neutrale posysje hâldt, kin symptomen ûnder it sliepen ferminderje; by oanhâldende swakte moat in langere proef mei thúsbehanneling net ôfwaachte wurde.
- Swakte fan 'e tomme: Swierrichheden om de tomme fan 'e palm ôf op te tillen of him tsjin de lytse finger oan te bringen, binne spesifyker as in oer it generaal swakke grip.
- Klinyske diagnoaze: De AAOS-rjochtline fan 2024 stipet de 6-item CTS-6-beoardieling ynstee fan routine-ultrasoan of senuwgeliedingsûndersyk yn dúdlike gefallen.
- Senuwûndersyk: Senuwgeliedingsûndersiken helpe om de kompresje te lokalisearjen en de earnst te beoardieljen; in normale útslach slút lichte, tuskenskoft foarkommende oandwaning net folslein út.
- Beheiningen fan bloedûndersyk: In HbA1c fan op syn minst 6.5% kin in diabetesdiagnoaze stypje, mei passende befêstiging, mar gjin bloedûndersyk befêstiget senuwkompresje yn 'e pols.
- Dringende symptomen: Ynienen dommens yn in hân mei in hingjende mûlehoeke, swierrichheden mei praten of nije swakte yn in earm freget om direkte needbeoardieling—even as mar 1 hân troffen is.
Hokker fingers wurde meastentiids troffen troch symptomen fan it karpale-tunnelsyndroom?
Symptomen fan karpale-tunnelsyndroom treffe meastal de tomme, wiisfinger, middelfinger en de helte fan 'e ringfinger oan 'e tommekant. De lytse finger bliuwt meastal frij. Tintelingen meitsje minsken faak nachts wekker, wylst oanhâldende dommens of ferlies fan tommekrêft wiist op wichtiger kompresje fan 'e medianus yn 'e pols.
De medianus rint ûnder it dwerse karpale ligament troch foardat er gefoel jout oan likernôch 3½ fingers. Symptomen treffe faak de oerflakken fan 'e fingers oan 'e palmkant en de fingertoppen, ynklusyf it gebiet fan it neilbêd; se hoege net krekt op te hâlden by in kreaze line dy't op in hândiagram tekene is.
Pine is anatomysk minder maklik ôf te bakenjen as dommens: ûngemak troch karpale-tunnelsyndroom kin útwreidzje nei de pols of ûnderearm, sels as it feroare gefoel binnen it gebiet fan 'e medianus bliuwt. Padua en kollega's beskriuwe dizze kombinaasje fan karakteristike gefoelssymptomen en fariabele pine yn har resinsje út 2016 yn Lancet Neurology; 1 allinnich in pynlike pols stelt de diagnoaze net fêst.
Myn redaksjonele oanpak as Thomas Klein, MD, is om te begjinnen mei de fingerkaart foardat ik laboratoariumresultaten ynterpretearje. Kantesti is in AI bloedtestanalysator dy't helpt om relevante laboratoariumfynsten te ferklearjen, net in ferfanging foar it lokalisearjen fan in komprimearre senuw; ús organisaasje en klinyske omfang ferklearje dat ûnderskied, dat fan belang is as 1 hân dommens fielt nettsjinsteande normale bloedûndersyksresultaten.
Wat betsjutte symptomen oan 'e ringfinger en dommens yn 'e palm?
De ringfinger hat in ferdielde sintúchlike oanfier: de helte oan 'e tommekant heart benammen by de medianus, wylst de kant oan 'e lytse finger benammen by de ulnaris heart. Dommens oer de flezige basis fan 'e tomme is minder typysk foar isolearre karpale-tunnelsyndroom, om't in tûke fan 'e medianus dat gebiet bûten de tunnel berikt.
De palmar kutane tûke ferlit de medianus meastal ferskate sintimeters foar de pols en rint oerflakkich foar it karpale ligament lâns. Troch dy anatomyske omwei kin echt gefoelsferlies oer de thenaremininsje—it flezige gebiet oan 'e tommebasis—oanlieding jaan ta ûndersyk nei kompresje hegerop yn 'e ûnderearm, ynstee fan derfan út te gean dat elk symptoom fan 'e medianus út 1 lokaasje komt.
Pasjinten kinne sizze dat de hiele hân dom is, sels as by ûndersyk in lytser gebiet fûn wurdt. In nuttige waarnimming yn 2 stappen is om tidens in ôflevering de fingertop te bepalen dy't it slimst troffen is, en dêrnei de lytse finger mei de wiisfinger te ferlykjen; dit helpt in klinikus mear as besykje in perfekte anatomyske tekening út 'e holle te learen.
Wiidfersprate sintúchlike symptomen freegje om in bredere ferklearring, benammen as beide fuotten likegoed as beide hannen troffen binne. Us besprek fan grinswearden foar B12 en senuwsymptomen behannelet in mooglike alternative ferklearring dy't foarkomme kin sûnder dúdlike bloedearmoed; in B12-wearde fan likernôch 200–300 pg/mL freget faak om klinyske kontekst, net om automatysk it etiket karpale-tunnelsyndroom.
Wêrom wiist tinteljen yn 'e hân nachts op it karpale-tunnelsyndroom?
Tintelingen yn 'e hân nachts binne karakteristyk foar karpale-tunnelsyndroom, om't it bûgjen of útrekkenjen fan 'e pols yn 'e sliep de druk om 'e medianus hinne ferheegje kin. Waking with numb fingers and getting temporary relief by shaking the hand supports the diagnosis, but neither feature proves it on its own.
The wrist does not have to be sharply bent to aggravate symptoms; prolonged positioning can matter more than a brief movement. In a hypothetical 46-year-old who wakes twice nightly with index- and middle-finger tingling, I would ask whether the hand is tucked beneath a pillow, whether the elbow is bent, and whether changing position actually helps.
An elbow bent for hours can also irritate the ulnar nerve, producing nighttime ring- and little-finger symptoms. That is why 2 people with identical sleep disruption may need different advice: a wrist splint targets median nerve pressure, while reducing prolonged elbow flexion targets a different compression site.
Nighttime numbness is a localization clue, not a reason to order a hormone panel simply because sleep is poor. Our guide to sleep-related laboratory changes separates temporary lab effects from structural nerve problems; record symptoms across 7 nights, including the affected fingers and the position that relieved them, before your appointment.
Wat binne de iere tekens fan it karpale-tunnelsyndroom?
Early signs of carpal tunnel usually include intermittent fingertip tingling, nighttime waking, and symptoms during sustained wrist positions or gripping. Constant numbness and visible thumb-muscle wasting are not reassuring early features; they can indicate more advanced nerve dysfunction and warrant prompt clinical assessment.
A normal-looking hand does not rule out carpal tunnel, and 1 symptom-free morning does not mean the nerve has recovered. Early episodes may disappear within minutes after changing position; later, the same person may notice altered touch while buttoning clothing, handling coins, or distinguishing a small object inside a pocket.
Progression is not a fixed sequence, and there is no reliable rule that symptoms become permanent after a particular number of weeks. A practical 3-part diary records episode frequency, whether sensation returns fully between episodes, and whether tasks are becoming harder; loss of recovery between episodes is more concerning than an isolated increase in discomfort.
Sensory symptoms can also precede anemia in tekoart oan fitamine B12, so a normal hemoglobin or MCV should not end the discussion when numbness involves the feet or balance. Our B12 versus folate comparison explains why checking 1 vitamin cannot always answer the question, particularly when high-dose folate supplements are already being taken.
Wannear wiist gripsswakte op skea oan 'e mediane senuw?
Carpal tunnel can weaken thumb opposition and thumb movement away from the palm, making pinch tasks and object handling difficult. General grip weakness is less specific: pain, arthritis, tendon problems, and other neurological conditions can all reduce how firmly someone holds an object.
De abductor pollicis brevis is particularly useful during examination because it lifts the thumb away from the plane of the palm. Clinicians compare the 2 hands and assess resistance rather than simply asking for a fist; squeezing can remain fairly strong while a small but important thumb movement is already weak.
Dropping a mug does not automatically mean permanent nerve damage. It may reflect reduced sensation, pain-limited grip, or true motor weakness—3 different mechanisms with different implications; visible flattening of the thumb-base muscles, especially with constant fingertip numbness, makes a specialist assessment more pressing.
A hypothetical 58-year-old with painful hand joints and weak grip needs a different evaluation from someone with painless thumb weakness and index-finger numbness. Muscle-related laboratory investigations such as those discussed in our aldolase and muscle weakness guide address a separate problem; neither an aldolase nor a CK result identifies compression inside 1 wrist tunnel.
Hoe ferskille problemen mei de earmtakke en de nekke fan it karpale-tunnelsyndroom?
Little-finger numbness suggests ulnar nerve involvement, while neck pain with radiating arm symptoms raises concern for a cervical nerve-root problem. Carpal tunnel more often produces median-territory fingertip symptoms, especially at night, without explaining weakness across several unrelated arm muscles.
Ulnar nerve compression at the elbow commonly affects the little finger and little-finger half of the ring finger; compression at the wrist can produce a similar fingertip pattern. Examining sensation on the back of the ulnar side of the hand helps distinguish these 2 sites, because the relevant sensory branch leaves the nerve before it enters the wrist canal.
A C6 or C7 radiculopathy can overlap thumb, index, or middle-finger symptoms, making finger distribution alone insufficient. Reflex changes, neck-provoked symptoms, and weakness outside the median nerve’s wrist territory help resolve the overlap; carpal tunnel and cervical disease can coexist, but the proposed double-crush mechanism remains more debated than the coexistence itself.
Weakness without sensory loss points away from a straightforward sensory nerve-compression explanation. Our myasthenia testing and symptom guide describes a different pattern involving fatigable weakness with preserved sensation; no single diagnosis should be chosen simply because 1 hand feels less capable.
Kinne bloedûndersiken de oarsaak fan dommens yn 'e hân fêststelle?
Blood tests cannot confirm carpal tunnel, but selected tests can identify contributors or alternative causes of numbness. HbA1c or glucose, vitamin B12, thyroid tests, and kidney function are considered when the history suggests generalized neuropathy, systemic illness, or symptoms beyond 1 median nerve territory.
Vitamin B12 below about 200 pg/mL, equivalent to approximately 148 pmol/L, often supports deficiency, although assays and diagnostic thresholds differ. An indeterminate result may need methylmalonic acid testing; renal impairment can raise that marker independently, so our biomarker-ynterpretaasjegids fan Kantesti is best used alongside the clinical history rather than as an automatic diagnosis.
Tingling around the mouth together with both hands or muscle cramps suggests an electrolyte problem more than isolated wrist compression. Total calcium commonly falls near 8.5–10.5 mg/dL in adult laboratory ranges, but albumin and ionized calcium change interpretation; our low-calcium symptom guide explains why widespread tingling should not be managed with a wrist brace alone.
Kantesti is in AI bloedtest-útslachplatfoarm that can organize these findings, but laboratory interpretation cannot establish which nerve is compressed. For unexplained distal neuropathy, a clinician may also consider protein electrophoresis with immunofixation; our serum protein assessment guide explains a targeted investigation, not a screening panel that everyone with 1 numb finger needs.
Hokker sûnensomstannichheden ferheegje it risiko op it karpale-tunnelsyndroom?
Diabetes, pregnancy, obesity, and some inflammatory joint conditions are associated with carpal tunnel; hypothyroidism can also be a contributor. These associations increase clinical suspicion but do not replace examination, and treating a systemic condition does not necessarily remove an established compression at the wrist.
HbA1c of at least 6.5%, or 48 mmol/mol, is a diabetes diagnostic threshold when appropriate confirmation and test reliability requirements are met. Diabetes can produce generalized neuropathy and focal entrapment at the same time; our high-glucose symptom guide helps distinguish systemic clues such as thirst from a 3½-finger sensory pattern.
A TSH above a laboratory’s reference range—often approximately 0.4–4.0 mIU/L—needs interpretation with free T4, symptoms, and medication history rather than automatic attribution of hand numbness to thyroid disease. Our subclinical hypothyroidism discussion explains this uncertainty; pregnancy-related carpal tunnel may improve after delivery, but persistent weakness still requires assessment rather than waiting through an assumed 6-week recovery.
Vitamin B6 supplements are not an established treatment for carpal tunnel, and excessive intake can itself cause sensory neuropathy. Kantesti can help readers put laboratory results in context, but supplement exposure often requires a separate history: add the B6 amounts across all products, including 1 multivitamin plus a B-complex, using our B-kompleks feiligensgids as a checklist.
Hoe ûndersiket in klinikus in fertochte foarm fan it karpale-tunnelsyndroom?
A clinician assesses the sensory pattern, nighttime symptoms, thumb strength, and provocative wrist maneuvers to estimate the likelihood of carpal tunnel. The 2024 AAOS guideline supports the 6-item CTS-6 clinical assessment instead of routinely using ultrasound or nerve conduction studies in a typical presentation.
Phalen’s test usually involves holding the wrist flexed for up to 60 seconds; Tinel’s sign involves tapping over the nerve to reproduce tingling. A positive result is more useful when it recreates the person’s usual median-territory symptoms, rather than merely causing local discomfort; Wipperman and Goerl’s 2016 American Family Physician review emphasizes the combined clinical picture.
De CTS-6 combines 6 findings rather than relying on a single maneuver, and a score around 12 or higher commonly supports a likely clinical diagnosis. The score is not intended as a do-it-yourself guarantee: accurate assessment of thenar weakness and two-point discrimination requires technique, and an atypical pattern can still justify further investigation despite a persuasive score.
Examination should extend beyond the wrist when 2 explanations remain plausible. Testing neck movement, reflexes, other hand muscles, and foot sensation can prevent indiscriminate laboratory testing; our guide to targeted tests for unexplained pain explains why normal inflammatory markers do not settle a nerve-localization question.
Wannear binne senuwgeliedingsûndersiken en EMG nuttich?
Nerve conduction studies help when the diagnosis is uncertain, symptoms are atypical, weakness is present, or severity will affect treatment decisions. They measure how electrical signals travel along the nerve; electromyography may be added to assess muscle involvement or look for a cervical nerve-root disorder.
A median nerve signal can be compared with an ulnar or radial nerve signal traveling a similar distance in the same hand. Differences of approximately 0.4–0.5 milliseconds may be significant in some comparison protocols, but thresholds depend on the technique; hand temperature, often kept at least 32°C, matters because cold can slow conduction and distort the interpretation.
A normal test does not completely exclude mild or intermittent carpal tunnel, and an abnormal result must still match the symptoms. There are 2 particularly useful questions for the report: does it show focal slowing across the wrist, and is there evidence of axonal loss rather than slowing alone; the latter can make persistent weakness more concerning.
The 2024 AAOS recommendation against routine testing in straightforward cases does not mean nerve studies are unnecessary before every difficult decision. Kantesti’s validation methods and limitations concern laboratory interpretation, not electrodiagnostic accuracy; a blood-test engine benchmark cannot demonstrate sensitivity for 1 compressed median nerve, and some clinicians obtain baseline studies when surgery is being considered.
Kin echografie it karpale-tunnelsyndroom befêstigje?
Ultrasound can support carpal tunnel diagnosis by showing median nerve enlargement and identifying structural contributors at the wrist. It measures anatomy rather than electrical function, so it complements—not duplicates—nerve conduction studies; routine imaging is usually unnecessary when the clinical presentation is already clear.
A median nerve cross-sectional area near or above 10 mm² at the tunnel inlet is a commonly used research and clinical threshold, but there is no universally reliable cutoff. Body size, measurement site, equipment, and local reference data matter; a value of 9.8 versus 10.2 mm² should not be treated as a sharp biological divide.
Ultrasound can identify a bifid median nerve, tendon-sheath changes, or a space-occupying structure that may alter management. A bifid nerve has 2 main divisions, so measuring only 1 can underestimate the total area; this is an example of why a technically detailed report can be more useful than its final positive-or-negative wording.
Disagreement between ultrasound and nerve conduction testing does not automatically mean that 1 test is wrong. Anatomy and function answer different questions, and our medyske rapport-feiligenschecklist encourages readers to check the original report and stated limitations; MRI is generally reserved for another suspected problem rather than routine confirmation of typical carpal tunnel.
Wat kinne jo dwaan wylst jo op in beoardieling wachtsje?
For intermittent symptoms without weakness, a neutral-position wrist splint at night and avoidance of sustained wrist bending are reasonable first steps. Arrange assessment if symptoms keep recurring, impair sleep or work, or fail to improve; constant numbness, thumb weakness, or muscle wasting should not wait for a prolonged self-care trial.
A splint should hold the wrist close to neutral, not force it backward, and its straps should not create new tingling. For mild intermittent symptoms, reviewing the response over roughly 2–6 wiken can help guide the next appointment; improvement supports a mechanical contributor but does not prove carpal tunnel, and worsening sensation or strength overrides that observation period.
A local corticosteroid injection can provide short-term symptom relief, but the 2024 AAOS guideline concludes that injections do not provide long-term improvement. Decompression may be discussed for persistent symptoms or significant neurological impairment; there is no single 3-month waiting rule that is appropriate for both intermittent tingling and progressive thumb weakness.
Kantesti is in AI-oandreaune ark foar analyse fan bloedtests, not a treatment-selection system for wrist compression, and our grinzen foar ferantwurde AI explain why clinical examination remains necessary. For repetitive tasks, try changing wrist angle and taking brief breaks every 20–30 minutes as a practical experiment—not a proven cure—and stop any exercise that consistently worsens tingling.
Hokker symptomen fan dommens yn 'e hân fereaskje driuwende soarch?
Sudden hand numbness with facial drooping, speech difficulty, new arm weakness, severe imbalance, or visual disturbance needs emergency assessment. A cold, pale, painful hand or rapidly worsening weakness also needs urgent evaluation; these are not symptoms to assume are routine carpal tunnel.
A stroke can occasionally begin with symptoms that seem confined to 1 hand, so sudden onset matters even when the usual facial or speech signs are absent. Symptoms that resolve can still represent a transient ischemic attack; seek emergency advice immediately rather than waiting until the next morning to see whether a wrist splint helps.
Rapidly progressive weakness in both legs or arms, especially after a recent illness, suggests a different neurological emergency. Our Guillain-Barré weakness warning guide explains why progression over hours to days is more concerning than a stable 2-month history of position-related fingertip tingling; breathing or swallowing difficulty warrants immediate emergency help.
Gradually developing thumb-muscle wasting is usually a prompt specialist issue rather than a stroke-style emergency, but it should not sit on a waiting list without clinical triage. Tell the service explicitly about constant numbness and new weakness, not just wrist pain; a noticeable decline over 1–2 weeks is a reason to request earlier assessment.
Undersykspublikaasjes: wat stipet dizze begelieding?
Carpal tunnel guidance should rest on condition-specific clinical evidence, not blood-test AI performance claims. As of October 22, 2026, this article draws on the 2024 AAOS guideline and published clinical reviews; the 2 Figshare records below concern separate AI engineering and deployment questions, not validation of carpal tunnel diagnosis.
De 2024 AAOS guideline supports structured clinical diagnosis and selective testing, while Padua et al. (2016) and Wipperman and Goerl (2016) explain presentation, differentials, and assessment. Thomas Klein, MD, Chief Medical Officer at Kantesti LTD, UK Company No. 17090423, is the named author for this draft; our medyske advysried describes the medical team, but this draft does not claim a completed independent review.
Multilingual AI assisted clinical decision support for early Hantavirus triage: Design, engineering validation, and real-world deployment across 50,000 interpreted blood test reports. (n.d.). Figshare. This supplied repository record addresses a different clinical topic; its title refers to 50,000 reports, which should not be treated as evidence about median nerve compression or the accuracy of a hand examination.
A pre-registered, rubric-based automated technical benchmark of the Kantesti blood-test interpretation engine on 100,000 synthetic test cases. (n.d.). Figshare. Synthetic-case performance does not establish patient diagnostic accuracy for carpal tunnel; DOI links and ResearchGate/Academia.edu discovery searches appear in the reference data below, with the 2 searches identified as discovery links rather than verified copies of either publication.
Faak stelde fragen
Ferdôvingsgefoel by it karpale-tunnelsyndroom: hokker fingers binne meastal oantaast?
Gefoelleazens fan it karpale tunnelsyndroom treft meastal de tomme, de wiisfinger, de middelfinger en de tommekant fan de ringfinger—it sintúchlike gebiet fan de medianusnerv fan likernôch 3½ fingers. De lytse finger wurdt by in isolearre karpale tunnelsyndroom meastal sparre. Soms omskriuwe minsken de hiele hân as gefoelleas, dus it beskreaune patroan is in oanwizing en gjin definitive test. In klinikus kontrolearret it gefoel, de krêft fan 'e tomme en oare senuwgebieten foardat er beslút oft fierder ûndersyk nedich is.
Kin karpaltunnelsyndroom de lytse finger beynfloedzje?
In isolearre karpaltunnel feroarsaket meastal gjin gefoelloosheid yn de lytse finger, om't de lytse finger gefoel krijt fia de nervus ulnaris. Gefoelloosheid yn de lytse finger en de neistlizzende helte fan de ringfinger wiist op kompresje fan de nervus ulnaris, faak by de earmtakke of soms by de pols. Twa senuwproblemen kinne tagelyk foarkomme, en symptomen wurde net altyd anatomysk presys beskreaun. Undersyk is nuttiger as de oarsaak ôf te lieden út mar 1 finger.
Wêrom tintelje myn hannen nachts?
Tintelingen yn 'e hân nachts kinne foarkomme as lang oanholden bûgjen fan 'e pols de druk op 'e middelste senuw yn 'e karpale tunnel fergruttet. Lang oanholden bûgjen fan 'e earmtakke kin ynstee de elleboogsenuw irritearje, benammen as de ringfinger en lytse finger troffen binne. In polsspalk dy't de pols yn in neutrale posysje hâldt, kin helpe by intermitterende symptomen yn it gebiet fan 'e middelste senuw, wylst in deiboek fan 7 nachten patroanen sjen litte kin dy't mei de lichemsposysje te krijen hawwe. Oanhâldende dommens, swakte of symptomen yn 'e fuotten moatte ûndersocht wurde ynstee fan oan te nimmen dat de sliephâlding alles ferklearret.
Haw ik senuwgeliedingsûndersyk nedich om it karpaltunnelsyndroom te diagnostisearjen?
Net elkenien hat senuwgeliedingsûndersyk nedich om karpaltunnelsyndroom te diagnostisearjen. De AAOS-rjochtline fan 2024 stipet de klinyske beoardieling CTS-6 mei 6 items ynstee fan routine-ultrasound of senuwgeliedingstests yn typyske gefallen. Senuwûndersyk is nuttich as de symptomen atypysk binne, de diagnoaze ûnwis is, der swakte oanwêzich is, of de earnst fan ynfloed is op behannelbeslissingen. In normale útslach slút lichte, intermitterende kompresje net folslein út.
Kin in bloedtest karpaletunnelsyndroom fêststelle?
Gjin bloedûndersyk kin karpaltunnelsyndroom befêstigje, om't laboratoariumtests net sjen litte oft de nervus medianus by de pols komprimearre wurdt. Selektearre tests kinne bydragende faktoaren of alternativen oan it ljocht bringe, lykas diabetes, vitamine B12-tekoart, in steurnis fan de skildklier of niersykte. In HbA1c fan op syn minst 6.5% kin in diagnoaze fan diabetes stypje as oan de easken foar befêstiging en betrouberens fan de test foldien is, mar it bewiist gjin karpaltunnelsyndroom. Tests moatte oanslute by it symptoompatroan en de medyske skiednis, ynstee fan in algemien testpanel foar in dôve hân.
Wannear moat ik my soargen meitsje oer dommens yn 'e hân en in swakke grip?
Ynienen dommens yn 'e hân mei in hingjend gesicht, spraakproblemen, nije swakte yn 'e earm of fisuele feroarings fereasket direkte medyske beoardieling yn in needgefal, ek as mar 1 hân troffen is. In kâlde, bleke, pynlike hân of rap tanimmende swakte fereasket ek driuwende beoardieling. Stadichoan ûntstiene oanhâldende dommens, muoite om de tomme tsjin de fingers te hâlden of sichtber spierferlies by de tomme freget om rappe klinyske beoardieling fanwegen mooglike wichtige senuwkompresje. Wachtsje net de folsleine proef fan 6 wiken mei in spalk ôf as de krêft of it gefoel minder wurdt.
Krij hjoed noch AI-oandreaune bloedtest-analyse
Doch mei oan mear as 2 miljoen brûkers wrâldwiid dy’t Kantesti fertrouwe foar direkte, krekte analyse fan laboratoariumtests. Upload jo bloedtest resultaten en ûntfange wiidweidige ynterpretaasje fan 15,000+-biomarkers yn sekonden.
📚 Ferwiisde ûndersykspublikaasjes
Klein, T., Mitchell, S., & Weber, H. (2026). Meartalige AI-stipe Klinyske Beslútfoarming foar Iere Hantavirus Trije: Untwerp, Yngenieursvalidaasje, en Echte Ynset oer 50.000 ynterpretearre Bloedtestrapporten. Kantesti AI Medysk Undersyk.
Klein, T., Mitchell, S., & Weber, H. (2026). In Pre-Registered, Rubric-Based Automated Technical Benchmark fan de Kantesti Blood-Test Interpretation Engine op 100.000 syntetyske testgefallen. Kantesti AI Medysk Undersyk.
📖 Eksterne medyske referinsjes
American Academy of Orthopaedic Surgeons (2024). Management of Carpal Tunnel Syndrome: Evidence-Based Clinical Practice Guideline. AAOS Clinical Practice Guideline.
Padua L et al. (2016). Carpal tunnel syndrome: clinical features, diagnosis, and management. The Lancet Neurology.
Wipperman J and Goerl K (2016). Carpal Tunnel Syndrome: Diagnosis and Management. American Family Physician.
⚕️ Medyske disclaimer
Dit artikel is allinnich foar ûnderwiisdoelen en foarmet gjin medysk advys. Rieplachtsje altyd in kwalifisearre soarchferliener foar besluten oer diagnoaze en behanneling.
E-E-A-T fertrouwensignalen
Ûnderfining
Dokter-oandreaune klinyske resinsje fan lab-ynterpretaasje-wurkprosessen.
Ekspertize
Fokus fan laboratoariummedisyne op hoe’t biomarkers har gedrage yn in klinyske kontekst.
Autoriteit
Skreaun troch dr. Thomas Klein mei resinsje troch dr. Sarah Mitchell en prof. dr. Hans Weber.
Betrouberens
Bewiis-basearre ynterpretaasje mei dúdlike ferfolchpaadkes om alarm te ferminderjen.