
New male breast enlargement may warrant testosterone, estradiol, LH, FSH and hCG testing; prolactin, SHBG and thyroid tests depend on clinical findings. Examination and medication review come first, because hormone results cannot rule out a concerning breast or testicular change.

أهم الخلاصات
- Core hormone tests may include testosterone, estradiol, LH, FSH and quantitative hCG when examination confirms unexplained glandular enlargement.
- التستوستيرون صباحًا should usually be collected around 7–10 am; diagnosing testosterone deficiency requires compatible symptoms and consistently low results on 2 separate mornings.
- استراديول commonly has an adult male reference interval around 10–40 pg/mL, but the laboratory method matters and no single cutoff diagnoses gynecomastia.
- فحوصات إضافية may include SHBG, prolactin, TSH, AFP and liver or kidney tests; a broad panel is not automatically necessary for every adolescent.
- Chest examination distinguishes a firm or rubbery subareolar disc from diffuse fat, although glandular tissue and fat can coexist.
- مراجعة الأدوية should include prescribed drugs, testosterone, anabolic steroids and supplements; do not stop essential treatment without advice.
- Pubertal enlargement often settles within approximately 1–2 years, but prepubertal onset, rapid progression or persistence beyond the expected course warrants reassessment.
- تقييم سريع is needed for a hard off-centre lump, nipple retraction or discharge, enlarged armpit nodes, or a new testicular lump; sudden severe testicular pain is an emergency.
Which hormones belong in a gynecomastia blood test?
A gynecomastia blood test may include total testosterone, estradiol, LH, FSH and quantitative hCG for unexplained glandular enlargement. SHBG, prolactin, TSH and other investigations depend on the examination, symptoms and medication history—not everyone needs the same panel.

The European Academy of Andrology guideline describes a potentially broad investigation set, including testosterone, estradiol, SHBG, LH, FSH, TSH, prolactin, hCG, AFP, liver and renal function (Kanakis et al., 2019). That is a framework for evaluating the cause, not a recommendation to purchase every assay without assessment; typical pubertal enlargement and new unexplained adult enlargement have different starting probabilities.
Testing answers 3 different questions: whether androgen activity is reduced, whether estrogen stimulation is increased, and whether a systemic illness or hormone-producing growth needs investigation. A normal estradiol result does not eliminate the first possibility, and normal testosterone does not exclude medication-related effects at the breast tissue receptor.
كانتيستي هو محلل اختبار الدم بالذكاء الاصطناعي that can help explain how these hormone results relate to one another, including why 2 testosterone measurements may be needed. Our hormone biomarker reference guide provides additional laboratory context, but neither our interpretation nor a normal panel replaces examination of a new lump.
How does examination distinguish gynecomastia from chest fat?
التثدي عند الرجال is enlargement of glandular breast tissue, usually felt as a rubbery or firm disc centred beneath the nipple. Pseudogynecomastia is predominantly diffuse fat; the 2 can coexist, so appearance or body weight alone cannot establish the diagnosis.
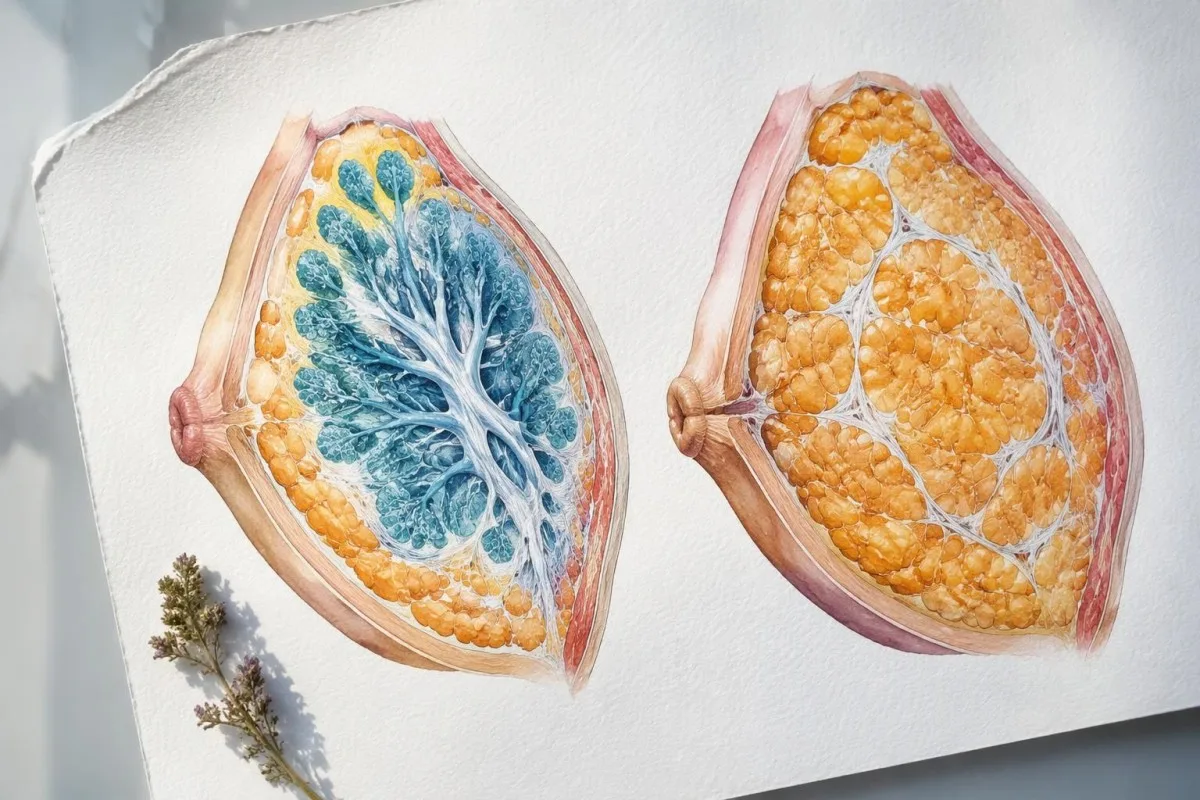
A clinician assesses the location, consistency, mobility and symmetry of the tissue, then checks the nipples and armpit nodes. For example, a hypothetical 2 cm mobile, tender subareolar disc has a different examination pattern from a 2 cm hard lump away from the nipple; size alone does not distinguish benign enlargement from cancer.
Recent glandular proliferation can be tender, whereas longstanding tissue may become firmer as fibrosis develops over months. Tenderness is therefore a clue about timing, not proof of a harmless cause; a painful lump with skin changes or rapid progression still deserves assessment, even when symptoms have lasted only 2 weeks.
Weight loss may reduce the fatty component without removing an established glandular disc, and a person can have true gynecomastia at a normal BMI. Our discussion of weight-related testing decisions explains why endocrine investigations should follow clinical clues rather than an assumption that every persistent chest change is caused by excess weight.
When does new male breast enlargement warrant hormone testing?
New unexplained adult gynecomastia, prepubertal enlargement, rapid progression or accompanying endocrine symptoms warrant clinical assessment and often targeted testing. Typical pubertal gynecomastia may instead be monitored, because it commonly improves over approximately 1–2 years without a persistent hormonal disorder.
A reassuring adolescent pattern consists of subareolar tissue arising during otherwise normal puberty, without a suspicious lump, systemic illness or abnormal genital examination. Persistence for more than about سنتين, substantial distress or continued growth merits reassessment; that interval is a practical review point, not a rule that earlier investigation is unnecessary.
Prepubertal glandular enlargement is unusual and should not be dismissed as ordinary puberty. Clinicians look for hormone exposure, unusual pubertal development and other endocrine signs; our guide to early puberty hormone testing explains why age, growth velocity and developmental stage change the meaning of an LH or testosterone result.
In an adult, reduced libido, erectile difficulties, infertility, small testes, weight loss, tremor or features of liver disease make laboratory testing more informative. The 2019 EAA guideline also advises looking for underlying disease even when a medication seems plausible, because a drug explanation and a second medical cause can occur together (Kanakis et al., 2019).
Why does medication review matter before hormone testing?
Medication-related gynecomastia may arise from reduced androgen action, altered hormone production or increased estrogen exposure. A useful review includes prescription drugs, nonprescription products and anabolic steroids, with doses and start dates; even a plausible drug cause does not cancel the need to examine a new lump.

Spironolactone, antiandrogens, finasteride, some antipsychotics and certain HIV treatments are recognised possibilities, although the strength of evidence differs between drugs. Finasteride is used at 1 mg or 5 mg daily for different indications; those doses belong in the history, but neither dose establishes causation or predicts whether an individual will develop enlargement.
Testosterone can be converted to estradiol, while stopping anabolic steroids may leave endogenous testosterone production suppressed. A hypothetical person developing tenderness 6 أسابيع after changing a testosterone regimen needs review of formulation, dose and sampling time—not an automatic aromatase inhibitor; our estradiol review during TRT explains why symptoms and numbers can disagree.
Supplements marketed as testosterone boosters may contain undeclared hormonal ingredients, so bring photographs of the packaging and a complete ingredient list. A practical history covers at least the preceding 3–6 أشهر, including stopped products; our تأثير الأدوية عند كبار السن also addresses why prescribed treatment should be adjusted with the prescriber rather than stopped independently.
How should testosterone be checked and interpreted?
التستوستيرون الكلي should usually be measured fasting in the morning, often around 7–10 am, when investigating possible deficiency. A low result requires confirmation on a separate morning, and diagnosis depends on compatible symptoms rather than breast enlargement or a single laboratory flag alone.

The Endocrine Society guideline gives a harmonised total testosterone reference interval of 264–916 ng/dL, ، تقريباً 9.2–31.8 nmol/L, for healthy, nonobese men aged 19–39 when appropriately standardised assays are used (Bhasin et al., 2018). The lower boundary is population- and method-specific; it is not a universal diagnosis threshold for every age group, laboratory or clinical situation.
منخفض أو مرتفع SHBG can make total testosterone misleading, so clinicians may request calculated free testosterone using total testosterone, SHBG and albumin, or equilibrium dialysis where available. Direct analogue free-testosterone immunoassays are less reliable; our low free testosterone explanation shows why a value such as 280 ng/dL needs its binding-protein context.
Kantesti AI can help organise 2 separate testosterone results, their collection times and the accompanying LH values, but it cannot diagnose hypogonadism from a screenshot alone. Shift workers may need sampling aligned with their main sleep period rather than a rigid clock time; our دليل جمع عينات الهرمونات الصباحية explains how sleep and recent illness affect preparation.
What do gynecomastia estradiol levels actually show?
Gynecomastia estradiol levels may be normal or elevated, because glandular growth reflects estrogen action relative to androgen action at the tissue. Many laboratories use an adult male estradiol interval around 10–40 pg/mL, but the assay-specific range—not an internet cutoff—should guide interpretation.
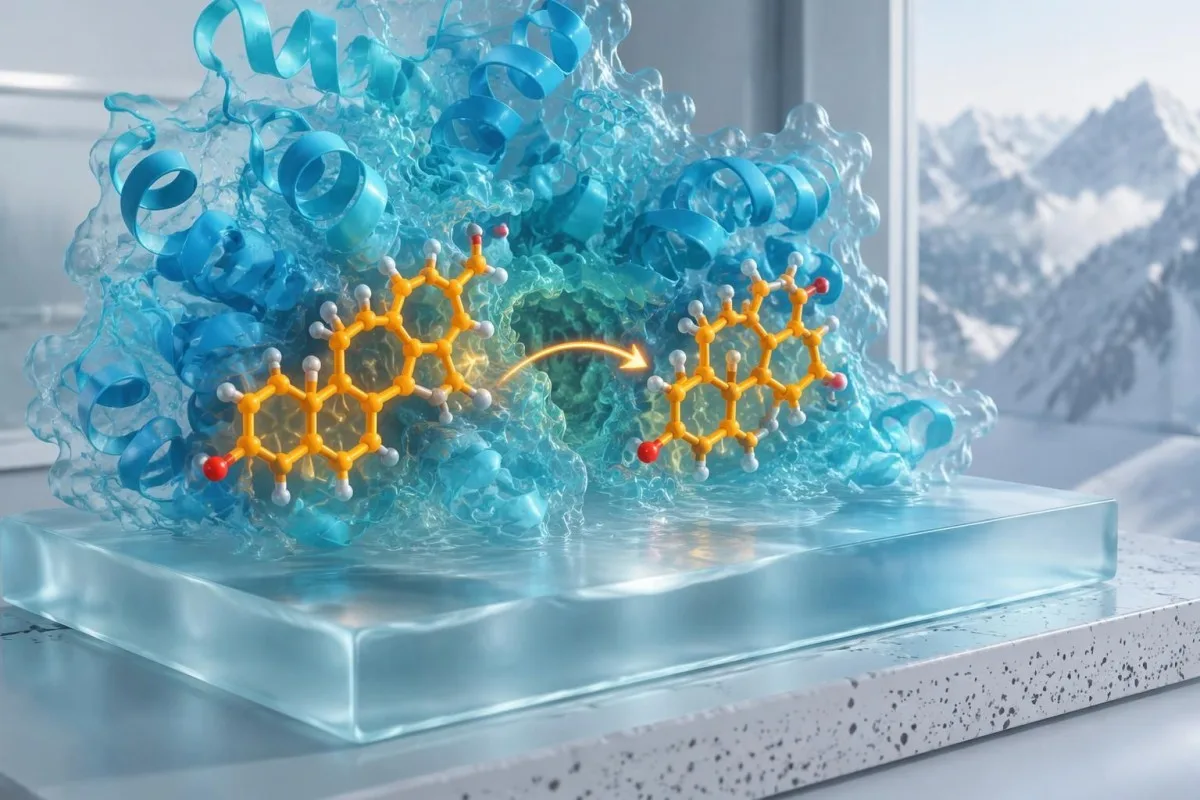
An estradiol interval of 10–40 pg/mL كيقابل تقريبا 37–147 pmol/L; converting units prevents the same result from appearing nearly 4 times higher on a different report. Some laboratories have wider intervals, and immunoassays can be less accurate at the low concentrations typical in men, so unexpected results may need confirmation with a suitably validated LC–MS/MS method.
A hypothetical estradiol result of 48 pg/mL with a laboratory upper limit of 40 is a mild elevation, not evidence by itself of a hormone-producing growth. The next questions are whether testosterone treatment, increased aromatisation, liver dysfunction or assay interference could explain it; rapid enlargement, substantially abnormal results or a testicular finding changes the urgency.
لا يوجد no validated universal estradiol-to-testosterone ratio that diagnoses gynecomastia, particularly when the hormones are reported in different units. SHBG also changes free hormone availability, which is why our SHBG والتستوستيرون is relevant; lowering estradiol solely to place a number below 40 pg/mL can create problems for bone and sexual health.
| المستوى | النطاق | شنو كتعني |
|---|---|---|
| Illustrative adult male interval | 10–40 pg/mL; approximately 37–147 pmol/L | Common laboratory interval, not universal; normal estradiol does not exclude gynecomastia. |
| Above the laboratory upper limit | For example, 48 pg/mL when the upper limit is 40 | Review medications, testosterone exposure and assay accuracy before drawing conclusions. |
| Clearly elevated and unexplained | No universal numerical threshold | Clinical findings determine confirmation, endocrine referral and investigation for a hormone-producing source. |
What do LH and FSH reveal about the underlying cause?
غالباً كيشير إلى فشل أولي فالغدد التناسلية، بينما suggests primary testicular dysfunction, while low testosterone with low or inappropriately normal LH suggests a hypothalamic–pituitary or functional cause. FSH adds information about sperm-producing function; interpreting all 3 hormones together is more useful than reading isolated reference-range flags.

Illustrative adult male intervals are LH 1.7–8.6 IU/L و FSH 1.5–12.4 IU/L, but age, assay and laboratory affect the limits. An LH of 4 IU/L may be normal when testosterone is normal yet inappropriately normal when testosterone is repeatedly very low, because the expected compensatory response is an increase in LH.
Small, firm testes, infertility and a high-gonadotropin pattern may prompt consideration of متلازمة كلاينفلتر, usually associated with a 47,XXY karyotype. Chromosome testing is not required for every person with gynecomastia; our Klinefelter chromosome testing guide explains why physical findings and reproductive history determine whether it belongs in the workup.
Low testosterone with suppressed LH and FSH may also follow anabolic steroid exposure, opioid use, severe illness or significant energy deficit. A hypothetical athlete with testosterone 190 ng/dL, ، LH 0.8 IU/L and recent steroid withdrawal has a different starting explanation from someone with the same testosterone and LH 18 IU/L; neither pattern justifies treatment without confirmation and assessment.
When should prolactin and macroprolactin be checked?
Prolactin testing is particularly useful when breast enlargement accompanies low testosterone with low or normal LH, reduced libido, nipple milk secretion or pituitary symptoms. Mild elevations should usually be reassessed in context; many adult male laboratory intervals have an upper limit around 15–20 نانوغرام/مل, but ranges vary.

Raised prolactin generally contributes indirectly by suppressing reproductive hormone signalling rather than acting as the usual direct driver of glandular enlargement. A hypothetical result of 28 نغ/مل against an upper limit of 18 may reflect stress, medication, hypothyroidism or a persistent endocrine problem; our mild prolactin elevation guide explains why one modest result rarely settles the question.
For a repeat sample, follow the laboratory's instructions and consider a quiet rest of 20–30 minutes beforehand, particularly if the first collection was stressful. A fall from 28 حتى 14 ng/mL would change the interpretation, whereas a persistent elevation requires medication and thyroid review; headaches with visual changes should be assessed promptly rather than waiting for routine retesting.
كانتيستي هو منصة تفسير تحليل الدم ديال AI that can help distinguish a total prolactin flag from a report of monomeric prolactin after laboratory processing. Persistent elevation with few compatible symptoms may lead to macroprolactin testing; our macroprolactin result explanation describes why this larger, often less biologically active complex can prevent an unnecessary leap to pituitary imaging.
Why might hCG and AFP be included in the workup?
Quantitative hCG can identify a hormone signal associated with certain testicular or other growths that may cause gynecomastia; AFP provides additional information when a germ-cell process is suspected. Neither marker is a stand-alone cancer diagnosis, and normal results do not exclude a testicular mass.

Some laboratories use an adult male hCG reference limit below 2 IU/L, while others report different cutoffs, including below 5; the exact method and reference interval must be checked. A clearly unexpected result, such as 38 IU/L in a hypothetical man without prescribed hCG, warrants prompt clinician review, confirmation and investigation rather than an assumption that the assay is only relevant to pregnancy.
A small unexpected hCG elevation can occasionally reflect assay interference, including heterophile antibodies, and clinicians may use a different analytical platform or other laboratory checks. IU/L and mIU/mL are numerically equivalent for hCG, so changing between those units does not explain a discrepancy; prescribed fertility treatment or bodybuilding-related hCG use must also be disclosed.
AFP reference limits are often around 8–10 ng/mL, but liver disease can also elevate AFP and some testicular cancers do not produce it. Our AFP interpretation and limits explains this overlap; a new testicular lump requires examination and usually ultrasound even if both hCG and AFP fall within the laboratory range.
Which thyroid, liver and kidney tests may be useful?
TSH, liver function and kidney function may help identify systemic causes of gynecomastia, particularly when symptoms or examination suggest illness. Hyperthyroidism can alter SHBG and hormone balance, while liver disease or advanced kidney disease can disrupt hormone handling; a mildly abnormal result alone rarely explains new enlargement.

A common adult TSH interval is approximately 0.4–4.0 mIU/L, although laboratories differ. A suppressed TSH with elevated free T4 or T3 supports hyperthyroidism, which can raise SHBG and shift effective androgen–estrogen balance; our TSH and thyroxine explanation helps distinguish that pattern from a single borderline TSH result.
Liver assessment may include ALT, AST, bilirubin, albumin and other tests selected for the clinical situation; normal transaminases do not exclude advanced chronic liver disease. Albumin is commonly around 35–50 g/L in adults, and our دليل تفسير بروتينات المصل explains why binding proteins and synthetic function can matter more than a small isolated enzyme rise.
Kidney tests usually begin with creatinine and estimated GFR, interpreted alongside history rather than as a direct gynecomastia test. An eGFR of 58 مل/دقيقة/1.73 م² on one occasion does not establish chronic kidney disease or explain breast enlargement; our cirrhosis symptom and laboratory guide also shows why systemic causes need a recognisable clinical pattern, not merely one abnormal number.
How should you prepare for gynecomastia hormone testing?
Preparation for gynecomastia hormone testing depends on the assays and any hormone treatment: morning fasting collection is usually appropriate for diagnostic testosterone, while treatment monitoring requires formulation-specific timing. Record the collection time, last dose and recent illness so 2 results can be compared meaningfully.
Poor sleep, acute illness and major calorie restriction can temporarily lower testosterone, so routine diagnostic testing is often deferred until recovery when clinically safe. If a hypothetical result of 220 نانوغرام/ديسيلتر was collected after an overnight shift and fever, a properly timed repeat may be more useful than immediately labelling permanent deficiency; our دليل التحضير لأخذ العينة الأولى covers what to document.
Biotin can interfere with certain immunoassays, with the direction and magnitude depending on the assay design. Supplements containing 5–10 mg, ، وهو ما يعادل 5,000–10,000 micrograms, deserve particular attention, but there is no universal safe washout period; ask the laboratory or clinician because dose, renal function and platform determine how long withholding may be required.
When reviewing results with Kantesti AI, retain the laboratory's units, reference intervals and any sample-quality comments, together with the time since the last testosterone dose. A sample collected 24 hours after an injection is not automatically comparable with one collected immediately before the next dose; unexplained discordance may require laboratory confirmation rather than a medication change.
Which breast or testicular changes need prompt evaluation?
A hard off-centre breast lump, nipple retraction or discharge, skin distortion, enlarged armpit nodes, or a new testicular lump needs prompt clinical evaluation. Do not wait for a gynecomastia blood test to reassure you; sudden severe testicular pain requires emergency care because torsion is time-sensitive.

Gynecomastia usually produces tissue centred beneath the nipple, but unilateral enlargement can still be benign and bilateral enlargement is not a guarantee of safety. A hypothetical 1 cm hard, fixed lump away from the nipple deserves a different pathway from a soft, mobile subareolar disc; blood tests cannot reliably distinguish these conditions without examination and, when needed, imaging.
When the examination is clearly typical of gynecomastia, routine breast imaging may not be necessary; an indeterminate or suspicious finding may require ultrasound, mammography and tissue sampling according to the clinical assessment. The 2019 EAA guideline supports imaging when examination is equivocal and direct tissue assessment for suspicious findings (Kanakis et al., 2019), rather than using normal estradiol as a reason to dismiss a lump.
A painless testicular lump, new firmness, size change or heaviness also deserves prompt review, while sudden severe pain should bypass routine outpatient hormone testing. Our family cancer risk testing guide explains why symptom-directed assessment differs from screening; a person with a new mass should not wait 3–6 أشهر for the next planned gynecomastia follow-up.
How do hormone patterns change the next step?
Hormone patterns guide the search for a cause; they do not choose treatment on their own. Low testosterone needs confirmation and clinical correlation, unexpected hCG needs prompt investigation, and an isolated mild estradiol rise may need review rather than suppression; the examination determines which pathway takes priority.
Consider a clearly hypothetical 52-year-old with tender subareolar tissue, testosterone 210 نغ/دL, ، LH 15 IU/L, estradiol 26 pg/mL and no suspicious mass. Repeating testosterone and assessing primary testicular dysfunction is more logical than treating normal estradiol as the problem; a low androgen signal can permit glandular enlargement even when estrogen lies inside its reference interval.
A second hypothetical adult has testosterone 520 ng/dL, estradiol 48 pg/mL and enlargement beginning after a medication change, while examination is reassuring and hCG is normal. Medication review and possible estradiol confirmation may come before treatment; if the same person instead has hCG 38 IU/L or a testicular lump, the priority changes to prompt investigation regardless of testosterone.
The EAA guideline does not recommend routine use of aromatase inhibitors, selective estrogen receptor modulators or non-aromatisable androgens for gynecomastia in general (Kanakis et al., 2019), although specialists may consider selected off-label treatment in particular circumstances. Kantesti can support discussion of 2 or more related results, ، بينما validation and clinical limits explain why an AI interpretation should not initiate testosterone, tamoxifen or estrogen-lowering medication.
Follow-up, AI limitations and research publications
Follow-up should track tissue changes and the underlying cause, not repeatedly order every hormone without a reason. A clinician may use a review interval around 3–6 أشهر for a reassuring, stable case, with earlier reassessment for progression or new breast, testicular or systemic symptoms.
A useful follow-up record includes symptom onset, medication changes, examination findings and whether a glandular disc is increasing or becoming less tender. Longstanding tissue may persist after the trigger is corrected, particularly after approximately 12 شهراً when fibrosis can limit regression; persistent discomfort or distress may justify specialist discussion even after the laboratory cause has been addressed.
كانتيستي هو أداة تحليل ديال تحاليل الدم مدعومة بالذكاء الاصطناعي that helps organise uploaded hormone reports and trends, including comparisons across 2 separate collection dates, without examining breast or testicular tissue. Kantesti LTD is the organisation behind the service, described on our company background page; انحلال الدم مبادئ الذكاء الاصطناعي المسؤول explain why new physical findings and urgent symptoms require human clinical assessment.
ال 2 منشورات Zenodo listed below are additional laboratory education resources covering iron studies and coagulation, not evidence sources for gynecomastia diagnosis or hormone treatment. The topic-specific recommendations in this article are supported by the 2019 EAA gynecomastia guideline و ال دليل جمعية الغدد الصماء لعام 2018 لهرمون التستوستيرون; a DOI identifies a deposited publication but does not, by itself, establish independent peer review or clinical validation.
أسئلة متكررة
شنو تحاليل الدم اللي خاص الراجل يدير باش يعرف واش عندو التثدي؟
تقييم التثدي عند الذكور يقدر يشمل التستوستيرون الكلي، والإستراديول، وLH وFSH وhCG الكمي، مع SHBG والبرولاكتين وTSH وAFP واختبارات الكبد أو الكلى حسب النتائج السريرية. كيوصف الدليل الإرشادي ديال الأكاديمية الأوروبية لعلم الذكورة لعام 2019 مجموعة واسعة من الفحوصات الممكنة، ولكن ماشي كل مراهق محتاج كل اختبار. كيتقاس التستوستيرون التشخيصي عادةً على الريق فالصباح، وكيتعاود القياس فصباح آخر إلا كان منخفض. الفحص ومراجعة الأدوية ضروريين، حيث تحاليل الدم ما كتقدرش تحدد جميع أسباب ظهور كتلة جديدة فالثدي.
واش ممكن يكون عندك التثدي مع مستوى عادي ديال الإستراديول؟
التثدّي يقدر يوقع حتى إلا كان الإستراديول عادي، حيت نمو الغدد كيتعلق بنشاط الإستروجين مقارنةً بنشاط الأندروجين فالنسيج. بزاف ديال المختبرات كيعتمدو مجال للإستراديول عند الرجال البالغين كيتراوح تقريباً بين 10 و40 pg/mL، ولكن النتيجة اللي داخلة فهاد المجال ما كتنفيش نقص التستوستيرون، ولا تأثيرات الأدوية، ولا حساسية النسيج. وحتى النتيجة العادية ديال الإستراديول ما كتقدرش تستبعد وجود كتلة مقلقة فالثدي. خاص العلاج يعالج السبب السريري، ماشي نفترضو أن كل حالة كتحتاج خفض الإستروجين.
واش نتيجة الإستراديول المرتفعة كتعني أنني محتاج لمثبّط الأروماتاز؟
0 الارتفاع فنتيجة الإستراديول ما كيعنيش تلقائيا أن استعمال مثبط الأروماتاز مبرر. مثلا، 48 pg/mL مقابل الحد الأعلى ديال المختبر، اللي هو 40 pg/mL، كيمثل ارتفاع خفيف، وقد يتطلب مراجعة الأدوية، وتقييم التعرض للتستوستيرون، أو التأكد باستعمال اختبار مناسب. إرشادات EAA ديال 2019 ما كتوصيش بمثبطات الأروماتاز كعلاج عام روتيني للتثدي. خفض الإستروجين بشكل مفرط يقدر يأثر سلبا على صحة العظام والوظيفة الجنسية، لذلك قرارات العلاج خاصها تكون عند طبيب.
How can I tell whether chest enlargement is fat or gynecomastia?
Gynecomastia typically feels like a rubbery or firm disc beneath the nipple, while predominantly fatty enlargement is more diffuse. Both can coexist, and a 2 cm lump cannot be classified safely from its size or a photograph alone. A clinician checks tissue location, mobility, nipple changes and armpit nodes to decide whether imaging is needed. A hard off-centre lump, nipple retraction or discharge needs prompt evaluation rather than a self-diagnosis of chest fat.
Should a teenager with gynecomastia have hormone blood tests?
A teenager with typical pubertal gynecomastia and otherwise normal development may be monitored without an extensive hormone panel. Pubertal enlargement commonly improves within approximately 1–2 years, but continued progression, persistence beyond the expected course or substantial distress warrants reassessment. Prepubertal enlargement, abnormal development, a suspicious lump or systemic symptoms should be investigated sooner. Hormone results must be interpreted using age and pubertal stage rather than adult reference ranges alone.
Can normal hormone tests rule out breast or testicular cancer?
Normal hormone tests cannot rule out breast or testicular cancer. Both hCG and AFP can be normal in a person with a testicular mass, and breast cancer may occur without abnormal testosterone or estradiol. A new hard breast lump, nipple change or testicular lump therefore needs examination and appropriate imaging regardless of the laboratory panel. Sudden severe testicular pain is an emergency and should not wait for a routine 3–6 month follow-up or laboratory appointment.
خذ شرح لنتائج تحليل الدم ديالك
حمّل تقرير التحاليل ديالك، وكيشرح AI ديال Kantesti كل مؤشر حيوي بلغة بسيطة فثواني. كايستعملوه أكثر من 2 مليون شخص فالعالم.
مراجع
- كلاين، ت.، ميتشل، س.، و ويبر، هـ. (2026). دليل دراسات الحديد: TIBC، تشبع الحديد، وقدرة الارتباط. الأبحاث الطبية ديال Kantesti AI. DOI
- كلاين، ت.، ميتشل، س.، و ويبر، هـ. (2026). aPTT: المجال الطبيعي، دليل D-Dimer وProtein C لتخثّر الدم. الأبحاث الطبية ديال Kantesti AI. DOI
- Kanakis GA et al. (2019). EAA clinical practice guidelines—gynecomastia evaluation and management. Andrology. DOI
- Bhasin S et al. (2018). Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline. The Journal of Clinical Endocrinology & Metabolism. DOI ببميد
- 2 مليون+الاختبارات المُحلَّلة
- 127+بلدان
- 100+اللغات
نبذة عن الفريق الطبي


إشارات الثقة E-E-A-T
خبرة
مراجعة سريرية يقودها الأطباء لسير عمل تفسير التحاليل.
خبرة
تركيز طب المختبر على كيفية سلوك الـ biomarkers في السياق السريري.
السلطة
راجعها طبياً الدكتور Thomas Klein، بمساهمات من الدكتورة Sarah Mitchell والأستاذ الدكتور Hans Weber.
الجدارة بالثقة
تفسير قائم على الأدلة مع مسارات متابعة واضحة لتقليل الإنذار.




إخلاء المسؤولية الطبية
هذه المقالة لأغراض تعليمية فقط ولا تشكل نصيحة طبية. استشر دائمًا مقدم رعاية صحية مؤهلًا لاتخاذ قرارات التشخيص والعلاج.
نُشر · تواصل مع فريق التحرير
منشور من طرف Kantesti Ltd، مسجل في إنجلترا وويلز، رقم الشركة. 17090423, ، لندن، المملكة المتحدة.
