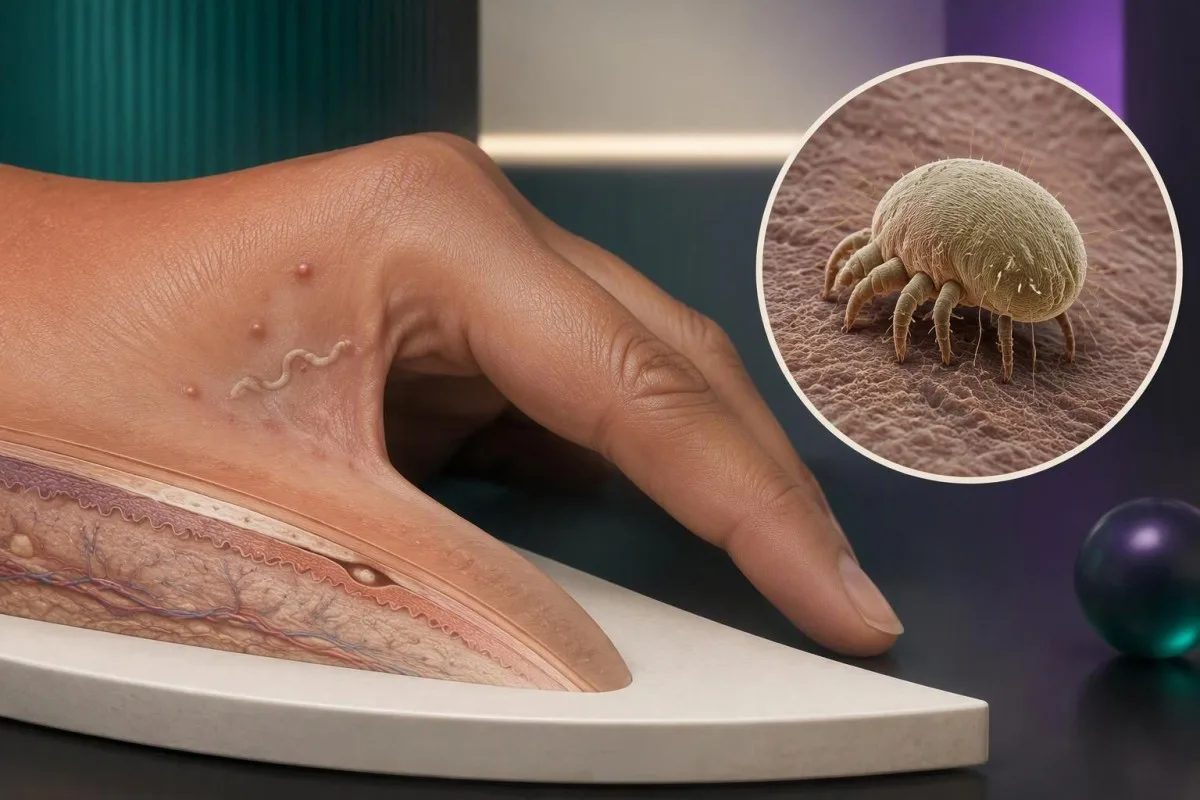
Scabies usually causes intensely itchy bumps and sometimes tiny, winding burrows, especially between the fingers and around the wrists. Itching often worsens at night, but appearance alone cannot reliably distinguish scabies from eczema or insect bites.


- Scabies symptoms usually include itchy bumps, scratch marks, and sometimes thin burrows measuring roughly 2–10 mm.
- Nighttime itching raises suspicion, especially when another household member itches, but does not establish the diagnosis.
- Early scabies symptoms may take 4–8 weeks to appear after a first infestation; someone can transmit mites before noticing symptoms.
- Typical locations include finger webs, wrists, armpits, the waist, buttocks, and genital skin; infants may also have scalp, palm, and sole involvement.
- Skin tone changes how the rash appears: pink or red bumps may look brown, purple, gray, or mainly darker than surrounding skin.
- Confirmation comes from identifying a mite, egg, or mite waste by microscopy, or directly visualizing a mite with an appropriate examination method.
- Close contacts often need coordinated treatment despite having no symptoms because delayed symptoms can otherwise allow reinfestation.
- Majibu ya matibabu is not immediate: itching can persist for 2–4 weeks, occasionally longer, after successful treatment.
- Tathmini ya haraka is needed for thick widespread crusting, rapidly worsening painful skin, or fever of 38°C or higher with an affected rash.
What does a scabies rash look and feel like?
Scabies symptoms usually include small, intensely itchy bumps, scratch marks, and occasionally narrow, winding burrows. Bumps often measure a few millimeters, while burrows may be roughly 2–10 mm long; nighttime itching and a characteristic distribution matter more than whether a rash looks exactly like an online photograph.
The scabies rash is largely an immune reaction to mites and their products, not a map of where every mite sits. Ordinary scabies often involves only about 10–15 mites, yet itching can affect much larger areas; a widespread rash therefore does not automatically mean a heavy infestation or crusted scabies.
Scratching changes the appearance within days: an initially discrete bump can become a rough patch, a small scab, or eczema-like scaling. Raised nodules, sometimes 5–10 mm across, can develop around the groin or armpits and persist after treatment, so the newest burrow is usually more diagnostically useful than the largest old bump.
Kantesti ni Mchambuzi wa mtihani wa damu wa AI, not a substitute for examining a suspicious skin eruption. I’m Dr. Thomas Klein, Chief Medical Officer; my approach is to consider 3 clues together—distribution, exposure, and examination findings—rather than label a photograph, and our organization and clinical remit explain that distinction.
When do early scabies symptoms first appear?
Early scabies symptoms often appear Wiki 4–8 after a first infestation, although the interval varies. Someone who has had scabies before may itch within 1–4 days of another exposure because the immune system recognizes the mite-related material sooner; symptoms cannot reliably identify the exact day transmission occurred.
The first noticeable change may be itch rather than an obvious rash, with just 1 or 2 bumps in a finger web or at the wrist. The World Health Organization’s scabies fact sheet describes symptoms commonly appearing after wiki 4–6; the broader practical window reflects variation in immune response and when a person first notices subtle changes (WHO, 2023).
A hypothetical scenario helps: 2 roommates develop itching three weeks apart even though both were exposed during the same period. That timing does not prove the second roommate acquired scabies later, and it certainly does not establish who introduced it; delayed symptoms make blame both medically unreliable and unhelpful.
Itching without visible burrows deserves a skin examination before a broad laboratory workup. Our guide to testing for itchy skin explains when blood tests become useful, but 0 routine blood tests are required to diagnose a typical scabies presentation; a normal panel does not exclude an infestation.
Why is scabies itching often worse at night?
Scabies itching at night reflects the skin’s immune response, with warmth under bedding and normal nighttime changes in itch perception potentially making symptoms more noticeable. Nighttime worsening is a useful clue, not a diagnostic test: eczema and other itchy disorders can also interrupt sleep for several consecutive nights.
The idea that mites emerge onto the surface every night is misleading; female mites live and lay eggs within the outer skin layer. Ordinary scabies usually carries roughly 10–15 mites, so severe itch does not require large numbers moving around, and we cannot infer mite activity from how restless someone feels at midnight.
A useful symptom record covers 3 nights: note the worst time, whether a warm shower aggravates itching, and whether new bumps appear in typical sites. I would give a new itchy finger-web track more weight than an itch score alone, because heat-sensitive nighttime symptoms occur in several conditions that do not spread between people.
Sleep loss can produce fatigue and reduced concentration before treatment begins; that is not evidence of a vitamin deficiency. Our discussion of usingizi mbaya na matokeo ya maabara addresses a separate issue, but a few disrupted nights should not automatically trigger testing when a treatable skin cause is already suspected.
What are scabies burrows, and how can you spot them?
Scabies burrows are tiny tunnels in the outermost skin layer, often appearing as thin, curved, skin-colored, grayish, or slightly darker lines about 2–10 mm long. A small darker point may sit at one end; burrows are easy to miss when scratching, eczema, or previous treatment obscures their shape.
Look first at the sides and webs of the fingers and the flexor surface of the wrists, using good side lighting rather than relying on color alone. Examining both hands is useful because a single intact track may survive on one side while scratch marks have erased comparable findings on the other.
A straight scratch is not the same as a mite tunnel: scratches usually follow a fingernail’s path, while burrows are short and may bend irregularly. Even so, 1 suspicious line is not enough for confident self-diagnosis; dermoscopy can reveal a mite at the end of a track that looks unremarkable to the unaided eye.
Do not scrape, puncture, or apply concentrated chemicals to a suspected burrow at home. A photograph taken from 2 distances, one showing location and one showing detail, can support a consultation, but our medical explanation safety guide explains why an image-based interpretation should not be mistaken for confirmed diagnosis.
Where does a scabies rash usually develop?
Scabies rash locations commonly include finger webs, wrists, elbows, armpits, the waist, buttocks, and genital skin. In otherwise healthy adults, the face and scalp are usually spared; checking both hands and wrists often provides more useful information than inspecting only the patch that happens to itch most.
A rash at the belt line can be mistaken for clothing irritation, and wrist itching can be blamed on a watch strap. The distinction becomes more persuasive when 2 or more characteristic regions are involved alongside compatible exposure; isolated irritation exactly beneath a new accessory is a different pattern, though not an absolute rule.
Genital papules or nodules can be diagnostically helpful, particularly when hand findings are subtle, but they require an appropriate private clinical examination. Scabies can spread through sexual contact without being exclusively sexually transmitted; 1 affected partner should prompt discussion of close-contact treatment rather than assumptions about other infections or relationship history.
Generalized dryness usually produces a different pattern, although dry skin and scabies can coexist. Our guide to dry skin diagnostic clues is useful when itching persists without convincing exposure or burrows, but a single normal thyroid result cannot settle whether characteristic itchy hand bumps represent scabies.
How do scabies symptoms differ across skin tones?
Scabies symptoms occur across every skin tone, but visible redness may be less obvious in deeply pigmented skin. Bumps can appear brown, purple, gray, or mainly darker than their surroundings; compare both color and texture, because raised papules, fine tracks, and distribution may be easier to recognize than redness.
In darker skin, persistent dark marks can remain after the itch improves; this post-inflammatory hyperpigmentation does not by itself indicate surviving mites. Over wiki kadhaa, distinguish flat, unchanged marks from genuinely new raised bumps or burrows, and avoid using redness as the sole measure of whether treatment worked.
Clinical lighting matters: harsh flash can flatten texture, while warm indoor lighting may change how purple or brown bumps appear. Take 2 comparison photographs in similar neutral light if your clinician recommends monitoring, keeping distance and angle consistent; otherwise apparent color changes can reflect the camera rather than the skin.
The 2020 IACS diagnostic criteria rely on examination findings, history, and exclusion of plausible alternatives—not a requirement for bright red lesions (Engelman et al., 2020). Kantesti describes its viwango vya kimatibabu na vikwazo separately; a blood-test interpretation system should not claim validated scabies recognition across skin tones without condition-specific evidence.
How can scabies look different in babies and children?
Scabies in infants and young children may involve the scalp, face, neck, palms, and soles, unlike the usual adult pattern. Small blisters can occur alongside itchy bumps; infants younger than Miezi 2 need clinician-directed treatment because age changes which products and application instructions are appropriate.
An infant cannot describe nighttime itching, so disrupted sleep, rubbing, and irritability may be the clues caregivers notice first. Those behaviors have many causes; examining viganja na nyayo and asking whether a caregiver has new itch is more informative than attributing several unsettled nights to scabies without looking at the skin.
Household patterns can be asymmetric: a child may have obvious palm bumps while an adult caregiver has only 1 subtle wrist burrow. Treatment instructions must still be individualized, particularly regarding the scalp, face, skin folds, and avoiding the eyes and mouth; do not simply copy an adult’s application plan for a baby.
Oral ivermectin is not routinely recommended in children weighing less than 15 kg, although specialist practice and evidence continue to evolve. Our guide to mipaka ya tafsiri ya AI ya watoto makes a related distinction: interpreting a laboratory result is not the same as selecting an age-appropriate treatment for a contagious skin condition.
How can you distinguish scabies from eczema?
Scabies is more likely than eczema when new itching follows close contact, several people itch, or examination finds burrows in characteristic locations. Eczema more often follows a recurrent dry-skin or trigger-related pattern, but both conditions can coexist, and neither nighttime itching nor a temporary response to steroid cream reliably separates them.
Steroid cream can reduce the visible immune reaction without eliminating mites, making scabies harder to recognize—a presentation sometimes called scabies incognito. If itching recurs after 1 short steroid course, the next step is reassessment of the diagnosis and application history, not automatically prescribing a stronger steroid or assuming the patient used it incorrectly.
An elevated IgE level does not distinguish scabies from eczema because allergic conditions and some parasitic disorders can both raise IgE. Our explanation of high IgE interpretation covers that overlap; 1 abnormal IgE result cannot identify a skin mite, establish contagiousness, or justify treating an entire household.
Contact eczema often matches where a substance touches the skin, such as a glove edge or a new cleaning product, whereas scabies may appear at several characteristic sites. Our guide to component allergy testing discusses selected IgE-mediated allergies, but that testing does not diagnose scabies or replace patch testing when contact allergy is the concern.
How does scabies differ from bedbug or flea bites?
Scabies differs from insect bites because mites live in the outer skin layer and can produce burrows, while bedbugs and fleas bite from the environment. Bite clusters on uncovered skin or around the ankles may suggest another cause, but a line of 3 bumps is not a reliable diagnostic signature of bedbugs.
Bedbug reactions can appear after sleep, so nighttime symptoms alone do not distinguish the conditions. Think about 2 different exposure routes: prolonged skin contact favors scabies, while evidence of insects in bedding favors bites; neither route proves the diagnosis, and a shared room can expose several people without direct transmission between them.
New bumps despite changing bedding do not prove resistant scabies, and improvement after leaving a room does not prove bedbugs. Delayed bite reactions and lingering scabies-related itch both complicate the timeline; a 7-day location-and-exposure diary can help your clinician identify whether new lesions follow a place, a contact, or neither.
Widespread blisters with fever need assessment for other conditions rather than being labeled bites; varicella, for example, follows a different clinical pattern. Our guide to varicella immunity results explains prior immunity testing, but 1 positive immunity result is not a diagnostic explanation for every new blistering rash or a substitute for examining it.
How do clinicians confirm a scabies diagnosis?
Clinicians confirm scabies by identifying mites, eggs, or mite waste on microscopy, or by directly visualizing a mite with an appropriate method such as dermoscopy. A negative scraping does not exclude scabies: ordinary cases may contain only 10–15 mites, and the sampled area may simply miss them.
The 2020 International Alliance for the Control of Scabies criteria distinguish confirmed, clinical, and suspected scabies, with different combinations of examination findings and history (Engelman et al., 2020). These are 3 diagnostic categories, not three levels of symptom severity; a clinician may reasonably treat a convincing clinical presentation even when direct visualization has not succeeded.
Sampling an intact, recent burrow is more useful than sampling a heavily scratched patch, and a second targeted examination can resolve an initially inconclusive visit. An eosinophil count above approximately 0.5 × 10⁹/L is nonspecific and does not confirm scabies; our guide to eosinophil-related symptoms and counts explains why many causes remain possible.
Kantesti ni jukwaa la tafsiri ya vipimo vya damu la AI that can explain laboratory findings, but no routine CBC pattern confirms or excludes scabies. Our mwongozo wa marejeo wa viashiria vya damu addresses laboratory interpretation; 0 routine blood biomarkers directly demonstrate the mite, so an upload should not delay examination or coordinated treatment when clinical suspicion is high.
Why do close contacts need treatment without symptoms?
Close contacts may need scabies treatment without symptoms because a first infestation can remain unnoticed for Wiki 4–8 while transmission is possible. Once scabies is diagnosed or strongly suspected, household members, sexual partners, and other relevant close skin contacts commonly need a coordinated plan rather than waiting until each person starts itching.
Ordinary scabies usually spreads through prolonged direct skin contact, not a brief greeting, and contact definitions should follow local clinical guidance. A clinician may ask about contacts over the preceding wiki 6–8; the exact look-back period and who qualifies vary, particularly in care facilities or when crusted scabies makes shorter contact and contaminated materials more consequential.
Treating just 1 symptomatic person can leave an unnoticed household infestation in place and lead to reinfestation after otherwise correct treatment. The European guideline emphasizes contact management alongside therapy (Salavastru et al., 2017); our family health coordination guide addresses organizing care while respecting each adult’s privacy and consent.
Kantesti’s family tools are not scabies contact tracing, and an asymptomatic contact does not need a blood-test bundle to decide whether exposure treatment is appropriate. Our discussion of risk-based family health checks separates preventive testing from exposure management; agree 1 shared treatment start date with the prescribing clinician and give each person their own instructions.
How long can itching last after scabies treatment?
Itching can continue for 2–4 weeks after successful scabies treatment, and occasionally longer, because the immune reaction settles more slowly than mites are eliminated. Persistent itch alone does not prove treatment failure; genuinely new burrows, missed application areas, untreated contacts, and reinfestation are more useful reasons to reassess.
A commonly used regimen is permethrin 5% cream, left on for 8–14 hours and repeated approximately siku 7 later, according to prescribing instructions. Oral ivermectin, when appropriate, is commonly given at 200 micrograms/kg in two doses siku 7–14 apart; pregnancy, body weight, other medicines, and local guidance affect selection (Salavastru et al., 2017).
Application details can explain apparent failure: finger webs, under the nails, skin folds, and areas washed during the treatment interval may be missed. Older adults may need help reaching affected areas and a medication review before oral therapy; our guide to medication effects in older adults discusses broader safety issues, not a requirement for routine scabies laboratory monitoring.
For ordinary scabies, clean clothing, towels, and bedding used during the preceding siku 3, following local advice; temperatures above 50°C for 10 minutes kill mites and eggs. Nonwashable items can usually be sealed for at least saa 72, sometimes up to a week depending on guidance, while excessive daily chemical spraying can irritate skin and prolong itching.
Which symptoms need urgent care rather than a routine rash visit?
Urgent assessment is needed for thick widespread crusting, rapidly spreading painful skin changes, or fever of 38°C au zaidi with a worsening rash. Crusted scabies can cause surprisingly little itch despite a very high mite burden, especially in people who are immunocompromised, frail, or unable to scratch normally.
Pain, warmth, expanding redness or darker discoloration, and drainage can indicate secondary bacterial infection rather than uncomplicated scabies alone. Seek same-day help when those changes progress over hours to a day; severe weakness, confusion, breathing difficulty, or fainting requires emergency care, and our guide to WBC and CRP disagreement explains why normal markers cannot override concerning symptoms.
Pregnancy creates a separate safety issue: itching of the palms and soles without a primary rash can require prompt assessment for intrahepatic cholestasis, even if scabies is also being considered. Our guide to bile acids and pregnancy itching explains that pathway; 1 reassuring skin photograph should not postpone maternity advice for new unexplained itching.
Kantesti ni Zana ya uchambuzi wa vipimo vya damu inayotumia AI that may help explain results obtained for a separate medical concern; it cannot assess household transmission from a CBC. As of October 3, 2026, the practical distinction remains the same: scabies requires skin-focused assessment, while systemic symptoms or an atypical itch pattern may justify additional testing for another condition.
What should you bring to a visit, and which evidence applies?
Bring an exposure timeline, photographs, and a list of products already used to a scabies assessment. A record covering the previous wiki 6–8, including who else itches and when treatment was applied, can help distinguish delayed symptoms, an incorrect diagnosis, incomplete treatment, and reinfestation without relying on speculative laboratory explanations.
Ask 3 practical questions before leaving: how confident is the diagnosis, which contacts need treatment, and what specific finding should trigger reassessment? This article is presented in the editorial voice of Thomas Klein, MD, Chief Medical Officer; oversight roles are described on our ukurasa wa ushauri wa kamati ya matibabu, which should not be confused with documentation of an individual examination or named review of this draft.
The directly relevant evidence consists of the 2020 IACS diagnostic criteria, vya 2017 European management guideline, and WHO’s scabies guidance. Those sources support the distinctions between confirmation, clinical suspicion, and contact management; laboratory interpretation publications address a different question and should not be cited as evidence that a blood panel diagnoses scabies.
Kantesti’s related reading includes our wa tafsiri ya urinalysis na iron studies interpretation guide, huku 2 supplied Zenodo DOI records listed below. Neither publication establishes scabies diagnostic accuracy or treatment effectiveness; the ResearchGate and Academia.edu links are title-search links for discovery, not assertions that verified copies exist on those services.
Maswali Yanayoulizwa Mara Kwa Mara
Dalili za awali za mbung'oto ni zipi?
The first signs of scabies are often itching and a few small bumps in finger webs, around the wrists, or at other characteristic sites. Symptoms after a first infestation commonly take 4–8 weeks to appear, so a recent-looking rash may reflect an older exposure. Someone who has had scabies before may develop symptoms within 1–4 days. A clinician should assess the distribution and contact history because early scabies can resemble eczema or insect bites.
Does scabies always itch worse at night?
Scabies often itches worse at night, but nighttime worsening is not universal and does not confirm the diagnosis. Eczema and several other skin disorders can also disturb sleep. A 3-night symptom record can help describe the pattern, especially when paired with information about new bumps and close contacts. Crusted scabies may cause little itching despite being highly contagious.
Can you have scabies without seeing burrows?
Scabies can be present without visible burrows because tracks may be subtle, scratched away, or obscured by eczema-like changes. Burrows are often only about 2–10 mm long. Dermoscopy or targeted microscopy can help identify mites, but a negative scraping does not exclude scabies. Clinicians may make a clinical diagnosis when the examination and exposure history fit and other explanations are less likely.
What does scabies look like on darker skin?
Scabies on darker skin may appear as brown, purple, gray, or darker-than-surrounding bumps rather than bright redness. Raised texture, short winding tracks, and characteristic locations remain useful clues. Dark marks can persist for several weeks after treatment and do not alone mean mites remain alive. New burrows or genuinely new raised bumps are more concerning than stable, flat pigmentation.
Can a blood test diagnose scabies?
No routine blood test confirms or excludes scabies. A raised eosinophil count, sometimes defined as above approximately 0.5 × 10⁹/L depending on the laboratory, can have many causes and does not identify a skin mite. Confirmation requires direct identification of a mite, egg, or mite waste with an appropriate examination method. Blood tests may be useful for a different suspected cause of itching or a complication, not as a replacement for skin assessment.
Should everyone in the house be treated for scabies?
Household members and other relevant close contacts commonly need coordinated treatment when scabies is diagnosed or strongly suspected, even without itching. A first infestation can remain symptom-free for 4–8 weeks while transmission is possible. Who needs treatment depends on the type of contact, local guidance, and whether crusted scabies is involved. A clinician or pharmacist should provide an individual regimen rather than having everyone share one person’s prescription.
How do I know whether scabies treatment worked?
Successful scabies treatment does not always stop itching immediately; itch commonly persists for 2–4 weeks and occasionally longer. Improvement without new burrows supports recovery, while new tracks, untreated contacts, or incomplete application warrant reassessment. A commonly prescribed permethrin regimen includes a second application about 7 days after the first, following product and clinician instructions. Seek follow-up if itching remains substantial after 2–4 weeks, worsens, or is accompanied by new lesions rather than repeatedly applying treatment without advice.
Pata Uchambuzi wa Vipimo vya Damu kwa AI Leo
Jiunge na zaidi ya watumiaji 2 milioni duniani kote wanaoamini Kantesti kwa uchambuzi wa papo hapo na sahihi wa vipimo vya maabara. Pakia matokeo yako ya vipimo vya damu na upate tafsiri ya kina ya viashiria vya 15,000+ ndani ya sekunde.
📚 Machapisho ya Utafiti Yanayorejelewa
Klein, T., Mitchell, S., & Weber, H. (2026). Kipimo cha Urobilinogen kwenye Mkojo: Mwongozo Kamili wa Uchambuzi wa Mkojo 2026. Kantesti uchambuzi wa damu kwa AI ya utafiti wa matibabu.
Klein, T., Mitchell, S., & Weber, H. (2026). Mwongozo wa Uchunguzi wa Chuma: TIBC, Kueneza Chuma na Uwezo wa Kufunga. Kantesti uchambuzi wa damu kwa AI ya utafiti wa matibabu.
📖 Marejeo ya Nje ya Tiba
Engelman D et al. (2020). The 2020 International Alliance for the Control of Scabies Consensus Criteria for the Diagnosis of Scabies. Jarida la Kimatibabu la Uingereza la Ngozi (British Journal of Dermatology).
Salavastru CM et al. (2017). European guideline for the management of scabies.0. . Jarida la Chuo Kikuu cha Ulaya cha Dermatology na Venereology.
Shirika la Afya Duniani (2023). mba. WHO Fact Sheets.
⚕️ Kanusho la Kimatibabu
Makala haya ni kwa madhumuni ya elimu tu na si ushauri wa kimatibabu. Wasiliana na mtoa huduma aliyehitimu kila wakati kwa maamuzi ya utambuzi na matibabu.
E-E-A-T Trust Signals
Uzoefu
Mapitio ya kimatibabu inayoongozwa na daktari ya mifumo ya tafsiri ya maabara.
Utaalamu
Kuzingatia dawa za maabara kuhusu jinsi viashiria (biomarkers) vinavyobadilika katika muktadha wa kliniki.
Mamlaka
Imeandikwa na Dk. Thomas Klein kwa mapitio ya Dk. Sarah Mitchell na Prof. Dk. Hans Weber.
Uaminifu
Tafsiri inayotegemea ushahidi yenye njia zilizo wazi za ufuatiliaji ili kupunguza tahadhari za hofu.