
An adrenal mass found unexpectedly is usually benign, but its scan pattern, size and hormone activity determine what happens next.

핵심 요점
- 정의 An adrenal incidentaloma is an adrenal mass, usually at least 1 cm, discovered during imaging performed for another reason.
- 영상검사 A homogeneous adrenal mass measuring 10 Hounsfield units or less on unenhanced CT is usually a benign lipid-rich adenoma.
- 코르티솔 A 1 mg overnight dexamethasone suppression test with cortisol above 1.8 micrograms/dL, or 50 nmol/L, may indicate mild autonomous cortisol secretion.
- Metanephrines Plasma free or urinary fractionated metanephrines are generally tested when the mass is not clearly a benign low-density adenoma.
- 알도스테론 The aldosterone-to-renin ratio is appropriate when hypertension or unexplained low potassium raises concern for primary aldosteronism.
- 후속 A homogeneous mass at 10 HU or less often needs no repeat imaging, while indeterminate lesions commonly require repeat CT or MRI at 6 to 12 months.
- 긴급도 Severe episodic headache with palpitations and sweating, marked blood-pressure elevation, fainting, new virilization or sudden abdominal pain requires prompt medical review.
What an adrenal incidentaloma means
An adrenal incidentaloma is an unexpectedly discovered adrenal mass that needs two parallel checks: whether it produces hormones and whether its imaging looks dangerous. Most are benign adenomas, but the next step depends on the CT density, homogeneity, size, growth and clinical context rather than the word mass alone.
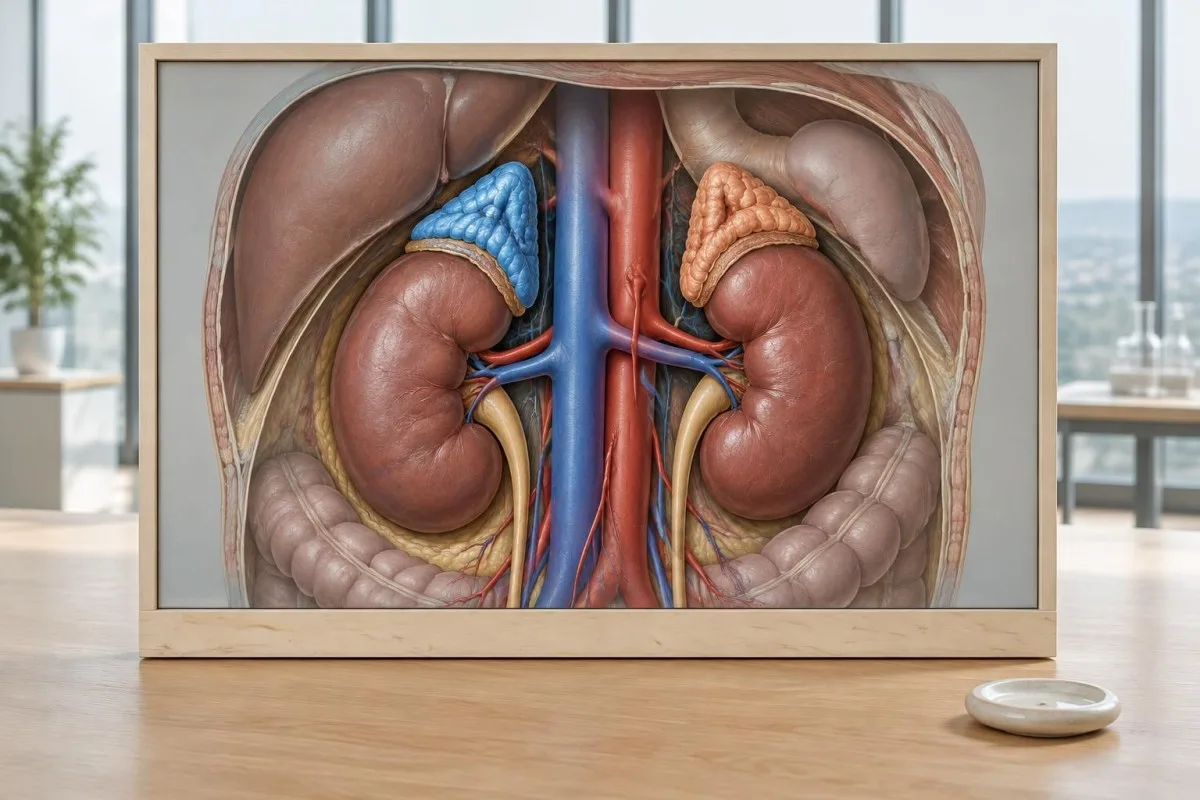
An adrenal incidentaloma is generally a lesion at least 1 cm that was found on CT, MRI or another scan performed for a different problem. The 2023 European Society of Endocrinology guideline recommends assessing imaging appearance and hormone secretion even when the person has no adrenal symptoms (Fassnacht et al., 2023).
The first clinical question is whether the mass is functioning. Excess cortisol, catecholamines or aldosterone can affect blood pressure, glucose, potassium and bone health long before symptoms become obvious; a normal-looking scan does not prove that hormone production is normal.
Kantesti is an AI blood test analyzer that organizes cortisol, metanephrine-related results, potassium and glucose into a trend view, but it cannot replace adrenal imaging or specialist interpretation. Uploading laboratory data can help you prepare a focused list of questions, especially when results were reported in different units.
How clinicians read the original adrenal scan
Clinicians first confirm that the mass truly arises from the adrenal gland and then review unenhanced CT density, homogeneity, borders and contrast behavior. A radiology report that says only adrenal nodule is incomplete for risk assessment; the actual Hounsfield-unit value and lesion size matter.
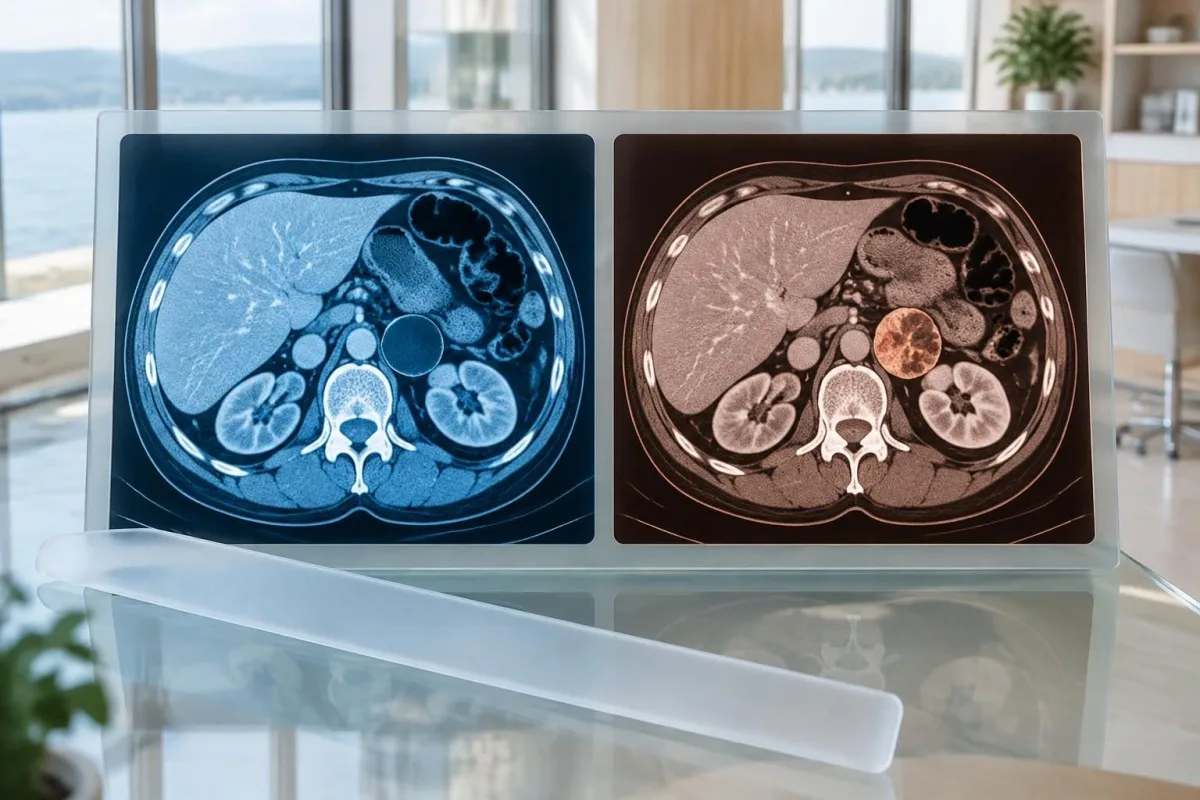
The most useful first imaging number is the unenhanced CT attenuation in Hounsfield units, or HU. A homogeneous adrenal mass measuring 10 HU or less is usually a lipid-rich adenoma, whereas a value above 10 HU is indeterminate rather than automatically cancerous.
Radiologists also assess whether the mass is homogeneous or heterogeneous, smooth or irregular, and whether it contains fat, calcification, hemorrhagic change or invasion into nearby structures. MRI chemical-shift imaging can support an adenoma diagnosis when CT is inconclusive, but MRI signal loss is not interchangeable with a CT HU result.
Ask for the original report and, when possible, the actual images; a 2.8 cm mass described as 8 HU is clinically different from a 2.8 cm mass described as 28 HU. Our 바이오마커 가이드 can help explain accompanying laboratory markers, although it does not interpret the scan itself.
Which size and density features raise concern?
Size and density are combined, not read in isolation. A homogeneous mass at 10 HU or less is usually low risk regardless of size, while a heterogeneous mass at least 4 cm or a lesion above 20 HU deserves multidisciplinary specialist assessment because the chance of malignancy is higher.
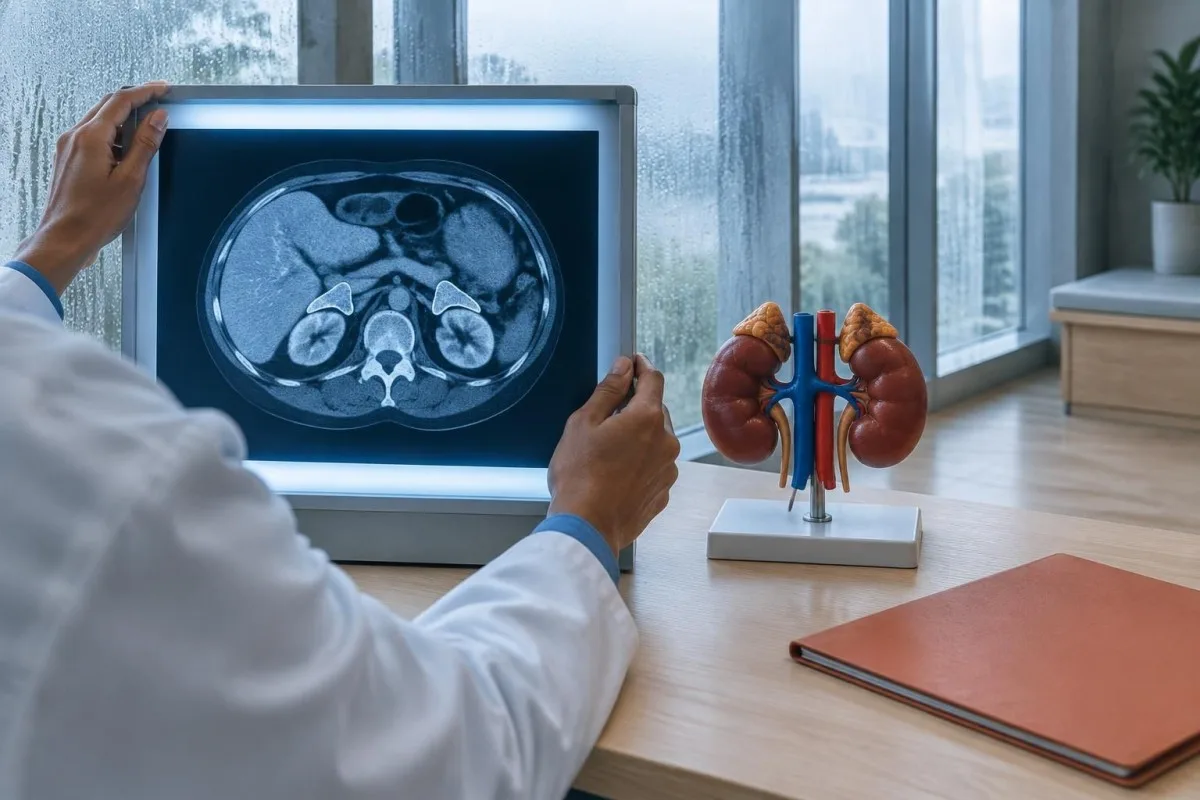
A lesion measuring 11 to 20 HU and smaller than 4 cm is often classed as indeterminate, not malignant. The 2023 guideline favors immediate additional imaging when available; if the diagnosis remains uncertain, repeat noncontrast CT or MRI after roughly 12 months may be considered.
A mass measuring at least 4 cm with heterogeneous appearance or unenhanced density above 20 HU has a sufficiently higher concern profile to justify discussion by an endocrine, radiology and surgical team. Size alone is not a diagnosis: a homogeneous 5 cm low-HU mass may be less worrying than a rapidly changing 2.5 cm heterogeneous mass.
Growth is meaningful when it exceeds 20% in maximum diameter and at least 5 mm during follow-up, although measurement error can complicate small lesions. The 코르티솔 참조 가이드 explains why scan risk and hormone results must be integrated rather than compared as separate checklists.
| 수준 | 범위 | 의미 |
|---|---|---|
| Typical benign pattern | Homogeneous and ≤10 HU | Usually a lipid-rich adenoma; no repeat imaging is often needed. |
| Indeterminate pattern | 11-20 HU and <4 cm | Consider additional imaging or repeat noncontrast CT or MRI within about 12 months. |
| 더 높은 위험 패턴 | >20 HU or heterogeneous | Prompt endocrine or multidisciplinary review is appropriate, especially when 4 cm or larger. |
| Suspicious progression | Growth >20% and ≥5 mm | Significant interval growth warrants specialist reassessment and often treatment planning. |
Which adrenal mass hormone tests come next?
Most adults with an adrenal incidentaloma receive a hormone screen for autonomous cortisol production, with metanephrines and aldosterone testing added according to the scan and clinical findings. The exact panel is individualized; ordering every adrenal hormone test for everyone can create false positives and confusing follow-up.
The usual first-line screen includes a 1 mg 야간 덱사메타손 억제검사, with blood cortisol measured the next morning. Plasma free or urinary fractionated metanephrines are considered when the lesion is not clearly a benign low-density adenoma, while an aldosterone-to-renin ratio is used when hypertension or low potassium is present.
A cortisol value of 1.8 micrograms/dL, equivalent to 50 nmol/L, or lower after dexamethasone generally excludes autonomous cortisol secretion. Values above that threshold require context, medication review and often confirmation of adrenocorticotropic hormone suppression; the cutoff identifies risk but does not by itself prove overt Cushing syndrome.
Kantesti is an AI blood test interpretation platform that can place cortisol, glucose, potassium and blood-pressure-related laboratory results beside their collection dates. Our AI 기술 가이드 explains why an algorithm can organize results while the decision to test or operate still belongs to a qualified clinical team.
How clinicians screen for excess cortisol
The 1 mg dexamethasone suppression test is the standard initial screen for mild autonomous cortisol secretion from an adrenal incidentaloma. Dexamethasone should suppress morning cortisol in most people; a result above 1.8 micrograms/dL, or 50 nmol/L, prompts a closer assessment rather than an automatic diagnosis.

Mild autonomous cortisol secretion can occur without the purple stretch marks, muscle weakness or classic appearance associated with overt Cushing syndrome. Clinicians look for related conditions such as hypertension, type 2 diabetes, osteoporosis or unexplained vertebral fractures because even modest cortisol excess may worsen these risks over time.
The result can be distorted by estrogen-containing medicines, some anti-seizure drugs, rifampicin, poor dexamethasone absorption and inconsistent sampling. A hypothetical example is a 55-year-old taking oral estrogen whose post-dexamethasone cortisol is 2.4 micrograms/dL; that result deserves medication-aware review, not immediate surgery.
A low or suppressed ACTH level supports adrenal autonomy, while repeat dexamethasone testing or another cortisol assessment may be used when the result is borderline. Our guide to Cushing syndrome tests explains why one abnormal cortisol value cannot establish the full syndrome.
When metanephrines are needed
Metanephrine testing looks for pheochromocytoma, a catecholamine-producing adrenal tumour, and is most relevant when imaging is indeterminate or symptoms suggest catecholamine excess. Plasma free metanephrines or 24-hour urinary fractionated metanephrines are preferred tests; a result more than 3 times the laboratory upper limit is particularly concerning.

The 2023 European guideline allows clinicians to omit metanephrines when a mass has a homogeneous unenhanced density of 10 HU or less, because pheochromocytoma is very unlikely in that imaging pattern. Testing remains appropriate for higher-density lesions, atypical masses or symptoms such as episodic headache, palpitations, sweating and blood-pressure surges.
Patient preparation affects the result. Acute illness, strenuous exercise, caffeine, nicotine, some antidepressants and improper posture can increase plasma metanephrines, while collecting blood after at least 20 minutes of quiet supine rest can reduce false positives in many laboratories.
The Endocrine Society guideline recommends biochemical testing before invasive procedures or adrenal surgery when pheochromocytoma has not been excluded (Lenders et al., 2014). Read our explanation of pheochromocytoma symptoms if the scan finding accompanies episodic cardiovascular symptoms.
When aldosterone and renin should be measured
The aldosterone-to-renin ratio is recommended when an adrenal incidentaloma occurs with hypertension or unexplained low potassium. It screens for primary aldosteronism, but the ratio has no universal cutoff because assays, units, posture, sodium intake and medicines change the result.
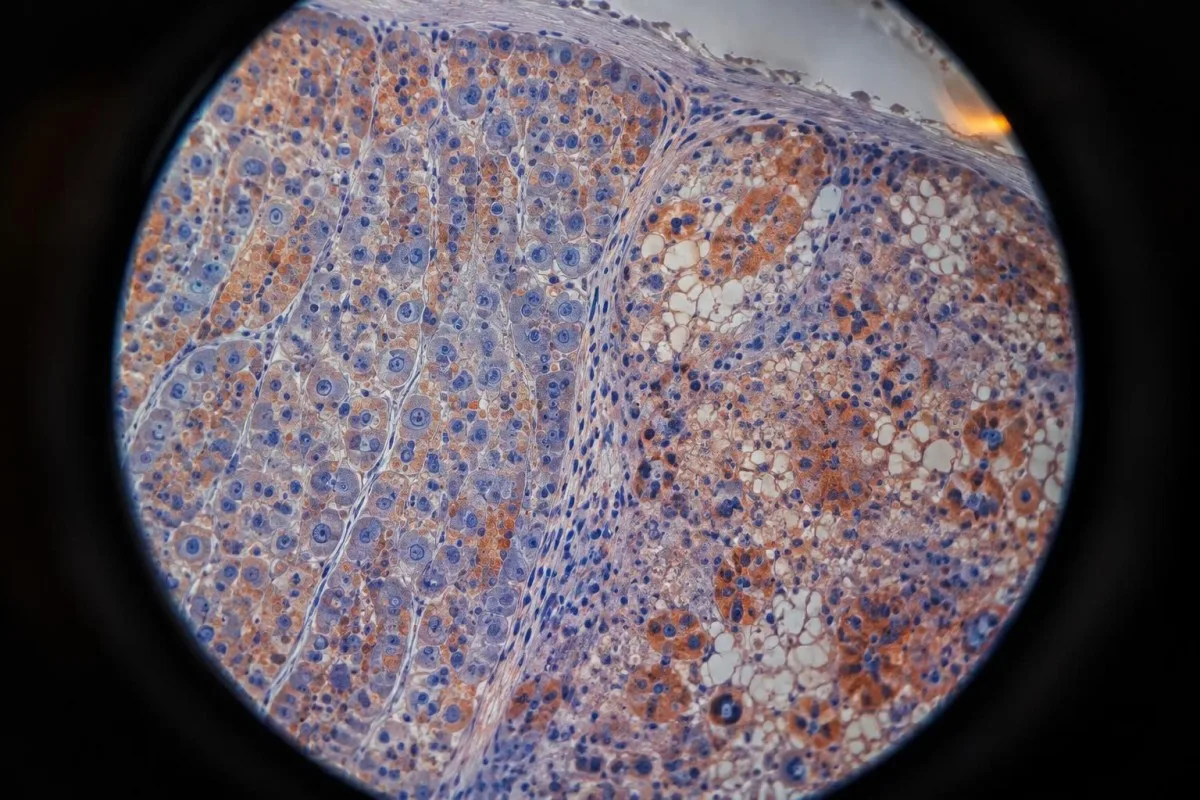
Aldosterone excess promotes sodium retention and potassium loss, so clinicians usually review blood pressure, potassium, bicarbonate, kidney function and renin together. A potassium concentration below 3.5 mmol/L is commonly considered low in adults, although laboratory intervals differ and a normal potassium value does not exclude primary aldosteronism.
Beta blockers can suppress renin and falsely raise the ratio, while mineralocorticoid receptor antagonists may alter both hormones substantially. A hypothetical patient with blood pressure of 168/96 mmHg and potassium of 3.1 mmol/L needs medication-aware testing rather than a ratio interpreted from a generic internet cutoff.
A positive screen is usually followed by repeat testing, confirmatory suppression testing or specialist assessment; surgery is considered only after subtype evaluation. The related guide to urine sodium results explains why sodium handling is informative but cannot substitute for an aldosterone-renin workup.
When adrenal androgen testing matters
DHEA-S, testosterone, estradiol or other sex-steroid tests are not routine for every adrenal incidentaloma; they are targeted to virilization, feminization or imaging that suggests an adrenal cortical malignancy. Rapidly progressive hormone-related physical changes make specialist review more urgent than a mild isolated laboratory abnormality.

Markedly elevated DHEA-S, rapid facial-hair growth, deepening voice, new severe acne or menstrual disruption can suggest androgen production from an adrenal source. In men, new breast enlargement or reduced libido may prompt broader endocrine testing, but these symptoms are nonspecific and do not identify the adrenal gland by themselves.
DHEA-S is age-dependent and can be influenced by supplements, exogenous hormones and laboratory method. A value mildly above a local reference range is less concerning than a rapidly rising result several times the upper limit, especially when the CT appearance is heterogeneous or the mass grows.
Kantesti AI can organize DHEA-S, testosterone and related results by date, but the platform cannot determine whether a hormone came from the adrenal gland, gonads or medication. Our article on low DHEA causes explains why both high and low results need clinical context.
How medicines and collection conditions alter results
Adrenal hormone results can be misleading when collection timing, posture, medication use or assay interference is ignored. Before repeating a cortisol, metanephrine or aldosterone test, clinicians review the exact dose, collection time, recent illness and laboratory method rather than simply ordering the same panel again.
The dexamethasone suppression test depends on taking 1 mg at the prescribed evening time and collecting cortisol the following morning. Oral estrogen can raise cortisol-binding globulin and total cortisol, while drugs such as carbamazepine, phenytoin and rifampicin can increase dexamethasone breakdown and weaken suppression.
Plasma metanephrines are sensitive to posture and stress, and urinary collections depend on a complete 24-hour sample. A borderline result only 1.2 times the upper limit after poor sleep, caffeine and an upright blood draw is not equivalent to a result 4 times the upper limit collected under controlled conditions.
Fasting is not universally required for every adrenal test, but some laboratories request it or specify restrictions for accompanying glucose and lipid measurements. The practical guide to fasting on a lab order helps distinguish a laboratory instruction from a blanket rule.
How often an adrenal mass is rechecked
Follow-up imaging depends on the initial CT pattern: a homogeneous mass at 10 HU or less often needs no repeat scan, while an indeterminate mass commonly receives repeat CT or MRI at 6 to 12 months. Repeating imaging too frequently adds radiation or cost without improving decisions when the lesion is already convincingly benign.
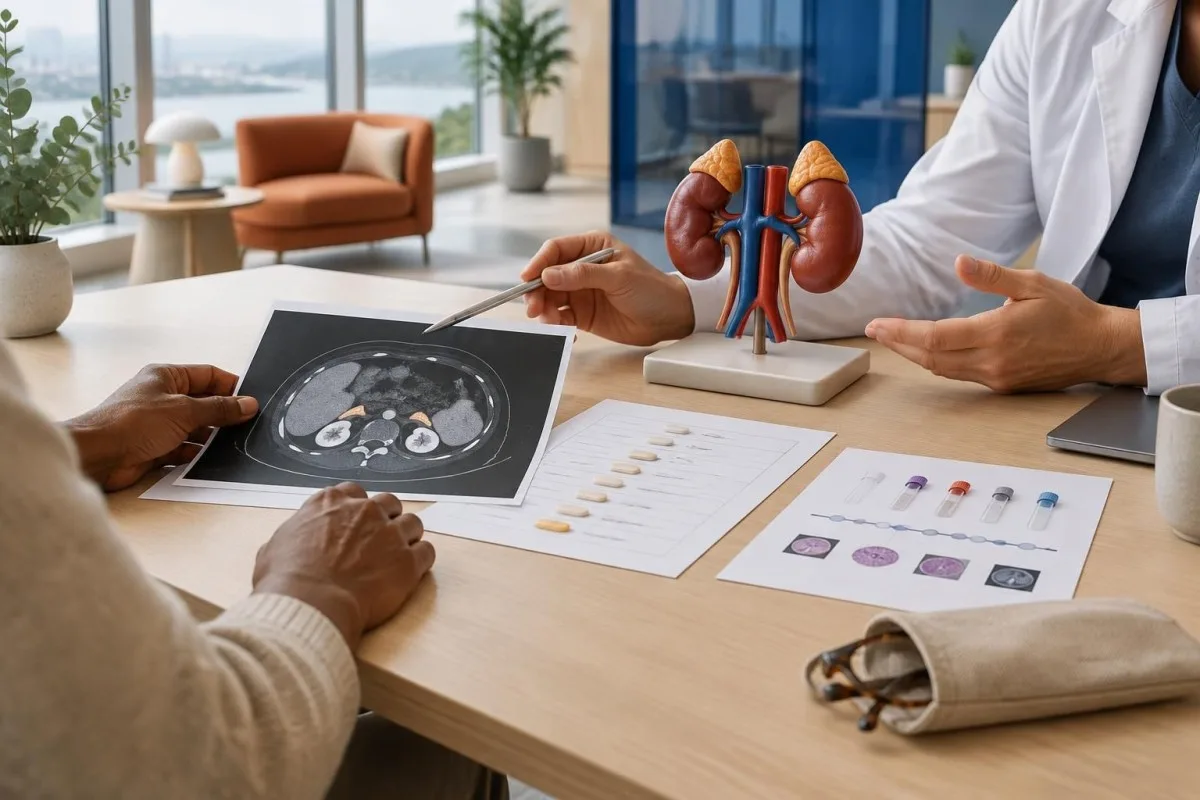
The 2023 guideline recommends no additional imaging for a homogeneous adrenal mass with unenhanced attenuation of 10 HU or less, regardless of size, when the radiologist is confident in the characterization. This is different from older practices that scheduled annual scans for almost every incidental mass.
For a lesion between 11 and 20 HU and smaller than 4 cm, clinicians may obtain dedicated adrenal imaging immediately or repeat noncontrast CT or MRI after roughly 12 months. If the lesion is indeterminate and the first follow-up is reassuring, further imaging may not be needed; local multidisciplinary practice varies.
Growth above 20% and at least 5 mm is a commonly used trigger for reassessment, but a 3 mm difference in a 12 mm lesion may reflect measurement variability. Kantesti can help display longitudinal laboratory trends beside scan dates; our blood-test trend analyzer is not a substitute for radiology comparison.
When an adrenal incidentaloma needs surgery
Surgery is considered for a hormonally active mass, a lesion with suspicious imaging or meaningful growth, and selected cases of mild autonomous cortisol secretion with relevant health complications. A benign-appearing, nonfunctioning adrenal mass is usually monitored or discharged from imaging follow-up rather than removed automatically.

A mass producing clinically significant cortisol, aldosterone or catecholamines may require adrenalectomy after appropriate preparation. For mild autonomous cortisol secretion, the decision is individualized using age, cardiovascular risk, diabetes control, osteoporosis, the degree of cortisol abnormality and whether the patient prefers intervention after informed discussion.
Suspicious imaging includes irregular margins, heterogeneity, local invasion, rapid growth or unenhanced density above 20 HU, particularly when the mass is at least 4 cm. A biopsy is not a routine next step because it cannot reliably distinguish many adrenal cortical tumours and may be dangerous if pheochromocytoma has not been excluded.
Specialist teams usually include endocrinology, radiology, surgery and pathology, with anaesthetic planning for hormone-producing lesions. Kantesti's 의학적 검증 정보 describes how our health information tools are designed to support interpretation and preparation, not to recommend an operation.
Red flags needing urgent specialist review
Urgent review is needed for severe episodic headache with palpitations and sweating, very high or unstable blood pressure, fainting, sudden abdominal or back pain, shock-like symptoms, rapidly progressive virilization or a scan suggesting invasion. These features can indicate hormone excess, hemorrhage or aggressive disease and should not wait for routine annual follow-up.
A suspected catecholamine crisis may cause severe headache, palpitations, sweating, tremor, chest discomfort or marked blood-pressure elevation. Blood pressure above 180/120 mmHg with neurological symptoms, chest pain, breathlessness or fainting is an emergency regardless of the adrenal scan result.
Sudden severe flank or abdominal pain, weakness, dizziness or low blood pressure can signal adrenal hemorrhage or acute adrenal insufficiency, particularly when both glands are enlarged or the person takes anticoagulants. New vomiting, confusion, sodium below 130 mmol/L or potassium above 5.5 mmol/L can add urgency, although thresholds must be interpreted by clinicians.
Rapid virilization, a new deep voice or fast-progressing facial hair over weeks to months deserves prompt endocrine assessment rather than a routine repeat hormone test. Our high DHEA guide explains why the speed of change can matter as much as the absolute value.
How pregnancy, age and cancer history change evaluation
Known cancer, bilateral adrenal masses, pregnancy, childhood, frailty and symptoms of adrenal insufficiency all modify the usual incidentaloma pathway. A scan that is low risk in an otherwise healthy adult may need a different plan when there is a previous malignancy or bilateral adrenal involvement.

In a person with a known extra-adrenal cancer, an adrenal mass may represent metastasis, a benign adenoma or a separate adrenal process. Comparison with earlier scans, contrast-enhanced imaging, MRI or functional imaging may be considered, but biopsy is generally reserved for cases where the result would change cancer treatment and pheochromocytoma has been excluded.
Bilateral masses raise additional questions about metastases, infiltrative disease, congenital adrenal hyperplasia or adrenal insufficiency. Morning cortisol, ACTH, electrolytes and sometimes an ACTH stimulation test may be appropriate when fatigue, weight loss, low blood pressure, vomiting or skin darkening accompany bilateral findings.
Pregnancy and frailty can change the balance between imaging exposure, surgery and testing burden, while children require pediatric endocrine pathways rather than adult cutoffs. Kantesti's 임상 사용 사례 show how structured timelines can organize information, but population-specific decisions still require the relevant specialist.
How to combine imaging, hormones and symptoms
No single result determines whether an adrenal incidentaloma is harmless. Clinicians combine CT density, size, homogeneity, growth, hormone tests, blood pressure, potassium, glucose, bone health, cancer history and symptoms to classify the mass and choose surveillance, additional imaging or treatment.
A hypothetical 52-year-old with a homogeneous 2.6 cm mass at 7 HU, normal metanephrines, post-dexamethasone cortisol of 1.2 micrograms/dL and normal blood pressure usually has a low-risk pattern. The same size mass at 28 HU with cortisol of 3.1 micrograms/dL and new diabetes requires a very different specialist discussion.
Glucose, HbA1c, potassium, sodium, kidney function and blood pressure are not adrenal-specific tests, but they reveal consequences that can strengthen or weaken the suspicion of hormone excess. For example, repeated potassium values of 3.0 mmol/L with resistant hypertension make aldosterone testing more relevant than an isolated normal potassium result.
Kantesti AI interprets laboratory patterns by comparing related biomarkers, collection dates and reference intervals instead of treating one flagged result as a diagnosis. Keep the original scan report, medication list, hormone-test timing and prior imaging together; that bundle is often more useful than a long list of disconnected results.
다음 진료에서 가져가야 할 질문들
The most useful appointment questions concern the exact CT density, lesion size, hormone tests performed, medication interference and the date of the next review. Writing these details down reduces the chance that a vague report such as adrenal nodule becomes the entire clinical conversation.
Ask: What is the unenhanced HU value, is the mass homogeneous, and was contrast washout or MRI characterization needed? Also ask whether the mass measured 2 cm, 4 cm or another size on the original images, because management thresholds are not based on the word small alone.
Ask which hormone tests were completed and whether the sample conditions were suitable. Useful specifics include the dexamethasone dose and timing, cortisol in micrograms/dL or nmol/L, metanephrines relative to the laboratory upper limit, potassium in mmol/L and whether blood-pressure medicines altered aldosterone or renin.
Ask for a written follow-up plan: no further imaging, repeat CT or MRI in 6 to 12 months, endocrine review, or multidisciplinary discussion. The 의료 자문 위원회 정보 describes the clinical oversight behind Kantesti's educational material, but your own endocrinology team remains responsible for individual care.
A practical adrenal nodule workup plan
A practical adrenal nodule workup starts by confirming the scan details, screening for clinically relevant hormone excess, checking for red flags and assigning a clear follow-up interval. Most low-density, homogeneous, nonfunctioning masses do not require surgery, while indeterminate or active lesions need timely specialist input.
Step one is to obtain the original radiology report and record size, side, unenhanced HU, homogeneity and comparison with previous scans. Step two is a medication-aware hormone review, usually including dexamethasone suppression testing and selective metanephrine or aldosterone-renin testing.
Step three is to match the result to a time frame: immediate specialist assessment for suspicious imaging or major hormone excess, repeat imaging at about 6 to 12 months for selected indeterminate masses, and no further imaging for many homogeneous lesions at 10 HU or less. Local guidelines and patient factors can change these intervals.
The safest interpretation is pattern-based rather than alarm-based. Use Kantesti as an organized laboratory record and discussion aid, and seek urgent help for severe blood-pressure symptoms, fainting, sudden abdominal pain, confusion or rapidly progressive hormone-related changes.
자주 묻는 질문
부신 우연종은 보통 암인가요?
Most adrenal incidentalomas are benign adenomas, particularly when they are homogeneous and measure 10 Hounsfield units or less on unenhanced CT. A mass that is heterogeneous, above 20 HU, rapidly enlarging or at least 4 cm requires more careful specialist assessment, but those features still do not prove cancer. Clinicians combine imaging, hormone results, previous scans and cancer history before deciding on surgery or further testing.
What blood tests are done for an adrenal incidentaloma?
The usual first hormone screen includes a 1 mg overnight dexamethasone suppression test, with morning cortisol measured afterward. Plasma free or urinary fractionated metanephrines are used when the mass is not clearly a benign low-density adenoma or when symptoms suggest catecholamine excess. An aldosterone-to-renin ratio is added when hypertension or unexplained potassium below about 3.5 mmol/L is present, while androgen tests are targeted to virilization or suspicious imaging.
What cortisol level is concerning after dexamethasone?
A cortisol level of 1.8 micrograms/dL, or 50 nmol/L, or lower after a correctly performed 1 mg overnight dexamethasone suppression test generally excludes autonomous cortisol secretion. A result above 1.8 micrograms/dL may indicate mild autonomous cortisol secretion, but it requires medication review, confirmation of test conditions and assessment for diabetes, hypertension or osteoporosis. It does not automatically diagnose overt Cushing syndrome or mean that surgery is required.
How often should an adrenal incidentaloma be scanned?
A homogeneous adrenal mass measuring 10 Hounsfield units or less on unenhanced CT often needs no repeat imaging under the 2023 European guideline. An indeterminate mass commonly receives additional imaging or repeat noncontrast CT or MRI after about 6 to 12 months, depending on its size and appearance. Growth exceeding 20% and at least 5 mm is a commonly used trigger for specialist reassessment.
When is an adrenal incidentaloma an emergency?
An adrenal incidentaloma needs urgent assessment when it is accompanied by severe episodic headache, palpitations, sweating, very high blood pressure, fainting, sudden severe abdominal or back pain, shock-like symptoms or rapidly progressive virilization. Blood pressure of 180/120 mmHg or higher with chest pain, neurological symptoms or breathlessness is an emergency regardless of the scan result. Bilateral masses with vomiting, confusion, low blood pressure, sodium below 130 mmol/L or potassium above 5.5 mmol/L also require prompt medical care.
Can a CT scan alone diagnose an adrenal incidentaloma?
CT can strongly suggest a benign adenoma when a mass is homogeneous and 10 Hounsfield units or less on an unenhanced scan, but CT alone cannot determine whether the mass produces hormones. Clinicians may still use a dexamethasone suppression test and selective metanephrine or aldosterone-renin testing. A CT report should include the mass size, unenhanced density, homogeneity and comparison with earlier imaging.
혈액검사 결과 보는법
검사실 보고서를 업로드하면 Kantesti의 AI가 몇 초 안에 각 바이오마커를 쉬운 말로 설명합니다. 전 세계 200만 명 이상이 사용하고 있습니다.
참고 자료
- Klein, T., Mitchell, S., & Weber, H. (2026). AI 혈액검사 분석기: 2.5M건 분석 | 글로벌 헬스 리포트 2026. Kantesti AI 의학 연구. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). RDW 혈액검사: RDW-CV, MCV 및 MCHC 완전 가이드. Kantesti AI 의학 연구. DOI
- Fassnacht M et al. (2023). European Society of Endocrinology clinical practice guidelines on the management of adrenal incidentalomas, in collaboration with the European Network for the Study of Adrenal Tumors. 유럽 내분비학 저널.
- Lenders JWM et al. (2014). Pheochromocytoma and Paraganglioma: An Endocrine Society Clinical Practice Guideline. The Journal of Clinical Endocrinology & Metabolism. DOI 퍼브메드
- 200만+분석한 검사
- 127+국가
- 100+언어
의료진 소개


E-E-A-T 신뢰 신호
경험
의사가 주도하는 검사 해석 워크플로 임상 검토.
전문적 지식
임상 맥락에서 바이오마커가 어떻게 거동하는지에 대한 검사실 의학 중심.
권위
Thomas Klein 박사의 의학적 검토를 거쳤으며, Sarah Mitchell 박사와 Hans Weber 교수의 기여가 있었습니다.
신뢰성
경고를 줄이기 위한 명확한 후속 경로가 포함된 근거 기반 해석.



의학적 면책 조항
이 글은 교육 목적만을 위한 것이며 의학적 조언을 구성하지 않습니다. 진단 및 치료 결정에는 항상 자격을 갖춘 의료 전문가와 상담하세요.
게시됨 · 편집팀에 문의
Kantesti Ltd 발행, 잉글랜드 및 웨일스에 등록된 회사, 회사 번호. 17090423, 런던, 영국.
