A positive antibody result does not automatically require treatment. Symptoms, exposure history, eosinophil counts and an eye examination can distinguish an incidental finding from disease needing care.

Негізгі тұжырымдар
- Оң антиденелер show an immune response to Toxocara antigens; 1 positive result cannot establish whether larvae are currently causing disease.
- Бұрынғы әсер can leave detectable IgG for years, so persistent positivity is not a reliable test of treatment failure.
- Эозинофилия generally means an absolute eosinophil count above 0.5 × 10⁹/L; it supports investigation but does not identify Toxocara as the cause.
- Higher eosinophil counts of at least 1.5 × 10⁹/L deserve evaluation when persistent or accompanied by organ symptoms, rather than automatic parasite treatment.
- Eye symptoms such as new blurred vision, floaters or reduced vision in 1 eye require prompt assessment; sudden visual loss warrants emergency care.
- Емдеу for visceral toxocariasis may include albendazole 400 mg twice daily for 5 days under clinician supervision, according to CDC guidance.
- Ocular disease needs specialist-directed treatment because controlling the tissue response can matter as much as treating the parasite.
- Қайта байланыс should track symptoms and relevant laboratory trends; an antibody index falling from 2.0 to 1.5 does not, by itself, prove recovery.
Does a positive Toxocara antibody result need treatment?
Positive toxocara antibodies do not automatically need treatment. Detectable antibodies can reflect previous exposure rather than active toxocariasis; treatment decisions depend on compatible symptoms, exposure history and supporting findings such as eosinophilia. New eye symptoms require prompt assessment, even when the antibody result is weakly positive or other tests are normal.

A positive antibody test detects immune recognition, not a live parasite count. Clinicians therefore separate 3 questions: whether exposure occurred, whether disease is present, and whether treatment is likely to help; the laboratory result answers only part of the first question.
For example, consider a hypothetical 38-year-old with a positive screening result, no symptoms and an absolute eosinophil count of 0.18 × 10⁹/L. That combination does not establish active toxocariasis, whereas the same result alongside persistent cough, eosinophilia and relevant exposure would justify a more targeted assessment.
Treatment should address a clinical syndrome rather than make an antibody result negative. Magnaval et al. (2001) describe the difficulty of separating past exposure from clinically significant toxocariasis using serology alone; our guide to оң антидене нәтижесінің интерпретациясы explains why different antibody tests lead to different decisions.
Кантести - бұл AI қан анализінің анализаторы that can help organise an antibody result alongside a CBC and liver panel, but cannot determine larval viability from 1 report. Read біздің ұйым туралы for the distinction between our interpretation service and the clinician-led assessment needed to prescribe treatment.
Why Toxocara antibodies can remain after past exposure
Toxocara IgG can remain detectable for years after exposure and may persist after treatment. Antibodies are part of immune memory, not a timestamp showing when exposure occurred. One positive sample cannot reliably distinguish remote exposure, persistent larvae without current symptoms, and larvae causing active tissue disease.
Humans usually harbour Toxocara larvae rather than adult intestinal worms. The 2 main species associated with human disease are Toxocara canis and Toxocara cati; larvae may migrate into tissues, where immune responses and symptoms differ from ordinary intestinal roundworm infection.
Persistent larvae and persistent antibodies are related but not interchangeable concepts. A person can have detectable IgG 3 years after a suspected exposure without evidence of current organ injury, and the antibody result alone cannot establish whether any remaining larvae are alive.
A strongly positive result does not reliably date exposure. Repeated exposure can boost antibody levels, and different assays recognise different antigen preparations; a numerical index of 4.0 therefore cannot be translated into 4 times as many larvae or 4 times the disease severity.
Long-lived antibodies make toxocariasis different from infections where direct organism detection is readily available. Our discussion of Babesia antibodies versus infection illustrates the same general distinction, although the confirmatory tests and treatment rules for Babesia are not transferable to Toxocara.
How to interpret antibody indexes, titres and borderline results
Toxocara serology interpretation must use the reporting laboratory’s method and cutoff. There is no universal antibody concentration in IU/mL that separates past exposure from active disease. ELISA indexes, optical-density ratios and dilution titres are different measurements, so 2 laboratories can report the same specimen differently.
An antibody index is usually an assay-specific signal rather than an absolute concentration. In a hypothetical laboratory using positivity above 1.1, an index of 1.3 would be just above the cutoff; that invented example is not a reference range to apply to your own report.
Borderline results deserve particular attention when symptoms and exposure are absent. A laboratory may recommend another specimen or a more specific confirmatory method, such as an immunoblot; our explanation of сапалы және сандық нәтижелер helps distinguish a positive flag from a genuinely comparable numerical measurement.
The probability of disease before testing changes what a positive result means. In an explicitly simulated group of 1,000 people, with 10% disease prevalence, 80% sensitivity and 90% specificity, testing would produce 80 true positives and 90 false positives—only about 47% of positive results would represent disease.
Those simulated figures are not performance estimates for a particular Toxocara assay. Kantesti AI can help identify the method and reference information on a report, but cannot replace missing validation data; antibody index confirmation also requires assay-specific reasoning, not borrowing cutoffs from another infection.
Which exposure histories make toxocariasis more plausible?
Toxocariasis is most often acquired by swallowing infective eggs from contaminated soil, hands or food. Dog and cat exposure matters because these animals can shed eggs, but simply owning a pet does not establish infection. Eggs generally require approximately 2–4 weeks in the environment to become infective.

Fresh animal faeces and established soil contamination are not identical exposure situations. Because eggs require environmental development, a garden or play area contaminated over several weeks can be more relevant than a single recent contact; daily pet-waste removal helps prevent eggs from reaching the infective stage.
Ask about 3 practical routes: soil or sand exposure, unwashed produce or hands, and consumption of undercooked tissues from infected animals. Foodborne transmission through larvae in animal tissues is recognised, but its contribution varies by setting; Trichinella antibody assessment involves a different parasite and different exposure clues.
A cat scratch is not the usual mechanism of Toxocara acquisition. Scratches instead raise other diagnostic possibilities, including Bartonella; our guide to cat scratch antibody testing explains why 1 animal-related event should not be used to label every positive infection test.
Geography changes the background likelihood of exposure but does not establish active disease. A hypothetical adult who gardened barefoot for 10 years may have a plausible exposure history, yet current symptoms, eosinophils and examination findings still determine whether that history explains the positive result.
Which symptoms and eosinophil counts support active disease?
Active visceral toxocariasis becomes more plausible when positive antibodies accompany compatible organ symptoms and eosinophilia. Fever, persistent cough, wheeze, abdominal discomfort or liver enlargement can support investigation, but none is specific. An absolute eosinophil count above approximately 0.5 × 10⁹/L is generally considered elevated in adults.
Eosinophilia is a clue to tissue responses, not a parasite identification test. Allergic disease, medicines, other helminths and some haematological disorders can raise eosinophils; a count of 0.8 × 10⁹/L therefore requires context rather than an automatic albendazole prescription.
Persistent counts of at least 1.5 × 10⁹/L warrant evaluation, especially when accompanied by respiratory, cardiac, neurological or other organ symptoms. That threshold reflects concern about hypereosinophilia and potential organ injury—not a validated Toxocara treatment cutoff; high eosinophil assessment неғұрлым кең дифференциалды диагностика туралы түсіндірмеміз бар.
Normal eosinophils do not exclude ocular toxocariasis. Disease confined to 1 eye may produce little systemic laboratory response, so a normal CBC cannot overrule new visual symptoms; this distinction is why eye complaints are assessed separately from the visceral disease pattern.
Mild or so-called covert toxocariasis is harder to establish because fatigue, itch and abdominal symptoms have many competing explanations. Magnaval et al. (2001) discuss these less specific presentations; when only 1 vague symptom is present, clinicians must avoid treating an incidental antibody result as proof of its cause.
Which other laboratory results help interpret Toxocara antibodies?
A CBC with an absolute eosinophil count usually adds more diagnostic context than the antibody index alone. Liver tests, total IgE and inflammatory markers may help assess a suspected clinical syndrome, but none confirms toxocariasis. Read the actual values and units, not just whether 1 result is flagged red.
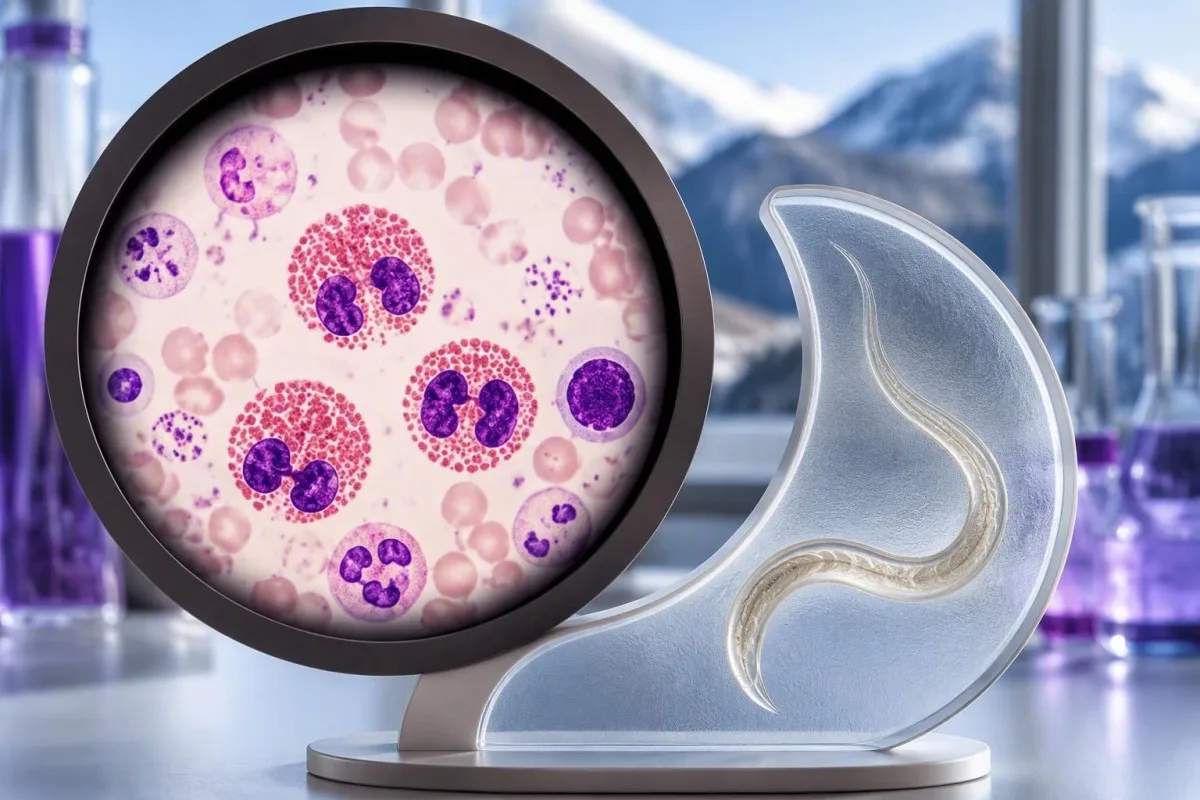
The absolute eosinophil count equals the white-cell count multiplied by the eosinophil fraction. A hypothetical WBC of 8.0 × 10⁹/L with 12% eosinophils gives 0.96 × 10⁹/L; 12% alone is less informative because the same percentage produces a different absolute count when total WBC changes.
Inflammatory markers cannot reliably separate Toxocara from allergy or another infection. CRP of 3 mg/L does not exclude localised eye disease, and CRP of 35 mg/L does not prove visceral toxocariasis; our guide to WBC пен CRP нәтижелерінің сәйкес келмеуі туралы түсіндірмеміз осы маркерлердің әртүрлі сұрақтарға жауап беретінін түсіндіреді.
Liver enzyme abnormalities describe tissue stress rather than its cause. A hypothetical ALT of 72 IU/L with a laboratory upper limit of 40 IU/L is 1.8 times that limit, but medicines, metabolic liver disease and other infections remain possibilities; бауыр панелі интерпретациясымен осы үлгілерді ажыратуға көмектеседі.
Кантести - бұл AI биомаркерлерін түсіндіру платформасы that can place eosinophils, ALT and antibody results in 1 organised summary for clinician review. Total IgE is particularly nonspecific: an elevated value may fit an allergic or helminth-related response, but no IgE threshold reliably establishes active toxocariasis.
Why do eye symptoms need prompt assessment?
New blurred vision, floaters or reduced vision—especially in 1 eye—need prompt assessment for ocular disease, regardless of the Toxocara antibody strength. Sudden visual loss, a curtain-like shadow or severe eye pain requires emergency care. Ocular toxocariasis can occur with low or negative serum antibodies and normal eosinophils.
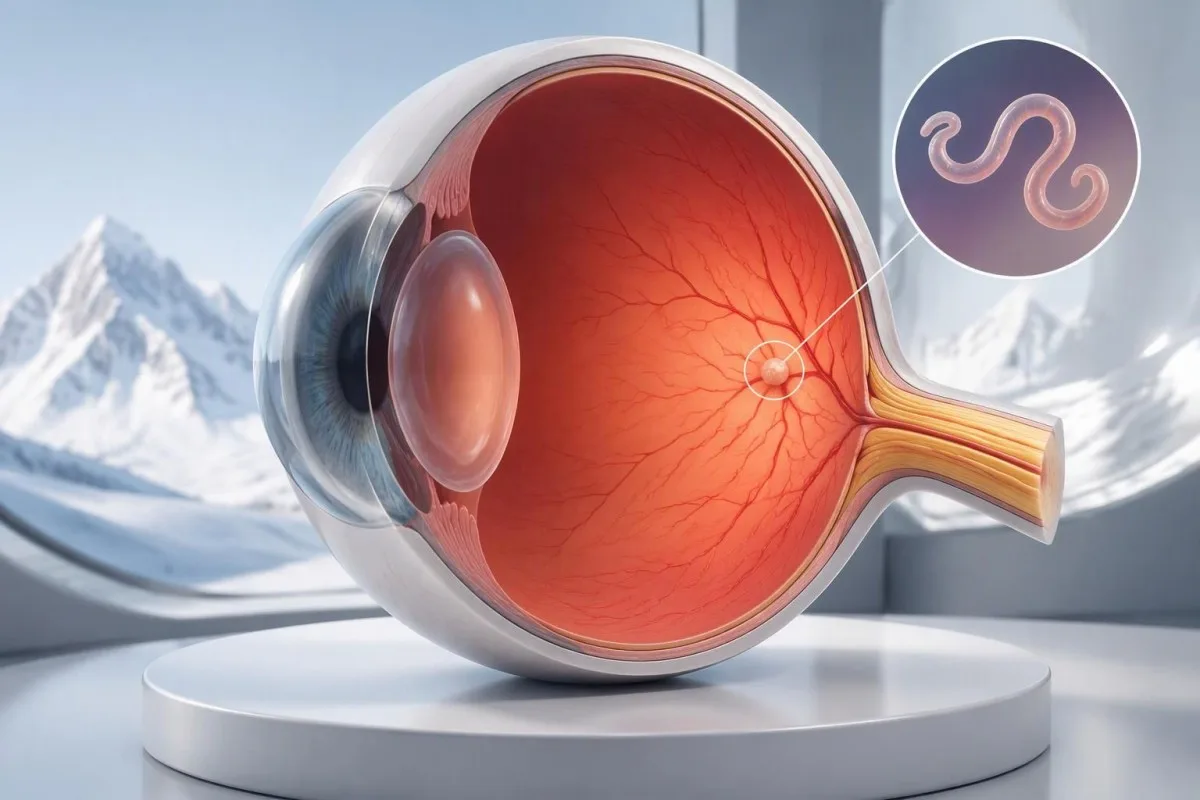
Ocular toxocariasis often affects only 1 eye. Ahn et al. (2014) describe retinal granulomas, vitreous tissue responses and other complications; the small local parasite burden helps explain why serum testing may be less informative than in systemic disease.
A positive antibody result does not identify the cause of every visual complaint. Uveitis, retinal tears, glaucoma and other conditions require different management, and HLA-B27-associated eye symptoms illustrate another reason that 1 positive laboratory marker cannot replace an eye examination.
Ocular toxocariasis diagnosis rests heavily on specialist examination. A dilated retinal examination and, when indicated, OCT or ocular ultrasound assess structures the antibody test cannot show; a weakly positive index of 1.2 should neither confirm the diagnosis nor delay referral in a symptomatic patient.
Do not wait several weeks for a repeat antibody result if vision has changed. Contact an urgent eye service the same day for new visual symptoms; in a child, a newly observed squint or white pupil also warrants urgent assessment because several sight-threatening conditions—not only Toxocara—can present that way.
How do clinicians make a toxocariasis diagnosis?
Toxocariasis diagnosis usually combines exposure history, compatible clinical findings, serology and exclusion of better explanations. No single routine test reliably confirms every form of the disease. Clinicians consider at least 3 evidence domains—exposure, organ findings and laboratory support—rather than treating a positive antibody flag as a diagnosis.

Human stool testing does not normally detect Toxocara eggs. Humans are accidental hosts, and larvae generally do not mature into egg-producing adult worms; 3 negative stool samples therefore do not rule out toxocariasis, although stool testing may help identify other parasites.
Cross-reactivity with other helminths can reduce serological specificity, particularly where multiple parasites circulate. Before prescribing systemic corticosteroids, clinicians may assess Strongyloides risk because steroids can precipitate severe strongyloidiasis; Strongyloides IgG follow-up follows different treatment principles from incidental Toxocara positivity.
Imaging should answer a specific organ-related question. Liver ultrasound or other imaging may be useful when symptoms, examination or laboratory findings suggest organ involvement, but scanning an asymptomatic person because of 1 positive antibody test can discover unrelated abnormalities without clarifying the diagnosis.
Kantesti can help organise these findings, but cannot resolve a discordant clinical picture from laboratory data alone. If antibodies are positive, eosinophils are 0.1 × 10⁹/L and symptoms point strongly toward another condition, the appropriate next step is clinician-led reassessment—not labelling every complaint as a parasite effect.
When is observation reasonable after a positive result?
Observation can be reasonable when a person has positive Toxocara antibodies but no compatible symptoms or evidence of organ involvement. This is a clinician-led decision, not a rule that all asymptomatic positives can be ignored. One unexplained laboratory abnormality, such as persistent eosinophilia, may still require investigation.
Evidence for treating every asymptomatic seropositive person is limited. Antibody persistence makes eradication difficult to measure, and the balance between benefit and medicine-related harm differs from symptomatic visceral disease; there is no universal antibody index, such as 2.0, that mandates treatment by itself.
An observation plan should specify what will be reviewed and what should trigger earlier contact. For example, a hypothetical clinician might arrange symptom and CBC review in 4–6 weeks when mild unexplained eosinophilia is present; that interval is an illustrative plan, not a universal toxocariasis follow-up guideline.
Routine parasite antibody screening is not usually useful solely because someone feels well and owns a pet. Broad screening increases the chance of finding evidence of past exposure without actionable disease; our guide to blood work without symptoms explains how risk-based testing reduces unnecessary follow-up.
Safety-net instructions make observation an active decision rather than neglect. New visual symptoms, persistent fever, worsening breathing or neurological symptoms should prompt earlier assessment, and a rising eosinophil count from 0.7 to 1.8 × 10⁹/L deserves review even if the antibody result is unchanged.
What treatment is used for symptomatic toxocariasis?
Clinicians commonly use albendazole for symptomatic visceral toxocariasis, while ocular disease needs specialist-directed treatment. CDC Clinical Care guidance lists albendazole 400 mg orally twice daily for 5 days for adults and children, but also states that the optimal treatment duration is undefined. This is prescribing information, not a self-treatment instruction.

Treatment duration can differ across specialist practice because evidence is limited. CDC also lists mebendazole 100–200 mg twice daily for 5 days, while longer albendazole courses appear in published clinical practice; different schedules should not be interpreted as proof that a short course always fails.
Ocular management aims to protect sight and control the tissue response. Ahn et al. (2014) discuss antiparasitic therapy, corticosteroids and procedural treatment in selected cases; 1 standard visceral regimen should not be copied into an eye-disease treatment plan without ophthalmology input.
Longer albendazole courses may require liver-enzyme and blood-count monitoring. Baseline liver disease, interacting medicines and treatment duration affect the monitoring plan; our guide to дәрі-дәрмектер қауіпсіздігінің үрдісін талдау explains why changes from an individual baseline can matter more than a single flag.
Kantesti does not prescribe antiparasitic medicines or corticosteroids. A hypothetical ALT rise from 30 to 110 IU/L during treatment needs clinician review rather than an AI-directed dose change; pregnancy, age under 2 years, liver disease and other medicines also require individual prescribing assessment.
How do children, pregnancy and immune status change decisions?
Children, pregnant people and patients needing immunosuppression require individual assessment rather than automatic treatment after positive serology. Exposure behaviours, eye findings and medicine safety differ across these groups. CDC notes limited albendazole safety evidence in children under 6 years, despite experience with younger children in public-health programmes.

Young children may have greater hand-to-mouth soil exposure, particularly with pica. A 3-year-old with repeated soil ingestion and eosinophilia has a different exposure profile from an asymptomatic adult, but neither age nor behaviour proves that a positive test represents active disease.
Paediatric laboratory interpretation needs age-appropriate reference information and an adult who can provide a reliable symptom history. Our discussion of AI балаларға арналған интерпретациясы explains why 1 automated summary cannot replace assessment of growth, visual behaviour and medicine suitability.
Pregnancy does not convert Toxocara IgG into proof of a new infection. Unlike toxoplasmosis, toxocariasis does not have an established routine prenatal serological screening pathway; an isolated positive result at 10 weeks of pregnancy requires contextual review, not assumptions about fetal infection or automatic antiparasitic treatment.
Before prolonged corticosteroid treatment, parasite assessment should match travel and exposure history. The immediate safety concern may be Strongyloides rather than Toxocara, and a patient taking prednisone 40 mg daily should not independently add or stop medicines because of an antibody report.
Should Toxocara antibodies be repeated after treatment?
Repeat Toxocara antibodies are not a reliable stand-alone test of cure because IgG can remain positive for years. Follow-up should prioritise symptom improvement, relevant organ findings and eosinophil trends. One antibody measurement after treatment cannot establish either eradication or failure.

Use the same laboratory method when numerical trends are clinically needed. A result of 2.4 on one assay and 1.7 on another may reflect different calibrators or antigen preparations, rather than biological improvement; switching assays can create a trend that does not exist.
Symptoms and eosinophils often provide a more practical follow-up signal than persistent IgG. In a hypothetical case, cough improving alongside an eosinophil decline from 1.2 to 0.4 × 10⁹/L supports clinical improvement, but does not prove that every larva has been eliminated.
A small numerical change may fall within assay variation. An index shifting from 1.4 to 1.3 should not be treated as meaningful without laboratory information about reproducibility; our guide to мағыналы қан анализінің өзгеруі explains the distinction between analytical variation and a real trend.
Ocular follow-up requires eye examination rather than antibody tracking alone. Stable serum IgG cannot show whether a retinal affected area is improving, and persistent or recurrent visual symptoms after a 5-day medicine course need specialist reassessment rather than repeated unsupervised treatment.
How can AI help without overcalling active toxocariasis?
AI can help organise Toxocara antibodies, eosinophils and liver results, but cannot diagnose active disease from serology alone. A useful interpretation preserves uncertainty and highlights missing clinical information. At minimum, the report should be considered with 3 details: symptoms, exposure history and the laboratory’s assay method.
Кантести - бұл AI қан талдауы нәтижесін түсіндіру платформасы that can summarise related results and help prepare questions for a clinician. Our AI технологиясының түсіндірмесі describes the interpretation workflow; a response generated in approximately 60 seconds is not an examination, a parasite-viability test or permission to delay urgent eye care.
Clinical reasoning should remain traceable to the original report. Check that an eosinophil value of 0.8 × 10⁹/L has not been confused with 0.8%, and that borderline and confirmed-positive findings are distinguished; our валидация және клиникалық қадағалау information describes how we discuss methodology without claiming every output establishes a diagnosis.
Privacy also matters when sharing laboratory documents. Remove unnecessary identifiers and obtain consent before submitting another person’s report; our құпиялылық және деректер туралы ақпаратты explains data handling, but privacy safeguards do not change the medical limitations of interpreting 1 antibody result.
Bring 4 items to the appointment: the complete report, symptom dates, exposure details and a medicine list. Ask whether the result explains a defined clinical syndrome, whether another diagnosis fits better, what would justify treatment, and which symptoms require urgent reassessment.
Research publications: what supports these treatment decisions?
Treatment decisions in this article rely on Toxocara-specific clinical literature and CDC guidance, not unrelated laboratory publications. The 2 peer-reviewed reviews listed below explain diagnostic limitations and ocular management. The separate Zenodo records cover iron and coagulation testing; they do not establish how positive Toxocara antibodies should be treated.
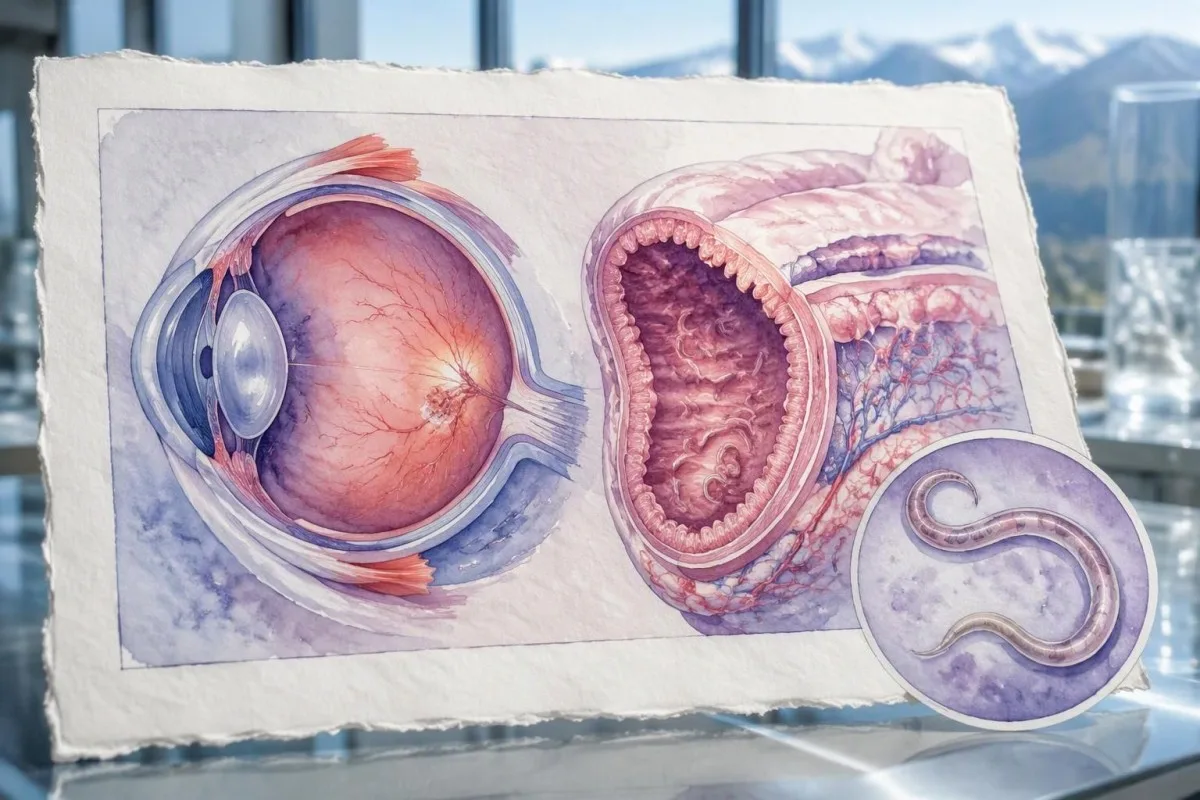
A review article is not the same as a randomised treatment trial. Magnaval et al. (2001) and Ahn et al. (2014) bring together clinical observations and published evidence, but important uncertainties remain about optimal treatment duration and the benefit of treating asymptomatic seropositivity.
Kantesti’s 2 listed Zenodo publications address different laboratory topics. The темір көрсеткіштерін зерттеу жөніндегі негізгі нұсқаулық may help with an independently identified iron abnormality, while the coagulation testing background guide addresses clotting tests; neither is a confirmatory test for toxocariasis.
A useful medical article must separate evidence, inference and illustration. The hypothetical antibody indexes and worked examples here are not patient records or validated treatment thresholds; our медициналық мазмұн стандарттары explain that approach, including why 1 positive antibody finding should never be presented as a complete diagnosis.
Жиі қойылатын сұрақтар
Toxocara-ға антиденелерге жасалған тест оң нәтиже көрсетсе, маған альбендазол қабылдау қажет пе?
Toxocara-ға антиденелерге тесттің оң нәтижесі альбендазол қабылдау қажет екенін автоматты түрде білдірмейді. IgG бірнеше жыл бойы анықталуы мүмкін, сондықтан дәрігерлер бір оң нәтижеге ғана сүйеніп ем тағайындамай, сәйкес симптомдарды, жұқтыру қаупімен байланысты анамнезді және растайтын белгілерді ескереді. CDC висцералды токсокароз кезінде 5 күн бойы күніне екі рет 400 мг альбендазол қабылдауды ұсынады, бірақ емдеу туралы шешімді және оның ұзақтығын дәрігер бақылауы тиіс. Көзге қатысты жаңа симптомдар пайда болса, өз бетіңізше емделудің орнына шұғыл түрде офтальмологқа қаралыңыз.
Can Toxocara antibodies stay positive after treatment?
Toxocara antibodies can remain positive for years after exposure and may remain detectable after treatment. A result that is still positive 6 months later does not, by itself, prove treatment failure. Symptoms, eosinophil trends and relevant organ examinations are usually more useful follow-up measures. Numerical antibody trends should only be compared when the laboratory methods are sufficiently consistent.
What eosinophil count suggests toxocariasis?
An absolute eosinophil count above approximately 0.5 × 10⁹/L supports investigation but does not specifically identify toxocariasis. Allergy, medicines, other parasites and haematological conditions can produce the same finding. Persistent counts of at least 1.5 × 10⁹/L deserve evaluation, particularly with organ symptoms. Normal eosinophils do not exclude disease confined to the eye.
Can ocular toxocariasis happen with a negative blood test?
Ocular toxocariasis can occur with low or negative serum antibodies because disease may be localised to 1 eye. A normal eosinophil count also does not exclude ocular involvement. An ophthalmologist assesses retinal and vitreous findings, sometimes using OCT or ultrasound to clarify the diagnosis. New blurred vision or floaters need prompt assessment, while sudden visual loss warrants emergency care.
Does a negative stool test rule out Toxocara?
A negative stool test does not rule out human toxocariasis. Humans generally harbour tissue larvae rather than adult Toxocara worms that produce eggs, so even 3 negative stool samples cannot exclude the condition. Stool testing may still identify other intestinal parasites. Toxocariasis assessment instead combines clinical findings, exposure history, serology and organ-specific evaluation when needed.
What does a borderline Toxocara antibody index mean?
A borderline Toxocara antibody index means the assay signal is close to that laboratory’s decision cutoff, not that active disease has been confirmed. For example, an index of 1.3 could be just above a hypothetical cutoff of 1.1, but those numbers are not universal reference values. The reporting laboratory may recommend repeat testing or a more specific confirmatory method. Symptoms and exposure history determine whether clarification is clinically useful.
Қан анализінің нәтижесін түсіндіріп алыңыз
Зертханалық есепті жүктеңіз, сонда Kantesti AI әр биомаркерді бірнеше секунд ішінде қарапайым тілмен түсіндіреді. Әлем бойынша 2 миллионнан астам адам қолданады.
Сілтемелер
- Klein, T., Mitchell, S., & Weber, H. (2026). Темір көрсеткіштеріне арналған нұсқаулық: TIBC, темірмен қанығу және байланыстыру қабілеті. Kantesti AI медициналық зерттеулері. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTT қалыпты аралығы: D-димер, C протеині және қанның ұюы жөніндегі нұсқаулық. Kantesti AI медициналық зерттеулері. DOI
- Magnaval JF et al. (2001). Highlights of human toxocariasis. The Korean Journal of Parasitology. DOI
- Ahn SJ et al. (2014). Ocular toxocariasis: clinical features, diagnosis, treatment, and prevention. Asia Pacific Allergy. DOI
- Centers for Disease Control and Prevention (n.d.). Clinical Care of Toxocariasis. CDC Parasites.
- 2 млн+Талданған тесттер
- 127+Елдер
- 100+Тілдер
Медициналық топ туралы


E-E-A-T сенім сигналдары
Тәжірибе
Дәрігер басқаратын зертханалық талдауды түсіндіру жұмыс ағындарын клиникалық шолу.
Сараптама
Биомаркерлердің клиникалық контексте қалай әрекет ететініне зертханалық медицина фокусы.
Билік
Доктор Томас Кляйн медициналық тұрғыдан тексерген, доктор Сара Митчелл мен профессор доктор Ханс Вебердің үлесімен.
Сенімділік
Дабыл қаупін азайту үшін айқын бақылау жолдарымен дәлелге негізделген түсіндіру.






Медициналық ескерту
Бұл мақала тек білім беру мақсатында ғана және медициналық кеңес болып табылмайды. Диагноз және ем туралы шешімдер үшін әрдайым білікті медицина қызметкеріне жүгініңіз.
Жарияланды · Редакция тобына хабарласыңыз
Англия мен Уэльсте тіркелген Kantesti Ltd басып шығарған, компания №. 17090423, Лондон, Біріккен Корольдік.
