
Stool alpha-1 antitrypsin clearance estimates intestinal protein loss using a timed stool collection and a blood sample taken around the same period. An elevated result supports protein loss through the gut, but it does not identify the cause or where the loss occurs.

Wichtichste punten
- Doel: Stool alpha-1 antitrypsin clearance helps investigate suspected protein-losing enteropathy, especially when albumin is low without an adequate explanation.
- Two samples: The calculation combines alpha-1 antitrypsin concentrations in a timed stool collection and a paired serum sample.
- Collection time: Many laboratories use 24 hours, but the ordering laboratory’s instructions determine the required interval.
- Example threshold: Some laboratories use an adult upper limit of approximately 27 mL/day without diarrhea; use the range on your own report.
- Diarrhea: High stool output can raise clearance, so some clinical references use a higher interpretive threshold, such as 56 mL/day, in this setting.
- Sammelingsflaters: Missing stool can underestimate clearance; urine, toilet water, or an incorrect collection period can make a sample unsuitable.
- Posityf resultaat: Elevated clearance supports intestinal protein loss but does not establish a specific diagnosis or pinpoint its location.
- Folgjende stap: Review the result alongside albumin, urine protein, liver assessment, symptoms, and the quality of the collection.
What does stool alpha-1 antitrypsin clearance measure?
Stool alpha-1 antitrypsin clearance estimates how much serum-equivalent fluid loses alpha-1 antitrypsin into stool each day. It is used to assess suspected protein-losing enteropathy, not to measure the exact grams of albumin lost.
Alpha-1 antitrypsin, often abbreviated A1AT, is a protein made mainly by the liver. It is relatively resistant to breakdown in the intestine, so its appearance in stool can help clinicians assess leakage of blood proteins into the digestive tract.
The clearance result is expressed in mL/day: a volume of serum containing an amount of A1AT equivalent to the amount recovered in stool during a day. It is not the physical volume of blood lost and should not be converted directly into grams of albumin.
Kantesti is an AI blood test analyzer that can help readers understand accompanying blood results such as albumin. Stool clearance still requires the laboratory’s calculation and a clinician’s assessment; our gids foar serum-aaiwiten explains the related blood markers.
When might a clinician order this protein-losing enteropathy stool test?
A clinician may order this protein-losing enteropathy stool test when low albumin or unexplained swelling raises concern that protein is being lost through the digestive tract. The test is particularly useful when urine protein loss, liver disease, and other explanations have not accounted for the findings.
Possible clues include persistent diarrhea, weight loss, swollen legs, abdominal fluid, or low immunoglobulin levels. Not everyone has diarrhea, and none of these findings proves intestinal protein loss.
Albumine wurdt faak rapporteare yn g/L in the UK and g/dL elsewhere: 30 g/L equals 3.0 g/dL. A low result can reflect inflammation, liver disease, kidney protein loss, fluid shifts, or several processes at once, rather than a single diagnosis.
Umar and DiBaise describe protein-losing enteropathy as a manifestation of multiple gastrointestinal and systemic disorders, not a disease with one cause (Umar and DiBaise, 2010). A urine protein assessment is relevant because kidney loss can produce a similar low-albumin picture.
Why is a paired serum sample needed?
The paired serum sample gives the laboratory a blood concentration against which to compare the amount of alpha-1 antitrypsin recovered from stool. Without it, a stool concentration alone is not a complete clearance calculation.

A1AT concentrations differ between people and can change during illness because A1AT is an acute-phase protein. Pairing stool with serum helps account for the circulating concentration at approximately the time of collection.
Ask the laboratory when the blood sample should be taken relative to the stool collection. A sample from an unrelated earlier illness may not accurately represent the concentration during the collection interval.
This serum measurement is different from testing for inherited A1AT deficiency, even though it measures the same protein. Our A1AT deficiency guide explains why a low blood result may need separate evaluation.
How is fecal alpha-1 antitrypsin clearance calculated?
The fecal alpha-1 antitrypsin clearance test divides the amount of A1AT passed in stool per day by the serum A1AT concentration. When compatible units are used, the result is reported in mL/day.
The conceptual formula is stool A1AT concentration × daily stool output ÷ serum A1AT concentration. The laboratory must use compatible units and its validated handling of stool volume or weight; patients should not assume that a reported gram value is interchangeable with millilitres.
For a hypothetical example, suppose a laboratory has a validated daily stool volume of 200 mL, stool A1AT of 30 mg/dL, and serum A1AT of 200 mg/dL. The calculation is 200 × 30 ÷ 200, giving 30 mL/day.
That example is not a diagnosis: the laboratory’s interval, stool consistency, symptoms, and collection quality determine interpretation. Levitt and Levitt discuss why stool output and serum concentration matter when estimating gastrointestinal protein loss (Levitt and Levitt, 2017).
How should you prepare for alpha-1 antitrypsin stool collection?
Prepare for alpha-1 antitrypsin stool collection by obtaining the laboratory’s container, written timing instructions, storage directions, and plan for the paired serum sample. Many protocols collect all stool for 24 oeren, but some laboratories use a different interval.

Before starting, confirm whether you need a collection device that fits over the toilet and whether the whole sample or a laboratory-directed portion must be returned. Follow the laboratory’s instructions rather than transferring or discarding material based on another test’s directions.
Ask whether refrigeration or freezing is required and how quickly the specimen should arrive. Storage conditions vary by laboratory and specimen method, so a generic temperature rule may be wrong for your kit.
Tell the clinician about medicines and supplements, especially acid-suppressing treatment and medicines that affect bowel movements. Do not stop a prescribed medicine unless the clinician instructs you to; gastrin testing offers another example of why medication context matters.
How does a timed stool collection work?
A timed stool collection aims to capture every bowel movement passed during the exact interval specified by the laboratory. Record the start and finish times and follow the kit’s instructions for stool passed near either boundary.

For a hypothetical 24-hour collection beginning at 8:00 a.m., the interval ends at 8:00 a.m. the next day. The timing records allow the laboratory to check that the amount submitted represents the prescribed period.
Keep stool separate from urine and toilet water when the kit requires it. Collection aids can make this easier, but the device and transfer method should be approved by the laboratory.
If a bowel movement is missed or the container leaks, call the laboratory before submitting it. A partial collection can underestimate daily loss, while guessing the missing amount cannot reliably correct the calculation; other timed sample collections have similar completeness concerns.
Which collection problems can make clearance misleading?
Missing stool, collecting for the wrong duration, contamination, and incorrect storage can make stool A1AT clearance difficult or impossible to interpret. The direction of error depends on the problem; not every flawed specimen produces a falsely high result.

A missed bowel movement usually reduces the amount recovered and can falsely lower the calculated daily loss. An incorrectly recorded interval can also distort a result normalized to mL/day.
Urine or toilet water may alter the sample or cause laboratory rejection. If contamination occurs, document it and ask whether to restart instead of silently submitting the container.
Visible gastrointestinal bleeding is relevant because blood entering the gut can add A1AT to stool and complicate interpretation. Report it promptly; our guide to bloed yn stoelgong explains when bleeding needs urgent attention.
What clearance result is considered elevated?
An elevated stool A1AT clearance is a result above the performing laboratory’s reference limit for its method and clinical circumstances. A commonly cited adult upper limit without diarrhea is approximately 27 mL/day, but laboratories can use different ranges.

Some clinical references use 56 mL/day as an upper threshold when diarrhea is present because increased stool output can raise clearance even without protein-losing enteropathy. This is not a universal cutoff: apply the laboratory’s stated reference interval and discuss diarrhea with the ordering clinician.
For example, a hypothetical result of 35 mL/day may be above a laboratory’s nondiarheal upper limit of 27 mL/day, but it should not automatically be interpreted the same way in someone with substantial diarrhea. The report’s range and the patient’s circumstances matter more than an isolated number.
A borderline result may warrant checking collection quality or repeating the test if the clinician thinks the result conflicts with the clinical picture. Kantesti can help organize the accompanying blood values, but it cannot validate a stool collection or replace the laboratory’s reference range.
| Nivo | Berik | Wat it betsjut |
|---|---|---|
| Within the laboratory range | For example, up to 27 mL/day without diarrhea | Does not demonstrate elevated clearance during that collection; it does not exclude every cause of protein loss. |
| Above the laboratory range | For example, above 27 mL/day without diarrhea | Supports excess gastrointestinal protein loss when the collection and clinical context are appropriate. |
| Diarrhea present | Some references use a threshold above 56 mL/day | Interpret with stool output and the laboratory’s method; this is not a universal cutoff. |
What does a positive or high clearance result mean?
A high clearance result supports increased loss of protein into the gastrointestinal tract when the specimen is valid and the appropriate reference limit is used. It does not identify the underlying disorder, the exact site of loss, or the amount of albumin lost.
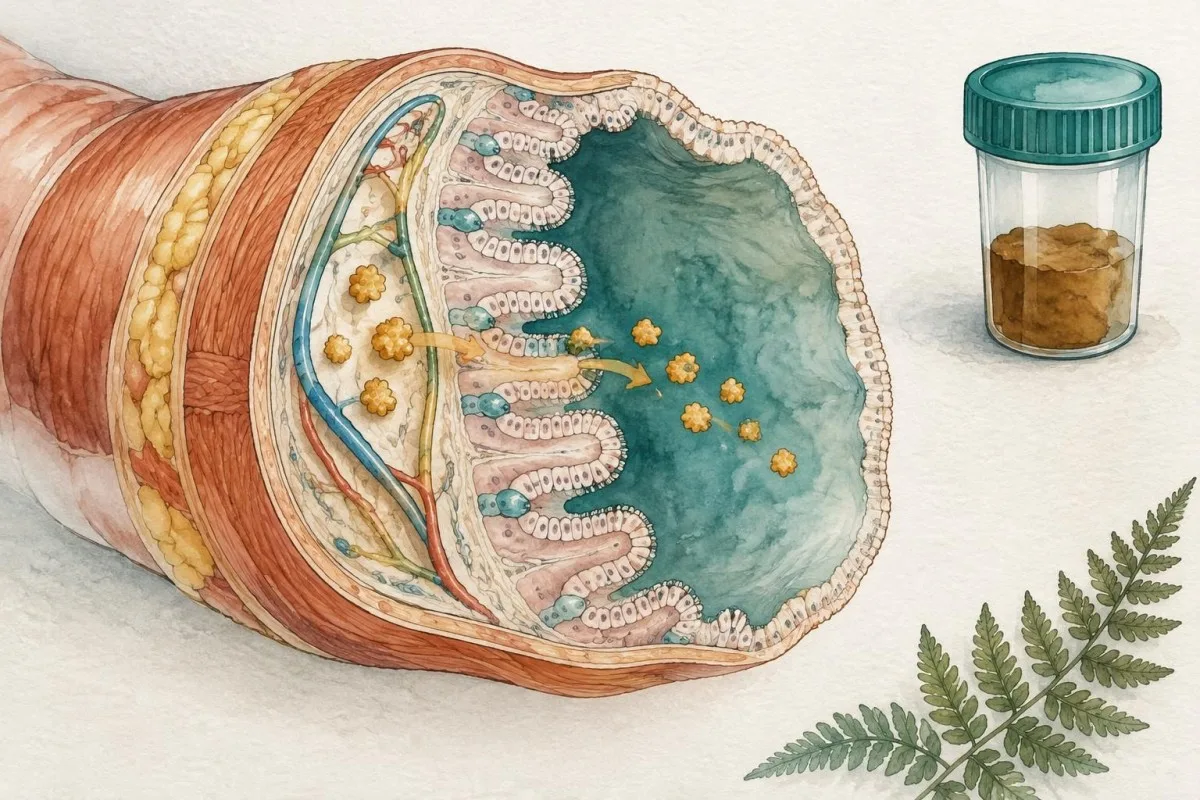
Potential mechanisms include an affected intestinal lining, increased intestinal lymphatic pressure, or other conditions that permit proteins to enter the gut. Each mechanism requires a different clinical workup, so a positive result is a starting point rather than a final diagnosis.
Conditions associated with protein loss include inflammatory bowel disease, celiac disease, intestinal lymphatic disorders, and some cardiac conditions. These are possibilities—not predictions about any individual result.
Testing for intestinal inflammation answers a different question from A1AT clearance. Our comparison of kalprotektine en laktoferrine explains why an inflammation marker cannot by itself quantify protein loss.
Can a normal clearance result miss protein loss?
A normal stool A1AT clearance can miss protein loss if the collection is incomplete, the loss is intermittent, or A1AT is substantially degraded before it reaches stool. A normal result is therefore interpreted alongside symptoms and the rest of the workup.
A1AT is less stable in a very acidic environment, making some cases of predominantly gastric protein loss harder to detect. The clinician may consider an acid-suppression protocol or a different test when appropriate, but patients should not start or stop acid-suppressing medicines on their own.
Rare inherited A1AT deficiency may also complicate use of A1AT as a stool marker; a very low serum concentration can make interpretation difficult. The laboratory and clinician can advise whether a different approach is more useful.
If suspicion remains high despite a valid result, a specialist may consider repeat testing or nuclear medicine studies using labelled proteins, depending on local availability. Other stool findings, including undigested food, do not independently rule protein loss in or out.
Is a random stool A1AT concentration the same as clearance?
A random stool A1AT concentration is not the same as a timed clearance result. Clearance includes stool output over time and a paired serum concentration; a spot concentration does not directly measure either.

Some laboratories offer a spot stool A1AT measurement as a screening or supporting test. Its interpretation depends on that assay’s reference interval and clinical context, and it should not be compared with a clearance range in mL/day.
Stool consistency can affect a concentration, while a timed calculation incorporates total output. A low concentration in watery stool does not necessarily mean the daily amount lost is low.
Before comparing reports, check the specimen type, units, collection interval, and whether serum was measured. Kantesti’s biomarker-gids can help readers distinguish related markers, but a laboratory report remains the source for the method used.
Which blood and urine results help explain protein loss?
Albumin, total protein, immunoglobulins, liver tests, and urine protein measurements help clinicians assess whether protein loss is intestinal, renal, hepatic, or multifactorial. No single accompanying blood test identifies protein-losing enteropathy on its own.
Urine albumin-to-creatinine or protein-to-creatinine ratios can identify kidney protein loss without requiring every patient to complete another timed collection. Creatinine helps account for urine concentration, although the test chosen depends on the clinical question.
Low albumin alongside low immunoglobulins may fit intestinal loss, but it is not specific; production and dilution also affect these results. Our immunoglobulin ynterpretaasjegids explains why IgG, IgA, and IgM should be read together.
Kantesti is an AI biomarker interpretation platform that can help readers review albumin and related blood markers together. Its output is educational, not a diagnosis, and it cannot determine whether a stool specimen was collected correctly.
What happens after intestinal protein loss is suspected?
After suspected intestinal protein loss, the next investigation is directed by symptoms, examination, and competing explanations rather than the clearance result alone. Possible next steps include targeted blood and stool tests, imaging, endoscopy, or cardiac assessment.
For example, chronic diarrhea and iron deficiency may lead a clinician to consider celiac testing, while signs of inflammatory bowel disease may lead to stool inflammation testing and endoscopy. Testing strategy changes if swelling or cardiac findings point toward a lymphatic or circulatory mechanism.
Do not begin a gluten-free diet solely to prepare for celiac testing without discussing it first: reducing gluten can affect test sensitivity. Our glutenútdagingsgids explains why timing and current diet matter.
Treatment targets the cause and may include a dietitian’s assessment of protein and nutrient needs. There is no universal protein dose for every patient, particularly when kidney, liver, or cardiac disease also affects the nutrition plan.
When should symptoms prompt urgent medical care?
Seek emergency care for severe shortness of breath, chest pain, fainting, confusion, or substantial gastrointestinal bleeding, regardless of a pending stool test. New or rapidly worsening swelling, persistent diarrhea, or signs of dehydration also deserve prompt clinical advice.

One swollen, painful leg can indicate a clot and needs urgent assessment, especially if it develops suddenly. Shortness of breath or chest pain alongside leg swelling is an emergency; our deep vein thrombosis guide describes these warning signs.
Black, tarry stool or a large amount of red blood warrants urgent evaluation, particularly with dizziness or weakness. A stool clearance test is not a safe substitute for assessing possible gastrointestinal bleeding.
Kantesti provides educational interpretation, not emergency triage or a replacement for a clinician. Our medyske ynhâldsnoarmen explain the principles behind our health information.
Faak stelde fragen
Wat is in normale alpha-1-antitrypsineklaring yn de ûntlasting?
Some clinical references use an adult upper limit of approximately 27 mL/day when diarrhea is absent, but the performing laboratory’s reference range takes priority. Diarrhea can increase clearance, and some references use 56 mL/day as a higher threshold in that setting. A result within range does not rule out every case of intestinal protein loss.
Does a high stool alpha-1 antitrypsin result mean cancer?
A high stool alpha-1 antitrypsin clearance does not mean cancer by itself. It supports gastrointestinal protein loss when the collection is valid and the appropriate reference limit is applied. Inflammatory, lymphatic, cardiac, and other conditions can also be associated with protein loss, so follow-up depends on the whole clinical picture.
Why do I need a blood sample with the stool collection?
The blood sample provides the serum alpha-1 antitrypsin concentration used as the denominator in the clearance calculation. The laboratory combines that concentration with the amount recovered during a timed stool collection, often 24 hours. A stool concentration without the paired serum result is not the same as clearance in mL/day.
Can diarrhea make stool alpha-1 antitrypsin clearance high?
Diarrhea can increase stool alpha-1 antitrypsin clearance because greater stool output affects the daily amount recovered. Some clinical references use a threshold of 56 mL/day during diarrhea rather than approximately 27 mL/day without diarrhea. The appropriate interpretation still depends on the laboratory’s method and the patient’s symptoms.
What should I do if I miss part of the stool collection?
Contact the laboratory if you miss any bowel movement during a timed stool collection, including a 24-hour collection. An incomplete specimen can underestimate the amount of alpha-1 antitrypsin passed and may require the test to be repeated. Do not estimate the missing amount or change the recorded times.
Can protein-losing enteropathy occur with a normal clearance result?
Protein-losing enteropathy can still be considered after a normal clearance result if clinical suspicion remains high. Intermittent loss, an incomplete 24-hour collection, or degradation of alpha-1 antitrypsin in a highly acidic stomach can complicate detection. A clinician may review the collection and consider repeat or alternative testing.
Lit jo bloedtest resultaten útlizze
Laad jo laboratoariumrapport op en de AI fan Kantesti leit elke biomarker binnen sekonden út yn gewoane taal. Brûkt troch mear as 2 miljoen minsken wrâldwiid.
Referinsjes
- Klein, T., Mitchell, S., & Weber, H. (2026). Gids foar serumproteïnen: Globulinen, albumine en de A/G-ferhâlding yn in bloedtest. Kantesti AI Medysk Undersyk. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Gids foar C3 C4-komplementbloedtests en ANA-titers. Kantesti AI Medysk Undersyk. DOI
- Umar SB, DiBaise JK (2010). Protein-losing enteropathy: case illustrations and clinical review. American Journal of Gastroenterology. DOI
- Levitt DG, Levitt MD (2017). Protein losing enteropathy: comprehensive review of the mechanistic association with clinical and subclinical disease states. Clinical and Experimental Gastroenterology. DOI
- 2M+Analysearre tests
- 127+Lannen
- 100+Talen
Oer it medyske team


E-E-A-T fertrouwensignalen
Ûnderfining
Dokter-oandreaune klinyske resinsje fan lab-ynterpretaasje-wurkprosessen.
Ekspertize
Fokus fan laboratoariummedisyne op hoe’t biomarkers har gedrage yn in klinyske kontekst.
Autoriteit
Medysk beoardiele troch Dr. Thomas Klein, mei bydragen fan Dr. Sarah Mitchell en prof. dr. Hans Weber.
Betrouberens
Bewiis-basearre ynterpretaasje mei dúdlike ferfolchpaadkes om alarm te ferminderjen.




Medyske disclaimer
Dit artikel is allinnich foar ûnderwiisdoelen en foarmet gjin medysk advys. Rieplachtsje altyd in kwalifisearre soarchferliener foar besluten oer diagnoaze en behanneling.
Publisearre · Nim kontakt op mei it redaksjeteam
Publisearre troch Kantesti Ltd, registrearre yn Ingelân en Wales, bedriuwsnûmer. 17090423, Londen, Feriene Keninkryk.
