A positive stool result usually identifies a bacterial intestinal infection; mild cases often need fluids rather than antibiotics. Severe right-sided abdominal pain, dehydration, or signs of sepsis require urgent assessment—even when the test appears to explain your symptoms.

Հիմնական եզրակացությունները
- Positive stool PCR means Yersinia genetic material was detected; it does not measure bacterial viability or prove that every symptom has the same cause.
- Incubation is typically 4–7 days, although symptoms can begin 1–14 days after exposure.
- Appendicitis mimic occurs because Yersinia can affect the terminal ileum and nearby lymph nodes; a positive stool test cannot exclude actual appendicitis.
- Supportive care is usually sufficient for uncomplicated illness in an otherwise healthy person who can drink and is improving.
- Oral rehydration replaces water and salts; adults without fluid restrictions can often start with approximately 200–250 mL after each loose stool.
- Հակաբիոտիկներ are considered for severe disease, bloodstream infection, or selected high-risk patients—not automatically for every positive result.
- Higher-risk situations include iron overload, deferoxamine treatment, significant immunosuppression, and serious underlying illness.
- Անհապաղ գնահատում is needed for worsening localized abdominal pain, inability to retain fluids, confusion, fainting, or substantial intestinal bleeding.
- Հետագա այցելություն is sensible when diarrhea lasts 14 days or longer; routine PCR clearance testing is usually unnecessary after uncomplicated recovery.
What does a Yersinia enterocolitica positive result mean?
A Yersinia enterocolitica positive stool result means the laboratory detected this bacterium or its genetic material. With compatible diarrhea, it usually supports intestinal infection; many uncomplicated cases improve over 1–3 weeks with hydration, while severe illness or high-risk conditions may justify antibiotics.

A positive result is not a severity score. Someone having 3 loose stools daily while drinking normally needs a different assessment from someone with persistent vomiting, low urine output, and worsening abdominal tenderness—even if both laboratory reports contain exactly the same wording.
The test method changes the interpretation. A report saying PCR detected identifies a genetic target, whereas a positive culture demonstrates growth of viable organisms; neither method alone tells a clinician whether the bacterium has entered the bloodstream or whether a separate abdominal emergency is present.
An unexpected result deserves clarification rather than automatic treatment. If you have had no diarrhea, have already recovered, or have 2 organisms detected on a multiplex panel, ask why the sample was collected and whether the finding matches the timing and pattern of your illness.
Կանտեստին մի է AI արյան անալիզատոր that can help explain accompanying laboratory abnormalities, but stool microbiology requires separate clinical interpretation. Our ընկերության մասին տեղեկություն describes our role; the immediate decision here depends on symptoms, hydration, examination, and individual risk—not an AI-generated infection label.
How reliable is a Yersinia stool PCR positive result?
A Yersinia stool PCR positive result is usually meaningful when symptoms fit, but PCR detects genetic material rather than proving that live bacteria remain. There is no universal cycle-threshold cutoff that separates active Yersinia illness from residual detection, and 2 different laboratories may use different panels.
Multiplex stool panels can detect more than 1 organism, and a second positive target can change treatment safety. The 2017 IDSA infectious-diarrhea guideline advises interpreting molecular results clinically because nucleic-acid detection does not necessarily establish viable organisms or identify the principal cause of symptoms (Shane et al., 2017).
Culture has a different purpose from repeating PCR. When susceptibility testing or public-health investigation is needed, ask whether the laboratory can perform ռեֆլեքսային ցանքս; Yersinia may require selective methods, and a standard stool culture does not necessarily include every organism listed on a molecular panel.
A negative culture after positive PCR does not automatically prove that the PCR was wrong. Recent antibiotics, transport conditions, low organism numbers, and culture technique can reduce recovery; the useful distinction is between 2 tests answering different questions, not a simple contest over which result wins.
Reports that say detected or not detected are որակական, not measures of bacterial burden; our որակական ընդդեմ քանակական ուղեցույցի explains that distinction. Persistent molecular detection also occurs with other organisms, but the timeline described in our ադենովիրուսի արտազատման բացատրությունը should not be transferred directly to Yersinia.
Which Yersinia infection symptoms fit the result?
Yersinia infection symptoms commonly include diarrhea, fever, and abdominal pain; younger children may have bloody diarrhea, while older children and adults can develop prominent right-lower abdominal pain. Symptoms typically start 4–7 days after exposure, with a reported range of 1–14 days.
Timing helps identify plausible exposures without proving their source. If symptoms began 6 days after a shared meal, that meal falls within the usual incubation window; symptoms beginning within a few hours are less typical for newly acquired Yersinia and should prompt consideration of other causes.
Undercooked pork is a recognized source, but contaminated water, unpasteurized milk, and cross-contamination can also transmit Yersinia. Refrigeration is not a complete safeguard: Yersinia can grow at refrigerator temperatures, so storing food at approximately 4°C does not replace adequate cooking and careful separation of raw foods.
Abdominal pain can outweigh diarrhea. The terminal ileum contains substantial lymphoid tissue, and involvement of this region can produce localized tenderness rather than a diffuse stomach bug; Bottone's review in Clinical Microbiology Reviews describes the intestinal and extraintestinal spectrum of yersiniosis (Bottone, 1997).
Record stool frequency, temperature, fluid intake, and pain location for 24 hours rather than relying only on stool appearance. Our կղանքի խտության ուղեցույցը can help describe changes, but a stool shape or color cannot identify Yersinia or determine whether antibiotics are needed.
Why can Yersinia mimic appendicitis?
Yersinia can mimic appendicitis by causing terminal ileitis և mesenteric lymph-node enlargement near the appendix. These 2 processes can produce fever and right-lower abdominal pain; a positive stool result does not exclude simultaneous appendicitis or remove the need for examination and, sometimes, imaging.
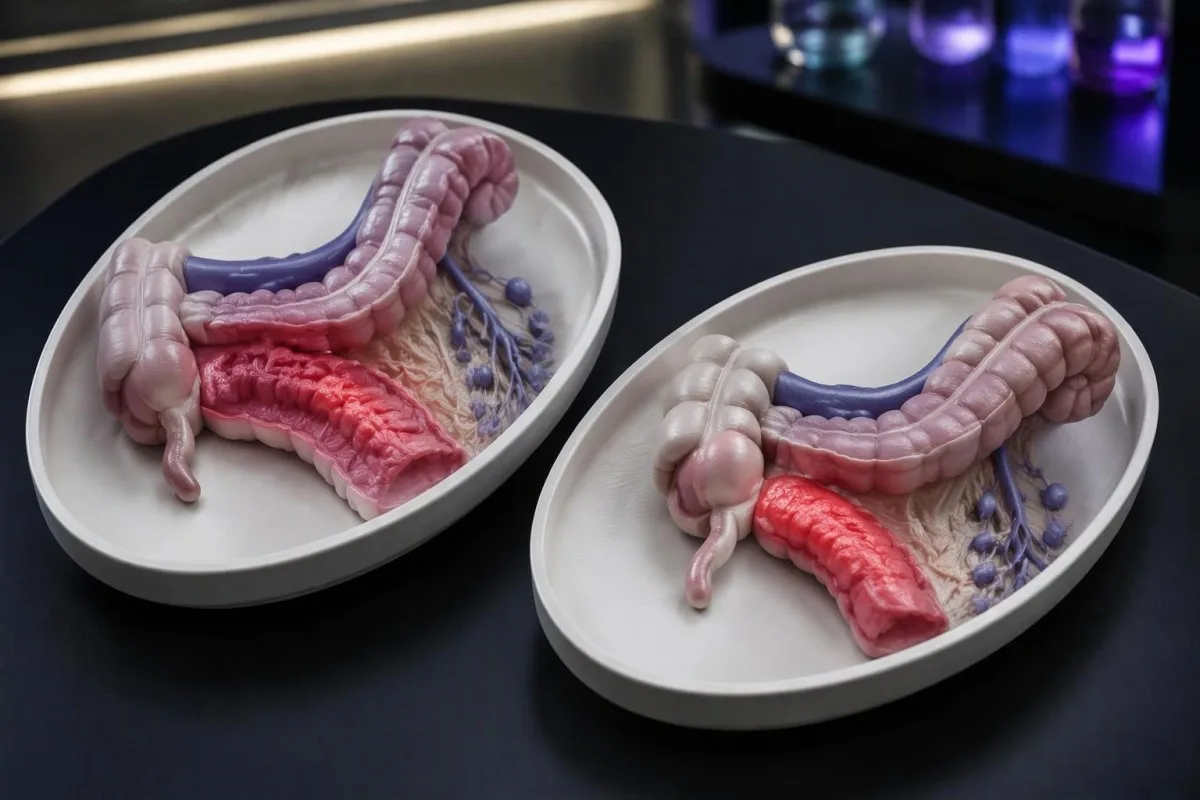
The anatomical explanation matters more than the stool label. The terminal ileum joins the cecum close to the appendix, so irritation of nearby bowel and lymph nodes can create a similar pain pattern; the term pseudoappendicitis describes the mimic, not a reliable diagnosis that can be made at home.
Worsening focal pain needs reassessment even if diarrhea is improving. For example, a hypothetical 16-year-old with fewer loose stools but increasing right-sided tenderness should not wait for repeat stool testing, because improvement in one symptom does not establish that the appendix or surrounding abdomen is safe.
Normal inflammatory markers do not settle the question. A white-cell count of 7.5 × 10⁹/L or a CRP of 3 mg/L can occur early in abdominal disease; our ապենդիցիտի հետազոտման սահմանափակումները explain why normal laboratory results cannot reliably rule out appendicitis.
Ultrasound is often considered first in children and pregnancy, while CT or MRI may be selected according to the clinical situation and local pathways. Kantesti's educational explanations cannot assess guarding, pain with movement, or imaging findings; severe or progressive localized pain warrants urgent in-person assessment rather than a 24-hour home experiment.
Which symptoms require urgent or emergency assessment?
Severe or worsening abdominal pain, confusion, fainting, inability to retain fluids, or substantial intestinal bleeding require urgent assessment. Fever of 39°C or higher merits prompt advice when accompanied by significant illness; a baby younger than 3 months with a temperature of 38°C or higher needs urgent medical assessment.

Emergency symptoms are not defined by fever alone. New confusion, very rapid breathing, collapse, cold or mottled extremities, or severe weakness can indicate systemic illness even without a temperature above 39°C; use your local emergency service rather than waiting for a laboratory callback.
Dehydration can become serious before a person looks dramatically unwell. Markedly reduced urine, dizziness on standing, a dry mouth, or inability to keep small sips down should prompt assessment; no urine for roughly 8–12 hours in an adult is concerning, but infants and frail people may need help much earlier.
Visible blood mixed with diarrhea generally deserves same-day advice, while large-volume bleeding, faintness, or new black tarry stool warrants emergency assessment. Our կղանքում արյան վերաբերյալ ուղեցույցը explains why color and quantity matter, but a known Yersinia result should not be used to dismiss ongoing blood loss.
A multiplex panel reporting both Yersinia and Shiga toxin creates a treatment-safety issue. Some antibiotic decisions appropriate for Yersinia may be inappropriate for Shiga toxin-producing E. coli; our Shiga toxin result guidance explains the distinction, and the 2 findings need clinician review before treatment.
When is supportive care enough for Yersinia?
Supportive care is usually enough for uncomplicated Yersinia diarrhea when a person can drink, has no concerning abdominal findings, and is improving. Oral rehydration solution replaces both water and salts; an adult without fluid restrictions can often start with approximately 200–250 mL after each loose stool.

Small, frequent amounts can work better than a large drink during nausea. Try approximately 5–10 mL every 1–2 minutes, increasing gradually if tolerated; prepare commercial oral rehydration sachets using exactly the specified water volume, because making them stronger or weaker changes their salt and glucose balance.
Children need weight-based assessment rather than an adult drinking target. NICE guideline CG84 recommends 50 mL/kg of oral rehydration solution over 4 hours, plus maintenance fluid, for children under 5 with clinical dehydration; a hypothetical 20 kg child would receive 1,000 mL for the deficit under an appropriate care plan (NICE, 2009).
Continue breastfeeding and resume usual age-appropriate food as tolerated rather than fasting for 24 hours. Our childhood gastroenteritis care guide discusses practical hydration observations, although the cause here is bacterial; infants, children with persistent vomiting, and anyone becoming unusually sleepy need reassessment.
Avoid loperamide when diarrhea is bloody, fever is present, or invasive intestinal disease is suspected, and do not give it to children for infectious diarrhea without specific advice. Kidney function may temporarily worsen during fluid loss; our dehydration and eGFR explanation shows why a new abnormal result needs comparison with baseline, not an immediate chronic-disease label.
When are antibiotics appropriate for Yersinia treatment?
Yersinia enterocolitica treatment may include antibiotics for severe illness, bloodstream infection, extraintestinal disease, or selected high-risk patients. The 2017 IDSA guideline lists trimethoprim-sulfamethoxazole as a treatment option, with cefotaxime or ciprofloxacin as alternatives; drug choice depends on susceptibility, patient factors, and infection site.
A positive PCR alone does not establish an antibiotic benefit. The evidence for shortening ordinary, self-limited enteritis is limited, whereas systemic disease creates a much clearer treatment indication; this distinction is reflected in the IDSA guideline's organism-specific recommendations and overall emphasis on targeted treatment (Shane et al., 2017).
Yersinia commonly resists ampicillin and many early-generation cephalosporins because of beta-lactamase activity. Do not assume leftover amoxicillin or a familiar urinary-infection prescription will work; our Salmonella treatment comparison illustrates why identifying a bacterial pathogen is only 1 step in deciding whether and how to treat.
Age, pregnancy, kidney function, allergies, and interacting medicines can change the safest option. Trimethoprim-sulfamethoxazole is generally avoided in infants younger than 2 months, while fluoroquinolones carry important adverse-effect restrictions; a clinician may choose a different agent or hospital-based therapy rather than applying an adult oral regimen to everyone.
There is no single course length that safely covers uncomplicated diarrhea, bacteremia, and a deep-seated focus. Blood cultures, susceptibility results, and response over the first 48–72 hours may guide treatment changes; our Campylobacter antibiotic guide provides another example of why organism-specific recommendations should not be exchanged between infections.
Who is at higher risk of severe Yersinia infection?
Iron overload and deferoxamine treatment are particularly relevant risk factors for severe Yersinia disease. Significant immunosuppression and serious underlying illness also lower the threshold for clinical assessment; a patient with 1 of these risk factors should contact their treating team promptly rather than assuming that ordinary home care is sufficient.
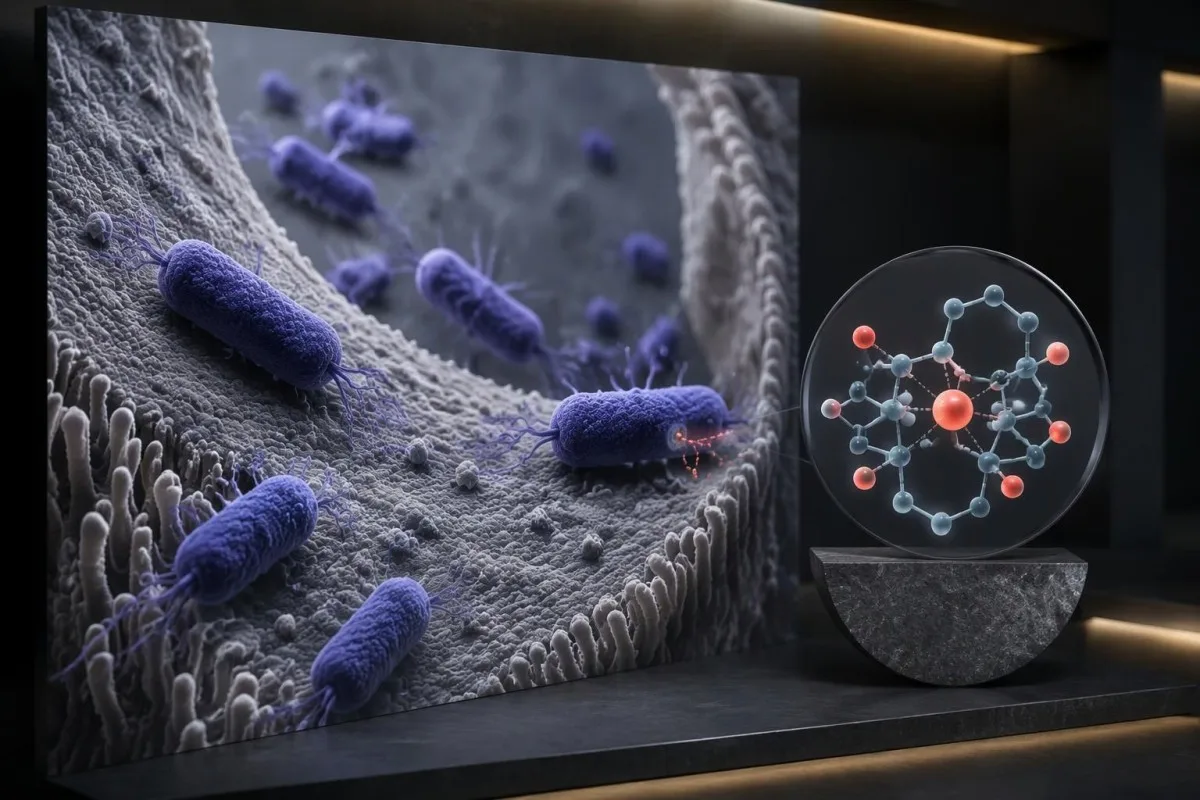
Deferoxamine can bind iron in a form that Yersinia can exploit, helping explain its distinctive association with invasive disease. Bottone's microbiological review discusses iron-dependent virulence and the clinical relevance of iron-loading disorders (Bottone, 1997); this is a biological risk mechanism, not a claim that every patient receiving chelation will become severely ill.
People with transfusion-dependent anemia, known hemochromatosis, or prescribed deferoxamine should tell the assessing clinician about those conditions immediately. If fever or abdominal symptoms develop during treatment, contact the prescribing team the same day; medication interruption or modification is a clinical decision, not a reason to independently abandon long-term chelation.
An isolated ferritin of 800 ng/mL during acute illness does not diagnose iron overload. Ferritin rises as an acute-phase reactant, so previous results, transferrin saturation, transfusion history, and the clinical setting matter; our երկաթի վահանակի մեկնաբանման ուղեցույցը explains why a raised storage marker cannot be interpreted alone.
Kantesti AI can help explain why 2 ferritin results taken during different illness states are not directly comparable, but it cannot determine bloodstream spread from ferritin. People receiving chemotherapy, transplant medicines, or substantial immunosuppression need individualized advice; fever, deterioration, or localized pain should trigger assessment even when diarrhea appears relatively mild.
Which blood tests help assess severity and dehydration?
CBC, CRP, electrolytes, and kidney-function tests can help assess the consequences of Yersinia illness, but they do not confirm the stool diagnosis. In an adult, a creatinine increase of at least 0.3 mg/dL, approximately 26.5 µmol/L, within 48 hours meets a standard acute-kidney-injury criterion and needs clinical interpretation.
A high inflammatory marker does not tell you whether the appendix is safe or whether antibiotics will help. For example, a hypothetical CRP of 65 mg/L may accompany several inflammatory conditions; our WBC և CRP համեմատությունը explains why disagreement between markers can reflect timing rather than a diagnostic contradiction.
Trend interpretation is more useful than reading a single flagged value. A creatinine rise from 70 to 100 µmol/L over 48 hours can be clinically meaningful even when the second result is close to a laboratory's reference interval; the change and the person's urine output matter more than whether the report prints an asterisk.
Electrolyte losses can cause weakness, cramps, or palpitations, especially when vomiting accompanies diarrhea. A potassium of 2.9 mmol/L is below usual adult reference intervals and warrants prompt clinical review; replacement decisions depend on symptoms, ECG findings, kidney function, and the ability to drink—not simply choosing a high-potassium food.
Կանտեստին մի է AI արյան անալիզի մեկնաբանություն հարթակ that can organize accompanying results and explain changes between 2 time points, without diagnosing invasive yersiniosis. Our BUN և կրեատինինի ուղեցույցը adds context for fluid-loss patterns; blood cultures are a separate clinician-directed test when systemic infection is suspected.
How does Yersinia spread, and when can you return to work?
Yersinia spreads through contaminated food or water and through fecal contamination of hands and surfaces. Many gastroenteritis policies require at least 48 hours without diarrhea or vomiting before returning to school or work, but food handlers, healthcare workers, and childcare staff may face additional local requirements.

Wash hands with soap and water for at least 20 seconds after using the toilet and before preparing food. Alcohol hand rub is not a substitute when hands are visibly soiled; clean frequently touched bathroom surfaces using an appropriate household product and follow its dilution and contact-time instructions.
Avoid preparing food for other people while symptomatic and during the exclusion period recommended locally. Keep raw meat and its utensils separate from ready-to-eat foods, because 1 contaminated cutting board can transfer organisms to food that will not receive further cooking; washing raw meat can also spread droplets around the kitchen.
The usual 48-hour rule is a practical public-health measure, not proof that every organism has disappeared from stool. Our post-recovery contagiousness explanation illustrates the difference between symptom resolution and detection, although Yersinia and norovirus have different biology and should not be assigned identical shedding timelines.
Household contacts without symptoms do not routinely need preventive antibiotics or stool testing just because 1 family member is positive. If several people develop diarrhea after a shared exposure, report that pattern to the clinician or local public-health service; a cluster may justify investigation even when each person's illness seems manageable.
How long does recovery take, and do you need another stool test?
Yersinia diarrhea can last 1–3 weeks and sometimes longer; routine repeat PCR is usually unnecessary after uncomplicated clinical recovery. Diarrhea continuing for 14 days or more deserves review, especially when there is weight loss, blood, persistent fever, or focal abdominal pain rather than a steadily improving pattern.

Clinical improvement means more than a negative laboratory result. Over 2–3 days, falling stool frequency, better drinking, improving appetite, and normalizing urine output are useful recovery signals; worsening focal pain or renewed fever moves the decision back toward assessment even if the diarrhea itself has eased.
A repeat positive PCR cannot reliably distinguish persistent viable organisms from residual genetic material. If symptoms remain significant, the next useful step may be culture, susceptibility testing, a broader stool investigation, or abdominal assessment—not repeatedly ordering the same multiplex test until it becomes negative.
Temporary food intolerance and postinfectious bowel symptoms can follow enteritis, but persistent inflammation needs a different evaluation. Fecal calprotectin can rise during bacterial intestinal illness, so 1 elevated result does not establish Crohn's disease; our calprotectin follow-up guide explains why timing and symptom persistence affect repeat testing.
A hypothetical adult still having diarrhea on day 18 should be assessed for hydration, treatment history, alternative pathogens, and noninfectious causes rather than assuming antibiotic resistance. New diarrhea after antibiotics also deserves review for antibiotic-associated complications; the presence of an earlier Yersinia result does not explain every later gastrointestinal symptom.
Can Yersinia cause joint or skin symptoms after diarrhea?
Yersinia can trigger reactive arthritis and erythema nodosum after the intestinal illness. Reactive joint symptoms often begin approximately 1–4 weeks after enteritis; a painful swollen joint, tender shin nodules, or eye pain should be assessed rather than automatically treated as evidence that intestinal bacteria are still active.
Reactive arthritis is an immune-mediated response, not simply bacteria spreading from stool into every painful joint. Knees and ankles may be affected asymmetrically; a new hot swollen joint with fever still needs urgent assessment because septic arthritis and other causes cannot be excluded from the timing alone.
Erythema nodosum usually produces tender nodules over the shins and has several possible triggers. Appearance 2 weeks after diarrhea can fit a postinfectious pattern, but medicines, inflammatory bowel disease, and other conditions remain relevant; examination is more informative than trying to diagnose the nodules from a positive stool report.
HLA-B27 can be associated with susceptibility or persistence of reactive arthritis, but it is not a routine screening test after uncomplicated yersiniosis. Our HLA-B27 interpretation guide explains why 1 genetic result cannot establish the cause of joint pain or predict an individual person's course.
Antibiotics for the original enteritis have not reliably been shown to prevent postinfectious complications. Joint treatment depends on the assessment and may differ from intestinal treatment; new eye pain, light sensitivity, or reduced vision needs urgent same-day care because an inflammatory eye complication can threaten vision even when diarrhea resolved weeks earlier.
How should you prepare your results for clinical review?
Bring the complete stool report, symptom timeline, medication list, and any accompanying blood results to clinical review. A concise 24–48-hour record of stool frequency, temperature, drinking, urine output, and pain location helps the clinician distinguish uncomplicated recovery from dehydration, appendicitis-like illness, or systemic disease.
Record when symptoms started and when the sample was collected, because those 2 dates answer different questions. Add whether antibiotics were taken before sampling and whether another organism was detected; these details can explain a culture-PCR mismatch and can materially change the safest treatment discussion.
Կանտեստին մի է AI-ով աշխատող արյան թեստի վերլուծության գործիք that accepts laboratory PDFs or photos and provides explanations in approximately 60 seconds, but that output is not a diagnosis or emergency assessment. Our բժշկական վավերացման տեղեկատվությունը describes evaluation and oversight; performance on blood-report interpretation should not be assumed to establish accuracy for stool-PCR diagnosis.
Check units and collection dates before comparing 2 results. Creatinine reported in mg/dL and µmol/L, or CRP measured before and after hydration, can look contradictory without proper context; an AI explanation should remain anchored to the original report and should never silently replace missing microbiology or examination findings with assumptions.
Laboratory reports can include names, dates of birth, and other identifiers, so share only what is needed for the task and consider consent when handling a family member's results. Our գաղտնիության և տվյալների մասին տեղեկությունները explains our approach; regardless of the interpretation method, do not delay urgent care to complete a digital report review.
Հետազոտական հրապարակումներ և արյան քննությունների մեկնաբանման սահմանափակումները
The Yersinia treatment discussion is supported by infectious-diarrhea guidance and microbiological literature, not by general blood-test publications. The 2 Zenodo guides listed below provide supplementary laboratory context; they are not Yersinia treatment trials and do not establish that an AI tool can diagnose intestinal infection.
The aPTT and clotting guide addresses coagulation interpretation, which is separate from stool pathogen detection. An uncomplicated positive Yersinia result does not routinely justify ordering aPTT, D-dimer, or Protein C; testing becomes relevant only when a clinician identifies an additional question, such as a severe systemic complication or a separate clotting concern.
The serum-protein guide explains albumin and globulin patterns that may become relevant during prolonged illness. An albumin of 30 g/L can reflect several processes, including inflammation, reduced intake, or protein loss; our շիճուկային սպիտակուցների մեկնաբանման ուղեցույց explains why that value cannot identify Yersinia or determine antibiotic necessity.
Kantesti's Zenodo guides should therefore be read as supporting educational material, while the 2017 IDSA guideline and organism-specific literature support the infection discussion. A repository DOI provides a persistent identifier; it does not, by itself, demonstrate peer review, clinical effectiveness, or validation of a pathogen-specific diagnostic claim.
Մեր բժշկական բովանդակության չափանիշներ describe how we distinguish source-backed guidance from illustrative examples. Before ending your review, identify 3 practical decisions: whether urgent assessment is needed, whether supportive care is adequate, and whether your risk factors or ongoing symptoms require clinician-directed testing or treatment.
Հաճախ տրվող հարցեր
Արդյո՞ք Yersinia enterocolitica-ի դրական թեստի պատասխանը նշանակում է, որ ինձ հակաբիոտիկներ են պետք:
Կղանքի նմուշում Yersinia enterocolitica-ի դրական արդյունքը ինքնաբերաբար չի նշանակում, որ հակաբիոտիկներ են անհրաժեշտ։ Չբարդացած վարակներից շատերն անցնում են 1–3 շաբաթվա ընթացքում՝ բերանային ռեհիդրատացիայի և օժանդակ բուժման շնորհիվ, թեև լուծը կարող է ավելի երկար տևել։ Հակաբիոտիկներ նշանակելու հարցը քննարկվում է ծանր հիվանդության, արյան վարակի, աղիքից դուրս ախտահարման կամ որոշ բարձր ռիսկի խմբերի պացիենտների դեպքում։ Երկաթի գերբեռնվածության, դեֆերոքսամինով բուժման և նշանակալի իմունաճնշման մասին պետք է անհապաղ հայտնել բուժող բժշկին։
Կարո՞ղ է Yersinia-ի կղանքի ՊՇՌ թեստի դրական արդյունքը կեղծ դրական լինել:
Yersinia-ի նկատմամբ կղանքի PCR-ի դրական արդյունքը երբեմն կարող է անսպասելի կամ մոլորեցնող լինել, հատկապես երբ ախտանշանները չեն համապատասխանում, սակայն դրական արդյունքը չպետք է պարզապես անտեսել։ PCR-ը հայտնաբերում է գենետիկական նյութը և չի կարող ապացուցել, որ կենսունակ միկրոօրգանիզմներ դեռ կան, կամ որ Yersinia-ն բացատրում է բոլոր ախտանշանները։ Եթե հայտնաբերվել է 2 հարուցիչ, կամ հիվանդությունն արդեն անցել է, կլինիկական մեկնաբանությունն ու երբեմն նաև կուլտուրան ավելի օգտակար են, քան PCR-ն ավտոմատ կերպով կրկնելը։ Թեստի արդյունավետությունը կախված է լաբորատոր մեթոդից, իսկ ակտիվ հիվանդության համար Yersinia-ի ցիկլի շեմի համընդհանուր արժեք գոյություն չունի։
Կարո՞ղ է Երսինիան ապենդիցիտի նման ցավ առաջացնել:
Երսինիան կարող է ապենդիցիտին նման ցավ առաջացնել՝ ախտահարելով տերմինալ զստաղին և հարակից միջընդերային ավշային հանգույցները։ Այս երկու անատոմիական հատվածները գտնվում են որդանման ելունի մոտ և կարող են աջ ստորին որովայնային ցավ ու ջերմություն առաջացնել։ Կղանքի դրական թեստը չի բացառում իրական ապենդիցիտը, իսկ լեյկոցիտների կամ CRP-ի նորմալ ցուցանիշները վստահորեն չեն բացառում այն։ Ուժեղ, տեղայնացված կամ վատթարացող ցավի դեպքում անհրաժեշտ է անհապաղ զննում, իսկ երբեմն՝ ուլտրաձայնային հետազոտություն, ՀՏ կամ ՄՌՏ։
How long does Yersinia enterocolitica infection last?
Yersinia intestinal illness often lasts 1–3 weeks, but symptoms can persist longer. Diarrhea lasting 14 days or more deserves clinical review, especially when accompanied by weight loss, blood, fever, or localized pain. Routine repeat PCR is usually unnecessary after uncomplicated recovery because genetic material may remain detectable without proving ongoing viable infection. Joint symptoms can begin approximately 1–4 weeks after enteritis and require a separate assessment.
Which antibiotics treat Yersinia enterocolitica?
The 2017 IDSA infectious-diarrhea guideline lists trimethoprim-sulfamethoxazole for Yersinia enterocolitica, with cefotaxime or ciprofloxacin as alternatives. Yersinia commonly resists ampicillin and many early-generation cephalosporins, so leftover antibiotics are not a safe substitute for a prescription. Selection depends on illness severity, susceptibility results, age, pregnancy, kidney function, and medication interactions. There is no single dose or course length suitable for uncomplicated enteritis, bacteremia, and every extraintestinal complication.
When should I seek urgent care after a positive Yersinia test?
Seek urgent assessment for severe or worsening abdominal pain, inability to keep fluids down, substantially reduced urine, fainting, confusion, or significant intestinal bleeding. A baby younger than 3 months with a temperature of 38°C or higher requires urgent medical assessment. People with iron overload, deferoxamine treatment, or significant immunosuppression should obtain prompt individualized advice rather than relying on routine home care. Do not wait for a repeat stool result if symptoms suggest dehydration, appendicitis, or systemic illness.
Is Yersinia contagious after diarrhea stops?
Yersinia can be transmitted through fecal contamination, and symptom resolution does not prove that stool shedding has ended. Many school and workplace gastroenteritis policies require at least 48 hours without diarrhea or vomiting, but local rules may be stricter for food handlers, healthcare workers, or childcare staff. Continue careful handwashing and avoid preparing food for others during the recommended exclusion period. Routine clearance testing is not usually needed after uncomplicated recovery unless a clinician or public-health authority requests it.
Ստացեք ձեր արյան անալիզի արդյունքների բացատրությունը
Վերբեռնեք ձեր լաբորատոր հաշվետվությունը, և Kantesti-ի AI-ն վայրկյանների ընթացքում պարզ լեզվով կբացատրի յուրաքանչյուր կենսամարկեր։ Օգտագործում է ավելի քան 2 միլիոն մարդ ամբողջ աշխարհում։.
Հղումներ
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTT-ի նորմալ միջակայքը․ D-Dimer-ի և Protein C-ի՝ արյան մակարդման ուղեցույց։. Kantesti AI բժշկական հետազոտություն։. ԴՕԻ
- Klein, T., Mitchell, S., & Weber, H. (2026). Շիճուկային սպիտակուցների ուղեցույց․ գլոբուլիններ, ալբումին և A/G հարաբերակցության արյան անալիզ։. Kantesti AI բժշկական հետազոտություն։. ԴՕԻ
- Shane AL և այլք (2017)։. Վարակիչ փորլուծության ախտորոշման և կառավարման վերաբերյալ Վարակիչ հիվանդությունների ամերիկյան ընկերության 2017 թվականի կլինիկական պրակտիկայի ուղեցույցներ։. Clinical Infectious Diseases։. ԴՕԻ
- Bottone EJ (1997). Yersinia enterocolitica: the charisma continues. Clinical Microbiology Reviews։
- Առողջապահության և խնամքի գերազանցության ազգային ինստիտուտ (2009)։. Գաստրոէնտերիտով պայմանավորված լուծ և փսխում մինչև 5 տարեկան երեխաների շրջանում. ախտորոշում և վարում։. NICE Clinical Guideline CG84.
- 2 միլիոն+Վերլուծված թեստեր
- 127+Երկրներ
- 100+Լեզուներ
Բժշկական թիմի մասին


E-E-A-T վստահության ազդանշաններ
Փորձառություն
Բժշկի կողմից ղեկավարվող կլինիկական վերանայում՝ լաբորատոր մեկնաբանության աշխատանքային հոսքերի համար։.
Մասնագիտություն
Լաբորատոր բժշկության կենտրոնացում՝ այն բանի վրա, թե ինչպես են բիոմարկերները դրսևորվում կլինիկական համատեքստում։.
Հեղինակություն
Բժշկական գրախոսությունը՝ դոկտոր Թոմաս Քլայնի կողմից, դոկտոր Սառա Միտչելի և պրոֆ. դոկտոր Հանս Վեբերի մասնակցությամբ։.
Հուսալիություն
Ապացույցների վրա հիմնված մեկնաբանություն՝ հստակ հետագա քայլերի ուղիներով՝ ահազանգերը նվազեցնելու համար։.





Բժշկական հրաժարում պատասխանատվությունից
Այս հոդվածը միայն կրթական նպատակների համար է և չի հանդիսանում բժշկական խորհրդատվություն։ Ախտորոշման և բուժման որոշումների համար միշտ խորհրդակցեք որակավորված բուժաշխատողի հետ։.
Հրապարակված · Կապ հաստատել խմբագրական թիմի հետ
Հրատարակված է Kantesti Ltd-ի կողմից, գրանցված Անգլիայում և Ուելսում, ընկերության համար. 17090423, Լոնդոն, Միացյալ Թագավորություն։.
