An ulcerative colitis blood test can reveal systemic inflammation, anaemia, nutritional effects and treatment safety issues, but no blood result confirms ulcerative colitis by itself. Diagnosis normally combines symptoms, stool testing, colonoscopy and tissue examination.

Հիմնական եզրակացությունները
- Ախտորոշում: No ulcerative colitis blood test confirms the condition; colonoscopy with tissue samples is usually needed to establish the diagnosis and extent.
- CRP և ESR: CRP below 5 mg/L and a low ESR often indicate less systemic inflammatory activity, but normal results do not exclude active colitis.
- CBC: Haemoglobin below 120 g/L in many non-pregnant adult women or below 130 g/L in adult men suggests anaemia, which may reflect intestinal blood loss or chronic inflammation.
- Թրոմբոցիտներ: A platelet count above 450 × 10⁹/L can accompany active inflammatory disease, although infection, iron deficiency and other causes can produce the same pattern.
- Ալբումին: Albumin below 30 g/L is a concerning marker in severe colitis because it may reflect inflammatory protein loss, reduced intake or intestinal protein leakage.
- Արտաթորանքի թեստավորում: Faecal calprotectin is not a blood test, but values above about 150 µg/g commonly support active intestinal inflammation and help decide whether endoscopic assessment is needed.
- Flare assessment: Clinicians interpret trends in CRP, haemoglobin, albumin and platelets alongside stool frequency, urgency, weight and objective stool or endoscopic findings.
- Limits: A normal CRP, negative antibody panel or normal white-cell count cannot safely rule out ulcerative colitis or prove remission.
What an ulcerative colitis blood test can and cannot show
Blood tests support ulcerative colitis assessment but do not confirm the diagnosis. They can show systemic inflammation, anaemia, dehydration, low protein, liver involvement and medication risks; they cannot demonstrate the characteristic continuous mucosal pattern that endoscopy and tissue examination provide.

A raised C-ռեակտիվ սպիտակուց, elevated ESR, low haemoglobin or high platelet count can make active inflammatory bowel disease more plausible, but each finding has alternatives. For example, CRP above 10 mg/L may occur with respiratory infection, urinary infection, obesity or another inflammatory condition, so the result is not specific to colitis.
The 2019 ACG guideline describes ulcerative colitis as a diagnosis built from clinical, endoscopic and histological information rather than one laboratory threshold (Rubin et al., 2019). Our բժշկական վավերացման չափանիշները reflect the same boundary: an interpreted result can organise evidence, but it cannot replace a gastroenterology assessment.
A hypothetical 28-year-old with six loose stools daily, CRP 38 mg/L and haemoglobin 108 g/L has a pattern that deserves prompt evaluation, not an automatic label. The combination suggests active inflammation with anaemia, whereas CRP 38 mg/L alone could reflect many conditions; stool pathogen testing and colonoscopy still decide the diagnosis.
CRP, ESR and white cells during a flare
CRP, ESR and white-cell counts measure inflammatory response, not ulcerative-colitis-specific injury. CRP changes relatively quickly over roughly 24 to 48 hours, ESR changes more slowly, and the white-cell count is particularly vulnerable to infection, corticosteroids and stress.

Many laboratories report adult CRP as normal below 5 mg/L, although some use below 3 mg/L; a result of 20 mg/L therefore signals a meaningful inflammatory response but does not identify its source. ESR reference limits vary by age and sex, and an ESR of 35 mm/hour may remain elevated after CRP has already fallen.
A white-cell count above about 11 × 10⁹/L can accompany active colitis, but prednisolone may raise neutrophils through demargination without indicating worsening intestinal tissue response. Conversely, immunosuppressive treatment can blunt leukocytosis, which is why a normal count of 6 × 10⁹/L cannot exclude a flare.
CRP and ESR disagreement is common: a person may have CRP 4 mg/L with ESR 42 mm/hour because of anaemia, age or another chronic condition. Our guide to WBC and CRP differences explains why trend, symptoms and sample timing are more informative than treating either marker as a yes-or-no test.
Why stool calprotectin often adds more than blood
Faecal calprotectin reflects neutrophil activity in the intestine and is often more gut-specific than CRP. It is not a blood test, but a result below about 50 µg/g generally supports low intestinal inflammatory activity, while values above 150 µg/g commonly justify repeat assessment or further investigation.

Calprotectin between 50 and 150 µg/g is an uncertainty zone rather than a diagnosis; recent infection, non-steroidal anti-inflammatory drugs and strenuous exercise can raise it. A result above 250 µg/g is more concerning for active intestinal inflammation, but it still cannot distinguish ulcerative colitis from Crohn disease, infection or some other bowel disorders.
The STRIDE-II treat-to-target update places symptoms, biomarkers such as CRP and faecal calprotectin, and endoscopic healing on different levels of assessment (Turner et al., 2021). That hierarchy matters because CRP 3 mg/L and calprotectin 420 µg/g are not contradictory: the first may be quiet systemically while the second detects local bowel activity.
A hypothetical patient whose calprotectin falls from 1,100 to 180 µg/g after treatment may be improving without having reached a low-risk target. Our calprotectin interpretation guide compares calprotectin with lactoferrin and explains why a sample collected during diarrhoea or shortly after NSAID use may need context.
Blood tests do not distinguish a flare from infection
A flare-like blood pattern can result from infection, so stool microbiology is part of safe assessment. C. difficile, Campylobacter, Salmonella, Shigella, parasites and cytomegalovirus-related disease can produce diarrhoea, raised CRP and low albumin that resemble ulcerative colitis activity.

CRP above 50 mg/L and a white-cell count of 14 × 10⁹/L may indicate severe inflammation, but the same numbers can occur with C. difficile colitis. Starting corticosteroids before appropriate infection assessment can worsen some infections, so clinicians often request stool toxin or molecular testing before escalating immunosuppression.
A positive C. difficile molecular assay can indicate toxin-gene carriage rather than toxin-mediated disease, particularly when stool is formed or symptoms have another explanation. The practical interpretation of C. difficile test combinations depends on symptoms, toxin results and the laboratory method, not on the blood count alone.
A negative stool pathogen panel also has limits: timing, prior antibiotics and the panel's organism coverage affect sensitivity. If a patient has CRP 12 mg/L, calprotectin 700 µg/g and persistent bloody diarrhoea after negative bacterial tests, endoscopic assessment may still be needed rather than assuming the result proves a non-infectious flare.
CBC results: anaemia, platelets and hidden disease burden
The complete blood count often reveals complications of ulcerative colitis rather than proving colitis itself. Low haemoglobin may reflect iron deficiency, inflammation, vitamin deficiency or ongoing intestinal loss; thrombocytosis can mirror inflammation but also occurs with iron deficiency and infection.

WHO thresholds commonly define anaemia as haemoglobin below 130 g/L in adult men and below 120 g/L in non-pregnant adult women, although pregnancy, age and local guidance change interpretation. A low MCV below 80 fL with low ferritin supports iron deficiency, while a normal or high MCV does not exclude mixed iron and B12 deficiency.
Platelets above 450 × 10⁹/L are often called thrombocytosis and may track inflammatory activity, but a platelet count of 510 × 10⁹/L is not specific. Iron deficiency can drive a similar rise, which is why clinicians pair the CBC with ferritin, transferrin saturation, CRP and the clinical history.
A hypothetical 52-year-old with haemoglobin 96 g/L, MCV 72 fL, ferritin 8 µg/L and platelets 590 × 10⁹/L has strong evidence of iron depletion with reactive thrombocytosis, not proof of a severe colitis flare. Reviewing low MCHC and red-cell patterns can help explain why the CBC needs iron studies rather than a single-marker conclusion.
Ferritin and iron studies when inflammation is present
Ferritin can be low in iron deficiency and falsely normal or high during inflammation. Ferritin below 30 µg/L commonly indicates depleted iron stores, but in active inflammatory bowel disease a value below 100 µg/L may still be compatible with iron deficiency when transferrin saturation is below 20%.

Transferrin saturation below 20% suggests insufficient circulating iron for red-cell production, while a high total iron-binding capacity often supports absolute iron deficiency. In inflammation, hepcidin reduces iron release and transferrin may fall, creating a mixed pattern in which ferritin 65 µg/L does not guarantee adequate iron stores.
A hypothetical patient with CRP 46 mg/L, ferritin 74 µg/L, serum iron 4 µmol/L and transferrin saturation 9% may have inflammation-associated functional iron restriction plus true deficiency. The երկաթի հետազոտությունների հղման ուղեցույցը explains why the result should be interpreted as a pattern and why oral or intravenous replacement depends on disease activity and clinical advice.
Iron deficiency can persist even when haemoglobin is 128 g/L, because storage depletion often precedes anaemia. Fatigue, reduced exercise tolerance and restless legs therefore deserve attention even when the CBC looks close to normal; repeat ferritin and saturation after treatment are more useful than assuming one normal haemoglobin ends the investigation.
Albumin, electrolytes and dehydration during active disease
Low albumin and abnormal electrolytes indicate disease burden or physiological stress, not a unique ulcerative-colitis signature. Albumin below 35 g/L may reflect inflammation, reduced intake or protein loss, while values below 30 g/L are more concerning when accompanied by frequent diarrhoea, oedema, tachycardia or weight loss.

Albumin has a half-life of roughly 20 days, so it may remain low after CRP improves and should not be used as an instant flare meter. A sodium level of 132 mmol/L may reflect gastrointestinal losses or excess free-water intake, whereas potassium below 3.0 mmol/L can become clinically urgent because diarrhoea and some medicines increase arrhythmia risk.
A patient with albumin 27 g/L, potassium 2.9 mmol/L and creatinine 118 µmol/L may need urgent fluid and electrolyte assessment even if CRP is only 18 mg/L. The reason is that the combined pattern suggests volume depletion and protein loss; each value alone is less informative than the physiological cluster.
Prealbumin changes faster than albumin but is also affected by inflammation, liver function and kidney disease, so it is not a pure nutrition score. Our prealbumin limitations guide explains why dietitian assessment, weight trend and intake history should accompany protein markers.
Liver blood tests and ulcerative-colitis-associated conditions
Liver tests can identify medication effects, bile-duct disease or fatty liver in people with ulcerative colitis, but they do not diagnose colitis. An alkaline phosphatase or gamma-glutamyl transferase rise may prompt evaluation for cholestasis, including primary sclerosing cholangitis, while ALT and AST more often reflect hepatocellular stress.
An ALT of 85 IU/L is approximately twice the upper limit in many laboratories, but reference limits differ and the result may reflect medication, metabolic liver disease or viral hepatitis. An alkaline phosphatase above 1.5 times the local upper limit, especially with raised GGT or bilirubin, deserves a different pathway from isolated mild ALT elevation.
Primary sclerosing cholangitis is associated with inflammatory bowel disease but is not identified by a single enzyme threshold; persistent cholestatic results may lead to ultrasound or magnetic-resonance cholangiography. A bilirubin of 45 µmol/L with alkaline phosphatase 360 IU/L is more suggestive of impaired bile flow than an isolated CRP rise, but obstruction and drug injury remain alternatives.
Medication review matters because thiopurines, biologics, corticosteroids and non-IBD medicines can alter liver results. A focused liver-test explanation can help organise ALT, AST, ALP, GGT and bilirubin, but persistent or worsening abnormalities require clinician-led investigation rather than self-directed drug changes.
Why IL-6 and other specialist markers are not routine tests
Specialist inflammatory markers such as interleukin-6 may rise in active disease, but they are not routine diagnostic substitutes for CRP, stool testing or endoscopy. IL-6 is biologically interesting because it drives hepatic acute-phase responses, yet assay availability, timing and treatment effects limit its individual clinical value.

An IL-6 concentration of 12 pg/mL may be above one assay's reference interval and normal for another, because methods and calibration differ. Cytokines also fluctuate over hours, so a single measurement can be less reproducible than CRP, whose routine interpretation is better standardised.
The reason IL-6 and CRP can disagree is biological: IL-6 may rise early, while the liver-derived CRP response follows later and can be altered by targeted treatment. Our IL-6 result guide explains why a specialist marker should answer a defined clinical question rather than become an expensive general screen.
Research assays may help compare populations or investigate treatment response, but a patient should not infer remission from IL-6 2 pg/mL if stool calprotectin is 600 µg/g and symptoms persist. The opposite combination also needs review, because a low cytokine result does not visualise the mucosa or exclude a structural complication.
Blood tests for treatment safety and biologic levels
Once ulcerative colitis is diagnosed, blood tests often monitor treatment safety and drug exposure rather than diagnose the disease. Liver enzymes, creatinine, full blood count and infection screening protect against avoidable harm; trough drug levels can help explain loss of response in selected situations.

For infliximab, a trough concentration below about 3 to 5 µg/mL may support underexposure in some maintenance settings, but targets vary by assay, treatment phase and whether the goal is symptom control or mucosal healing. Anti-drug antibodies and albumin affect interpretation, so a low level does not automatically mean the medicine has failed.
A hypothetical result showing infliximab 1.2 µg/mL, high anti-drug antibodies and CRP 28 mg/L suggests a pharmacokinetic problem more than a simple need for dose escalation. The infliximab level guide explains why timing must be recorded precisely: a sample drawn immediately after infusion is not a trough.
Before biologic or immunomodulator treatment, clinicians may check hepatitis B, tuberculosis risk, vaccination status and baseline CBC or liver tests. A normal CRP does not make a medicine safe, and a raised ALT does not automatically prove toxicity; the medication timeline and repeat testing are essential.
TPMT, blood counts and thiopurine safety
TPMT and NUDT15 testing can predict susceptibility to thiopurine toxicity, but they do not diagnose ulcerative colitis. A normal genotype or enzyme activity reduces one risk pathway; it does not remove the need for serial CBC and liver monitoring because toxicity can occur through other mechanisms.
TPMT activity below about 10 units per millilitre of red cells is often treated as low, while intermediate activity may require a reduced thiopurine dose; laboratories use different units and cutoffs. NUDT15 variants are especially relevant in some Asian and Hispanic populations, so a normal TPMT result alone may not capture inherited risk.
A falling neutrophil count below 1.5 × 10⁹/L or a rising ALT after starting azathioprine needs prompt clinical review, even if baseline testing was normal. The thiopurine metabolite guide shows why metabolite results can separate underdosing, non-adherence, preferential metabolism and toxicity patterns.
A blood test taken 3 days after treatment starts cannot reliably establish long-term safety because marrow suppression may develop later. Monitoring intervals vary by local protocol, but repeat CBC and liver tests during the first weeks and months are more informative than relying on one reassuring baseline panel.
Why endoscopy remains central to diagnosis
Colonoscopy with tissue examination remains central because it directly assesses mucosal distribution, severity and microscopic change. Blood tests can indicate inflammatory burden, but they cannot show whether inflammation is continuous from the rectum, whether ulcers are present, or whether microscopic features support an alternative diagnosis.
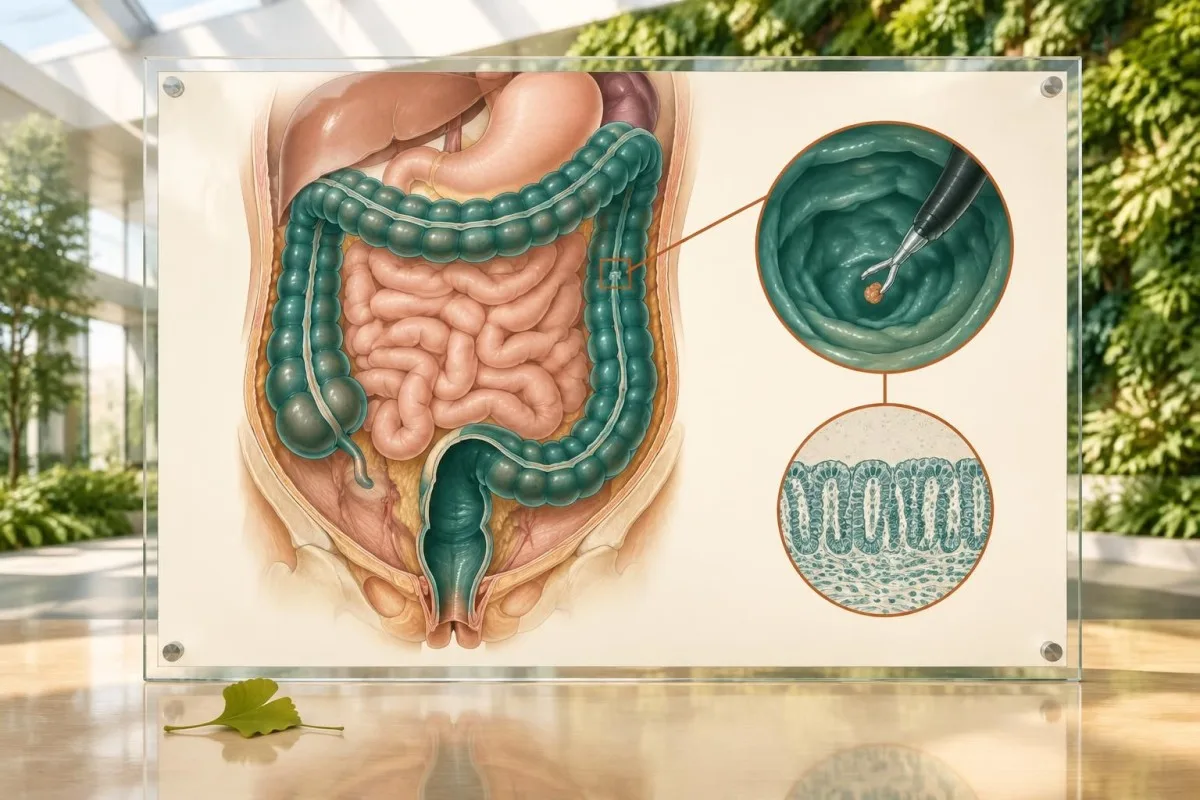
The ECCO-ESGAR diagnostic guideline recommends combining symptoms, laboratory results, stool testing, ileocolonoscopy and biopsies when evaluating suspected inflammatory bowel disease (Maaser et al., 2019). A CRP of 6 mg/L with rectal urgency may still warrant endoscopy, while CRP 80 mg/L may require urgent stabilisation before a full procedure.
Endoscopy also detects extent, which blood tests cannot grade reliably: proctitis, left-sided colitis and extensive colitis can produce overlapping CRP values. Histology may identify chronic architectural change, microscopic activity or cytomegalovirus-related findings that would alter treatment, even when the blood count is near normal.
A negative colonoscopy does not always end the workup if symptoms persist, because sampling location, preparation quality and treatment exposure affect what is seen. The diagnostic process should document medication use, stool results and the number and distribution of tissue samples rather than treating an isolated normal blood marker as decisive.
When blood results suggest severe disease or urgent care
Blood results become urgent when they combine with frequent bloody stools, fever, tachycardia, dehydration, severe pain or rapid deterioration. In acute severe ulcerative colitis, classic Truelove and Witts criteria include at least 6 bloody stools daily plus systemic features such as pulse above 90 beats per minute, temperature above 37.8°C, haemoglobin below 105 g/L or ESR above 30 mm/hour.

A haemoglobin of 101 g/L with pulse 112, temperature 38.1°C and six or more bloody stools is not a result to manage through an online interpretation alone. The combination raises concern for acute severe disease, where hospital assessment may include intravenous fluids, infection exclusion, abdominal imaging and urgent gastroenterology review.
Creatinine above a person's baseline, urea elevation, potassium below 3.0 mmol/L or lactate elevation can indicate dehydration or systemic compromise, but each result needs the clinical setting. A normal lactate of 1.3 mmol/L does not make severe colitis safe if the patient is faint, unable to drink or passing frequent blood-stained stools.
Do not wait for repeat home testing if there is heavy rectal blood loss, fainting, confusion, severe abdominal distension, persistent vomiting or inability to keep fluids down. Our explanation of coagulation test limits also clarifies that a normal PT or aPTT does not rule out gastrointestinal blood loss or determine its cause.
How to read ulcerative colitis blood-test trends
Trends are more useful than isolated ulcerative colitis blood-test values. A falling CRP, recovering albumin, stable haemoglobin and normalising platelets support improvement, but objective stool or endoscopic assessment is still needed because symptoms and mucosal activity can move at different speeds.

A CRP decline from 64 to 18 mg/L over 7 days is encouraging, but it does not prove mucosal healing; albumin may lag because its half-life is about 20 days. A haemoglobin fall from 124 to 111 g/L over the same period is a separate warning that ongoing loss or dilution may be occurring.
Kantesti is an AI blood test analyzer that compares serial biomarker patterns while preserving the distinction between inflammation, anaemia, nutrition and treatment safety. Our AI տեխնոլոգիայի ուղեցույց explains why trend interpretation can flag combinations for clinician review without converting a pattern into a diagnosis.
The most useful personal record includes sample date, symptoms, stool frequency, medication dose, recent infection, menstrual or other blood loss and whether the sample was taken during steroids. Two CRP results 48 hours apart after a viral illness do not carry the same meaning as two results 6 weeks apart during stable treatment.
Can normal blood tests rule out ulcerative colitis?
Normal blood tests cannot rule out ulcerative colitis, especially when disease is limited to the rectum or left colon. CRP may remain below 5 mg/L in active mucosal disease, and a normal haemoglobin or white-cell count says little about early, localised or intermittently active inflammation.
A patient with rectal bleeding, urgency and CRP 2 mg/L may have clinically significant proctitis even though systemic inflammation is minimal. The practical reason is anatomical: a small inflamed area may release too little signal to raise a whole-body marker, while symptoms remain locally intense.
Conversely, CRP 35 mg/L can result from pneumonia, dental infection or a strenuous inflammatory illness without any colitis. This is why a normal or abnormal result must be matched to stool studies, examination, calprotectin and endoscopy rather than used as a standalone rule-in or rule-out test.
A normal blood panel is reassuring for anaemia, kidney function and some complications, but it does not replace surveillance or a planned review. If symptoms persist for more than a few weeks, recur after treatment reduction or include blood and nocturnal diarrhoea, clinical assessment should take priority over repeated self-ordered panels.
How to use blood-test interpretation without replacing care
AI interpretation can organise laboratory patterns, but it cannot confirm ulcerative colitis or decide urgent treatment. A safe workflow uses the original report, laboratory reference intervals, dates, medicines and symptoms, then sends concerning combinations to a qualified clinician.
Kantesti is an AI blood test interpretation platform that reads results in context, including units, reference intervals and changes over time. It can help a reader identify that CRP 42 mg/L, albumin 29 g/L and haemoglobin 104 g/L form a higher-concern pattern than any one result alone, but it cannot inspect the bowel or interpret an endoscopic image.
Kantesti uses a large biomarker knowledge base to explain possible meanings and follow-up questions, not to issue a definitive inflammatory bowel disease diagnosis. Uploading a report should never delay urgent care for severe pain, fainting, heavy rectal blood loss, fever above 38°C or inability to drink.
Before sharing results, remove identifiers when appropriate and retain the original laboratory report because ranges differ between countries and analysers. A clinician needs the exact assay, collection date and medication timeline; a copied number without units, such as CRP 18, is incomplete because mg/L and mg/dL differ by a factor of 10.
What to ask after receiving ulcerative-colitis blood results
The best follow-up questions connect the result to diagnosis, disease activity, complications and next action. Ask which findings are specific, whether infection has been excluded, whether a trend matters, and whether stool testing or endoscopy is needed.
Ask whether the laboratory used CRP below 5 mg/L as its reference limit, whether ferritin is reliable in the presence of inflammation, and whether the haemoglobin pattern suggests iron, B12 or folate deficiency. These questions prevent a result such as ferritin 70 µg/L from being misread as proof that iron stores are adequate.
Ask what would trigger repeat testing: for example, a CRP rise from 4 to 25 mg/L, albumin falling below 30 g/L or potassium below 3.0 mmol/L may each change urgency, but thresholds depend on symptoms and baseline values. Also ask whether the sample was taken before or after steroids, antibiotics, biologic dosing or intravenous fluids.
Kantesti is an AI-powered blood test analysis tool that can help prepare a concise list of result-specific questions for an appointment, while the Բժշկական խորհրդատվական խորհուրդ explains the clinical oversight principles behind our health content. Bring the complete report and symptom timeline; do not bring only highlighted abnormal values.
Հաճախ տրվող հարցեր
Can a blood test confirm ulcerative colitis?
No blood test confirms ulcerative colitis by itself. CRP above 5 mg/L, ESR above the local reference range, anaemia or platelets above 450 × 10⁹/L may support active inflammation or complications, but these results are not specific. Diagnosis usually combines symptoms, stool testing, colonoscopy and tissue examination, because blood tests cannot show the distribution or microscopic pattern of bowel disease.
What CRP level suggests an ulcerative colitis flare?
A CRP above 5 mg/L is above the common adult reference limit, and values above 10 mg/L often indicate clinically meaningful inflammation, but no CRP cutoff proves an ulcerative colitis flare. CRP can rise with infection, injury or other inflammatory conditions, while active localised colitis can occur with CRP below 5 mg/L. Clinicians interpret CRP alongside stool frequency, faecal calprotectin, infection testing and examination.
What blood test shows anaemia from ulcerative colitis?
A full blood count shows anaemia, while ferritin and transferrin saturation help identify iron depletion. Haemoglobin below 130 g/L in many adult men or below 120 g/L in non-pregnant adult women meets common anaemia thresholds, and transferrin saturation below 20% supports insufficient available iron. Ferritin below 30 µg/L commonly indicates depleted stores, but inflammation can raise ferritin, so a value below 100 µg/L may still be compatible with iron deficiency in active inflammatory bowel disease.
Can ulcerative colitis be active with normal CRP?
Yes, ulcerative colitis can be active with a normal CRP, particularly when inflammation is limited to the rectum or left colon. A CRP below 5 mg/L indicates a low systemic inflammatory signal but does not prove mucosal healing. Persistent urgency, diarrhoea or rectal blood may require faecal calprotectin, stool infection testing or endoscopy even when CRP and white-cell count are normal.
Which blood tests are checked during an ulcerative colitis flare?
Common flare assessments include a full blood count, CRP, ESR, electrolytes, kidney function, albumin, liver tests and iron studies. Haemoglobin below 105 g/L, albumin below 30 g/L, potassium below 3.0 mmol/L or creatinine rising above baseline can indicate complications that need prompt evaluation, although each threshold requires clinical context. Stool pathogen testing and faecal calprotectin are also important because blood tests cannot reliably distinguish infection from intestinal inflammation.
Is a high platelet count a sign of ulcerative colitis?
A platelet count above 450 × 10⁹/L can accompany active ulcerative colitis, but it is a nonspecific reactive finding. Iron deficiency, infection, surgery and other inflammatory disorders can produce the same result, so platelets do not diagnose colitis. A high count becomes more informative when it falls alongside CRP and symptoms after treatment, or when it appears with low ferritin and microcytosis suggesting iron deficiency.
Ստացեք ձեր արյան անալիզի արդյունքների բացատրությունը
Վերբեռնեք ձեր լաբորատոր հաշվետվությունը, և Kantesti-ի AI-ն վայրկյանների ընթացքում պարզ լեզվով կբացատրի յուրաքանչյուր կենսամարկեր։ Օգտագործում է ավելի քան 2 միլիոն մարդ ամբողջ աշխարհում։.
Հղումներ
- Klein, T., Mitchell, S., & Weber, H. (2026). Երկաթի հետազոտությունների ուղեցույց․ TIBC, երկաթի հագեցվածություն և կապելու ունակություն։. Kantesti AI բժշկական հետազոտություն։. ԴՕԻ
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTT-ի նորմալ միջակայքը․ D-Dimer-ի և Protein C-ի՝ արյան մակարդման ուղեցույց։. Kantesti AI բժշկական հետազոտություն։. ԴՕԻ
- Rubin DB et al. (2019). ACG Clinical Guideline: Ulcerative Colitis in Adults. The American Journal of Gastroenterology։. ԴՕԻ PubMed
- Maaser C et al. (2019). ECCO-ESGAR Guideline for Diagnostic Assessment in IBD Part 1: Initial Diagnosis, Monitoring of Known IBD, Detection of Complications. Journal of Crohn's and Colitis. ԴՕԻ PubMed
- Turner D et al. (2021). STRIDE-II: An Update on the Selecting Therapeutic Targets in Inflammatory Bowel Disease Initiative of the International Organization for the Study of IBD. Gastroenterology։. ԴՕԻ PubMed
- 2 միլիոն+Վերլուծված թեստեր
- 127+Երկրներ
- 100+Լեզուներ
Բժշկական թիմի մասին


E-E-A-T վստահության ազդանշաններ
Փորձառություն
Բժշկի կողմից ղեկավարվող կլինիկական վերանայում՝ լաբորատոր մեկնաբանության աշխատանքային հոսքերի համար։.
Մասնագիտություն
Լաբորատոր բժշկության կենտրոնացում՝ այն բանի վրա, թե ինչպես են բիոմարկերները դրսևորվում կլինիկական համատեքստում։.
Հեղինակություն
Բժշկական գրախոսությունը՝ դոկտոր Թոմաս Քլայնի կողմից, դոկտոր Սառա Միտչելի և պրոֆ. դոկտոր Հանս Վեբերի մասնակցությամբ։.
Հուսալիություն
Ապացույցների վրա հիմնված մեկնաբանություն՝ հստակ հետագա քայլերի ուղիներով՝ ահազանգերը նվազեցնելու համար։.




Բժշկական հրաժարում պատասխանատվությունից
Այս հոդվածը միայն կրթական նպատակների համար է և չի հանդիսանում բժշկական խորհրդատվություն։ Ախտորոշման և բուժման որոշումների համար միշտ խորհրդակցեք որակավորված բուժաշխատողի հետ։.
Հրապարակված · Կապ հաստատել խմբագրական թիմի հետ
Հրատարակված է Kantesti Ltd-ի կողմից, գրանցված Անգլիայում և Ուելսում, ընկերության համար. 17090423, Լոնդոն, Միացյալ Թագավորություն։.
